


 Chat with AI
Exam 1: Medicine

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 26-year-old woman is brought to the emergency department after a near-syncope episode. The patient began feeling dizzy and lightheaded while at work at a skilled nursing facility where she is a patient care assistant. She had no chest pain, palpitations, or dyspnea. A nearby coworker helped her to the ground. The patient has had chronic diarrhea with 10-12 nonbloody, watery bowel movements per day, which are often associated with abdominal cramping. The diarrhea occasionally awakens her at night. Temperature is 37.1 C (98.8 F), blood pressure is 112/71 mm Hg supine and 91/50 mm Hg upright, and pulse is 94/min. Heart sounds are normal without murmur. Lung auscultation is unremarkable. The abdomen is soft, nondistended, and without tenderness. Bowel sounds are normal. Stool guaiac is negative. Laboratory testing shows hypokalemia and metabolic alkalosis. Intravenous fluids and electrolyte supplements are started. Colonoscopy reveals areas of dark brown mucosal pigmentation in the proximal colon. Which of the following findings would also be expected in this patient?
(Multiple Choice)
4.8/5  (77)
(77) A 28-year-old woman, gravida 1 para 0, at 30 weeks gestation comes to the office due to burning pain in her right hand. The pain is mild and intermittent but worse at night and is felt mainly over the first, second, and third digits. Shaking the hands or letting them hang down briefly relieves the pain. There is no associated neck or forearm pain. Her pregnancy has otherwise been uncomplicated. The patient does not use tobacco, alcohol, or illicit drugs. Vital signs are normal. Fetal heart tones are 160/min. On examination, there is no thenar or hypothenar atrophy, and thumb opposition is normal. Percussion over the volar aspect of the wrist reproduces the pain. Which of the following is the best next step in management of this patient?
(Multiple Choice)
5.0/5 (71)
(71) A 31-year-old primigravida at 7 weeks gestation is brought to the emergency department by her husband due to vaginal bleeding and lower abdominal pain. The bleeding began 4 hours earlier, and the patient has saturated 3 perineal pads in that time. Her abdominal cramping has become progressively more severe and unresponsive to acetaminophen. She has no fevers, chills, or abnormal vaginal discharge. The patient was treated at age 18 for Chlamydia trachomatis cervicitis. Her surgical history includes a loop electrode excision procedure for high-grade cervical intraepithelial neoplasia, but she has had normal Pap tests since. The patient takes a prenatal vitamin daily and does not use tobacco, alcohol, or illicit drugs. Temperature is 37 C (98.7 F), blood pressure is 100/76 mm Hg, pulse is 112/min, and respirations are 14/min. Pelvic examination reveals blood clots in the vaginal vault and active bleeding from a dilated cervix. A bimanual examination demonstrates a 6-week-size tender uterus. Ultrasound reveals a gestational sac in the lower segment of the uterus, a simple cyst in the right ovary, and free fluid in the posterior cul-de-sac. Which of the following is the most likely diagnosis of this patient?
(Multiple Choice)
4.9/5 (79)
(79) A 53-year-old homeless man comes to the emergency department due to several days of shortness of breath and productive cough. A month ago, the patient was evaluated for dysphagia and was found to have Candida esophagitis. He received nystatin but refused any further workup and left against medical advice. The patient uses cocaine and intravenous heroin. Temperature is 38.8 C (101.8 F), blood pressure is 121/72 mm Hg, pulse is 124/min and regular, and respirations are 22/min. Oxygen saturation is 89% on 2 L/min of oxygen by nasal cannula. He is awake, alert, and in mild respiratory distress. There are extensive white plaques over the oral mucosa. A 2/6 midsystolic murmur is heard at the left upper sternal border. Lung auscultation is remarkable for faint, bilateral crackles. There is no jugular venous distension or lower extremity edema. Which of the following is the most likely underlying mechanism responsible for this patient's hypoxemia?
(Multiple Choice)
4.9/5 (77)
(77) A 54-year-old woman comes to the physician due to worsening epigastric pain over the last 2 months. The pain, which is worse at night, was initially intermittent but is now somewhat constant and radiates to the back. She has lost 6.8 kg (15 lb) over the past 3 months. The patient reports no change in the color of stools or urine. Two years ago, she was diagnosed with idiopathic chronic pancreatitis and started on pancreatic enzyme replacement therapy. The patient initially had diarrhea, epigastric discomfort, and flatulence that improved with pancreatic enzymes. She does not use tobacco, alcohol, or illicit drugs. Vital signs are within normal limits. Her BMI is 21 kg/m2. There is no jaundice. Abdominal examination demonstrates mild epigastric tenderness on deep palpation. Laboratory results are as follows:  Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.8/5 (84)
(84) A 38-year-old woman, gravida 5 para 4, at 10 weeks gestation comes to the office for an initial prenatal visit. She feels well and has no concerns. The patient takes prenatal vitamins and has a history of type 2 diabetes mellitus that is currently managed with insulin. She has no vaginal bleeding or pelvic pain. The patient reports no urinary urgency, hematuria, or dysuria. She does not use tobacco, alcohol, or illicit drugs. Temperature is 36.7 C (98.1 F) and blood pressure is 130/80 mm Hg. BMI is 29 kg/m2. The fetal heart rate is 155/min on Doppler ultrasound. Physical examination shows no abnormalities. A clean-catch urine culture from today's visit grows >100,000 colony-forming units/mL of Escherichia coli. Which of the following is the best next step in management?
(Multiple Choice)
5.0/5 (98)
(98) A 27-year-old man with type 1 diabetes mellitus that was diagnosed 15 years ago comes to the emergency department due to abdominal pain, nausea, and vomiting. The patient takes insulin glargine at night and insulin lispro before meals 3 times a day, but has not been compliant with his insulin injections. He stopped taking his insulin for the last 2 days due to not feeling well and inability to eat. The patient's medical history is otherwise unremarkable. He does not use tobacco or alcohol. Temperature is 36 C (96.8 F), blood pressure is 102/60 mm Hg, pulse is 110/min, and respirations are 26/min. The patient appears lethargic and dehydrated. The lungs are clear to auscultation. The abdomen is soft, nontender, and nondistended. Laboratory results are as follows:  Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.7/5 (84)
(84) A 58-year-old man comes to the emergency department due to a persistent, painful erection that has lasted 8 hours. His other medical conditions include ulcerative colitis, kidney stones, depression, insomnia, hypertension, drug-induced diabetes, obesity, and hypercholesterolemia. The patient does not use tobacco, alcohol, or recreational drugs. He takes prednisone, mesalamine, mirtazapine, insulin, trazodone, 6-mercaptopurine, simvastatin, glyburide, and enalapril. He has no known drug allergies. Vital signs are stable. Examination confirms the patient's chief complaint but is otherwise unremarkable. Which of the following medications is the most likely cause of his condition?
(Multiple Choice)
4.9/5 (78)
(78) A 32-year-old woman comes to the emergency department due to chest pain and shortness of breath that woke her up this morning. The chest pain is sharp and worsens with inspiration. The patient has had no fever or cough but has had worsening right leg swelling over the past several days. Review of systems is positive for myalgias, joint pains, and facial rash brought on by sun exposure. Medical history includes 2 miscarriages at 12 and 16 weeks gestation. She takes no medications and does not use tobacco, alcohol, or illicit drugs. Temperature is 37.2 C (99 F), blood pressure is 152/86 mm Hg, pulse is 98/min, and oxygen saturation is 95% on room air. Physical examination shows clear lungs, normal heart sounds, and no abdominal organomegaly. The right lower extremity is swollen and tender to touch. CT angiography of the chest reveals pulmonary emboli. Which of the following additional laboratory findings is most likely to be present in this patient?
(Multiple Choice)
5.0/5 (90)
(90) A middle-aged woman is found wandering the streets with an abnormal gait. She is brought to the hospital by police officers. When asked for identification, the patient mumbles incoherently. She is not oriented to time or place. Her temperature is 36.2 C (97.3 F), blood pressure is 160/100 mm Hg, pulse is 100/min, and respirations are 18/min. BMI is 17 kg/m2. Head and neck examination shows bitemporal wasting and dry mucous membranes. The pupils are 3 mm bilaterally and react slowly to light. Her neck is supple, and she moves all extremities equally. Deep-tendon reflexes are symmetrical bilaterally. Which of the following is the best initial treatment for this patient?
(Multiple Choice)
4.9/5 (78)
(78) A 42-year-old woman comes to the emergency department with extensive, painful skin lesions. She is unable to eat or drink due to painful blistering and ulceration in her mouth and throat. The rash was preceded by fever, headache, sore throat, cough, nausea, and vomiting. She was treated for acute cystitis with trimethoprim-sulfamethoxazole 5 days ago, but her history is otherwise unremarkable. Temperature is 38.3 C (101 F), blood pressure is 95/60 mm Hg, pulse is 110/min, and respirations are 14/min. On examination, the skin is hot and tender with widespread confluent erythematous macules that cover most of the visible skin surface on her entire body. The oral mucosa shows blistering and erosions. A representative photograph from her back is shown below. 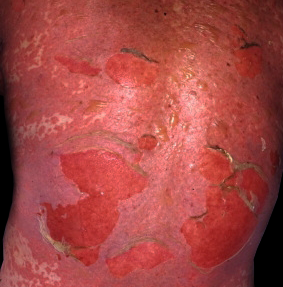 What is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (60)
(60) A 28-year-old man comes to the clinic for routine follow-up for type 1 diabetes mellitus. The patient was diagnosed 11 years ago and takes insulin as prescribed. He has no new concerns since his last visit. Temperature is 37.1 C (98.8 F), blood pressure is 124/76 mm Hg, and pulse is 72/min. Physical examination shows no evidence of peripheral neuropathy. Serum creatinine is 0.8 mg/dL and hemoglobin A1c is 7.4%. Urine albumin/creatinine ratio is 280 mg/g (increased from 220 mg/g a year ago). Pharmacologic therapy that accomplishes which of the following is most likely to slow the progression of renal disease in this patient?
(Multiple Choice)
4.8/5 (83)
(83) A 38-year-old man comes to the office due to progressive shortness of breath and cough with mucoid sputum over the past 6 months. His shortness of breath is worse with exertion. The patient has no chest pain, weight loss, or night sweats. Past medical history is otherwise unremarkable, and he takes no medications. He smoked cigarettes for 5 years but quit 13 years ago. The patient does not use alcohol or illicit drugs. Temperature is 36.7 C (98 F), blood pressure is 128/78 mm Hg, pulse is 78/min, and respirations are 16/min. His pulse oximetry is 96% on room air. BMI is 32 kg/m2. Breath sounds are decreased at the bases, and there are no crackles or wheezes. Heart sounds are normal. There is no jugular venous distension or peripheral edema. Chest imaging reveals bilateral basilar hyperlucency. Complete blood count and basic metabolic panel are normal. Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.7/5 (85)
(85) A 5-year-old boy is brought to the office for an annual physical examination. The child has been healthy and takes no medications. His maternal uncle died from a myocardial infarction at age 56. Height and weight are at the 50th percentile. Temperature is 36.7 C (98 F), blood pressure is 95/53 mm Hg, pulse is 92/min, and respirations are 20/min. He is well-appearing and alert. Auscultation of the chest shows a grade II systolic ejection murmur at the left lower sternal border. It is best heard when the child is lying down and decreases with standing. No rubs or gallops are heard. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.7/5 (75)
(75) A 65-year-old woman comes to the emergency department due to a burn on her left hand. She lost her grip when pouring a large pot into the kitchen sink, spilling boiling water onto her hand. Medical history includes obesity, hypertension, and well-controlled type 2 diabetes mellitus. The patient is up to date on vaccinations. Blood pressure is 136/84 mm Hg and pulse is 82/min. There is erythema of the skin on the palmar surface of the left hand and distal forearm; the area is dry, has no blisters, and has good capillary refill but is painful when touched. Following cleansing of the area, ointment and a clean dressing are applied. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (76)
(76) A prospective cohort study revealed a strong positive association between smoking and liver cirrhosis (relative risk = 2.8). The researchers then divided the cohort into two groups: alcohol consumers and non-consumers. Subsequent statistical analysis did not reveal any association between smoking and liver cirrhosis with either group. The scenario described above is an example of which of the following?
(Multiple Choice)
4.9/5 (72)
(72) A 44-year-old man comes to the office due to persistent cough and dyspnea on exertion for approximately the last 3 months. He has had no fever, chills, rhinorrhea, or sputum production. Over the past year, the patient has had progressively worsening shortness of breath and is unable to sleep lying flat. He has no chest pain or diaphoresis but has had palpitations previously. The patient does not use tobacco or alcohol. He moved to the United States from Southeast Asia 10 years ago. On examination, the patient is alert but in mild distress. Temperature is 36.7 C (98 F), blood pressure is 110/70 mm Hg, and pulse is 100/min. BMI is 34 kg/m2. Heart sounds are distant due to body habitus. The lungs demonstrate crackles on auscultation. Chest x-ray reveals an enlarged cardiac silhouette with vascular congestion. The left main stem bronchus appears to be elevated. There is no other visible lung pathology. ECG shows an irregularly irregular rhythm. Which of the following is the most likely cause of this patient's presentation?
(Multiple Choice)
4.9/5 (82)
(82) A 76-year-old woman comes to the office due to headache. For the last week, she has had a dull, right-sided headache associated with malaise; her symptoms are unlike any headache she has had in the past. Medical history includes type 2 diabetes mellitus, hypertension, and coronary artery disease. The patient smokes 2 packs of cigarettes a day and does not drink alcohol. Vital signs are normal. Examination shows normal extraocular movement and funduscopic inspection. There is normal, pain-free range of motion at the cervical spine and no focal cervical or cranial tenderness. Cranial nerve examination is normal. Cardiac examination is also normal, and the feet are warm and dry. Erythrocyte sedimentation rate is 55 mm/hr (normal: ≤29). Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (77)
(77) A 25-year-old woman is evaluated for occasional episodes of palpitations. She describes the episodes as a sudden, abrupt onset of fast and regular heartbeats that feel like "her heart is racing in her chest." The episodes are commonly unprovoked and are not related to exertion. During one episode, her blood pressure was recorded as 100/60 mm Hg and her heart rate was 185/min and regular. She has no significant past medical history and does not take any medications. She has no family history of heart disease. Physical examination is unremarkable, including no heart murmurs or additional sounds. She also reports that she has been self-treating by immersing her face in cold water during the palpitation episodes. Generally, she says, cold-water immersion relieves her symptoms abruptly within several minutes. This maneuver terminates the palpitations by directly altering which of the following?
(Multiple Choice)
4.8/5 (73)
(73) A 34-year-old woman, gravida 1 para 0, comes to the office at 38 weeks gestation due to increasing shortness of breath. The patient says that the pregnancy is causing too much discomfort and requests delivery. She cannot find a comfortable position to sleep in, and after walking several steps she needs to stop to catch her breath. The patient's pregnancy has been uncomplicated, and she has no significant medical conditions. She does not use tobacco or alcohol. Blood pressure is 132/85 mm Hg and pulse is 112/min and regular. An S3 is present on cardiac auscultation. A new grade III/VI holosystolic murmur is heard at the apex. Pitting edema is present over the lower extremities to just below the knees. Urinalysis shows trace protein. ECG demonstrates sinus tachycardia. Which of the following is the best next step in management of this patient?
(Multiple Choice)
5.0/5 (80)
(80) Showing 921 - 940 of 1702
 Prev
- 1
- ...
- 2
- ...
- 3
- ...
- 4
- ...
- 5
- ...
- 6
- ...
- 7
- ...
- 8
- ...
- 9
- ...
- 10
- ...
- 11
- ...
- 12
- ...
- 13
- ...
- 14
- ...
- 15
- ...
- 16
- ...
- 17
- ...
- 18
- ...
- 19
- ...
- 20
- ...
- 21
- ...
- 22
- ...
- 23
- ...
- 24
- ...
- 25
- ...
- 26
- ...
- 27
- ...
- 28
- ...
- 29
- ...
- 30
- ...
- 31
- ...
- 32
- ...
- 33
- ...
- 34
- ...
- 35
- ...
- 36
- ...
- 37
- ...
- 38
- ...
- 39
- ...
- 40
- ...
- 41
- ...
- 42
- ...
- 43
- ...
- 44
- ...
- 45
- ...
- 46
- ...
- 47
- ...
- 48
- ...
- 49
- ...
- 50
- ...
- 51
- ...
- 52
- ...
- 53
- ...
- 54
- ...
- 55
- ...
- 56
- ...
- 57
- ...
- 58
- ...
- 59
- ...
- 60
- ...
- 61
- ...
- 62
- ...
- 63
- ...
- 64
- ...
- 65
- ...
- 66
- ...
- 67
- ...
- 68
- ...
- 69
- ...
- 70
- ...
- 71
- ...
- 72
- ...
- 73
- ...
- 74
- ...
- 75
- ...
- 76
- ...
- 77
- ...
- 78
- ...
- 79
- ...
- 80
- ...
- 81
- ...
- 82
- ...
- 83
- ...
- 84
- ...
- 85
- ...
- 86
- ...
- Next

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)