


 Chat with AI
Exam 1: Medicine

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 48-year-old woman comes to the emergency department due to a day of fever and skin rash. Eight months ago, the patient was found to have an adnexal mass and elevated CA-125 level. She underwent a hysterectomy with bilateral salpingo-oophorectomy and lymph node dissection. Histopathology showed serous carcinoma of the ovary, and she received adjuvant chemotherapy treatment. A recent imaging study revealed metastatic lesions in the liver, and a new chemotherapy regimen was administered a week ago. Temperature is 38.8 C (102 F), blood pressure is 110/60 mm Hg, and pulse is 114/min. Cardiopulmonary auscultation reveals no abnormalities other than tachycardia. The abdomen is nontender, and the surgical scars are well healed. The trunk has several indurated, nontender macules and pustules. Some of the lesions have become gangrenous ulcers. Complete blood count is as follows:  Which of the following is the most likely cause of this patient's skin lesions?
 (Multiple Choice)
4.7/5  (71)
(71) A 60-year-old woman comes to the emergency department due to progressive pain, swelling, and redness of her left leg for 4 days. She has had no obvious trauma or insect bites to that area. Two months ago, the patient had a hysterectomy for endometrial hyperplasia. She also has a history of rheumatoid arthritis and gastroesophageal reflux disease. She does not use tobacco, alcohol, or illicit drugs. Temperature is 39.4 C (102.9 F), blood pressure is 130/80 mm Hg, pulse is 106/min, and respirations are 18/min. The patient appears well. Her left anterior leg is swollen, erythematous, tender, and warm to the touch over a 10x5 cm region, as shown in the exhibit. 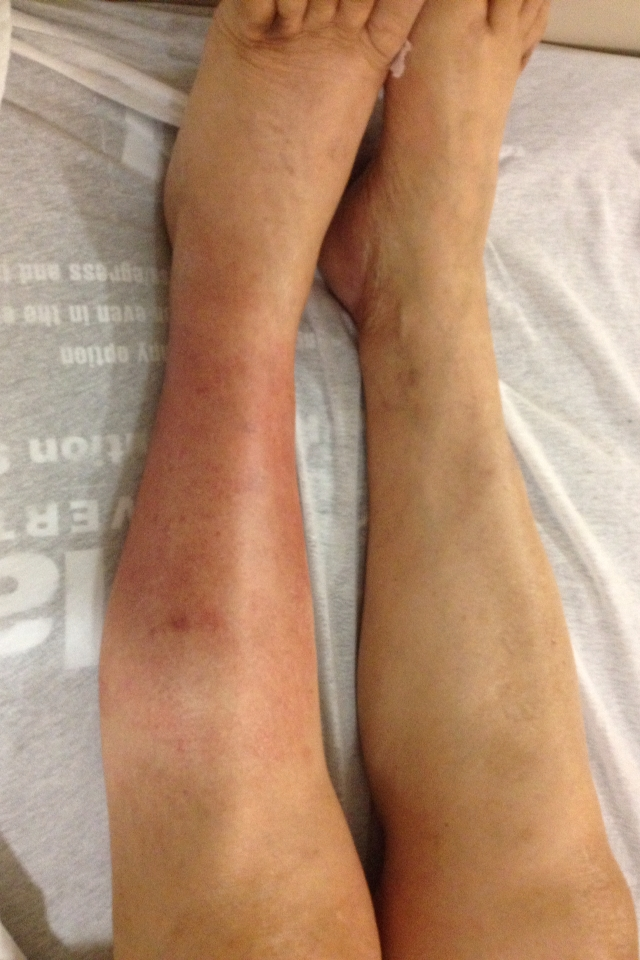 The erythema is present throughout the affected area and has a flat border. There is no overlying crepitus or bullae. The left thigh and right leg are normal in appearance. The remainder of the examination is normal. Laboratory results are as follows:
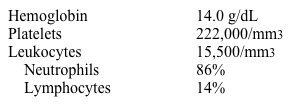 Which of the following is the most likely diagnosis?
The erythema is present throughout the affected area and has a flat border. There is no overlying crepitus or bullae. The left thigh and right leg are normal in appearance. The remainder of the examination is normal. Laboratory results are as follows: Which of the following is the most likely diagnosis? (Multiple Choice)
4.9/5 (67)
(67) A 24-year-old woman comes to the clinic after 3 weeks of heat intolerance and increased appetite. Despite increased caloric intake, she has lost weight. The patient's medical history is insignificant, and she takes no prescription or over-the-counter medications. She does not use tobacco or illicit drugs, and consumes alcohol only on rare occasions. The patient's last menstrual period was 3 days ago and was unusually light. Temperature is 37.2 C (99 F), blood pressure is 130/75 mm Hg, pulse is 110/min and regular, and respiratory rate is 14/min. On examination, the thyroid gland is mildly enlarged, mobile, and nontender. Cranial nerve examination is normal, although there is mild lid lag. Laboratory results are as follows:  Radioactive iodine uptake is <5% (normal: 8%-25%). The thyroid gland is not visualized on thyroid scan. Which of the following is the most likely diagnosis for this patient?
 (Multiple Choice)
4.8/5 (69)
(69) A 17-year-old boy comes to the office due to leg pain in his left thigh for over a year. He first noticed the pain only while running, but it became more frequent and more intense even after walking short distances. For the last 3 weeks, the pain has occurred even while sitting down or lying in bed. He has taken acetaminophen and ibuprofen with no relief. The patient has a history of sickle cell disease and has previously been hospitalized for back, chest, and leg pain, but he says that the current pain is different. Three weeks ago, he had an upper respiratory illness that lasted for 3 days and resolved spontaneously. He does not use tobacco, alcohol, or illicit drugs. Temperature is 36.7 C (98 F), blood pressure is 110/70 mm Hg, and pulse is 78/min. Height and weight are at the 10th percentile for age. Physical examination demonstrates an alert, uncomfortable adolescent. There is pain on flexion, extension, and rotation of the left hip, with restricted range of motion. Distal pulses and deep tendon reflexes are normal. Gait is notable for a slight limp. Complete blood count shows normocytic anemia with a normal white blood cell count. Which of the following would most likely explain this patient's symptoms?
(Multiple Choice)
4.8/5 (62)
(62) A 22-year-old woman comes to the office due to a 6-month history of progressive pain and swelling of the hands. She also reports bluish discoloration of the fingers when exposed to the cold and frequent episodes of food getting stuck in her chest while swallowing. She has no prior medical problems and takes no medications. The patient does not use tobacco, alcohol, or illicit drugs. Temperature is 37.1 C (98.8 F), blood pressure is 120/80 mm Hg, and pulse is 76/min. There is an erythematous rash over the malar area and nasal bridge. The skin of her hands appears shiny and thick, with small ulcers at the fingertips. The hand joints and wrists are swollen and tender. Laboratory results are as follows:  This patient most likely will exhibit clinical manifestations of which of the following conditions in the future?
 (Multiple Choice)
4.9/5 (79)
(79) A 23-year-old woman comes to the office due to pain in the right forefoot. The pain started 6 weeks ago and has worsened over the past week. She reports no trauma or inciting event. The pain prevents the patient from doing her usual exercise; she normally runs 3 times a week and occasionally goes hiking. The patient takes no medications and does not use tobacco, alcohol, or illicit drugs. Her last menstrual period was 3 weeks ago, and she is not sexually active. Temperature is 37 C (98.6 F), blood pressure is 100/60 mm Hg, pulse is 70/min, and respirations are 12/min. BMI is 22 kg/m2. Physical examination of the right foot elicits a clicking sensation when the third and fourth metatarsal heads are squeezed together; this also produces a burning pain over the plantar surface of the foot. The remainder of the examination is unremarkable. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
5.0/5 (85)
(85) A 71-year-old man is brought to the emergency room due to sharp chest pain for 2 hours. The pain is not related to exertion but is worse with deep breaths. He has not done any unusual activity lately. The patient has a history of advanced chronic kidney disease and is preparing to initiate chronic dialysis soon. His other medical problems include type 2 diabetes mellitus, hypertension, and lumbar spinal stenosis. The patient does not use tobacco or illicit drugs but consumes 1 alcoholic drink with dinner on most nights. Temperature is 37.7 C (99.8 F), blood pressure is 160/98 mm Hg in both arms, pulse is 98/min, and respirations are 20/min. When the patient is placed in a supine position during the examination, he experiences chest pain that appears to improve when he sits back up. A diastolic sound with a squeaking quality is heard at the left sternal border. Breath sounds are normal. ECG shows nonspecific T wave abnormalities. Chest x-ray is normal. Cardiac enzymes are normal. Laboratory studies show a blood urea nitrogen level of 68 mg/dL and a serum creatinine of 5.3 mg/dL. Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5 (77)
(77) A 54 year-old-man comes to the office due to a 3-day history of fever, malaise, and loss of appetite. The patient has not experienced weight loss, headache, cough, dyspnea, rash, vomiting, or bloody stools. Medical history is unremarkable, and he takes no medications. He lives in an overcrowded homeless shelter, drinks several beers a day, and intermittently smokes marijuana but denies other illicit drug use. The patient is not sexually active and has not traveled outside of the United States. Family history is unremarkable. Temperature is 38.1 C (100.6 F), blood pressure is 135/80 mm Hg, and pulse is 85/min. Scleral icterus is absent. Cardiopulmonary and skin examinations are unremarkable. The abdomen is soft and nondistended. Hepatomegaly is present. Laboratory results are as follows:  Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.8/5 (71)
(71) A 32-year-old woman with a 13-year history of type 1 diabetes mellitus comes to the hospital with palpitations and shortness of breath. She has had these symptoms for the last several months, but they have worsened recently. The patient also has experienced anxiety, poor sleep, and unintentional weight loss that she attributes to drinking too much coffee at work. She drinks 2 8-oz cups of coffee daily and a glass of red wine on weekends. The patient's diabetes is managed with a regimen of insulin glargine and insulin lispro, and she has had good glycemic control in the past. However, in the last few months she has had rising home glucose readings and has required increasing insulin doses to maintain control. The patient has also had irregular menstrual periods, for which she was started on a combination estrogen-progesterone oral contraceptive pill 2 months ago. CT scan of the chest with contrast performed in the emergency department shows no evidence of pulmonary embolism, and the patient is admitted for additional evaluation. Following admission, she develops nausea and vomiting. Six hours later, the patient is found to be confused, diaphoretic, and agitated. Her temperature is 38.9 C (102 F), blood pressure is 145/65 mm Hg, and pulse is 154/min. The chest is clear to auscultation. Examination of skin and abdomen is unremarkable. Laboratory results are as follows: 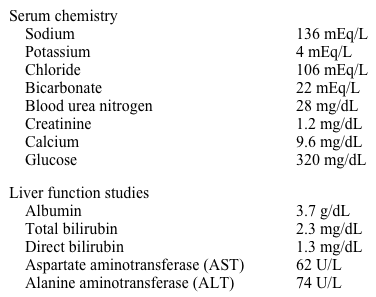 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.8/5 (84)
(84) A 65-year-old man comes to the office due to nausea, abdominal bloating, and early satiety for the past several months. He has had no heartburn or epigastric pain but does have occasional vomiting. The patient has a long-standing history of type 2 diabetes mellitus complicated by retinopathy, for which he takes basal-bolus insulin. Over the past 2 months, he has had several hypoglycemic episodes after meals despite decreases in premeal insulin dosage. Vital signs are within normal limits. On physical examination, the abdomen is soft and nontender with normal bowel sounds. Which of the following would be most helpful in treating this patient's condition?
(Multiple Choice)
4.8/5 (79)
(79) An 80-year-old woman comes to the office for evaluation of a skin lesion. She has a black nodule on her back that has been present "for quite a while." The nodule has occasional associated itching, but no pain, bleeding, or recent change in appearance. Medical history is notable for hypertension, hypothyroidism, and mild dementia. The patient lives in an assisted living facility and does not use tobacco or alcohol. On examination, there is a raised nodule with a rubbery texture and oily surface, as shown in the image below. 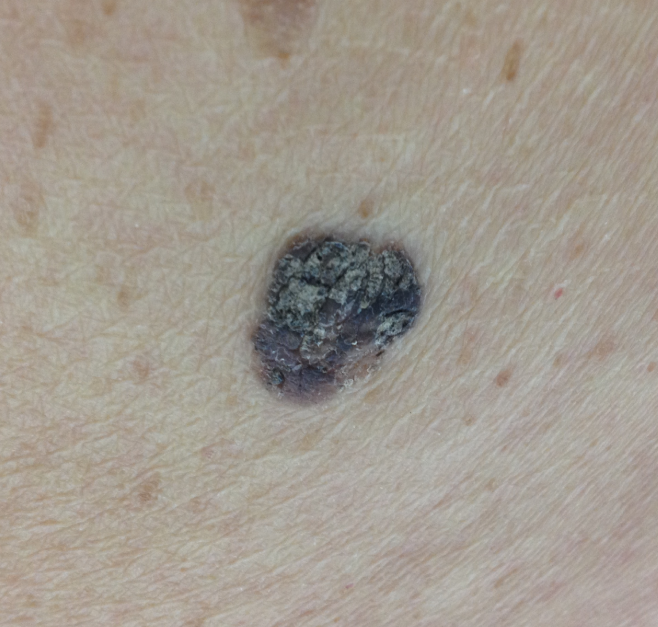 What is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (89)
(89) A 23-year-old woman comes to the office due to fatigue, anxiety, and difficulty sleeping over the last several months. The patient has used melatonin as a sleep aid but with no benefit. Medical history is remarkable only for menorrhagia, for which she takes a combination estrogen/progesterone contraceptive pill. Her mother has hypothyroidism and hypertension. The patient occasionally smokes marijuana but does not use tobacco or alcohol. Blood pressure is 120/78 mm Hg and pulse is 82/min. BMI is 18.8 kg/m2. Examination of the neck shows a normal-size thyroid gland without nodules. Serum TSH is 1.5 μU/mL and total T4 is 15 µg/dL. Which of the following is the most likely explanation of this patient's laboratory findings?
(Multiple Choice)
4.7/5 (66)
(66) A 53-year-old man comes to the office due to a 3-day history of right leg swelling and pain. He has had no chest pain or dyspnea. The patient describes himself as healthy, and his last visit to the doctor was 10 years ago. He has had no weight loss or abdominal pain. The patient smokes and has a 30-pack-year history. He has an active lifestyle and has not recently traveled. The patient's mother died of breast cancer, and his father has congestive heart failure. Temperature is 37 C (98.6 F), blood pressure is 140/80 mm Hg, pulse is 70/min, and respirations are 14/min. Oxygen saturation is 97% on room air. Normal vesicular breath sounds and cardiac sounds are heard on chest auscultation. Abdominal examination is unremarkable. The right leg is swollen and tender up to midthigh. Results of complete blood cell count and coagulation studies are within normal limits. Duplex ultrasonography demonstrates incompressible popliteal and femoral veins, and anticoagulation is started immediately. Chest x-ray is unremarkable. Which of the following is most appropriate in evaluation of this patient's current condition?
(Multiple Choice)
4.8/5 (72)
(72) A 46-year-old man comes to the office for follow-up. The patient was diagnosed with HIV 10 years ago and has had episodes of pneumocystis pneumonia, cryptococcal meningitis, and oropharyngeal candidiasis. He has been treated with several different antiretroviral combinations due to drug resistance from medication nonadherence. Over the past year, he notes a sensation of numbness and pinpricks in his feet, which has now progressed proximally up his lower legs. Vital signs are within normal limits. There is loss of sensation to touch, pain, and temperature over the distal legs and feet bilaterally. Motor strength is intact, but ankle jerk reflex is decreased bilaterally. Cranial nerve examination is normal, and there are no signs of meningeal irritation. Blood cell counts, liver and renal function tests, and fasting plasma glucose are within normal limits. CD4 count is 180/mm3. In addition to counseling about the importance of adherence to antiretroviral therapy, which of the following is the most appropriate treatment for this patient's current symptoms?
(Multiple Choice)
4.7/5 (92)
(92) An 80-year-old woman is brought to the emergency department due to diarrhea. The patient has advanced Alzheimer dementia and is cared for by her daughter at home. Her daughter reports that the patient has had 6-8 nonbloody, watery bowel movements a day for the past several days. The patient has had multiple hospitalizations for similar symptoms in the past 6 months; in each case, evaluation was negative for infection, and symptoms resolved within a few days. Home medications include donepezil and memantine. Temperature is 37 C (98.6 F), blood pressure is 110/70 mm Hg, pulse is 104/min, and respirations are 18/min. Physical examination shows dry mucous membranes. Heart and lung sounds are normal. The abdomen is soft and nontender. Laboratory evaluation shows hypokalemia and metabolic alkalosis. C-reactive protein and fecal calprotectin are unremarkable. The patient is hospitalized, and intravenous fluids and potassium replacement are begun. Colonoscopy shows dark brown mucosal pigmentation in the proximal colon but is otherwise unremarkable. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (81)
(81) A 27-year-old woman comes to the office due to worsening generalized weakness. The patient has also had occasional palpitations, muscle cramps, abdominal bloating, and constipation. She reports no chronic medical conditions, but 6 months ago she was hospitalized due to bloody emesis and was found to have a Mallory-Weiss tear. She does not use tobacco, alcohol, or illicit drugs. Temperature is 37 C (98.6 F), blood pressure is 110/70 mm Hg, pulse is 90/min, and respirations are 10/min. BMI is 24.6 kg/m2. Physical examination shows anicteric sclera, dry oral mucosa, dental caries, and bilateral swollen cheeks. The lungs are clear on auscultation and heart sounds are normal. The abdomen is soft and nontender with no organomegaly. There is mild lower extremity edema. Skin is dry without any rashes. Muscle strength is mildly decreased throughout. Which of the following sets of findings are most likely to be present in this patient?
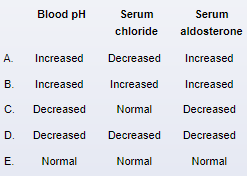
(Multiple Choice)
4.8/5 (88)
(88) A prospective cohort study is conducted to assess the relationship between elevated C-reactive protein level (exposure) and the development of acute coronary syndrome (disease). A sample of 100 adults age >45 is categorized according to their C-reactive protein (CRP) levels. After a 5-year follow-up period, the following data were obtained:  What is the 5-year risk of getting acute coronary syndrome in subjects with elevated CRP levels?
 (Multiple Choice)
4.7/5 (85)
(85) A 26-year-old man comes to the emergency department with left ankle pain. He reports that he was playing golf, went to look for his ball in some tall grass, heard rattling, and then felt a sharp pain just above his left ankle 30 minutes ago. On examination, vital signs are normal. Two puncture marks are present just above his left lateral malleolus. There is mild edema, tenderness, and ecchymosis immediately surrounding the bite. Swelling to the rest of the lower leg is absent. Pulses and sensation in the left leg are intact. Laboratory studies reveal normal complete blood count, serum electrolytes, and coagulation panel. Repeat physical examination in 30 minutes reveals no interval change. Which of the following is the most appropriate course of action for this patient?
(Multiple Choice)
4.9/5 (81)
(81) A 44-year-old man comes to the office for evaluation of lower extremity swelling and exertional dyspnea for 3 months. The patient has homozygous sickle cell disease and a history of multiple vasoocclusive episodes and acute chest syndrome. He has required frequent blood transfusions. Medications include hydroxyurea and folic acid. The patient does not use tobacco, alcohol, or illicit drugs. Temperature is 37 C (98.6 F), blood pressure is 130/80 mm Hg, heart rate is 94/min, and respirations are 22/min. BMI is 24 kg/m2. Examination shows clear lungs. The second heart sound is loud. The point of maximal impulse is at the left fifth intercostal space in the midclavicular line. The liver is palpable 2 cm below the right costal margin. There is 2+ pedal edema bilaterally. Laboratory studies show a hemoglobin of 9.8 g/dL and 2% reticulocytes. Diffusing capacity for carbon monoxide is normal. Which of the following is the most likely cause of this patient's symptoms?
(Multiple Choice)
4.8/5 (80)
(80) A 22-year-old man comes to the emergency department after a motor vehicle collision. His car was stopped at a red light when another vehicle hit his car's rear end at approximately 16 kph (9.9 mph). The patient was restrained; however, on impact, his head moved suddenly backward then forward. He has mild neck soreness but no other pain. Temperature is 36.8 C (98.3 F), blood pressure is 128/74 mm Hg, pulse is 82/min, and respirations are 14/min. The patient does not appear intoxicated. Glasgow Coma Scale score is 15, and neurologic examination is normal. Palpation of the midline spine elicits no pain. The rest of the physical examination is unremarkable. Which of the following is the most appropriate imaging for evaluating this patient's cervical spine for injury?
(Multiple Choice)
4.9/5 (70)
(70) Showing 621 - 640 of 1702
 Prev
- 1
- ...
- 2
- ...
- 3
- ...
- 4
- ...
- 5
- ...
- 6
- ...
- 7
- ...
- 8
- ...
- 9
- ...
- 10
- ...
- 11
- ...
- 12
- ...
- 13
- ...
- 14
- ...
- 15
- ...
- 16
- ...
- 17
- ...
- 18
- ...
- 19
- ...
- 20
- ...
- 21
- ...
- 22
- ...
- 23
- ...
- 24
- ...
- 25
- ...
- 26
- ...
- 27
- ...
- 28
- ...
- 29
- ...
- 30
- ...
- 31
- ...
- 32
- ...
- 33
- ...
- 34
- ...
- 35
- ...
- 36
- ...
- 37
- ...
- 38
- ...
- 39
- ...
- 40
- ...
- 41
- ...
- 42
- ...
- 43
- ...
- 44
- ...
- 45
- ...
- 46
- ...
- 47
- ...
- 48
- ...
- 49
- ...
- 50
- ...
- 51
- ...
- 52
- ...
- 53
- ...
- 54
- ...
- 55
- ...
- 56
- ...
- 57
- ...
- 58
- ...
- 59
- ...
- 60
- ...
- 61
- ...
- 62
- ...
- 63
- ...
- 64
- ...
- 65
- ...
- 66
- ...
- 67
- ...
- 68
- ...
- 69
- ...
- 70
- ...
- 71
- ...
- 72
- ...
- 73
- ...
- 74
- ...
- 75
- ...
- 76
- ...
- 77
- ...
- 78
- ...
- 79
- ...
- 80
- ...
- 81
- ...
- 82
- ...
- 83
- ...
- 84
- ...
- 85
- ...
- 86
- ...
- Next

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)