


 Chat with AI
Exam 1: Medicine

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 26-year-old woman, gravida 1 para 0, at 33 weeks gestation comes to the office due to dyspnea. The patient has had anxiety attacks during the pregnancy and reports a recent mild upper respiratory illness. She smoked 2-3 cigarettes daily prior to conception. Family history is significant for scleroderma in the patient's mother. BMI is 38 kg/m2. Pulmonary evaluation shows the following:  Which of the following is the most likely explanation for this patient's findings?
 (Multiple Choice)
4.9/5  (85)
(85) A 32-year-old woman comes to the emergency department due to progressive weakness and shortness of breath over the last several weeks. The patient has had no chest pain, palpitations, or syncope. She has not had any recent upper respiratory infection. Medical history is significant for migraine headaches for which she takes ibuprofen a few times per week. She does not take any other over-the-counter or prescription medications. The patient has had 2 cesarean sections, most recently 2 years ago. She has smoked a pack of cigarettes a day since age 17 and uses methamphetamine. The patient has no family history of heart disease or sudden cardiac death. Temperature is 36.1 C (97 F), blood pressure is 88/60 mm Hg, pulse is 105/min and regular, and respirations are 22/min. Pulse oximetry is 91% on room air. She is sitting upright in bed and appears uncomfortable. Examination reveals diffuse crackles throughout the lung fields and dullness to percussion at the right lung base. Apical impulse is palpated along the left anterior axillary line. There is an extra low-pitched sound in early diastole, best heard with the bell of the stethoscope placed on the apex. The patient's legs are cool and pulses are diminished. There is 1+ bilateral peripheral edema. Laboratory results are as follows:  Pregnancy test is negative. In addition to other appropriate therapy, the patient is given an intravenous medication that acts by primarily stimulating beta-1 adrenergic receptors. Which of the following is the most likely mechanism by which this medication may improve her condition?
 (Multiple Choice)
4.9/5 (87)
(87) A 3-year-old boy is brought to the emergency department by his mother due to cough and difficulty breathing. The patient was playing outside with his older sisters when he started coughing uncontrollably. He has been coughing with audible wheezing for the past 30 minutes. The patient has no chronic medical conditions but has had rhinorrhea for the past few days. Temperature is 36.7 C (98.1 F), blood pressure is 92/48 mm Hg, pulse is 114/min, and respirations are 48/min. Pulse oximetry is 91% on room air. The right lung has diminished breath sounds and expiratory wheezing. The left lung is clear. Supplemental oxygen is applied. Chest x-ray reveals hyperinflation of the right lung and left mediastinal shift. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (70)
(70) A 55-year-old man comes to the office due to progressive difficulty walking and frequent falls over the past year. Initially the patient had difficulty with balance when walking up and down the stairs. Now he has to brace himself against a wall even when walking on flat surfaces. He has had no urinary incontinence, slurred speech, or headaches. The patient was diagnosed with type 2 diabetes mellitus and hypertension several years ago but is not compliant with medications. He also has a history of long-term, heavy alcohol and tobacco use. Blood pressure is 170/96 mm Hg and pulse is 84/min. The patient is alert and oriented. Bilateral pupils are equal and reactive. Extraocular movements are normal. Muscle bulk, tone, and strength are normal. Proprioception and vibration sensation are normal in the lower extremities. The patient exhibits a wide-based gait and is unable to perform tandem walking. Heel-knee-shin testing is abnormal but finger-nose testing is normal. Which of the following is the most likely cause of his ambulatory dysfunction?
(Multiple Choice)
4.8/5 (77)
(77) A 46-year-old man with chronic HIV infection comes to the office for a health maintenance visit. The patient just moved into the state for a job with an architecture firm. Currently, he is sexually active with 2 male partners and uses condoms. The patient's immunization records show that he received all childhood immunizations through age 18, and received a meningococcus vaccination as a freshman in college. He also received a vaccination for tetanus-diphtheria-acellular pertussis 3 years ago following a motor vehicle accident. The patient has no history of opportunistic infections. He is on antiretroviral therapy, and his last CD4 count was 670/mm3. Assay for hepatitis B surface antibody (anti-HBs) is positive. In addition to influenza and pneumococcus vaccinations, which of the following vaccines is most appropriate for this patient?
(Multiple Choice)
4.8/5 (74)
(74) A 64-year-old man is brought to the emergency department with a 2-hour history of severe chest pain accompanied by nausea. The pain started suddenly, and the patient describes it as "tearing." He has a long-standing history of hypertension and type 2 diabetes mellitus. He has no history of coronary artery disease or stroke. The patient is a former smoker with a 35-pack-year history. He does not use illicit drugs. ECG shows sinus tachycardia without any significant ST-segment or T-wave changes. CT angiography is performed and confirms dissection of the ascending aorta extending up to the arch. While the patient is being prepared for urgent surgery, he develops increasing shortness of breath and refuses to lie flat. Chest auscultation reveals bibasilar crackles that were not present on initial evaluation. Which of the following is the most likely cause of this patient's shortness of breath?
(Multiple Choice)
4.7/5 (63)
(63) A 65-year-old man with known ischemic cardiomyopathy comes to the office due to 2 weeks of progressive shortness of breath and nonproductive cough. One week ago, he was instructed to increase his furosemide dose, but it did not seem to help. He has had no chest pain or orthopnea. He takes all of his medications as directed and comes to all of his clinic visits. The patient had a myocardial infarction 5 years ago and has severe left ventricular systolic dysfunction with an ejection fraction of 20%. He has an automatic implantable cardioverter-defibrillator (AICD). Six months ago, he was hospitalized with recurrent AICD shocks due to ventricular tachycardia; he was successfully treated with antiarrhythmic therapy, which he is currently still taking. He is afebrile. His blood pressure is 122/70 mm Hg and his pulse is 68/min and regular. His mucous membranes are moist. His jugular veins are flat while he is in a seated position. Bilateral inspiratory crackles are heard on lung auscultation. There are no cardiac murmurs. There is no significant peripheral edema. Chest x-ray reveals bilateral lung infiltrates involving primarily the middle lung fields. Which of the following is the most likely cause of this patient's current symptoms?
(Multiple Choice)
4.9/5 (73)
(73) A 76-year-old woman is brought to the emergency department by her son with 2 days of intermittent confusion, daytime somnolence, and decreased oral intake. Her medical conditions include mild dementia, hypertension, and type 2 diabetes mellitus. The son says that the patient has been talking to people who are not there and wandering around the house in the middle of the night. She has no history of recent falls. Medications include valsartan and metformin. Temperature is 37.2 C (99 F), blood pressure is 100/60 mm Hg, and pulse is 100/min and regular. The patient is easily distracted and disoriented to time and place. Neck is supple. She can move all 4 extremities. Cardiopulmonary examination is normal. Abdomen is soft and nontender. Fingerstick glucose level is 155 mg/dL. Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.8/5 (68)
(68) A 55-year-old woman comes to the hospital due to fever, chills, left flank pain, and dysuria for 2 days. She was treated for a urinary tract infection twice in the past 3 months, the latest being 4 weeks ago. Both times, the patient was compliant with antibiotic treatment and her symptoms improved. She has no other medical problems and takes no medications. Temperature is 39 C (102.2 F), blood pressure is 110/70 mm Hg, pulse is 90/min, and respirations are 16/min. BMI is 40 kg/m2. Examination shows left costovertebral angle tenderness. Laboratory results are as follows:  Kidney ultrasound shows a 1.3-cm, irregularly shaped stone in the left renal pelvis. Which of the following is the most likely mechanism of stone formation in this patient?
 (Multiple Choice)
4.9/5 (76)
(76) A 58-year-old man with a history of chronic renal insufficiency and schizophrenia comes to the emergency department with chest pain. A 12-lead ECG shows ST elevations in leads II, III, and aVF. The patient's troponin and CK-MB levels are elevated. A cardiology consult is called and the patient is prepared for emergency percutaneous coronary intervention. The risks and benefits of the procedure, including the risk of contrast-induced renal failure, are explained to the patient. He shows an understanding of his condition, the benefits of percutaneous coronary intervention, and the risks of not performing the procedure. However, despite continued persuasion, he refuses any procedure that might lead to renal failure. On mental status examination, the patient is alert and oriented to person, place, and time. His mood is anxious and his affect is flat. He says that he prefers to live alone, "because you can't trust people not to steal your things." The patient hears voices calling his name daily. He has no suicidal ideation. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (79)
(79) A 76-year-old woman is brought to the hospital due to confusion for the past hour. The patient's husband says she started having an occipital headache 2 hours ago and took acetaminophen and went to bed. An hour later, he had difficulty waking her and found her confused. Medical history is significant for hypertension and seizure disorder. The patient takes phenytoin, amlodipine, and lisinopril. She lives with her husband and is independent in her daily activities. Temperature is 37.9 C (100.2 F), blood pressure is 170/100 mm Hg, and pulse is 70/min and regular. The patient is somnolent but wakes up with painful stimuli and withdraws all 4 extremities to pain. She is unable to follow simple commands and mumbles a few unintelligible words. Deep tendon reflexes are symmetric, and Babinski sign is absent bilaterally. Fingerstick blood glucose is 110 mg/dL. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (76)
(76) A 36-year-old woman, gravida 1 para 0, at 36 weeks gestation is undergoing induction of labor due to preeclampsia with severe features. The patient is receiving a magnesium sulfate infusion for seizure prophylaxis and an oxytocin infusion for labor augmentation. She had spontaneous rupture of membranes with clear fluid 4 hours ago. The patient had epidural anesthesia placed due to increasingly painful contractions and now has adequate pain relief. She has a history of hypothyroidism that has been poorly controlled during pregnancy. Temperature is 39.4 C (103 F), blood pressure is 150/90 mm Hg, and pulse is 114/min. Fetal heart rate tracing is shown below: 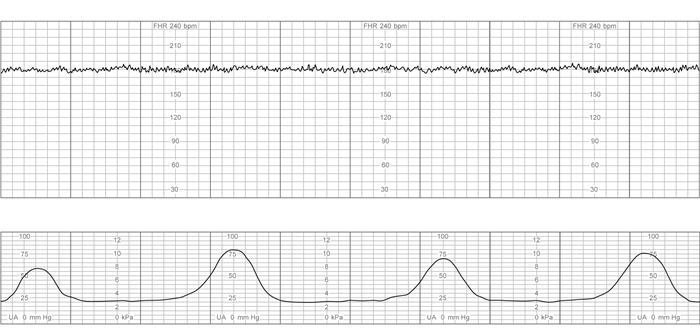 Which of the following is the most likely cause of this patient's fetal heart rate tracing?
 (Multiple Choice)
4.9/5 (60)
(60) A 45-year-old woman comes to the emergency department with vomiting and severe right flank pain that radiates to her groin. The patient has been to the emergency department twice in the past due to similar episodes of renal colic. Previous imaging showed radio-opaque stones. The stones passed spontaneously, and she did not seek further medical care. Imaging now shows another ureteral stone. A 24-hour urine collection shows urinary calcium excretion of 350 mg (normal is <250 mg in women). Laboratory results show a serum calcium concentration of 8.9 mg/dL; serum parathyroid hormone is normal. Further investigations fail to reveal a cause of the hypercalciuria. Apart from advising increased fluid intake, which of the following interventions will benefit this patient?
(Multiple Choice)
4.8/5 (91)
(91) An 81-year-old man comes to the office due to dizziness and near falls. The patient's daughter reports that, over the past 2 weeks, the patient has stated that he experiences intermittent lightheadedness and he sometimes "appears wobbly" and almost falls, most notably in the morning after getting out of bed. Medical history is significant for hypertension and Alzheimer dementia. He takes amlodipine and was recently started on quetiapine for aggressive behavior toward caregivers and delusions that his daughter has been cloned. Temperature is 37 C (98.6 F), blood pressure is 105/66 mm Hg, and pulse is 95/min. Pulse oximetry is 96% on room air. The patient is awake, alert, and oriented to person and place. Heart sounds are regular and without murmurs. The lungs are clear to auscultation bilaterally. Strength is 5/5 in the upper and lower extremities. Reflexes are normal. ECG shows normal sinus rhythm. Which of the following is the most likely cause of this patient's symptoms?
(Multiple Choice)
4.8/5 (74)
(74) A 33-year-old man comes to the office due to a rash. For the last several months, an increasing number of small lesions have appeared on his hands. The spots are associated with intermittent, mild itching but are otherwise asymptomatic. He uses electronic cigarettes regularly and drinks 3-5 alcoholic beverages on weekends. Vital signs are within normal limits. BMI is 32 kg/m2. Skin examination findings are shown in the exhibit. 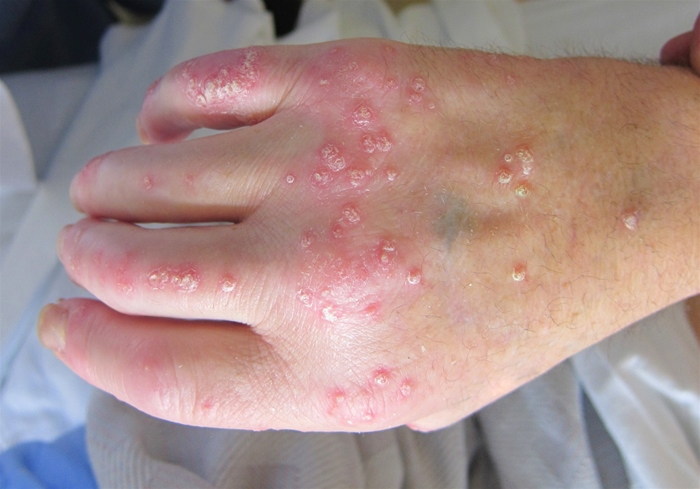 Similar lesions are visible in other locations, including the scalp. Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (79)
(79) A 27-year-old woman comes to the office due to intermittent episodes of palpitations and dyspnea on exertion. Blood pressure is 130/80 mm Hg and pulse is 78/min. On examination, there is no peripheral edema or jugular venous distension. The lungs are clear to auscultation. A 3/6 ejection-type systolic murmur is heard along the left sternal border and decreases in intensity when the patient moves from a standing to a squatting position. Which of the following additional history is most helpful for establishing a diagnosis?
(Multiple Choice)
4.8/5 (82)
(82) A 35-year-old man comes to the office due to right ankle pain. The pain has been present for the past 3 months, worsens with walking or running, and improves slightly with rest. There is no history of trauma, although the patient has been training for a marathon for the past 6 months. He took over-the-counter naproxen for a week, which provided little help. The patient has no chronic medical conditions. Vital signs are normal. Examination shows tenderness at the right Achilles tendon 4 cm proximal to its insertion. No swelling, redness, or deformity is apparent. Plantar flexion is intact. Which of the following would be the most appropriate therapy?
(Multiple Choice)
4.9/5 (78)
(78) A 43-year-old woman comes to the physician with lower-extremity edema over the last week. She has no cough, shortness of breath, chest pain, or leg pain. Medical history is significant for diet-controlled type 2 diabetes mellitus and hypertension. Her antihypertensive regimen was recently adjusted. Blood pressure is 133/80 mm Hg and BMI is 27 kg/m2. Physical examination shows bilateral pedal edema but is otherwise unremarkable. Which of the following is most likely responsible for this patient's symptoms?
(Multiple Choice)
4.9/5 (73)
(73) An 80-year-old woman is brought to the emergency department from a nursing home due to progressive lethargy. The patient has a history of Alzheimer disease and at baseline is conversant and able to indicate her needs. For the past several days, she has been somnolent and lying in bed most of the time. She has had no fever, vomiting, or diarrhea. Two weeks ago, the patient was treated with ciprofloxacin for a urinary tract infection. Her other medical problems include hypertension, type 2 diabetes mellitus, and coronary artery disease. Blood pressure is 100/60 mm Hg, pulse is 100/min, and respirations are 20/min. Mucous membranes are dry. Lungs are clear to auscultation, and heart sounds are normal. The abdomen is soft and nontender. The patient has no skin rash. Laboratory results are as follows:  A month ago, her serum creatinine was 0.9 mg/dL. Which of the following is the most likely cause of this patient's current renal abnormality?
 (Multiple Choice)
4.8/5 (68)
(68) A 54-year-old woman is admitted to the hospital with a day of right-sided weakness. The stroke team was activated, but no intervention was performed due to long length of time since symptom onset. The patient also notes 6 weeks of headaches and generalized weakness. She has not had recent fever, shortness of breath, cough, chest pain, palpitations, or syncope. She has no chronic medical conditions and does not take medications. The patient smoked a pack of cigarettes daily for 20 years but quit 15 years ago. She does not use alcohol or illicit drugs. Temperature is 37.1 C (98.8 F), blood pressure is 160/96 mm Hg, and pulse is 80/min and regular. Oxygen saturation is 99% on room air. BMI is 25 kg/m2. Cardiopulmonary examination shows no abnormalities. Abdomen is soft and tender; there is no hepatosplenomegaly. Extremities have no cyanosis, clubbing, or edema. A right facial droop is present. Motor strength is 2/5 in right upper extremity, 3/5 in right lower extremity, and 5/5 in left upper and left lower extremities. Sensation is intact diffusely. Laboratory results are as follows:  MRI of the brain reveals an acute infarction involving the left internal capsule. Chest x-ray is normal. ECG shows normal sinus rhythm. Echocardiogram shows no abnormalities. Which of the following is most likely to establish a diagnosis in this patient?
 (Multiple Choice)
4.8/5 (77)
(77) Showing 901 - 920 of 1702
 Prev
- 1
- ...
- 2
- ...
- 3
- ...
- 4
- ...
- 5
- ...
- 6
- ...
- 7
- ...
- 8
- ...
- 9
- ...
- 10
- ...
- 11
- ...
- 12
- ...
- 13
- ...
- 14
- ...
- 15
- ...
- 16
- ...
- 17
- ...
- 18
- ...
- 19
- ...
- 20
- ...
- 21
- ...
- 22
- ...
- 23
- ...
- 24
- ...
- 25
- ...
- 26
- ...
- 27
- ...
- 28
- ...
- 29
- ...
- 30
- ...
- 31
- ...
- 32
- ...
- 33
- ...
- 34
- ...
- 35
- ...
- 36
- ...
- 37
- ...
- 38
- ...
- 39
- ...
- 40
- ...
- 41
- ...
- 42
- ...
- 43
- ...
- 44
- ...
- 45
- ...
- 46
- ...
- 47
- ...
- 48
- ...
- 49
- ...
- 50
- ...
- 51
- ...
- 52
- ...
- 53
- ...
- 54
- ...
- 55
- ...
- 56
- ...
- 57
- ...
- 58
- ...
- 59
- ...
- 60
- ...
- 61
- ...
- 62
- ...
- 63
- ...
- 64
- ...
- 65
- ...
- 66
- ...
- 67
- ...
- 68
- ...
- 69
- ...
- 70
- ...
- 71
- ...
- 72
- ...
- 73
- ...
- 74
- ...
- 75
- ...
- 76
- ...
- 77
- ...
- 78
- ...
- 79
- ...
- 80
- ...
- 81
- ...
- 82
- ...
- 83
- ...
- 84
- ...
- 85
- ...
- 86
- ...
- Next

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)