


 Chat with AI
Exam 1: Medicine

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 28-year-old woman comes to the office for a periodic recheck of "moles." The patient has a history of multiple irregular melanocytic nevi that have been monitored with regular surveillance, but none of the lesions have required removal. She is concerned about a lesion on her abdomen, which is associated with intermittent itching and has enlarged since her last visit. The patient has a history of recurrent sunburn in childhood. On examination, there are numerous benign-appearing nevi scattered across the body surface. In addition, there is a 2 x 1 cm, pigmented lesion at the lateral abdomen, as shown in the image, which has increased in length since her last visit 6 months ago. Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5  (92)
(92) A 24-year-old Indian man comes to the emergency department due to 3 days of left upper quadrant abdominal pain. The pain began after he flew back from India, where he was visiting family. He has had no fever, palpitations, nausea, vomiting, or diarrhea. He does not use tobacco or alcohol regularly, but on the flight back to the United States, he had some alcohol to help him sleep. He has no chronic medical conditions and takes no medications. Temperature is 37.3 C (99.1 F), blood pressure is 120/80 mm Hg, pulse is 96/min, and respirations are 16/min. Pulse oximetry is 97% on room air. Mucous membranes are moist, and there is no jugular venous distension or palpable lymphadenopathy. Cardiopulmonary auscultation is normal. Abdominal examination reveals left upper quadrant tenderness with no rigidity or rebound guarding. Bowel sounds are present, and there is no hepatosplenomegaly. There is no lower extremity edema or skin rashes. Laboratory results are as follows:  Abdominal ultrasound shows normal liver size, but the spleen is slightly enlarged with a hypoechoic wedge consistent with an infarction. Which of the following would be most helpful in determining the underlying cause of his current condition?
 (Multiple Choice)
5.0/5 (82)
(82) A 62-year-old man comes to the office due to worsening itchy, dry skin on the hands. For 2 years, he has experienced thickened, cracking skin at the dorsum of both hands that has extended to the fingers. The patient tried moisturizing lotions, with partial relief, but the symptoms relapsed if he did not apply the lotions regularly. Medical history is notable for seasonal allergies and an occasional herpes rash on his upper lip following upper respiratory infections. He works as a janitor and does not use tobacco, alcohol, or illicit drugs. Examination shows scaly skin and erythema on the fingers, finger webs, and dorsum of both hands, as shown in the exhibit.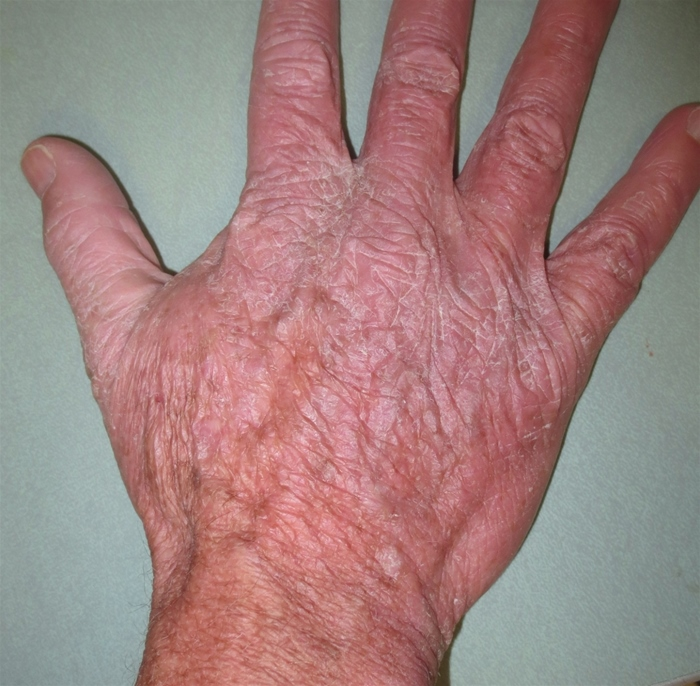 No other skin lesions are seen. Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (70)
(70) A 35-year-old man comes to the emergency department due to severe pain behind his left eye. The patient reports that the pain is intense and stabbing and that it woke him up around midnight. It improved after 30 minutes and he was about to go back to sleep when the same pain began again. He took ibuprofen without relief. Several months ago, the patient had similar episodes of pain that resolved spontaneously after 2 weeks. He has had no fevers, blurry vision, nausea, or vomiting but has had nasal congestion. The patient has seasonal allergies for which he takes cetirizine. He works as a flight operations officer and describes his job as "pretty stressful." He drinks 2 or 3 cups of coffee daily and drinks alcohol occasionally. His mother has migraine headaches. Temperature is 36.7 C (98 F), blood pressure is 140/90 mm Hg, and pulse is 94/min. The patient is restless and agitated. Physical examination shows left-sided ptosis, miosis, and rhinorrhea. Neurologic examination shows bilateral equal and normal motor strength, sensation, and deep tendon reflexes. Which of the following is the most likely cause of this patient's headache?
(Multiple Choice)
4.9/5 (84)
(84) A 64-year-old woman is brought to the office by her spouse due to cognitive impairment. The patient has been mildly forgetful over the past 2 years, with further significant decline in the last 3 months. She performs most daily activities independently but must be reminded frequently to perform basic self-care. The patient has also become unsteady, and she has had 2 near falls in the last 3 months. She still enjoys spending time with family and friends. The patient has a 6-year history of HIV infection and takes antiretroviral therapy. Her most recent CD4 cell count was 600/mm3 3 months ago. Other medical history includes hypertension, hyperlipidemia, and type 2 diabetes mellitus. Temperature is 37.1 C (98.8 F), blood pressure is 140/82 mm Hg, and pulse is 80/min. On physical examination, the patient is oriented to time, place, and person, but there is short-term memory impairment. Mild weakness of the left-sided extremities and a pronator drift of the left arm are present. She is unsteady in the Romberg position with her eyes closed. Which of the following is the most likely cause of this patient's cognitive impairment?
(Multiple Choice)
4.9/5 (70)
(70) A 47-year-old man comes to the office due to bloating and abdominal discomfort for the past 2 months. The patient's abdomen has become progressively enlarged in association with a 9-kg (19-lb) weight gain. He also notes fatigue and difficulty breathing while walking up and down steps but denies chest pain or palpitations. The patient drinks 8-10 beers a day but does not use tobacco or illicit drugs. He has no relevant medical history. Temperature is 37.5 C (99.5 F), blood pressure is 130/65 mm Hg, pulse is 75/min, and respirations are 15/min. Physical examination shows scleral icterus, palmar erythema, and multiple spider angiomas. The abdomen is distended and nontender, and a fluid wave is present. A right upper quadrant ultrasound demonstrates a nodular, shrunken liver as well as the presence of fluid in the intraperitoneal cavity. Diagnostic paracentesis reveals straw-yellow fluid. Which of the following fluid analysis tests should be performed?
(Multiple Choice)
4.9/5 (68)
(68) A 65-year-old man with chronic obstructive pulmonary disease, atrial fibrillation, hypertension, and type II diabetes mellitus comes to the emergency department due to shortness of breath for 3 days. The patient's condition began with a runny nose, itchy eyes, and sore throat. His symptoms progressed to productive cough, wheezing, and dyspnea. On examination, blood pressure is 150/90 mm Hg and pulse is 110/min and irregular. Oxygen saturation is 91% on room air. Examination shows a mildly overweight man in moderate respiratory distress. Lung sounds are decreased throughout, with prolonged expiration and bilateral wheezes. The patient is started on inhaled bronchodilators, systemic corticosteroids, high-flow facial mask oxygen, and intravenous lorazepam for agitation. Thirty minutes later, he is lethargic and confused. Shortly thereafter, he experiences a generalized tonic-clonic seizure. Which of the following most likely contributed to this patient's neurologic symptoms?
(Multiple Choice)
4.9/5 (76)
(76) A 48-year-old woman with advanced-stage epithelial ovarian cancer undergoes surgery and adjuvant therapy with paclitaxel and carboplatin. At a follow-up visit 2 weeks after her first cycle of chemotherapy, the patient reports losing "clumps" of hair in the shower and while brushing her hair that morning. She feels moderately fatigued but has no other symptoms. Examination shows thinning of the hair across the vertex and crown. The skin of the scalp shows no erythema or scaling. Which of the following is the most likely explanation for this patient's hair loss?
(Multiple Choice)
4.9/5 (82)
(82) A 65-year-old man comes to the clinic due to periodic substernal chest pain over the last 6 months. The pain episodes occur during strong emotion, last for 10-15 minutes, and resolve spontaneously. The patient has a long history of hypertension and diabetes mellitus type 2. His right foot was amputated 2 years ago due to diabetes complications. Myocardial perfusion imaging is performed to evaluate for possible obstructive coronary artery disease. Resting imaging reveals uniform distribution of the radioactive isotope throughout the myocardium. Imaging after administration of an adenosine analog reveals nonuniform radioactive isotope uptake in the myocardium, consistent with myocardial ischemia. Which of the following best describes the mechanism of the change observed during the stress portion of the study?
(Multiple Choice)
4.9/5 (93)
(93) A 42-year-old man comes to the office after attempting to donate blood, when he was found to have abnormal viral serologic results for hepatitis. The patient feels well and takes no medications. He has no history of liver disease, but his father died of complications of alcoholic cirrhosis. The patient drinks 1 or 2 beers on weekdays and 5 or 6 on the weekends. He used injection drugs for several years in his 20s but not recently. The patient does not use tobacco. He has had several lifetime sexual partners but is now in a monogamous relationship. Temperature is 37.1 C (98.8 F), blood pressure is 136/85 mm Hg, and pulse is 84/min. BMI is 34.2 kg/m2. A smooth, nontender liver edge is palpable 3 cm below the right costal margin; otherwise, the physical examination is unremarkable. Laboratory results are as follows:  Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.8/5 (84)
(84) A 40-year-old woman comes to the office due to pain in her right hip for the past 4 weeks. The pain increases with weight bearing. She has no morning stiffness, warmth, or erythema, and no pain in other joints. The patient has no history of significant trauma to the hip and has not had similar pain before. She was diagnosed with systemic lupus erythematosus 7 years ago. Her current medications include low-dose prednisone, hydroxychloroquine, and lansoprazole. The patient does not use tobacco, alcohol, or illicit drugs. She is afebrile, and vital signs are normal. There is no local tenderness over any joints, and range of motion of the right hip is normal. Plain film radiograph of the hip is normal. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (82)
(82) A 35-year-old man is brought to the emergency department due to generalized weakness. Medical history is significant for end-stage renal disease due to glomerulonephritis. The patient usually does peritoneal dialysis at home but has not had treatment for the past 2 days. Temperature is 37.3 C (99.1 F), and blood pressure is 80/60 mm Hg. Cardiopulmonary examination shows no abnormalities. The abdomen is soft and nontender. Bowel sounds are present. Pulses are palpable bilaterally. Muscle strength is 4/5 in all 4 extremities. ECG is shown in the exhibit. 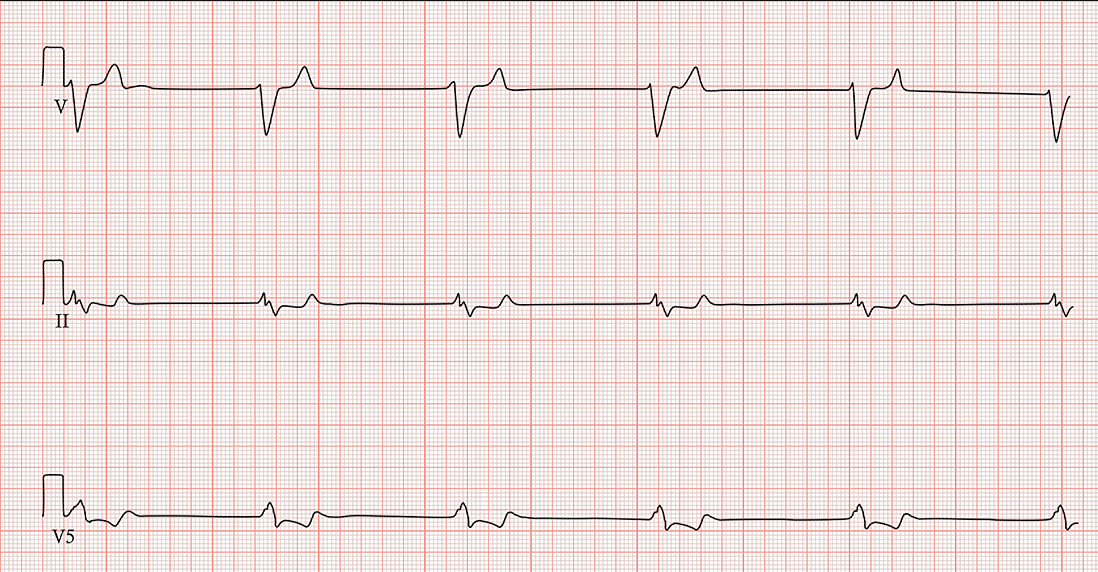 Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.9/5 (86)
(86) A 52-year-old man comes to the office due to decreased libido and inability to achieve and maintain erections for the past several months. He has also had fatigue, anorexia, and a 5-kg (11-lb) weight loss over the same duration. The patient is married and has one child. He drinks alcohol but does not use tobacco or illicit drugs. Blood pressure is 110/70 mm Hg and pulse is 82/min. Physical examination shows bilateral gynecomastia and firm and small testes. Laboratory testing shows normal TSH with decreased levels of total triiodothyronine (T3) and thyroxine (T4). Which of the following is the most likely diagnosis?
(Multiple Choice)
5.0/5 (81)
(81) A 57-year-old woman comes to the emergency department due to a day of worsening right-upper quadrant pain and fever. The patient has a history of untreated chronic hepatitis C infection. She smokes a pack of cigarettes a day and drinks 1 or 2 beers most nights; she used to inject methamphetamines but quit 12 years ago after developing a splenic abscess. Temperature is 38.8 C (101.9 F), blood pressure is 104/58 mm Hg, pulse is 118/min, and respirations are 20/min. Abdominal examination shows right-upper quadrant tenderness with positive Murphy sign. Ultrasonography reveals increased gall bladder wall thickness with intramural gas and pericholecystic fluid. No gallstones or biliary duct dilation is present. Intravenous fluids and broad-spectrum antibiotics are begun and a laparoscopic cholecystectomy for acute acalculous cholecystitis is performed. Blood cultures drawn at the time of admission grow Clostridium septicum. Which of the following is most appropriate to evaluate for associated conditions in this patient?
(Multiple Choice)
4.8/5 (84)
(84) A 33-year-old man comes to the office due to 6 weeks of nonproductive cough and fatigue. The patient has also had subjective fevers and a 2.26-kg (5-lb) unintended weight loss over the same period. He has no prior medical conditions and takes no medications. The patient drinks alcohol socially and has a 6-pack-year history of smoking but quit 2 years ago. Vital signs are within normal limits. Lungs are clear on auscultation, and heart sounds are normal. Chest x-ray reveals clear lung fields but an enlarged mediastinum; subsequent CT scan of the chest shows hilar and mediastinal adenopathy. A positron emission tomography scan using 18-fluorodeoxyglucose demonstrates avid tracer uptake in the brain, kidneys, urinary bladder, and supraclavicular and mediastinal lymph nodes. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (92)
(92) A 65-year-old woman comes to the office reporting progressively increasing orthopnea, daytime fatigue, and morning headache for the last month. She has had no chest pain or problems with swallowing or speech. Medical conditions include myocardial infarction, type 2 diabetes, hypertension, and amyotrophic lateral sclerosis. Temperature is 37 C (98.6 F), blood pressure is 130/70 mm Hg, pulse is 88/min, and respirations are 16/min. Pulse oximetry shows 95% on room air. BMI is 24 kg/m2. Examination shows normal jugular venous pressure, clear lungs, and normal heart sounds. There is no peripheral edema. Neurologic examination shows 3/5 power in right lower extremity and 4/5 power in left lower extremity and muscle atrophy, unchanged from her last examination 2 months ago. Laboratory results are as follows: 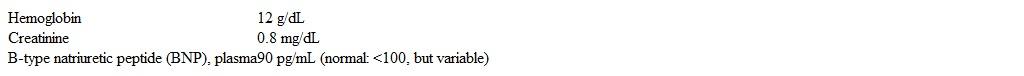 Which of the following is the most appropriate next step in management?
 (Multiple Choice)
4.8/5 (87)
(87) A 62-year-old man comes to the office due to fatigue and weight loss. Over the last 6 months, he has lost 9 kg (20 lb) and can no longer walk long distances without sitting down to rest. The patient has not seen a physician in 15 years. He has smoked a pack of cigarettes daily for the last 35 years but does not use alcohol or illicit drugs. He has not recently traveled. Temperature is 36.9 C (98.4 F), blood pressure is 130/80 mm Hg, pulse is 88/min, and respirations are 12/min. Lungs are clear to auscultation, and abdominal examination shows a liver span of 14 cm with no tenderness. Rectal examination reveals normal sphincter tone but a slightly enlarged prostate that is nontender to palpation. Chest x-ray is unremarkable. CT scan of the abdomen with contrast is shown in the image below. 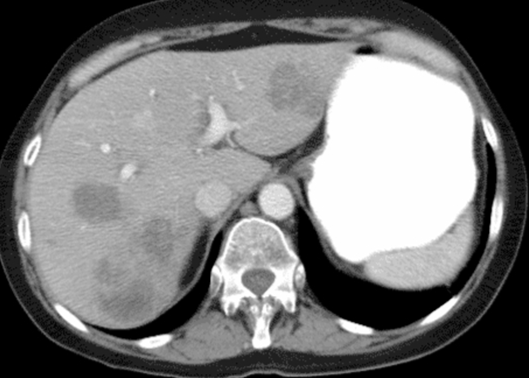 Which of the following is most likely to establish the diagnosis in this patient?
 (Multiple Choice)
4.9/5 (82)
(82) A 76-year-old woman comes to the office due to intermittent palpitations for the last 6 months. The patient describes episodes of her heart beating fast. These happen on average once a week, last up to an hour, and resolve spontaneously. She cannot identify any provoking factors but thinks they occur typically when she is tired. The patient has had no chest pain, dyspnea, syncope, or lower extremity swelling. She has a history of hypertension. The patient is a lifetime nonsmoker. Blood pressure is 145/85 mm Hg, and pulse is 75/min and regular. There are no heart murmurs. The lungs are clear on auscultation. Peripheral pulses are full and symmetric. ECG shows normal sinus rhythm. Echocardiogram shows moderate left atrial enlargement, left ventricular hypertrophy, ejection fraction of 65%, and no valvular abnormalities. Further workup is most likely to identify which of the following in this patient?
(Multiple Choice)
4.9/5 (68)
(68) A 25-year-old female presents to your office complaining of exertional dyspnea and fatigue. Her past medical history is insignificant. She does not smoke or consume alcohol. Her blood pressure is 110/70 mmHg and heart rate is 90/min. Physical examination reveals pale conjunctiva. The laboratory values are:  What is the best next step in the management of this patient?
 (Multiple Choice)
4.8/5 (77)
(77) A 64-year-old man with a history of hypertension and diet-controlled type 2 diabetes mellitus comes to the office due to generalized malaise and palpitations for the past 2 weeks. An echocardiogram last year showed mild left atrial dilation and left ventricular hypertrophy. The patient's medications include lisinopril and hydrochlorothiazide. Blood pressure is 170/90 mm Hg. ECG rhythm strip is shown in the exhibit. 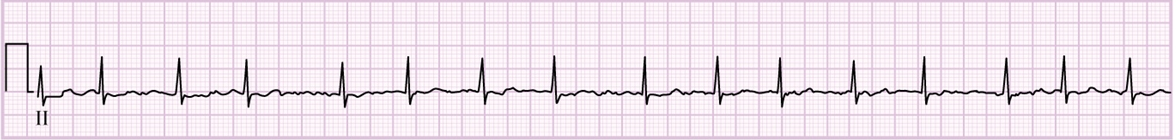 Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.8/5 (70)
(70) Showing 201 - 220 of 1702
 Prev
- 1
- ...
- 2
- ...
- 3
- ...
- 4
- ...
- 5
- ...
- 6
- ...
- 7
- ...
- 8
- ...
- 9
- ...
- 10
- ...
- 11
- ...
- 12
- ...
- 13
- ...
- 14
- ...
- 15
- ...
- 16
- ...
- 17
- ...
- 18
- ...
- 19
- ...
- 20
- ...
- 21
- ...
- 22
- ...
- 23
- ...
- 24
- ...
- 25
- ...
- 26
- ...
- 27
- ...
- 28
- ...
- 29
- ...
- 30
- ...
- 31
- ...
- 32
- ...
- 33
- ...
- 34
- ...
- 35
- ...
- 36
- ...
- 37
- ...
- 38
- ...
- 39
- ...
- 40
- ...
- 41
- ...
- 42
- ...
- 43
- ...
- 44
- ...
- 45
- ...
- 46
- ...
- 47
- ...
- 48
- ...
- 49
- ...
- 50
- ...
- 51
- ...
- 52
- ...
- 53
- ...
- 54
- ...
- 55
- ...
- 56
- ...
- 57
- ...
- 58
- ...
- 59
- ...
- 60
- ...
- 61
- ...
- 62
- ...
- 63
- ...
- 64
- ...
- 65
- ...
- 66
- ...
- 67
- ...
- 68
- ...
- 69
- ...
- 70
- ...
- 71
- ...
- 72
- ...
- 73
- ...
- 74
- ...
- 75
- ...
- 76
- ...
- 77
- ...
- 78
- ...
- 79
- ...
- 80
- ...
- 81
- ...
- 82
- ...
- 83
- ...
- 84
- ...
- 85
- ...
- 86
- ...
- Next

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)