


 Chat with AI
Exam 1: Medicine

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 38-year-old man comes to the office for follow-up after his blood pressure was found to be elevated at a health fair. The patient has had no headache, blurry vision, or chest pain. He does not use tobacco, alcohol, or illicit drugs. Temperature is 36.7 C (98.1 F), blood pressure is 148/96 mm Hg in the right arm and 146/94 mm Hg in the left, pulse is 74/min, and respirations are 14/min. BMI is 36 kg/m2. Examination shows a regular heart rate and rhythm with no heart murmurs or carotid and abdominal bruits. Peripheral pulses are 2+ without radiofemoral delay. Breath sounds are normal. ECG is normal, and a 48-hour ambulatory blood pressure monitor shows an average pressure of 138/88 mm Hg. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.7/5  (77)
(77) A 52-year-old man comes to the emergency department due to generalized weakness, anxiety, and tremors. The patient has a history of alcohol use disorder. His last drink was 2 days ago. He has no other medical problems and no medical follow-up. The patient smokes cigarettes but does not use illicit drugs. He takes no medications. On examination, he appears disheveled and malnourished. His initial electrolyte panel results are as follows:  He is treated for alcohol withdrawal and given aggressive intravenous potassium as well as oral potassium supplementation. Three days later, his electrolyte panel results are as follows:
 Which of the following best explains why this patient's potassium level is very difficult to correct?
He is treated for alcohol withdrawal and given aggressive intravenous potassium as well as oral potassium supplementation. Three days later, his electrolyte panel results are as follows: Which of the following best explains why this patient's potassium level is very difficult to correct? (Multiple Choice)
4.8/5 (80)
(80) A 56-year-old woman comes to the emergency department due to a week of fever, dyspnea, and cough with productive, foul-smelling sputum. She has no chills or rigors. The patient was seen at an urgent care center for these symptoms 4 days ago and was prescribed a 5-day course of azithromycin to treat pneumonia. However, she continues to feel worse despite taking the medicine. She underwent an upper gastrointestinal endoscopy 10 days ago for a long history of heartburn. Temperature is 38.7 C (101.7 F), blood pressure is 130/80 mm Hg, pulse is 108/min, and respirations are 22/min. Dentition is poor. Crackles are heard over the right upper lung field. There are no cardiac murmurs. Abdomen is soft and nontender. Complete blood count shows leukocytes of 14,500/mm3. Chest x-ray reveals a right upper lobe infiltrate. Which of the following additional therapies would be most helpful for this patient's condition?
(Multiple Choice)
4.8/5 (84)
(84) A 75-year-old man is brought to the emergency department due to a 2-day history of progressive lethargy and confusion. His family reports that he has had fatigue and blurred vision over the last several days. The patient was recently diagnosed with polymyalgia rheumatica and is taking prednisone. Medical history is notable for diet-controlled type 2 diabetes mellitus, hypertension, and hyperlipidemia. Temperature is 37.9 C (100.2 F), blood pressure is 90/60 mm Hg, pulse is 112/min, and respirations are 18/min. Oral mucous membranes are dry. The lungs are clear to auscultation, and the heart has a regular tachycardia with no murmur. The neck is supple. The patient is somnolent but arousable and moves all extremities equally on command. Laboratory results are as follows:  Urinalysis shows trace ketones. Which of the following is the most likely cause of this patient's altered sensorium?
 (Multiple Choice)
4.9/5 (77)
(77) A 30-year-old man comes to the office due to a 3-month history of progressive left breast enlargement. He has had no breast pain or nipple discharge. The patient has a history of Klinefelter syndrome and takes testosterone replacement therapy. Vital signs are within normal limits. BMI is 30 kg/m2. Physical examination shows a 2.5-cm, nontender, firm subareolar mass on the left side. Right breast examination is normal. The testes are atrophic and body hair is sparse. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.7/5 (74)
(74) A 28-year-old woman comes to the emergency department due to persistent bilateral headaches. The patient was initially seen at an urgent care clinic for the same symptoms 4 weeks ago and had normal physical examination findings. The headache was attributed to a suspected upper respiratory illness, and ibuprofen as needed was advised. The headache has failed to improve, and now the patient also feels fatigued. She has had no fever, nausea, vomiting, cough, shortness of breath, chest or abdominal pain, or diarrhea. The patient has no chronic medical conditions but says she sunburns easily. She does not use tobacco, alcohol, or illicit drugs. Temperature is 37.2 C (99 F), blood pressure is 170/110 mm Hg, pulse is 82/min, and respirations are 14/min. Physical examination shows normal jugular venous pressure, clear lungs, normal heart sounds, and a nontender abdomen. There is 1+ pitting edema of the bilateral lower extremities. Laboratory results are as follows:  Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.8/5 (74)
(74) A 77-year-old man comes to the physician with a 2-week history of fevers and generalized weakness. His other medical history includes a hospitalization for pyelonephritis requiring intravenous antibiotics 3 months ago, an episode of rheumatic fever as a child, and Hodgkin's lymphoma treated with chemotherapy 15 years ago. He also recently underwent cystoscopy for evaluation of persistent dysuria. His temperature is 37.8 C (100 F), blood pressure is 150/86 mm Hg, pulse is 98/min, and respirations are 16/min. The patient appears slightly diaphoretic. There is a new II/VI holosystolic murmur at the apex and tender erythematous lesions affecting several fingertips. The remainder of the physical examination is unremarkable. Which of the following bacteria is most likely responsible for this patient's present illness?
(Multiple Choice)
4.9/5 (78)
(78) A 60-year-old man comes to the office due to shortness of breath over the last 5 months. He also has a chronic mild mucoid cough, especially in the morning. The shortness of breath initially occurred with heavy exertion or long-distance walking, but the patient now experiences it even if he walks only 2 or 3 blocks. He has no fever, chills, hemoptysis, chest pain, or difficulty breathing while lying on his back. His only other medical problem is hypertension. The patient has smoked a pack of cigarettes daily for the last 40 years. Temperature is 37.2 C (99 F), blood pressure is 130/86 mm Hg, pulse is 78/min, and respirations are 18/min. Pulse oximetry shows 95% oxygen saturation on room air and 92% after a short, brisk walk. Examination shows a thin man in no respiratory distress. Breath sounds are mildly decreased throughout. Spirometry results are as follows:  No significant change is noted with bronchodilator therapy. Complete blood count is normal. Which of the following is the most effective measure to decrease mortality in this patient?
 (Multiple Choice)
5.0/5 (82)
(82) A 55-year-old man comes to the physician with acute-onset muscle pain. His other medical problems include hypertension, hyperlipidemia, and a myocardial infarction 2 months ago. His medications include metoprolol, lisinopril, aspirin, and simvastatin. His blood pressure is 130/80 mm Hg and pulse is 60/min. Examination shows no muscle weakness. There is no hepatosplenomegaly. No skin rash is present. Liver function tests show slightly increased aspartate aminotransferase and alanine aminotransferase. The serum creatine kinase level is elevated. The physician suspects a drug-induced reaction. Which of the following is the most likely mechanism of action for this drug?
(Multiple Choice)
4.8/5 (67)
(67) A 62-year-old man comes to the office due to sudden onset of pain and redness in the left eye. The patient also has photophobia, nausea, and a severe headache that has not responded to ibuprofen. There has been no trauma, and he has never had such an episode before. Medical history is unremarkable. On review of systems, the patient has had "a mild cold" for which he has been using an over-the-counter oral decongestant. Physical examination shows a nonreactive, mid-dilated left pupil. The eye appears red with conjunctival flushing. Which of the following is the best next step in evaluating this patient's condition?
(Multiple Choice)
4.9/5 (70)
(70) A 65-year-old man comes to the physician for fatigue, poor appetite, and lower-leg swelling. Past medical history is significant for hypertension, type 2 diabetes mellitus, chronic cough, chest infections, and lower-extremity peripheral artery disease. The patient has a 40-pack-year smoking history. He does not use alcohol or illicit drugs. Physical examination shows a barrel-shaped chest, with bilateral scattered wheezing on auscultation. The patient's abdomen is distended, and the liver edge is palpated 4 cm below the right costal margin. There is 2+ pitting edema and dilated, tortuous superficial veins over both lower extremities. Manual pressure on the abdomen causes persistent distension of the jugular veins. His serum sodium level is 135 mEq/L, and creatinine is 1.2 mg/dL. An abnormality of which of the following is most likely the cause of this patient's edema?
(Multiple Choice)
4.7/5 (83)
(83) A 34-year-old man comes to the physician complaining of occasional dizziness and palpitations in crowded spaces. He is an executive who travels frequently and reports high stress levels at work. He takes no medications and his family history is unremarkable. He drinks alcohol occasionally and does not use tobacco or illicit drugs. His blood pressure is 130/80 mm Hg and pulse is 80/min. Chest examination is unremarkable. The liver span is 8 cm and the spleen is not palpable. There is no cervical lymphadenopathy or skin rash. Laboratory results are as follows:
 Peripheral smear confirms a reduced platelet count without clumping or malignant cells. Which of the following is the most appropriate next test for this patient?
 (Multiple Choice)
4.7/5 (70)
(70) A 68-year-old man comes to the hospital due to abdominal distension. His waist has progressively enlarged over the past few weeks, leading to a feeling of "heaviness." In addition, the patient has trouble walking more than two city blocks before becoming severely short of breath. He has a long history of heavy alcohol use. Scleral icterus is present on physical examination as well as 2+ pitting edema in the bilateral lower extremities. Multiple spider angioma are identified. The abdomen is grossly distended and mildly tender to palpation. Shifting dullness is elicited. Which of the following changes are most likely present in this patient?
(Multiple Choice)
4.8/5 (83)
(83) A 24-year-old man comes to the emergency department due to a few hours of fever with rigors, headache, and myalgias. While at an urgent care center last night, he was diagnosed with syphilis and received a dose of intramuscular benzathine penicillin G. The patient has a history of HIV infection, and a recent CD4 count was 540/mm3. He is not currently taking antiretroviral therapy and takes no other medications. He continues to have unprotected intercourse with several partners despite counseling. The patient does not use tobacco, alcohol, or illicit drugs. Temperature is 38 C (100.4 F), blood pressure is 90/60 mm Hg, and pulse is 110/min. The patient is diaphoretic and appears uncomfortable. A diffuse, faint, macular rash involving the palms and soles is present. Genital examination shows a nontender ulcer with induration and several enlarged inguinal lymph nodes. Which of the following is the most likely cause of this patient's current condition?
(Multiple Choice)
4.9/5 (84)
(84) A 38-year-old man comes to the office for evaluation of bilateral progressive hand pain with intermittent swelling over the past 6 months. The patient has no other symptoms or history of trauma or family history of arthropathy. Medical history is significant for type 2 diabetes mellitus, for which he takes metformin. Vital signs are normal. BMI is 24 kg/m2. Examination reveals mild swelling and tenderness over the second and third metacarpophalangeal (MCP) joints bilaterally. There is no muscle weakness. X-ray reveals joint space narrowing and chondrocalcinosis involving the second MCP joints with osteophyte formation at the second and third metacarpal heads. Serum alanine and aspartate aminotransferases are elevated. Which of the following therapies would be of most benefit to this patient?
(Multiple Choice)
4.7/5 (74)
(74) A 65-year-old man comes to the emergency department due to fever, chills, and a productive cough for the past 3 days. He also has shortness of breath and right-sided chest pain that is worse with deep breathing. His other medical problems include coronary artery disease, type 2 diabetes mellitus, and hyperlipidemia. The patient's medications include low-dose aspirin, atorvastatin, metformin, and sitagliptin. He does not use tobacco, alcohol, or illicit drugs. His temperature is 39.2 C (102.5 F), blood pressure is 95/60 mm Hg, pulse is 112/min, and respirations are 24/min. Oxygen saturation is 96% on room air. Examination shows dry mucous membranes. Laboratory results are as follows:  Chest x-ray reveals a right lower-lobe infiltrate. Blood cultures are obtained and intravenous fluids and antibiotics are administered. Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
5.0/5 (98)
(98) A 19-year-old man is brought to the emergency department by his college roommate due to a day of confusion, severe dyspnea, and cough productive of yellowish sputum streaked with blood. According to his roommate, the patient visited an urgent care clinic last week for fever, rhinorrhea, and malaise. He was diagnosed with a "viral infection" and given a prescription medication that seemed to improve his illness. He has no other medical issues, takes no other medications, and does not smoke cigarettes or drink alcohol. Temperature is 40 C (104 F), blood pressure is 124/75 mm Hg, pulse is 125/min, and respirations are 32/min. Lung auscultation shows bilateral crackles in the lung midfields. A 2/6 ejection systolic murmur is heard at the left upper sternal border. Extremities are warm with bounding peripheral pulses. Chest x-ray reveals alveolar infiltrates in the midlung fields bilaterally as well as several thin-walled cavities. Which of the following is the most likely cause of this patient's condition?
(Multiple Choice)
5.0/5 (84)
(84) A 69-year-old man is brought to the emergency department by his family for increasing confusion over the last 2 days. He also has had nausea, vomiting, and back and abdominal pain. At baseline, the patient is interactive and pleasant. His medical history is notable for type 2 diabetes mellitus controlled with metformin and hypertension treated with amlodipine. Temperature is 37.2 C (99 F), blood pressure is 112/70 mm Hg, and pulse is 102/min and regular. The patient appears disheveled and confused. Examination shows clear lung fields and normal heart sounds. There are no neck masses or enlarged lymph nodes. Neurologic examination shows no focal muscle weakness. Laboratory results are as follows:  Which of the following is the most appropriate next step for this patient?
 (Multiple Choice)
4.8/5 (78)
(78) A 34-year-old man comes to the emergency department with severe abdominal pain. He describes the pain as "sharp" and "unbearable." It is located in the lower left abdomen and radiates to the groin. He has vomited twice since it began. The patient has no burning with urination. He is afebrile. He has difficulty lying still on the examination table due to the discomfort. Mucous membranes appear slightly dry. Lungs are clear to auscultation. Heart sounds are normal and there are no murmurs or gallops. The abdomen is soft and nontender to palpation. Inspection and palpation show normal genitalia. Extremities have no cyanosis, clubbing, or edema. Which of the following is the most appropriate test to diagnose this patient's condition?
(Multiple Choice)
4.8/5 (81)
(81) A 68-year-old woman with type 2 diabetes mellitus is hospitalized for an acute ST-segment elevation myocardial infarction. She undergoes immediate cardiac catheterization and successful stenting of the mid-left anterior descending artery. The patient is treated with aspirin, prasugrel, metoprolol, lisinopril, and rosuvastatin. On the third day of hospitalization, she complains of vague abdominal pain. Her blood pressure is 122/70 mm Hg and pulse is 62/min. Lungs are clear to auscultation. There are no cardiac murmurs. Her abdomen is soft and mildly tender in the periumbilical area. Bilateral pedal pulses are full and symmetric. There is bluish discoloration of her right great toe and all the toes on her left foot. She has additional skin findings as shown below: 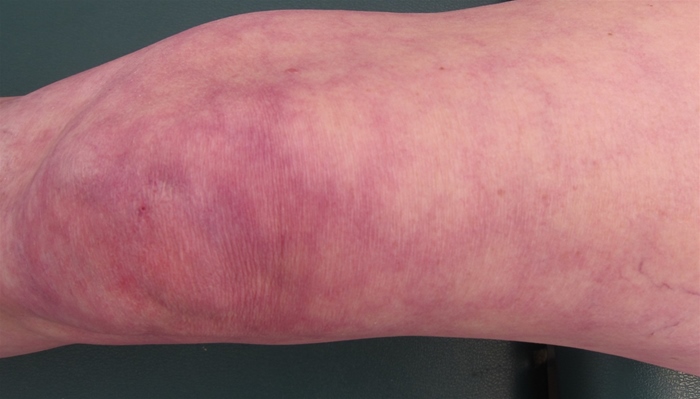 Serum creatinine is 2.3 mg/dL (1.1 mg/dL on admission). Electrocardiogram (ECG) shows sinus rhythm and Q waves in anterior leads. Which of the following is the most likely cause of this patient's symptoms?
 (Multiple Choice)
4.9/5 (69)
(69) Showing 1501 - 1520 of 1702
 Prev
- 1
- ...
- 2
- ...
- 3
- ...
- 4
- ...
- 5
- ...
- 6
- ...
- 7
- ...
- 8
- ...
- 9
- ...
- 10
- ...
- 11
- ...
- 12
- ...
- 13
- ...
- 14
- ...
- 15
- ...
- 16
- ...
- 17
- ...
- 18
- ...
- 19
- ...
- 20
- ...
- 21
- ...
- 22
- ...
- 23
- ...
- 24
- ...
- 25
- ...
- 26
- ...
- 27
- ...
- 28
- ...
- 29
- ...
- 30
- ...
- 31
- ...
- 32
- ...
- 33
- ...
- 34
- ...
- 35
- ...
- 36
- ...
- 37
- ...
- 38
- ...
- 39
- ...
- 40
- ...
- 41
- ...
- 42
- ...
- 43
- ...
- 44
- ...
- 45
- ...
- 46
- ...
- 47
- ...
- 48
- ...
- 49
- ...
- 50
- ...
- 51
- ...
- 52
- ...
- 53
- ...
- 54
- ...
- 55
- ...
- 56
- ...
- 57
- ...
- 58
- ...
- 59
- ...
- 60
- ...
- 61
- ...
- 62
- ...
- 63
- ...
- 64
- ...
- 65
- ...
- 66
- ...
- 67
- ...
- 68
- ...
- 69
- ...
- 70
- ...
- 71
- ...
- 72
- ...
- 73
- ...
- 74
- ...
- 75
- ...
- 76
- ...
- 77
- ...
- 78
- ...
- 79
- ...
- 80
- ...
- 81
- ...
- 82
- ...
- 83
- ...
- 84
- ...
- 85
- ...
- 86
- ...
- Next

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)