



 Chat with AI
Exam 4: Surgery

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 19-year-old man is brought to the emergency department due to suspected hypothermia. He was found by police after his family reported him missing 8 hours ago. He appeared to be intoxicated and was sleeping in the snow without gloves. On arrival, temperature is 35 C (95 F), blood pressure is 140/86 mm Hg, and pulse is 112/min. The patient is sleepy but arousable to verbal stimuli. Examination shows no signs of trauma to the head or neck. Pupils are equal and reactive to light. Heart and lung sounds are normal. The left hand is pale and cold; the fingers appear grayish, with sensory loss to the level of the metacarpophalangeal joints. Plain radiographs of the hand reveal no fractures. Rewarming with heated blankets and warm intravenous fluids is started immediately; the left hand is submerged in a 38 C (100.4 F) water bath. Thirty minutes later, body temperature is 36.5 C (97.7 F), but there is persistent sensory loss, and the left hand is still grayish. Which of the following is the best next step in management of this patient's condition?

Free
(Multiple Choice)
4.7/5  (81)
(81) Correct Answer: Verified
B
A 56-year-old man comes to the office due to exertional dyspnea for the past month. He has great difficulty walking half a block without experiencing shortness of breath. He also has palpitations, dry cough, and lower extremity swelling. He has no chest pain, lightheadedness, or syncope. The patient was hospitalized 4 months ago for myocardial infarction after having 2 days of chest pain. He also has a history of hypertension, type 2 diabetes mellitus, hyperlipidemia, intermittent asthma, and gout. He is a current smoker with a 35-pack-year history. His father suffered a myocardial infarction at age 50 and died of heart disease at age 55. Blood pressure is 144/86 mm Hg, pulse is 72/min, and oxygen saturation is 96% on room air. BMI is 32 kg/m2. He does not appear to be in acute distress. Physical examination shows distended jugular veins while sitting up. Bibasilar crackles are heard on lung auscultation. There is moderate lower extremity pitting edema. ECG performed in the office is shown in the exhibit. 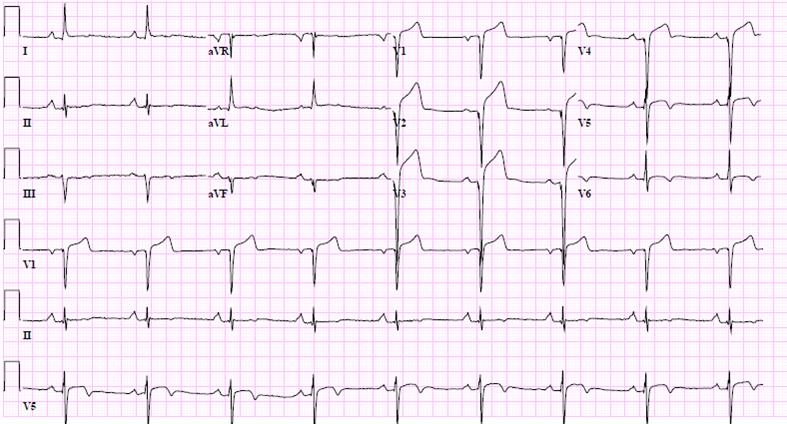 Which of the following is the most likely diagnosis?
Free
(Multiple Choice)
4.9/5 (73)
(73) Correct Answer:Verified
VerifiedB
A 30-year-old man is admitted for observation following a motorcycle collision. He was hemodynamically stable at presentation, and the initial workup revealed an isolated liver laceration. The patient has no chronic medical conditions and takes no medications. He consumes 3-4 alcoholic drinks daily and has been smoking 1 pack of cigarettes daily for the past 10 years. Overnight, his hemoglobin levels acutely decreased, and a packed red blood cell transfusion was ordered. An hour after the transfusion starts, the patient develops difficulty breathing. The transfusion is stopped. Temperature is 36.9 C (98.4 F), blood pressure is 86/42 mm Hg, pulse is 110/min, and respirations are 26/min. Pulse oximetry shows 88% on room air. Lung examination reveals bilateral crackles. Skin examination is normal. Chest x-ray reveals bilateral pulmonary infiltrates. Which of the following is the best next step in management of this patient's respiratory distress?
Free
(Multiple Choice)
5.0/5 (85)
(85) Correct Answer:Verified
VerifiedE
A 65-year-old man is being evaluated in the hospital due to altered mental status and fever. He was admitted 10 days ago for acute pancreatitis secondary to alcohol use. On admission, the patient was afebrile, and CT scan revealed pancreatic edema and necrosis. He has been receiving intravenous fluids and intravenous opioid pain control since then. Today, the patient appears confused and requests more pain medication. Temperature is 38.9 C (102 F), blood pressure is 90/64 mm Hg, pulse is 120/min, and respirations are 22/min. The pupils are 2 mm and symmetric, and the neck is supple. The lungs are clear to auscultation, and heart sounds are normal. Bowel sounds are decreased, but the abdomen is nondistended; there is tenderness to palpation in the epigastrium. The flanks are tympanic to percussion, without any fluid wave. Neurologic examination shows no focal findings. Which of the following is the best next step in management?
(Multiple Choice)
4.8/5 (84)
(84) A 46-year-old man comes to the emergency department for evaluation of left ankle pain. The patient was walking down a flight of stairs when he missed a step and landed on the lateral aspect of his foot. He immediately experienced pain in the ankle that has progressively worsened over the past 4 hours despite ibuprofen and application of ice. The patient's medical conditions include chronic hypertension and hyperlipidemia. Temperature is 36.7 C (98 F), blood pressure is 130/80 mm Hg, and pulse is 76/min. BMI is 29 kg/m2. Examination of the left ankle shows significant bruising over the lateral aspect. Range of motion is limited on external rotation of the foot due to pain. There is no tenderness to palpation over bony prominences of the ankle and sensation is normal. The patient can walk to the examination room but has a significant limp. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (80)
(80) A 58-year-old computer engineer is evaluated for a murmur heard during a routine physical. He has no symptoms and no significant medical history. Specifically, he has no dyspnea, chest pain, syncope, or lower extremity swelling. The patient smokes a cigar and drinks a glass of brandy every Friday night. His lifestyle is mostly sedentary, but he walks for several miles on weekends. Blood pressure is 122/69 mm Hg and pulse is 72/min. There is no jugular venous distension. Vesicular breath sounds are auscultated bilaterally. There is a 3/6 holosystolic murmur best heard at the apex. Echocardiogram shows the mitral valve cusps bulging into the left atrium during systole, and there is severe mitral regurgitation. The left ventricle is dilated with ejection fraction of 52%. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (72)
(72) A 40-year-old man comes to the emergency department with 2 weeks of fever, malaise, weakness, and an unintentional 2.3-kg (5-lb) weight loss. During the last 4 days, he developed left-sided chest and upper abdominal pain. He has asymptomatic mitral valve prolapse. His wife was treated for an upper respiratory infection 3 weeks ago. The patient works for a large corporation and frequently travels to Mexico. He has a 20-pack-year smoking history. He does not use alcohol. His temperature is 39.4 C (103 F), blood pressure is 120/70 mm Hg, pulse is 96/min, and respirations are 16/min. Lung examination shows decreased breath sounds in the left lower lung field with dullness to percussion. Cardiac examination shows a 2/6 systolic murmur at the apex. Laboratory results are as follows:  Imaging studies reveal left-sided pleural effusion and splenomegaly with a splenic fluid collection. Which of the following is the most likely underlying diagnosis in this patient?
 (Multiple Choice)
4.8/5 (92)
(92) A 35-year-old man comes to the emergency department due to right knee pain. The patient was participating in a recreational football game when he jumped to catch a ball and landed with his foot planted and knee partially bent. He heard a loud popping sound, felt immediate pain, and has been unable to walk since. The patient smokes half a pack of cigarettes a day and drinks a few beers on the weekend. BMI is 35 kg/m2. There is a large effusion over the right knee. The patient can bend the right knee but is unable to straighten his leg due to weakness. He is unable to bear weight on the knee but has no instability. X-ray of the right knee shows a large effusion and a low-lying patella with no fractures noted. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
5.0/5 (79)
(79) A 6-year-old boy is brought to the office for follow-up for a limp. His symptoms began 2 months ago as a dull ache in the left knee with an intermittent limp. The parents brought him to an urgent care center at that time and were reassured that the laboratory evaluation and x-rays of the knees and hips were normal. The pain has not worsened, but the patient now has a persistent limp with no other joint or muscle pain. He has been well except for a brief upper respiratory infection with low-grade fever about 2 weeks ago. He has a history of recurrent ear infections and had tympanostomy tubes placed 2 years ago. The patient takes no daily medications, and immunizations are up to date. Temperature is 37.1 C (98.8 F), blood pressure is 95/65 mm Hg, pulse is 80/min, and respirations are 16/min. BMI is at the 60th percentile. Examination shows a well-appearing and alert child. Range of motion, particularly internal rotation and abduction, of the left hip is markedly limited. The remainder of the examination is normal. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
5.0/5 (88)
(88) An 82-year-old man is brought to the emergency department due to fever and confusion. Yesterday, he experienced abdominal pain, nausea, vomiting, and rigors in the nursing home where he lives. Earlier today, he was found to be lethargic. Medical history includes hypercholesterolemia, type 2 diabetes mellitus, and Alzheimer dementia. The patient quit smoking 30 years ago and does not drink alcohol. Temperature is 39.1 C (102.4 F), blood pressure is 105/55 mm Hg, pulse is 110/min, and respirations are 20/min. He is lethargic but arousable to strong stimuli. On examination, the mucous membranes are dry. Scleral icterus is present. No cardiac murmurs are heard. The lungs are clear to auscultation. There is marked tenderness in the right upper quadrant and epigastrium but no distension, rebound, or guarding. Laboratory results are as follows:  An abdominal ultrasound reveals multiple gallstones and a dilated common bile duct. The gallbladder wall is not thickened. In addition to aggressive intravenous hydration and antibiotics, which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (69)
(69) A 26-year-old man comes to the office due to right heel pain and swelling. He accidentally stepped on a rusty nail while working 2 weeks ago. The nail pierced his sneaker and entered his right heel. He applied over-the-counter antibiotic cream and took oral acetaminophen but continued to have pain. The patient has no other medical problems and takes no medications. He has no known drug allergies. He smokes 2 or 3 cigarettes daily and drinks alcohol occasionally. Temperature is 38.3 C (101 F), blood pressure is 140/90 mm Hg, pulse is 84/min, and respirations are 14/min. The right heel is swollen, red, warm, and tender to palpation. A small puncture wound is visible. Laboratory results show mild leukocytosis. X-ray of the right foot reveals bone changes suggestive of osteomyelitis. Which of the following is the most likely organism causing this patient's infection?
(Multiple Choice)
4.8/5 (90)
(90) A 23-year-old man comes to the office for evaluation of right leg pain. The patient underwent a below-knee amputation 4 months ago following a motorcycle collision in which he sustained nonsalvageable devascularization of the right foot. The patient reports having severe postoperative pain and expresses frustration that it hasn't gone away. The pain is shooting in quality and located in the absent portion of the extremity. It is often worse on urination or defecation. Vitals signs are normal. Examination of the right lower extremity shows a well-healed surgical scar and adequate soft tissue padding over the distal bone. The distal stump is nontender to palpation and percussion. Range of motion at the spine, hip, and right knee are full and nonpainful. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (86)
(86) A 40-year-old woman is brought to the emergency department following a low-speed motor vehicle accident. The patient was in the front passenger seat. During the accident, she hit her head against the windshield and hurt her right leg. She appears alert and oriented. Glasgow Coma Scale score is 15/15. Bilateral pupils are equal and reactive to light. There is a bruise over the right forehead, but no tenderness is present on palpation of the cranial bones. Examination of the right leg shows a hematoma over the thigh. Right knee extension and patellar reflex are markedly reduced compared to those on the left. There is decreased sensation to both sharp and dull stimuli over the anterior side of the right thigh and the medial side of the lower leg. All other dermatomes are intact. This patient most likely has an injury to which of the following nerves?
(Multiple Choice)
4.9/5 (82)
(82) An 82-year-old woman is brought to the emergency department due to severe abdominal pain and vomiting. She has been feeling "unwell" with nausea and decreased appetite for the past 5 days. The patient describes several mild, self-resolving episodes of vomiting, abdominal bloating, and cramps during that time. She attributed her symptoms to a "stomach virus" and did not seek medical attention. Her past medical history includes diabetes mellitus, hypertension, mitral valve prolapse, osteoarthritis, gallstones, and constipation. She was treated medically for diverticulitis 2 years ago without recurrence. The patient has no known drug allergies. Her temperature is 37.2 C (99 F), blood pressure is 108/68 mm Hg, pulse is 106/min, and respirations are 20/min. Physical examination reveals an anxious and obese woman. Cardiopulmonary examination reveals a late systolic click but is otherwise unremarkable. Her abdomen is soft but distended with hyperactive bowel sounds. There is no evidence of icterus. Laboratory workup is significant for a leukocyte count of 11,000/mm3 and mild elevation of liver transaminases. Abdominal x-ray shows dilated loops of small bowel and air in the intrahepatic bile ducts. Which of the following is the most likely cause of this patient's symptoms?
(Multiple Choice)
5.0/5 (78)
(78) A 72-year-old man comes to the hospital due to several episodes of bright red blood per rectum. He also has dizziness and severe fatigue. The patient has never had prior episodes of gastrointestinal bleeding. He takes lisinopril and amlodipine for hypertension. The patient is a lifetime nonsmoker. Laboratory evaluation reveals decreased levels of von Willebrand factor multimers but a normal platelet count. Upper endoscopy and colonoscopy do not identify a source of bleeding. Which of the following is most likely associated with this patient's condition?
(Multiple Choice)
4.8/5 (79)
(79) A 34-year-old woman is in the Intensive Care Unit after she jumped out of the third-story window of a burning building. The patient sustained multiple bony fractures and approximately 50% total body surface area burns. The patient is intubated, sedated, and mechanically ventilated. For the first 24 hours after admission, she received aggressive fluid resuscitation that maintained her urine output at an appropriate 0.5 mL/kg/hour. However, over the past couple hours, the patient's urine output has progressively decreased despite additional fluid boluses being given, and she has been difficult to ventilate. In the last hour, urine output was 8 mL. Temperature is 37.2 C (99 F), blood pressure is 132/88 mm Hg, and pulse is 128/min. Peak inspiratory pressure is persistently high at 36 cm H2O (normal: <20-25). On examination, burn dressings are present on all 4 of the patient's extremities and around the patient's abdomen and lower back. Heart and lung sounds are normal. The abdomen is distended and tense to palpation. A urinary catheter is present, with scant yellow urine in the container. Chest x-ray reveals normal endotracheal tube position and no infiltrates. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (80)
(80) An 82-year-old man is found to be agitated and confused on day 2 following surgery for a right hip fracture. The surgery was uncomplicated and was not accompanied by hemodynamic instability. The patient has a history of mild cognitive impairment and lives at home with his daughter. He also has hypertension, gout, and benign prostatic hyperplasia. Temperature is 37.2 C (99 F), blood pressure is 134/90 mm Hg, and pulse is 100/min. The patient has 2 peripheral intravenous lines that appear clean. He does not have a Foley catheter. Lungs are clear on auscultation. Heart rhythm is regular with a faint mid-systolic murmur heard over the left sternal border. The lower abdomen is tender and palpation exacerbates the agitation. The surgical site appears clean with minimal discharge. Laboratory results are as follows:  Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (91)
(91) A 42-year-old obese woman with a history of chronic alcoholism presents with right upper quadrant abdominal pain that began shortly after she had dinner at a local steakhouse. The pain is sharp, rated 7/10 in severity, and radiates to her right scapula. She also complains of nausea and vomiting. Her medical records indicate she has a history of asymptomatic gallstones. She drinks approximately 6 beers a day for the past 20 years but denies tobacco or illicit drug use. Her temperature is 38.5 C (101.3 F), blood pressure is 110/60 mm Hg, pulse is 96/min, and respirations are 16/min. On physical examination, there is right upper quadrant tenderness with deep inspiration. The rest of her examination is within normal limits. Laboratory studies are shown below.  Complete blood count shows leukocytosis with mild left shift. Which of the following is the most likely initial event leading to this patient's symptoms?
 (Multiple Choice)
4.8/5 (86)
(86) A 62-year-old man is evaluated in the burn unit due to progressive confusion, lethargy, and reduced urine output. Five days ago, the patient was hospitalized for a 20% body surface area burn and mild inhalation injury after his house caught fire. He is receiving analgesics, enteral feedings, and intravenous fluids. Temperature is 35.5 C (96 F), blood pressure is 100/60 mm Hg, pulse is 120/min, and respirations are 26/min. Physical examination shows third-degree burns on sections of the bilateral legs and a second-degree burn on the torso. Some areas of partial-thickness injury appear to have progressed to full-thickness necrosis. Laboratory results are as follows: 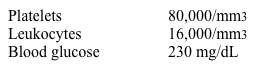 Which of the following is the most likely cause of this patient's current condition?
 (Multiple Choice)
4.7/5 (75)
(75) A 11-year-old girl is brought to the emergency department due to persistent vomiting. The first episode of emesis occurred 12 hours ago, and for the past 4 hours, the patient has been unable to keep any liquids down. She also has nausea and epigastric discomfort but no fever, abdominal distension, or diarrhea. The patient is a competitive gymnast. Yesterday, she fell and struck her abdomen hard on the balance beam during practice. Temperature is 36.7 C (98.1 F), blood pressure is 106/72 mm Hg, pulse is 110/min, and respirations are 18/min. On examination, mucous membranes are dry. Lung and heart sounds are normal. The abdomen is scaphoid with linear bruising across the epigastrium. On palpation, there is epigastric tenderness without guarding, rigidity, or rebound tenderness. Upright chest and abdominal x-rays are normal, with no free air under the diaphragm. Focused assessment with sonography for trauma reveals no intraperitoneal free fluid or air. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (75)
(75) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)