



 Chat with AI
Exam 4: Surgery

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 75-year-old man is brought to the emergency department due to worsening generalized abdominal pain and nausea for the past 2 days. He has multiple chronic medical conditions and resides at a nursing facility. Temperature is 37.2 C (99 F), blood pressure is 128/74 mm Hg, and pulse is 94/min. Abdominal examination shows distension and diffuse tenderness without rigidity or rebound tenderness. Abdominal x-ray is shown in the image below: 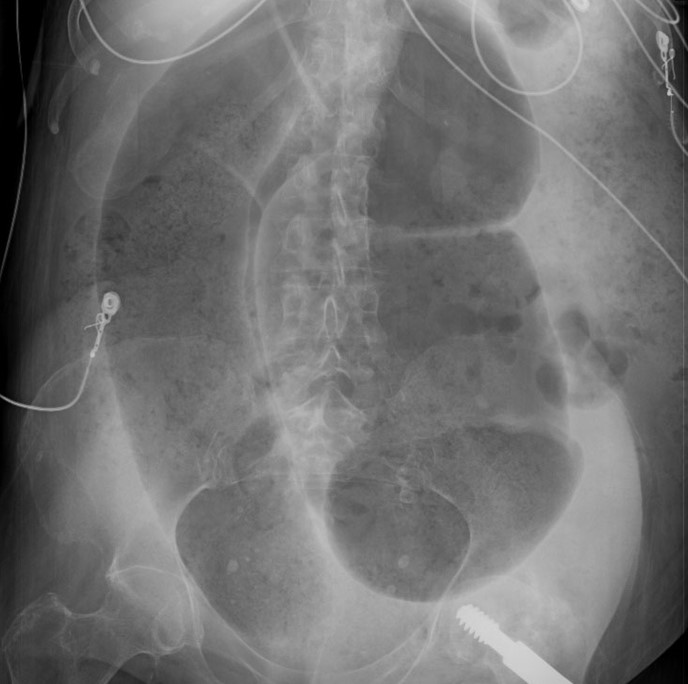 Which of the following factors in this patient's history most likely increased the risk for developing this condition?
 (Multiple Choice)
4.9/5  (79)
(79) A 59-year-old man comes to the office for postoperative follow-up. He underwent a partial (distal) gastrectomy for a perforated peptic ulcer 3 weeks ago. The patient also received an extended course of antibiotics, with the last dose taken 2 weeks ago. For the past 10 days, he has had intermittent abdominal cramps and diarrhea. Symptoms begin 20-30 minutes after the patient eats and are associated with nausea, weakness, palpitations, light-headedness, and diaphoresis. He has no symptoms overnight, and there is no associated fever or weight loss. Medical history is notable for hypertension. The patient has a 20-pack-year smoking history but quit after the recent hospitalization. Temperature is 36.7 C (98 F), blood pressure is 130/65 mm Hg, pulse is 80/min, and respirations are 18/min. BMI is 26 kg/m2. On examination, the abdomen is soft and nontender with normal bowel sounds. The surgical wound is healing well and has no erythema or discharge. Cardiopulmonary examination is normal. Complete blood count is normal. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (76)
(76) A previously healthy 35-year-old man is evaluated in the hospital for new-onset fever. He was admitted 9 days ago following a motorcycle collision that resulted in severe traumatic brain injury and multiple extremity fractures. The patient initially required mechanical ventilation and multiple interventions to lower his intracranial pressure. He has since stabilized and underwent fracture fixation and tracheostomy, with subsequent weaning off of mechanical ventilation. Yesterday, while receiving a sponge bath, the patient was noted to be diaphoretic as well as hypertensive and tachycardic; his symptoms improved after morphine administration. Today, during routine repositioning and vital sign measurement, he again becomes diaphoretic. Temperature is 38.8 C (101.8 F), blood pressure is 194/110 mm Hg, pulse is 146/min, and respirations are 40/min. Oxygen saturation is 98% on room air. On examination, heart sounds and lung sounds are normal. Neurologic examination shows eye opening and withdrawal of all 4 extremities in response to painful stimuli, which is unchanged from previous examinations. Which of the following is the most likely cause of this patient's abnormal vital signs?
(Multiple Choice)
4.8/5 (77)
(77) A 23-year-old man comes to the emergency department due to hemoptysis. The patient has had increasing dyspnea over the past several months. Today, he coughed up approximately 20 mL of blood. He also reports frequent episodes of epistaxis since childhood but has no other medical conditions. The patient does not use tobacco, alcohol, or illicit drugs. Temperature is 37.2 C (99 F), blood pressure is 110/60 mm Hg, and pulse is 98/min. Physical examination shows clear lungs, but there is a faint, continuous bruit on the right infrascapular region. Laboratory evaluation shows microcytic anemia and a normal urinalysis. Chest x-ray reveals several round lung nodules with well-demarcated, smooth borders and no calcifications. Which of the following is the most likely cause of this patient's hemoptysis?
(Multiple Choice)
4.7/5 (81)
(81) A 40-year-old man comes to the emergency department with a week of progressive abdominal discomfort, abdominal distension, and nausea. Over the last 2 days, he has also had several episodes of vomiting. Six weeks ago, he was hospitalized for an episode of acute pancreatitis. The patient used to drink heavily before the hospitalization but has been abstinent since then. He also has a history of emergency department visits due to alcohol intoxication and street fights. The patient does not use tobacco or illicit drugs. His temperature is 37 C (98.6 F), blood pressure is 117/84 mm Hg, pulse is 86/min, and respirations are 16/min. Examination shows epigastric fullness and tenderness. Bowel sounds are present. There is no rebound tenderness or rigidity. Cardiopulmonary examination shows no abnormalities. There is no peripheral edema. Complete blood count and serum chemistries are within normal limits. CT scan of the abdomen with intravenous contrast is shown below. Which of the following is the most appropriate next step in management? 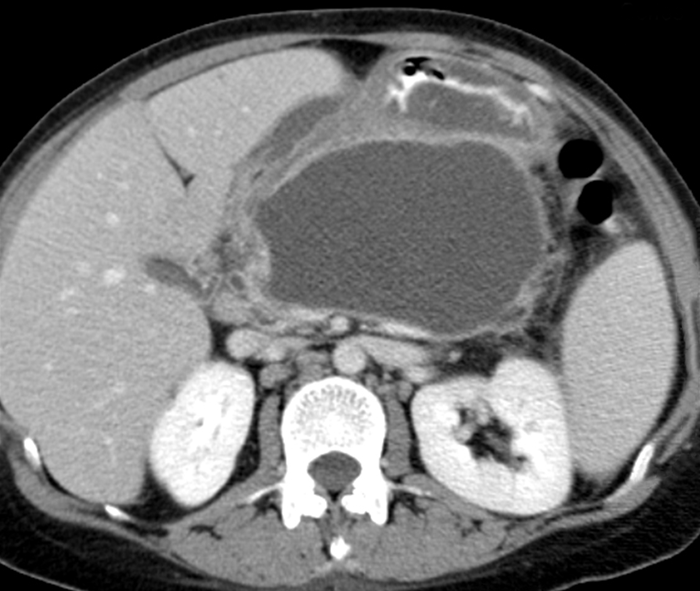
(Multiple Choice)
4.9/5 (86)
(86) A 46-year-old woman comes to the office for evaluation of a rash on her breast. For the past 2 months, the patient has had a pruritic rash on her left breast that has slowly spread. She has had no fever, nipple discharge, or recent changes in soaps or laundry detergent. The patient has used a topical antibiotic ointment and a drying powder over the rash but has had no improvement. She has well-controlled type 2 diabetes mellitus and hypertension. BMI is 37 kg/m2. The left breast is diffusely enlarged with an area of erythema below the areola that extends to the inframammary fold. There are no palpable breast masses. Two nontender lymph nodes are palpated in the left axilla. The remainder of the physical examination is unremarkable. Mammogram a year ago was normal. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.7/5 (83)
(83) A 19-year-old woman, gravida 1 para 0, at 34 weeks gestation is admitted to the hospital for preeclampsia with severe features. She has no chronic medical conditions and takes no medications. On admission, temperature is 36.7 C (98.1 F), blood pressure is 170/110 mm Hg, pulse is 80/min, and respirations are 16/min. While administering the magnesium sulfate bolus, the fetal heart rate becomes persistently bradycardic to the 90s. The patient is rushed to the operating room for an emergency cesarean delivery and undergoes general anesthesia. Immediately after intubation, intraoperative temperature is 39.4 C (102.9 F), blood pressure is 180/110 mm Hg, pulse is 130/min, and respiratory rate is 30/min. The patient is markedly rigid and increasingly difficult to ventilate. Which of the following is the most likely cause of this patient's acute decompensation?
(Multiple Choice)
4.7/5 (93)
(93) A 22-year-old woman comes to the office for evaluation of new-onset foot pain. The pain is located at the heel and is most pronounced when she gets up from sitting after a long period of time. The patient is a collegiate soccer player who plays both indoor and outdoor soccer. In addition, she enjoys trail running and occasionally runs barefoot along the beach. Physical examination of the foot shows a moderately high arch with no discoloration or deformity. Direct pressure to the bottom of the heel elicits sharp pain, but mediolateral squeezing of the heel causes no discomfort. Which of the following is the most likely etiology of the patient's foot pain?
(Multiple Choice)
4.7/5 (89)
(89) A 65-year-old woman comes to the office due to feeling her heart race, even while she is at rest. She has had multiple episodes like this over the past 2 weeks, lasting anywhere from a few minutes to a couple of hours and associated with lightheadedness. The patient's other medical conditions include obesity, type 2 diabetes mellitus, hypertension, and gastroesophageal reflux disease. She smoked a pack of cigarettes daily from age 16 to 35. Vital signs are normal except for an irregularly irregular pulse. The patient is diagnosed with atrial fibrillation and given anticoagulation and rate control medication. In preparation for cardioversion, she undergoes transesophageal echocardiography, which rules out a mural thrombus. That evening, the patient develops severe chest and interscapular back pain. Temperature is 38.9 C (102 F), blood pressure is 100/70 mm Hg, and pulse is 108/min. The patient is in distress and restless. Heart and lung sounds are normal. ECG shows sinus tachycardia without ST segment changes. Chest x-ray reveals a widened mediastinum. Stool testing for occult blood is negative. Which of the following is the best next step to diagnose this patient's condition?
(Multiple Choice)
4.8/5 (75)
(75) A 67-year-old woman comes to the office due to knee pain. For the past year, she has had gradually increasing pain in the left knee that is worse with prolonged walking or climbing stairs. The patient has also had brief (5-10 min) stiffness in the knee when she first rises from bed in the morning. She reports minimal pain at rest and no nocturnal pain. There are no clicking or locking symptoms. Her pain is relieved with topical diclofenac but recurs if the patient does not use it regularly. Vital signs are normal. Examination shows slightly reduced flexion at the left knee compared to the right. No joint tenderness, warmth, or palpable effusion is present. There is no laxity with varus or valgus stress or with anterior or posterior traction on the proximal tibia. X-ray of the knee is shown in the image below: 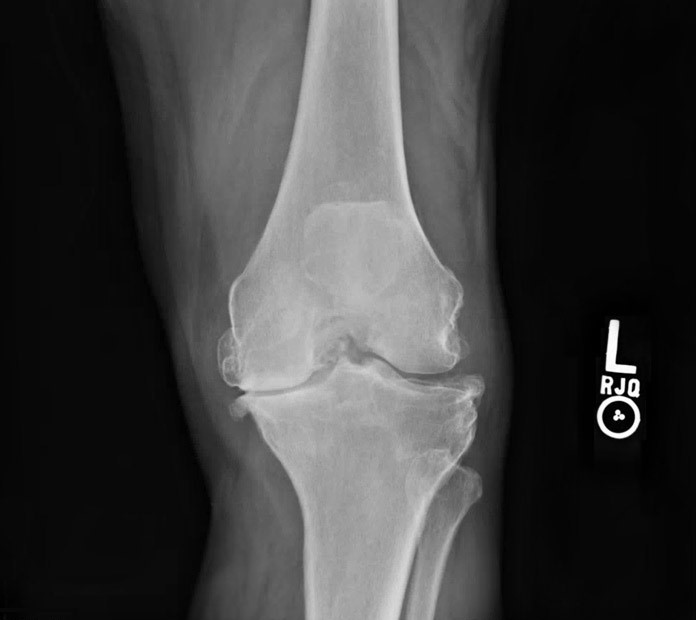 Which of the following is the most appropriate next step in management of this patient's knee pain?
 (Multiple Choice)
4.9/5 (67)
(67) A 41-year-old man comes to the office due to abdominal pain and distension. Over the past 2 months, the patient has noted constant, gnawing epigastric pain that intensifies after meals. More recently, his abdomen has become progressively enlarged and uncomfortable. The patient has been admitted to the hospital multiple times due to alcohol-related intoxication and seizures. He does not use tobacco or intravenous drugs. Family history is unremarkable. Temperature is 37.7 C (99.9 F), blood pressure is 132/78 mm Hg, and pulse is 80/min. Mental status is normal, and cardiopulmonary examination is unremarkable. The abdomen is grossly distended and mildly tender to palpation in the epigastric region. Shifting dullness is present. A diagnostic paracentesis is performed, which reveals serosanguinous fluid. Analysis of this fluid shows high levels of both total protein and amylase. Serum albumin is 3.4 mg/dL. Which of the following is the most likely explanation for this patient's presentation?
(Multiple Choice)
4.8/5 (66)
(66) A 30-year-old man comes to the office for follow-up after traumatic injury to his left eye. Two months ago, there was an explosion at the factory where he worked. A large piece of shrapnel penetrated his left eye. Surgical removal of the shrapnel was performed, and vision in the left eye recovered to 20/200. Today, the patient reports that vision in his right eye is becoming blurry. On examination, there is bilateral conjunctival erythema. The right eye visual acuity is 20/160, which was normal 2 months ago. Which of the following is most likely involved in the pathogenesis of this patient's current ocular condition?
(Multiple Choice)
4.8/5 (79)
(79) A 29-year-old woman comes to the office to establish care. The patient feels well overall but has had 4-5 loose bowel movements a day with mild, cramping abdominal pain. She has no weight loss, bloody stools, vomiting, rashes, or joint pain. Medical history is significant for long-standing Crohn disease that required an ileocolectomy 3 years ago. The patient has been taking adalimumab and azathioprine since the surgery. In addition to Crohn disease, she has type 2 diabetes, morbid obesity, and generalized anxiety disorder. The patient frequently consumes fast food and rarely eats fruits, vegetables, or whole wheat bread. She has smoked both cigarettes and marijuana for the past 15 years. Temperature is 37.5 C (99.5 F), blood pressure is 132/89, pulse is 80/min, and respirations are 12/min. BMI is 41 kg/m2. Oropharyngeal examination reveals moist mucosal membranes and no mouth ulcers. Heart and lung sounds are unremarkable. The abdomen has a well-healed laparoscopic scar but is otherwise nontender and nondistended. Which of the following is most strongly associated with progression of this patient's Crohn disease?
(Multiple Choice)
4.9/5 (68)
(68) A 68-year-old man is brought to the hospital due to acute fever, malaise, lower abdominal discomfort, and right flank pain. Six months ago, he was hospitalized for similar symptoms and was diagnosed with a urinary tract infection; at that time, his urine culture grew Escherichia coli, and his symptoms completely resolved with antibiotic therapy. Over the past year, the patient has experienced frequent nighttime urination and dribbling but no gross hematuria. Medical history is significant for major depressive disorder and mild idiopathic pulmonary fibrosis. Temperature is 38.7 C (101.7 F), blood pressure is 130/80 mm Hg, and pulse is 98/min. The patient appears acutely ill. Bilateral basal crackles are present. There is right costovertebral angle tenderness. Laboratory results are as follows:  Which of the following is the most likely underlying cause of the patient's current condition?
 (Multiple Choice)
5.0/5 (94)
(94) A 70-year-old man comes to the emergency department due to a 4-day history of fever, shortness of breath, and right-sided pleuritic chest pain. Medical history is significant for type 2 diabetes mellitus and hypercholesterolemia. Temperature is 38.7 C (101.7 F), blood pressure is 128/78 mm Hg, pulse is 98/min, and respirations are 20/min. Decreased breath sounds and dullness to percussion are noted in the right lower lung field. Chest x-ray reveals a right lower lobe infiltrate and a pleural effusion. Ultrasound examination reveals the pleural effusion is free flowing without loculation. Thoracentesis is performed, and Gram stain of the fluid shows segmented neutrophils and gram-positive cocci in pairs. Cultures of the fluid, blood, and sputum are pending. In addition to systemic antibiotic therapy, which of the following is the most appropriate next step in management?
(Multiple Choice)
4.7/5 (70)
(70) A 52-year-old hospitalized patient is evaluated for chest pain and persistent tachycardia. She was recently diagnosed with colon adenocarcinoma and underwent right hemicolectomy and ileocolic anastomosis 5 days ago. Yesterday, the patient was noted to be tachycardic and hypoxemic during physical therapy, and the tachycardia persisted at rest. She also has had shortness of breath and intermittent, right-sided chest pain. The patient is not using the incentive spirometer as frequently as advised. She is taking a liquid diet without significant abdominal pain or nausea but has had no bowel movements. Current medications are prophylactic-dose low molecular weight heparin and an opioid analgesic as needed. Temperature is 37.8 C (100 F), blood pressure is 116/72 mm Hg, pulse is 112/min, and respirations are 20/min. Oxygen saturation is 94% on 2 L/min oxygen by nasal cannula. On physical examination, the patient appears slightly uncomfortable and speaks in short sentences. Lung auscultation shows decreased breath sounds over the posterior right base. Cardiac examination reveals a regular rhythm without murmurs or gallops. The abdomen is soft with normal bowel sounds, and there is no erythema, drainage, or dehiscence of the surgical incision. There is mild, bilateral lower extremity pitting edema. ECG shows sinus tachycardia, and chest x-ray reveals right basal atelectasis. Which of the following is the best next step in the management of this patient?
(Multiple Choice)
5.0/5 (98)
(98) A 31-year-old nulligravida woman comes to the office for preconception counseling after a murmur was found on her routine physical examination. Her lifestyle is sedentary, and she reports shortness of breath on moderate exertion. She emigrated from Brazil at age 25. The patient does not use tobacco or alcohol. She was married 6 months ago and is planning to have a child "very soon." Blood pressure is 112/72 mm Hg, and pulse is 67/min and regular. BMI is 29 kg/m2. Transthoracic echocardiogram reveals mitral leaflet restriction with an estimated mitral valve area of 1.2 cm2 (normal: 4-6). The mitral leaflets and subvalvular apparatus are not significantly thickened, and there is minimal calcification. There is minimal mitral regurgitation. The rest of the examination is unremarkable. Which of the following is the best recommendation for this patient?
(Multiple Choice)
4.9/5 (92)
(92) A 24-year-old man is brought to the emergency department after being shot during a street fight. On the way to the hospital, the patient became obtunded and required intubation. He also received 2 L of normal saline. On arrival, blood pressure is 86/40 mm Hg and pulse is 130/min. The trachea is midline, and breath sounds are equal bilaterally. Heart sounds are normal. Two gunshot wounds are present: one in the left sixth intercostal space just lateral to the midclavicular line and another in the left seventh intercostal space posteriorly. Portable chest x-ray shows irregular opacities at the left lung base. Focused Assessment with Sonography for Trauma reveals no pericardial effusion and is equivocal for intraperitoneal free fluid. Transfusion of uncrossmatched blood is pending. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (73)
(73) A 50-year-old woman comes to the emergency department due to increasing right flank pain, nausea, and hematuria. The flank pain started 3 days ago and is constant, dull, and nonradiating. She reports no dysuria. The patient was diagnosed with pancreatic cancer a month ago and received the first cycle of chemotherapy 2 weeks ago. She has smoked a pack of cigarettes daily for 30 years but does not use alcohol. Temperature is 37 C (98.6 F), blood pressure is 130/90 mm Hg, pulse is 88/min, and respirations are 16/min. Examination shows right flank and costovertebral angle tenderness. Bowel sounds are present. Peripheral pulses are normal and there is no edema. Laboratory results are as follows:  Abdominal ultrasound shows an enlarged right kidney and normal left kidney; there is no evidence of hydronephrosis. The pancreatic mass is unchanged from prior scans. Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (80)
(80) A 10-year-old boy is brought to the emergency department due to postprandial abdominal pain and bilious emesis. He has never had similar symptoms and has no other medical conditions. Two days ago, the patient stopped his bicycle abruptly and slammed into the handlebar. He immediately experienced abdominal pain, which improved over the next several hours. Vital signs are normal. Physical examination shows epigastric tenderness without rigidity or rebound tenderness. Bowel sounds are normal. Bedside ultrasonography reveals no intraperitoneal free fluid. Plain abdominal radiograph shows gastric dilation with scant distal gas. Laboratory results are as follows:  Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (77)
(77) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)