



 Chat with AI
Exam 4: Surgery

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 38-year-old man comes to the emergency department due to a day of progressive shortness of breath. Over the past week, he has also had fever and malaise. The patient uses intravenous heroin daily. Temperature is 39.6 C (103.3 F), blood pressure is 100/56 mm Hg, pulse is 102/min and regular, and respirations are 20/min. Oxygen saturation is 93% on room air. The patient is in moderate respiratory distress. Bibasilar crackles are heard on lung auscultation. Cardiac examination reveals a 3/6 holosystolic murmur that radiates to the left axilla. There is 1+ bilateral pedal edema. Laboratory evaluation shows a hematocrit of 33% and a leukocyte count of 19,000/mm3 with a left shift. ECG reveals sinus tachycardia. Chest x-ray reveals pulmonary edema and no cardiomegaly. Echocardiography demonstrates a 1-cm vegetation on the mitral valve and severe mitral regurgitation. Blood cultures are drawn, and empiric broad-spectrum antibiotics are initiated. Oxygen is also administered via nasal canula. What is the most appropriate next step in management?
(Multiple Choice)
4.9/5  (85)
(85) A 22-year-old man comes to the emergency department due to sudden-onset dyspnea 2 hours ago while watching television. The patient's dyspnea is gradually improving but he still has sharp right-sided chest pain that is worse with deep inspiration or cough. His medical history is unremarkable. The patient smokes 4-5 cigarettes daily and occasionally drinks alcohol. Temperature is 36.7 C (98 F), blood pressure is 140/80 mm Hg, pulse is 86/min, and respirations are 18/min. Pulse oximetry shows 98% on room air. He weighs 68 kg (150 lb), is 188 cm (6 ft 2 in) tall, and has a BMI of 19.3 kg/m2. Physical examination is unremarkable. Chest x-ray reveals a small right apical pneumothorax. Which of the following is the most appropriate management of this patient?
(Multiple Choice)
4.8/5 (71)
(71) A 28-year-old man is the unrestrained driver in a motor vehicle collision. He is conscious immediately after the collision and refuses transfer to a hospital for detailed evaluation. Two hours later, he is brought to the emergency department due to progressively worsening mental status. Systolic blood pressure is 60 mm Hg, pulse is 130/min, and respirations are 30/min. On examination, the patient is stuporous and responsive only to noxious stimuli. There are bruises over the extremities and upper abdomen. The trachea is midline, neck veins are flat, and abdomen is distended but nontender. Large-bore peripheral intravenous lines are secured to begin fluid resuscitation while the trachea is intubated. Immediately after the patient is placed on mechanical ventilation, the cardiac monitor shows asystole and no pulse is palpable. Which of the following is the most likely underlying mechanism leading to cardiac arrest in this patient?
(Multiple Choice)
4.7/5 (93)
(93) A 70-year-old man comes to the hospital due to worsening right upper quadrant pain, fever, and anorexia for the past 2 days. Today, he also developed chills. The patient was treated for acute diverticulitis 4 weeks ago. Medical conditions also include type 2 diabetes mellitus and hypertension. He does not use tobacco, alcohol, or illicit drugs. The patient has not traveled recently. Temperature is 39.3 C (102.7 F), blood pressure is 130/80 mm Hg, pulse is 98/min, and respirations are 18/min. Examination shows no jaundice. The right upper quadrant is markedly tender with some guarding on palpation. Bowel sounds are normal, and there is no ascites. Laboratory results are as follows:  CT scan of the abdomen is shown in the exhibit:
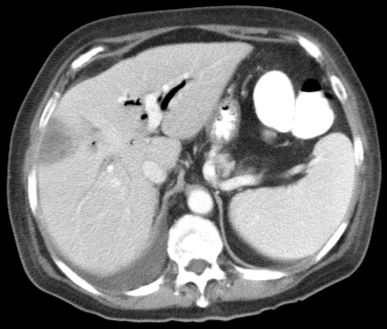 Blood cultures are obtained. Which of the following is the best next step in diagnosis?
CT scan of the abdomen is shown in the exhibit:
Blood cultures are obtained. Which of the following is the best next step in diagnosis? (Multiple Choice)
4.8/5 (77)
(77) A 22-year-old man is brought to the emergency department after a high-speed motor vehicle collision. Blood pressure is 102/60 mm Hg, pulse is 122/min, and respirations are 40/min. Pulse oximetry is 88% on 6 L oxygen. The patient is alert but appears to be in respiratory distress. Breath sounds are diminished bilaterally, and bilateral chest tubes are placed. The patient's respiratory status initially improves; however, over the next hour, he develops respiratory failure, requiring intubation and mechanical ventilation. Postintubation chest x-ray is shown below. 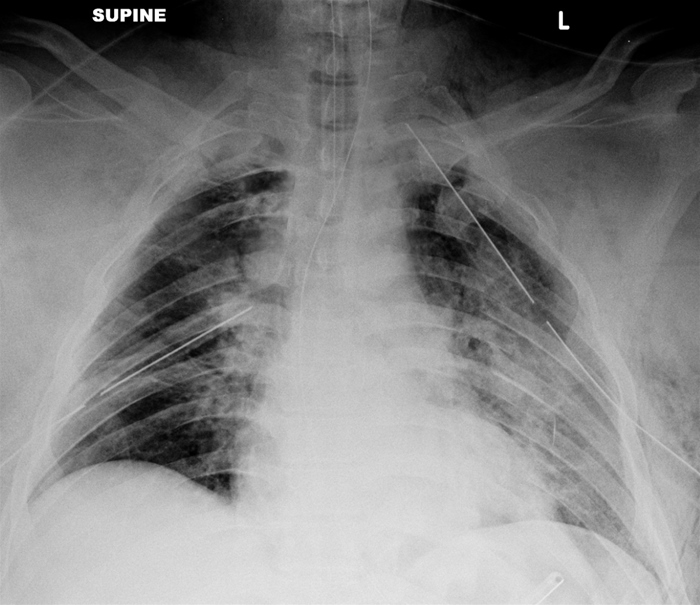 Which of the following is the most likely cause of this patient's need for mechanical ventilation?
 (Multiple Choice)
4.9/5 (71)
(71) A 63-year-old man comes to the office for evaluation of a left breast mass. The patient noticed a small lump in the left breast a few months ago after he was struck in the chest. He expected the lump to disappear, but it has since enlarged and becomes irritated by the heavy protective vest he wears while working as a corrections officer. Medical history is significant for obesity, hypertension, and obstructive sleep apnea. Physical examination shows an obese habitus with increased fatty breast tissue bilaterally. There is a 2-cm firm, fixed, nontender subareolar mass in the left breast with nipple inversion. The right breast has no discrete masses. There is no axillary or supraclavicular lymphadenopathy. The rest of the physical examination is unremarkable. Which of the following is the best next step in management of this patient?
(Multiple Choice)
5.0/5 (73)
(73) A 21-year-old soldier comes to the medical clinic due to right foot pain. She is in her second month of basic training and has had pain for the last 3 weeks. The patient has no history of acute trauma. The pain initially occurred only with activity but is now present even at rest. Medical history is unremarkable, and she takes no medications. Vital signs are normal. Examination shows swelling and warmth in the foot and point tenderness over the second metatarsal. Plain films of the foot show a hairline fracture of the shaft of the second metatarsal. Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.8/5 (64)
(64) A 63-year-old man with chronic obstructive pulmonary disease comes to the emergency department due to 3 days of increasing dyspnea after running out of his maintenance and rescue inhalers. At first, he had dyspnea with exertion only, but it is now present at rest and associated with wheezing and a nonproductive cough. Chest x-ray reveals lung hyperinflation but no infiltrates. The patient is admitted to the medical floor and started on appropriate therapy. He does not respond to treatment; therefore, he is intubated and mechanically ventilated for worsening hypercapnia and increased work of breathing. Following intubation, portable chest radiograph confirms appropriately positioned endotracheal tube with no infiltrates, effusions, or pneumothorax. Which of the following interventions would be most likely to prevent this patient from developing ventilator-associated pneumonia?
(Multiple Choice)
4.8/5 (80)
(80) A 26-year-old man comes to the emergency department due to 6 weeks of intermittent lower abdominal pain and cramps accompanied by rectal urgency, bloody diarrhea, nausea, and decreased appetite. His symptoms have become more severe over the past 2 days. The patient has never traveled outside the country and has not been prescribed antibiotics recently. Temperature is 38.5 C (101.3 F), blood pressure is 90/50 mm Hg, pulse is 130/min, and respirations are 15/min. The patient is ill appearing and lethargic. Bowel sounds are decreased. The abdomen is distended, tympanic to percussion, and diffusely tender to palpation; rebound tenderness and muscle rigidity are absent. Rectal examination shows marked tenderness and mucus mixed with blood in the vault. Laboratory results are as follows:  Intravenous fluids are started, with improvement of blood pressure to 104/58 mm Hg and pulse to 108/min. Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.8/5 (89)
(89) A 45-year-old man comes to the emergency department due to 3 weeks of fever, malaise, and cough productive of foul-smelling, purulent sputum. Six weeks ago, the patient was hospitalized after sustaining a head injury during a motor vehicle collision; he briefly required intubation and was discharged from the hospital 4 weeks ago. He does not use tobacco, alcohol, or illicit drugs. Temperature is 39.1 C (102.3 F), blood pressure is 120/74 mm Hg, pulse is 110/min, and respirations are 14/min. Laboratory studies reveal a hemoglobin of 12.5 g/dL and leukocyte count of 18,000/mm3. X-ray of the chest is shown in the exhibit. 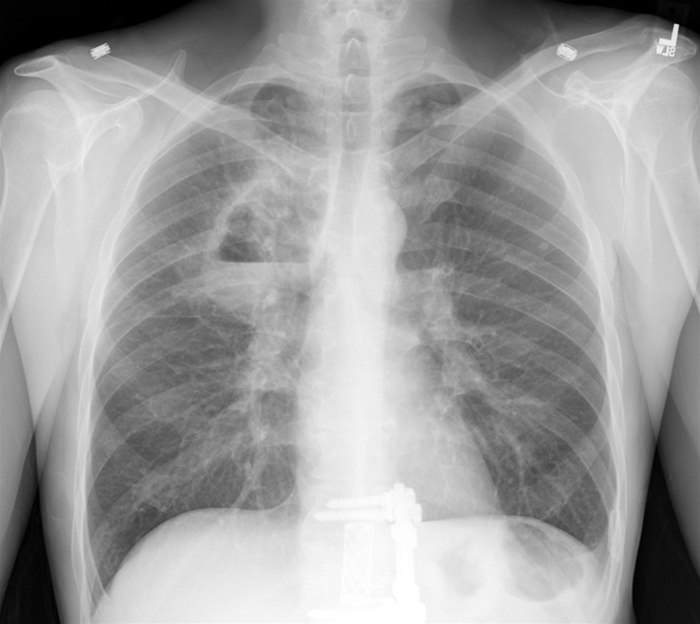 Sputum cultures are obtained. Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.8/5 (77)
(77) A 64-year-old man with a history of coronary artery disease and peripheral vascular disease undergoes coronary artery bypass surgery. His postoperative course is complicated by hypotension, which is treated successfully with intravenous fluids; however, a few hours later, he experiences abdominal pain followed by bloody diarrhea. His temperature is 37.8 C (100 F), blood pressure is 110/60 mm Hg, pulse is 110/min, and respirations are 20/min. Abdominal examination shows normal bowel sounds, with no significant guarding or focal tenderness. Laboratory results are as follows:  The venous lactic acid level is elevated. An abdominal CT scan is ordered. Which of the following areas will most likely show abnormal findings?
 (Multiple Choice)
4.7/5 (81)
(81) A 56-year-old man is brought to the emergency department by a friend after vomiting bright red blood several times during the past 2 hours. The patient has no abdominal pain or diarrhea. He has a history of peptic ulcer disease and alcoholic cirrhosis. His friend says that the patient continues to drink alcohol and is not sure whether he is taking his medications regularly. Temperature is 37.6 C (99.7 F), blood pressure is 96/62 mm Hg, and pulse is 112/min. The patient has muscle wasting and scleral icterus. The abdomen is nontender and distended with bulging flanks. Rectal examination shows internal hemorrhoids and maroon stool that is positive for occult blood. He is receiving a normal saline infusion through a peripheral intravenous catheter. Which of the following is the best next step in management of this patient?
(Multiple Choice)
5.0/5 (79)
(79) A 19-year-old man is brought to the emergency department by ambulance after a motor vehicle collision. The accident occurred 1 hour ago when his vehicle spun out of control and rolled over. He was wearing his seatbelt and his airbag deployed. The patient is alert and reports abdominal pain. Blood pressure is 110/70 mm Hg, pulse is 106/min, and respirations are 16/min. On examination, lungs are clear to auscultation bilaterally and the chest wall is nontender. Heart sounds are normal. The abdomen is nondistended with tenderness to palpation in the left upper quadrant. There are no gross deformities of the extremities. A Focused Assessment with Sonography for Trauma (FAST) examination reveals free fluid in the left subphrenic space. Which of the following is the best next step in management?
(Multiple Choice)
4.9/5 (83)
(83) A 37-year-old man comes to the emergency department due to 2 days of progressive, colicky abdominal pain, abdominal distension, nausea, and vomiting. He had a similar episode 2 years ago that resolved spontaneously and did not require medical attention. He has no chronic medical conditions. Temperature is 36.8 C (98.2 F), blood pressure is 122/80 mm Hg, and pulse is 92/min. The abdomen is distended and tender without rigidity or guarding. Abdominal x-ray is shown in the image below: 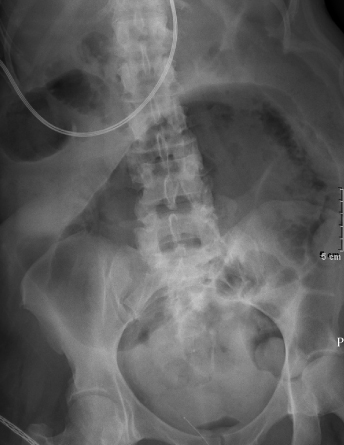 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (72)
(72) A 67-year-old man was hospitalized yesterday following elective right knee arthroplasty for osteoarthritis. Medical history is notable for hypertension, type 2 diabetes, and coronary artery disease; the patient is receiving chronic antiplatelet therapy with clopidogrel, which was stopped 5 days prior to surgery. The procedure was performed under anesthesia via epidural and femoral nerve block, and no intraoperative complications were noted. Following surgery, patient-controlled analgesia was provided for pain control, and prophylactic enoxaparin was given beginning 12 hours after surgery completion. Today, the patient has had difficulty urinating after removal of the urinary catheter, as well as low back pain and numbness in the legs. Examination shows tenderness at the insertion site of the epidural catheter. The knee incision is clean with no bleeding or drainage. There is weakness of right plantar flexion and dorsiflexion. Sensation is decreased in the anterior thigh and leg bilaterally. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (75)
(75) A 58-year-old man comes to the emergency department due to sudden onset of severe right leg pain several hours ago; the leg has since become numb. He has never had similar symptoms and has no history of trauma, fever, or chills. The patient recently had an acute anterior wall myocardial infarction that resulted in cardiogenic shock; he is undergoing cardiac rehabilitation. Temperature is 36.7 C (98.1 F), blood pressure is 120/70 mm Hg, pulse is 90/min and regular, and respirations are 16/min. Cardiopulmonary examination is unremarkable. Compared with the left leg, the right leg appears pale and is cool to the touch. In the right lower extremity, the popliteal pulse is normal, but more distal pulses are not palpable. Pulses in the other extremities are normal. Neurologic examination shows loss of sensation over the dorsum of the right foot and mild weakness with dorsiflexion. Which of the following is the most likely cause of this patient's symptoms?
(Multiple Choice)
4.9/5 (81)
(81) A 19-year-old man comes to the office due to a change in bowel habits. Six months ago, the patient began having loose, watery stools with increased frequency to approximately 5 times daily. In addition, he has had crampy, intermittent abdominal pain that usually improves after defecation. No nausea, vomiting, melena, fevers, night sweats, or weight loss has occurred. The patient vacationed in South America 12 months ago. He does not use tobacco or alcohol. Temperature is 37.4 C (99.3 F), blood pressure is 138/87 mm Hg, pulse is 75/min, and respirations are 12/min. The patient appears comfortable and is not in acute distress. There is no conjunctival pallor, scleral icterus, or palpable lymphadenopathy. Cardiopulmonary examination is unremarkable. The abdomen is nontender and nondistended. Rectal examination reveals scant blood in the stool but no hemorrhoids or fissures. Laboratory results are as follows:  Stool studies are negative for ova and parasites as well as Clostridioides (formerly Clostridium) difficile. Which of the following is the best next step in management?
 (Multiple Choice)
4.8/5 (94)
(94) A 34-year-old man is being discharged from the hospital after treatment for splenic rupture and intraabdominal bleeding following blunt abdominal trauma. His postoperative course was uncomplicated. The patient has no other chronic medical conditions and previously took no medications. He has no known drug allergies. Vital signs are normal. Abdominal examination shows a well healing incision. Appropriate vaccinations are planned for the first follow-up appointment in 2 weeks. Which of the following antibiotics should be prescribed for this patient to take immediately if he develops a fever?
(Multiple Choice)
4.8/5 (78)
(78) A 46-year-old man is brought to the emergency department after a fall during a downhill bicycle race. The patient lost consciousness for approximately 1 minute and has severe back and abdominal pain. He has no other medical conditions. CT scan of the head reveals no intracranial bleeding; CT scan of the abdomen reveals a small retroperitoneal hemorrhage and splenic laceration. Lumbar film suggests a compression wedge fracture of the L2 vertebral body, and a brace is placed. The patient is conservatively managed with analgesics and supportive measures. On hospital day 3, he has mild, diffuse abdominal pain and nausea. His abdomen is distended, tympanic, and mildly tender without rebound or guarding. Bowel sounds are absent. Upright x-ray of the abdomen is shown in the image below: 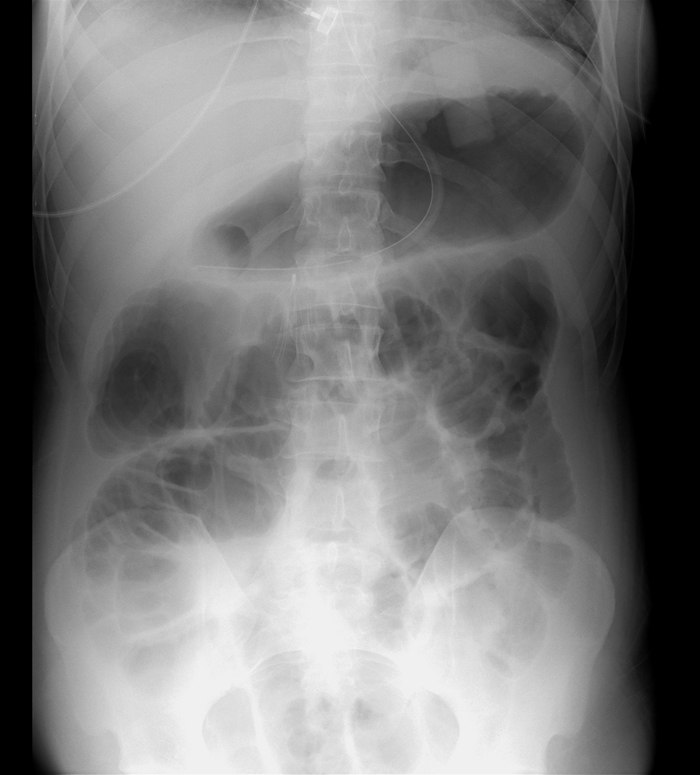 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (78)
(78) A 38-year-old woman comes to the hospital due to right upper quadrant pain associated with nausea and vomiting for the past 12 hours. She has had similar pain previously, usually after the ingestion of fatty foods, but past episodes have always resolved within 1-2 hours. Past medical history includes hypertriglyceridemia, for which she takes fenofibrate. The patient's temperature is 38.3 C (101 F), blood pressure is 130/70 mm Hg, pulse is 98/min, and respirations are 20/min. Her BMI is 34 kg/m2. Examination shows right upper quadrant tenderness. Laboratory results are as follows:  Abdominal ultrasound reveals gallstones, a thickened gallbladder wall with edema, and a normal common bile duct. In addition to the supportive care, which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.8/5 (75)
(75) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)