



 Chat with AI
Exam 4: Surgery

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 21-year-old woman comes to the office for evaluation of progressively increasing dyspnea and nonproductive cough for the past 2 weeks. Four months ago, the patient underwent bilateral lung transplantation for bronchiectasis due to underlying cystic fibrosis. Other medical conditions include pancreatic insufficiency and osteoporosis. Current medications are pancreatic enzymes, multivitamins, tacrolimus, mycophenolate mofetil, and prednisone. Temperature is 38 C (100.4 F), blood pressure is 110/78 mm Hg, pulse is 96/min, and respirations are 18/min. Pulse oximetry shows 98% with the patient using 2 liters/min of supplemental oxygen. Examination shows bilateral lung crackles. Chest x-ray reveals perihilar opacities, interstitial edema, and small bilateral pleural effusions. What is the most appropriate next step in management?
(Multiple Choice)
4.9/5  (62)
(62) A 72-year-old man comes to the office due to upper abdominal pain and weight loss. The abdominal pain is worse when eating food and is sometimes relieved with over-the-counter antacids. He has not had dysphagia, melena, or rectal bleeding. The patient has a history of hypertension, which is well controlled with chlorthalidone. He does not take other prescription or over-the-counter medications and does not use tobacco, alcohol, or illicit drugs. The patient emigrated from South Korea 20 years ago. Temperature is 36.8 C (98.2 F), blood pressure is 110/70 mm Hg, pulse is 84/min, and respirations are 14/min. BMI is 17.2 kg/m2. Mucous membranes are dry. Cardiopulmonary examination shows no abnormalities. Epigastric fullness and tenderness are present, but there is no hepatosplenomegaly. Peripheral pulses are full and capillary refill is normal. Which of the following is the best next step in management?
(Multiple Choice)
4.9/5 (73)
(73) A 70-year-old woman comes to the office for routine evaluation. The patient feels well and has had no shortness of breath, fatigue, dizziness, chest pain, unexpected weight changes, or bloody stools. Medical history is significant for constipation-predominant irritable bowel syndrome, hypertension, and diabetes mellitus. Temperature is 37.1 C (98.8 F), blood pressure is 138/86 mm Hg, pulse is 85/min, and respirations are 12/min. Mild conjunctival pallor is noted. Heart and lung sounds are unremarkable. The abdomen is soft, nontender, and nondistended. Rectal examination shows external hemorrhoids, and fecal occult blood testing is positive. Complete blood count reveals a hemoglobin level of 10.5 g/dL. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (84)
(84) A 13-year-old boy is seen in the office for persistent right knee pain. He first noticed a dull pain along the anterior knee 2 months ago. Initially, the pain was noticeable only after basketball practice. Two days ago, the pain worsened after the patient landed during a rebound attempt at a basketball game. The knee pain is now constant and not relieved with ibuprofen or ice. The patient has no chronic medical conditions. Temperature is 37.4 C (99.3 F). Height is at the 75th percentile, and weight is at the 95th percentile. The patient walks with a limp with the right foot pointed laterally. There is no tenderness, erythema, or swelling around the right knee. The anterior and posterior drawer tests are normal. No abnormal findings during knee flexion and extension are present with either internal or external rotation of the tibia. Range of motion of the right hip is limited, and the knee points laterally upon passive hip flexion. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (82)
(82) A 44-year-old previously healthy woman comes to the office due to 2 months of low-grade fever, abdominal pain, and intermittent bloody diarrhea. Her pain has dramatically increased over the past 48 hours. The patient takes no medications and has no allergies. She has lost 4.5 kg (10 lb) over the past 8 weeks. She has no recent travel history. Temperature is 38.9 C (102 F), blood pressure is 102/70 mm Hg, pulse is 118/min, and respirations are 22/min. Examination shows pale and dry mucous membranes. Abdominal examination reveals distension and diffuse tenderness. Laboratory results are as follows:  HIV test is negative. X-ray of the abdomen is shown below:
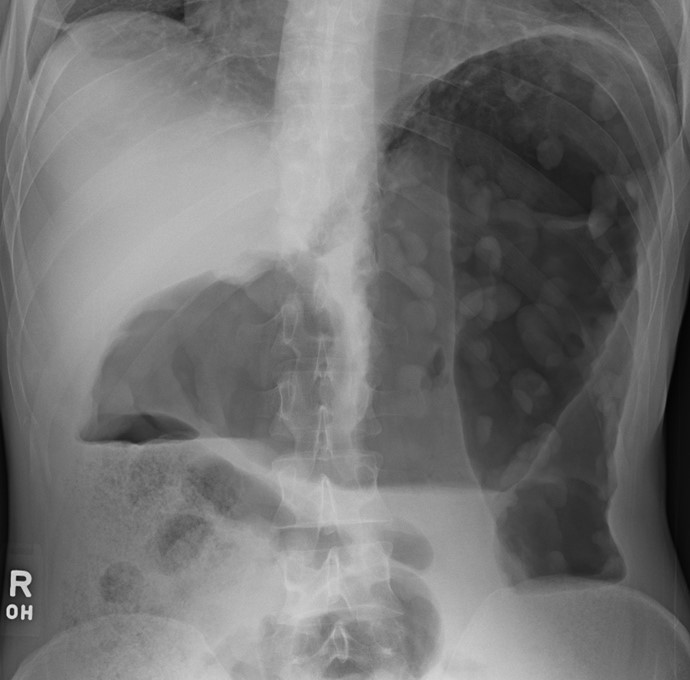 Which of the following interventions is indicated at this time?
HIV test is negative. X-ray of the abdomen is shown below:
Which of the following interventions is indicated at this time? (Multiple Choice)
4.8/5 (75)
(75) A 42-year-old woman comes to the emergency department due to diffuse abdominal pain. The pain began 6 hours ago while the patient was playing tennis. She reports that the pain started suddenly in the right lower abdomen and has become diffuse and radiates to her right shoulder. The patient has never had this pain before and has no previous trauma. Two months ago, she was hospitalized for a deep venous thrombosis; the patient had been taking combination oral contraceptives, which were discontinued immediately. She has since been taking an oral anticoagulant daily. The patient has no other medical conditions and has had no prior surgery. Her last menstrual period was 3 weeks ago. She does not use tobacco, alcohol, or illicit drugs. Temperature is 37.2 C (99 F), blood pressure is 80/40 mm Hg, and pulse is 118/min. Physical examination shows a rigid abdomen with diffuse tenderness, rebound, and guarding. Laboratory results are as follows:  Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.8/5 (88)
(88) A 46-year-old man is brought to the emergency department after a burn injury. The patient is a cook and spilled hot oil on his trunk and legs 30 minutes ago. The patient has no significant medical history. Temperature is 36.2 C (97.2 F), blood pressure is 140/90 mm Hg, pulse is 102/min, and respirations are 20/min. On physical examination, the patient appears distressed and in pain. Partial- to full-thickness burns cover approximately 25% of the body surface area, including the lower abdomen, genitalia, and lower extremities. Intravenous fluids are begun after access is obtained with 2 large-bore peripheral catheters. Which of the following is the best immediate step in management of this patient?
(Multiple Choice)
4.8/5 (84)
(84) A 27-year-old man is brought to the emergency department with an anterior abdominal stab injury sustained in a street fight. He has a history of alcohol and polysubstance abuse. Imaging reveals free air under the diaphragm. The patient undergoes urgent exploratory laparotomy. General anesthesia is achieved with an inhalation anesthetic agent, muscle relaxant, and opioid, and ventilation is mechanically controlled. Intraoperatively, he also receives intravenous fluids and packed red blood cell transfusion. Anesthesia is terminated after successful repair of the liver and small intestinal lacerations. Prior to the transfer to the recovery unit, the patient is breathing spontaneously. Blood pressure is 160/90 mm Hg, pulse is 130/min, and respirations are 9/min. An hour later, blood pressure is 110/60 mm Hg, pulse is 70/min, and respirations are 7/min. Arterial blood gas analysis shows pH 7.30, pCO2 50 mm Hg, and pO2 70 mm Hg. Which of the following best explains this patient's postoperative findings?
(Multiple Choice)
4.8/5 (88)
(88) A 53-year-old man is brought to the emergency department after being involved in a motor vehicle collision as an unrestrained driver. The patient was found unresponsive at the scene and was intubated by the paramedics. On arrival, blood pressure is 74/50 mm Hg and pulse is 116/min. The patient is intubated and mechanically ventilated. The trachea is midline. There are multiple bruises over the anterior chest. Breath sounds are present and equal bilaterally, and heart sounds are normal. A central venous catheter is placed for fluid resuscitation. Initial central venous pressure (CVP) is 12 mm Hg (normal: 6-8). After rapid infusion of 2 L of normal saline, blood pressure is 78/52 mm Hg, pulse is 120/min, and CVP is 18 mm Hg. Which of the following is the most likely diagnosis?
(Multiple Choice)
4.7/5 (91)
(91) A 66-year-old man is brought to the emergency department with low back and left hip pain. The patient tripped at work and fell backwards, landing on his left side. He has no head injury or loss of consciousness. Medical history is unremarkable. Blood pressure is 148/90 mm Hg, pulse is 105/min, and respirations are 18/min. On examination, the left paraspinal lumbar area and left hip are tender to palpation. The neurovascular examination is intact. X-ray is obtained and is shown in the exhibit. 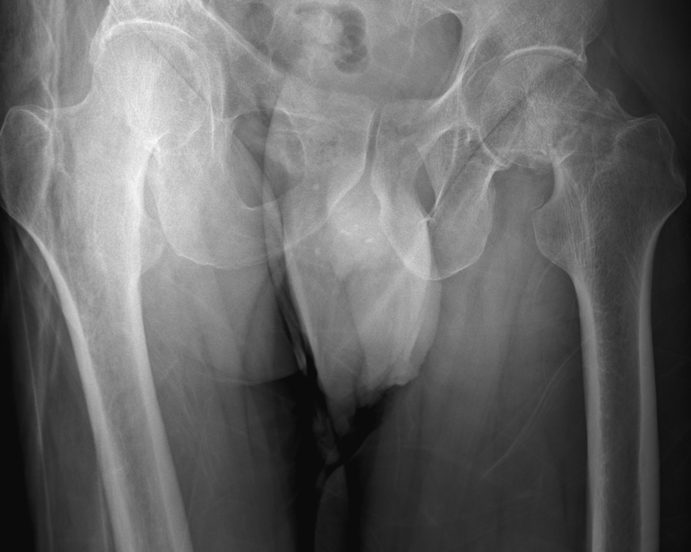 Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (81)
(81) A 42-year-old man comes to the office due to increasing anal pain. Three days ago, he noticed mild anal discomfort when wiping after a bowel movement; since then, the pain has steadily increased and is now constant and severe. The patient has had no anal drainage, hematochezia, or melena. Medical history includes hypertension and type 2 diabetes mellitus. There is no family history of colon cancer. Temperature is 38.3 C (100.9 F), blood pressure is 122/74 mm Hg, and pulse is 90/min. Examination shows an erythematous, tender, 2-cm mass external to the anal verge on the right. Digital rectal examination is normal, and stool guaiac testing is negative. Incision and drainage are performed under local anesthesia, yielding approximately 5 mL of purulent fluid. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.7/5 (81)
(81) A 45-year-old man comes to the clinic for suture removal. Two weeks ago, he was brought to the emergency department due to alcohol intoxication and was found to have a left leg laceration. The laceration was cleaned and sutured, and he received a tetanus toxoid vaccine and a prescription for oral antibiotics, which he completed. The patient has a history of alcohol use disorder and had been hospitalized on several occasions due to alcohol intoxication and acute alcoholic pancreatitis. The patient currently takes no medications, does not use tobacco, and smokes marijuana occasionally. He is experiencing homelessness and has had difficulty staying in homeless shelters regularly due to alcohol use. Temperature is 36.7 C (98.1 F), pulse is 82/min, blood pressure is 124/76 mm Hg, and respirations are 14/min. BMI is 18.8 kg/m2. Physical examination shows a disheveled man who appears older than his stated age. Dentition is poor with multiple dental caries. The gingiva is receded and bleeds easily to touch. Cardiopulmonary auscultation reveals clear lungs and normal heart sounds. The abdomen is soft and nontender with no hepatosplenomegaly. Left lower extremity examination shows scant serosanguineous discharge on the wound dressing. The surgical sutures are intact, but the wound margins are poorly approximated. There is mild erythema at the wound borders with no tenderness or warmth. Mild, bilateral, lower-extremity pitting edema is present, and distal pulses are 2+. Skin examination shows scattered ecchymoses. Laboratory results are as follows:  Which of the following is the most likely cause of this patient's impaired wound healing?
 (Multiple Choice)
4.8/5 (77)
(77) A previously healthy 35-year-old man comes to the emergency department due to severe abdominal pain for the last 4 hours. The pain started in the periumbilical area but has now shifted to the right lower quadrant. The patient has also had nausea and 2 episodes of vomiting. He has no history of other medical conditions and takes no medications. Temperature is 38.3 C (100.9 F), blood pressure is 126/80 mm Hg, pulse is 100/min, and respirations are 20/min. Abdominal examination shows tenderness in the right lower quadrant that does not worsen with inspiration. Palpation of the left lower quadrant produces pain in the right lower quadrant. Urinalysis is normal. Laboratory results are as follows:  Which of the following diagnostic imaging studies is most appropriate prior to definitive treatment of this patient?
 (Multiple Choice)
4.8/5 (75)
(75) A 53-year-old man comes to the emergency department due to increasing shortness of breath and right-sided pleuritic chest pain over 10 days. He visited an urgent care center 5 days ago and was diagnosed with pneumonia. The patient received an unknown antibiotic (which he took as prescribed), but it has not helped. He has no other medical problems. He smokes a pack of cigarettes a day and drinks 2 or 3 beers each night. Temperature is 38.7 C (101.6 F), blood pressure is 136/88 mm Hg, pulse is 104/min, and respirations are 18/min. The patient appears comfortable. There is no jugular venous distension. Cardiopulmonary examination shows dullness to percussion over the lower part of the right lung and normal heart sounds. There is no peripheral edema. Chest imaging reveals a large, loculated right pleural fluid collection. Which of the following sets of pleural fluid findings is most likely in this patient?
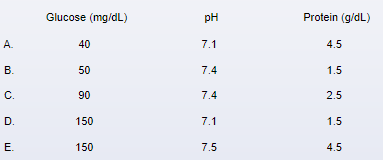
(Multiple Choice)
4.7/5 (74)
(74) A 66-year-old man comes to the office due to a sore throat over the last 3 months. The pain in the throat is worsening and is particularly noticeable when the patient swallows. He thought the pain was related to tonsil stones and tried picking them out with toothpicks and gargling with salt water after meals, but this did not relieve the pain. The patient has noticed an ulcer on the right tonsil that bleeds when he touches it. Medical history is significant for chronic obstructive pulmonary disease, for which he uses multiple inhalers. The patient has smoked 2 packs of cigarettes daily for the past 50 years. Vital signs are within normal limits. Ear examination is normal. The nasal mucosa is dry, and examination of the oral cavity shows poor dentition with no lesions. Oropharyngeal examination shows an enlarged, firm right tonsil with a 1-cm ulceration with surrounding fibrinous debris. The left tonsil has several small tonsil stones without surrounding inflammation. There is no cervical adenopathy. Biopsy of this lesion would most likely reveal which of the following?
(Multiple Choice)
4.8/5 (91)
(91) A 54-year-old man comes to the emergency department after 2 days of fever, chills, dysphagia, and drooling. The patient has been unable to eat or drink due to pain in his mouth and neck. He has a history of heavy alcohol use but does not use recreational drugs. Temperature is 38.8 C (101.8 F), blood pressure is 110/70 mm Hg, pulse is 108/min, and respirations are 22/min. The patient appears toxic with drooling and a muffled voice. The tongue is displaced posteriorly and superiorly due to a swollen area on the floor of the mouth. The bilateral submandibular area is tender, indurated, and nonfluctuant with palpable crepitus. Which of the following is the most likely source of infection in this patient?
(Multiple Choice)
4.9/5 (72)
(72) A 58-year-old woman comes to the emergency department due to dyspnea and chest discomfort over the past 2 weeks. The patient was diagnosed with left breast cancer 2 years ago and underwent surgery but refused chemotherapy and radiotherapy due to potential adverse effects. Blood pressure is 110/70 mm Hg, and pulse is 110/min and regular. Chest x-ray reveals an enlarged cardiac shadow. Echocardiography confirms a large pericardial effusion. The patient undergoes pericardiocentesis with removal of 700 mL of serosanguinous fluid. Cytologic examination of the fluid shows malignant cells consistent with metastatic breast cancer. What is the best next step in management of this patient's pericardial effusion?
(Multiple Choice)
4.9/5 (85)
(85) A 19-year-old woman comes to the emergency department due to lower abdominal pain. The pain is intermittent and started this morning during a yoga class. The patient has also vomited twice. She has no chronic medical conditions and takes no daily medications. She is sexually active and uses a copper-containing intrauterine device for contraception. The patient's last menstrual period was 2 weeks ago. Temperature is 36.7 C (98.1 F), blood pressure is 130/80 mm Hg, and pulse is 104/min. Abdominal examination shows diffuse lower abdominal tenderness, left greater than right, with no rebound or guarding. Pelvic ultrasound reveals a complex left adnexal mass with absent Doppler flow. There is a moderate amount of free fluid in the posterior cul-de-sac of the pelvis. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (74)
(74) A 42-year-old woman is evaluated in the postoperative care unit for sudden-onset tachycardia and dyspnea 15 minutes after surgery. The patient underwent a dilation and curettage for gestational trophoblastic diseases complicated by intraoperative bleeding that required 2 units of packed red blood cells. The bleeding was controlled, and the remainder of the procedure and subsequent extubation were uneventful. The patient has a 10-pack-year smoking history but no other medical conditions or prior surgeries. She takes no daily medications. Temperature is 37.8 C (100 F), blood pressure is 160/110 mm Hg, pulse is 134/min, and respirations are 38/min. The patient appears diaphoretic and has shallow, labored breathing. Cardiac examination shows sinus tachycardia with no rubs or murmurs. The lungs are clear to auscultation bilaterally. The abdomen has no marked distension, rebound, or guarding. Bilateral extremities have generalized rigidity. The Foley catheter is draining brown-appearing urine. Which of the following is the most likely diagnosis for this patient?
(Multiple Choice)
4.7/5 (87)
(87) A 73-year-old man is brought to the emergency department due to increasing confusion for the last day. The patient has a history of type 2 diabetes mellitus, neuropathy, nonhealing foot ulcer, and coronary artery disease. On arrival, he is lethargic. Temperature is 37.6 C (99.7 F), blood pressure is 80/50 mm Hg, pulse is 120/min, and respirations are 18/min. Pulse oximetry on room air shows an oxygen saturation of 97%. Mucous membranes are moist. Cardiopulmonary examination reveals no abnormalities. The abdomen is soft and nontender. Neurologic examination shows no focal findings. A nonhealing diabetic ulcer with small eschar is present over the right heel; there is no purulence, tenderness, or surrounding erythema. Laboratory results are as follows:  Which of the following is the most appropriate next step in management of this patient within the first hour of arrival in the emergency department?
 (Multiple Choice)
4.8/5 (85)
(85) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)