



 Chat with AI
Exam 5: Obstetrics & Gynecology

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 29-year-old woman, gravida 1 para 1, is evaluated in the emergency department for a headache. Three days ago, she had an uncomplicated vaginal delivery with neuraxial anesthesia. This morning, the patient developed an occipital headache that has not improved with acetaminophen. The headache has become progressively worse, and the patient cannot sit without becoming nauseated and vomiting. The patient has no chronic medical conditions and does not use tobacco, alcohol, or illicit drugs. Temperature is 36.7 C (98.1 F), blood pressure is 162/96 mm Hg, pulse is 98/min, and respirations are 18/min. On examination, heart sounds are normal with no rubs or murmurs, and the lungs are clear to auscultation. Cranial nerves are intact and deep tendon reflexes are 3+. There is 5/5 strength in the right lower extremity and 3/5 strength in the left. Which of the following is the best next step in management of this patient?

Free
(Multiple Choice)
4.9/5  (88)
(88) Correct Answer: Verified
B
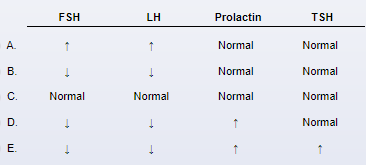
A 34-year-old woman comes to the office for evaluation of 3 months of amenorrhea. She first began experiencing irregular periods a year ago, and now they have stopped completely. The patient has no headaches, visual changes, galactorrhea, hair loss, or fatigue. She has a history of non-Hodgkin lymphoma for which she received chemotherapy 5 years ago; there are no signs of recurrence. The patient currently takes no medications. Family history is noncontributory. Her most recent Pap test was last year and all prior testing was normal. She has no history of sexually transmitted infections. The patient does not use tobacco, alcohol, or illicit drugs. Blood pressure is 120/80 mm Hg and pulse is 78/min. BMI is 28 kg/m2. Physical examination reveals a nonenlarged thyroid without masses. Cardiopulmonary examination is normal. Pelvic examination reveals dry vaginal mucosa and a small, anteverted, mobile uterus with no adnexal masses. A pregnancy test is negative. Which of the following laboratory findings are most likely present in this patient?
Free
(Multiple Choice)
4.9/5 (78)
(78) Correct Answer:Verified
VerifiedA
A 15-year-old girl is brought to the office due to irregular menstrual periods. Menarche was at age 13, and since then her periods have been irregular with cycles varying from 3 to 8 weeks. The patient has no chronic medical issues, has never had surgery, and takes no medications. Her mother and older sister have polycystic ovary syndrome, and both take oral contraceptives. The patient has never been sexually active. Vital signs are normal. Physical examination shows normal hair distribution with Tanner V secondary sexual characteristics. Abdominal examination is normal. There is dark red blood noted at the cervical os with no active bleeding. Serum prolactin and TSH levels are normal. Administration of micronized oral progesterone results in withdrawal bleeding in 3 days. Pelvic ultrasound reveals normal ovaries and uterus. Which of the following is the most likely explanation of this patient's irregular menstrual periods?
Free
(Multiple Choice)
4.9/5 (80)
(80) Correct Answer:Verified
VerifiedD
Serum rapid plasma reagin and herpes simplex virus PCR testing are negative. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (87)
(87) A 45-year-old woman comes to the office for an annual well-woman visit. She feels well and has no concerns. The patient takes a combined estrogen/progestin oral contraceptive and has regular monthly menses. She has no chronic medical conditions and has had no prior surgeries. The patient had 2 term vaginal deliveries in her 30s, and her last Pap smear with human papillomavirus cotesting was normal 5 years ago. The patient does not use tobacco, alcohol, or illicit drugs. Her last menstrual period started 2 days ago. Blood pressure is 110/60 mm Hg and pulse is 70/min. BMI is 23 kg/m2. Pelvic examination shows a multiparous cervix without lesions. Pap testing reveals benign-appearing endometrial cells and no intraepithelial lesions. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (78)
(78) A 21-year-old woman, gravida 1 para 0, at 20 weeks gestation comes to the office for a fetal anatomy ultrasound. Her initial prenatal visit was last week, and she has had no vaginal bleeding, contractions, or leakage of fluid. The patient had not realized she was pregnant because her menses are irregular, typically occurring only once every 2 or 3 months. She has no known medical conditions and takes no medications. Blood pressure is 146/98 mm Hg and pulse is 88/min. BMI is 30 kg/m2. Ultrasound shows a large defect in the calvaria and meninges, with only a small cerebellum and brainstem, as seen in the image below. 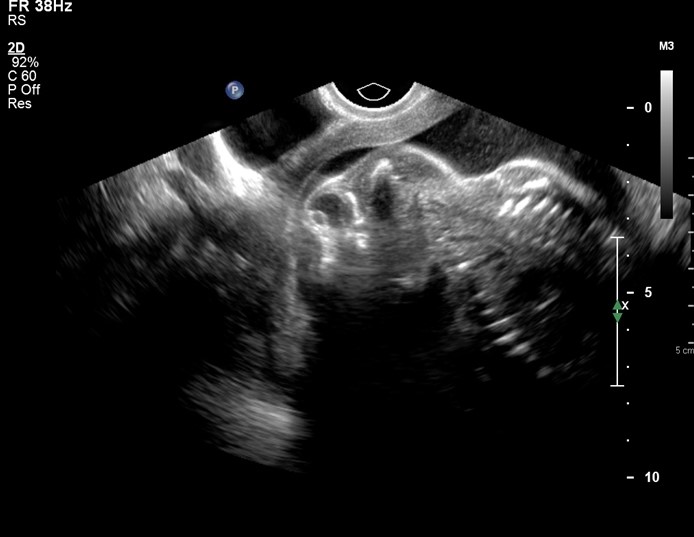 The remainder of the fetal anatomy appears normal. Amniotic fluid volume measures 26 cm (normal: <24 cm). Which of the following maternal factors is most commonly associated with this fetal anomaly?
 (Multiple Choice)
4.7/5 (89)
(89) The patient is diagnosed with lichen sclerosus. Which of the following is the best treatment option for this patient?
(Multiple Choice)
4.8/5 (75)
(75) A 28-year-old woman, gravida 1 para 0, at 41 weeks gestation comes to the hospital for antepartum fetal surveillance. She has had less fetal movement than usual but no abdominal pain, leakage of fluid, or vaginal bleeding. Blood pressure is 120/80 mm Hg. The patient's pre-pregnancy BMI was 40 kg/m2, and she has gained 20 kg (44 lb) during the pregnancy. Her pregnancy has otherwise been uncomplicated. Nonstress test shows a baseline fetal heart rate of 140/min, moderate variability, and no accelerations for >40 minutes. Two contractions are observed on the tocodynamometer. An episode of fetal heart rate decrease to 130/min began after the peak of a contraction and lasted for a minute. Ultrasound shows a fetus in cephalic presentation, a loop of umbilical cord near the fetal neck, an estimated fetal weight at the 35th percentile for gestational age, and a single deepest pocket of amniotic fluid of 1 cm. The biophysical profile results are shown below. Which of the following is the most likely cause of this patient's biophysical profile results?
(Multiple Choice)
4.9/5 (70)
(70) A 74-year-old woman, gravida 5 para 5, comes to the office due to vaginal spotting and discharge for several months. She reports a mass coming out of her vagina. She is now having difficulty defecating; increased straining causes the mass to increase in size. The patient has hypertension, type 2 diabetes mellitus, and NYHA class III heart failure. Her last hemoglobin A1c was 11.8. She had 5 spontaneous vaginal deliveries and has no history of abnormal Pap tests. The patient has a 40-pack-year smoking history. Blood pressure is 150/90 mm Hg, pulse is 84/min, and respirations are 16/min. Oxygen saturation is 89% on room air. BMI is 41 kg/m2. Cardiopulmonary examination reveals decreased breath sounds bilaterally. The abdomen is nontender and has no palpable masses. Pelvic examination reveals the cervix at the level of the vaginal introitus. The vaginal mucosa is thin with multiple areas of excoriation and erosion. Ultrasonography reveals a thin endometrial stripe. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (88)
(88) A 68-year-old woman comes to the office due to blood-tinged vaginal discharge. The patient has had intermittent, slightly malodorous discharge for the past several weeks but has not passed large clots or had heavy vaginal bleeding. Medical history is significant for exposure to diethylstilbestrol in utero that resulted in infertility. She underwent menopause at age 55 and has used combined menopause hormone therapy for several years. Her mother was diagnosed with endometrial cancer at age 54, and her uncle was diagnosed with colorectal cancer at age 70. The patient has smoked a pack of cigarettes daily for the last 40 years and drinks a few glasses of wine each week. BMI is 32 kg/m2. Pelvic examination demonstrates a blood-tinged watery discharge and a 3-cm ulcerated lesion on the posterior vaginal wall; the cervix appears normal. Transvaginal ultrasound shows a 2-mm endometrial stripe. Biopsy of the lesion demonstrates squamous cell carcinoma. Which of the following is the greatest risk factor for this patient's diagnosis?
(Multiple Choice)
4.9/5 (74)
(74) A 19-year-old woman comes to the office due to continuous vaginal discharge. The patient has had a clear, slightly malodorous vaginal discharge for the past few weeks but no pelvic pain, dysuria, or vulvovaginal pruritus. She is 6 weeks postpartum from a vaginal delivery of a stillborn male infant after 3 days of labor and 4 hours of pushing. The patient had no prenatal care and delivered at home. Temperature is 36.7 C (98 F), blood pressure is 120/60 mm Hg, and pulse is 70/min. Pelvic examination shows a well-healed, third degree perineal laceration. On speculum examination, there is a small, red area of granulation tissue on the anterior vaginal wall. The cervix has no lesions and there is a pool of clear fluid in the vagina with a pH of 6. Which of the following would most likely establish the diagnosis in this patient?
(Multiple Choice)
5.0/5 (73)
(73) A 25-year-old woman comes to the office for evaluation of increasing amounts of malodorous vaginal discharge over the past 4 days. The patient has no postcoital spotting or intermenstrual bleeding. Her last menstrual period was 3 weeks ago. She has been sexually active with a new partner for the past month and they use condoms intermittently. She has no chronic medical conditions or previous surgeries. The patient takes no daily medications. She has a history of chlamydial cervicitis at age 19. Vitals signs are normal. Physical examination shows no vulvar or vaginal erythema or lesions. There is an off-white discharge throughout the vaginal vault with no discharge from the cervical os. The uterus is mobile and nontender with no adnexal masses. Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (91)
(91) A 26-year-old woman comes to the office due to a vulvar lesion that she noticed 2 days ago. The lesion began as a papule, but this morning it developed a small ulcer in the center. The patient has mild burning with urination but no fever, abnormal vaginal discharge, or oral ulcers. She is sexually active and has had 5 male partners over the past year. Her only medication is an oral contraceptive. The patient smokes 1 pack of cigarettes daily but does not use alcohol or illicit drugs. Vital signs are normal. Vulvar examination shows a 2-cm ulcer with a nonexudative base and a raised, indurated margin. There is no tenderness with palpation. Moderate, painless bilateral inguinal lymphadenopathy is present.
Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.9/5 (93)
(93) A 27-year-old primigravid woman at 16 weeks gestation comes to the office for an initial prenatal visit. She has had no pelvic pain, vaginal bleeding, or abnormal discharge. The patient immigrated to the United States 6 years ago. She has no medical issues or previous surgeries. She had regular menses prior to pregnancy and has no history of sexually transmitted infections. Family history is noncontributory. The patient takes a daily prenatal vitamin and does not use tobacco, alcohol, or illicit drugs. Blood pressure is 110/70 mm Hg. BMI is 23 kg/m2. Fetal heart rate is 155/min. The patient's blood type is O, Rh negative. Rubella and varicella titers both show no immunity. Hemoglobin is 11.2 g/dL, and mean corpuscular volume is 84 fL. All other routine prenatal laboratory studies are normal. Which of the following is the best recommendation for this patient?
(Multiple Choice)
4.9/5 (72)
(72) A 54-year-old woman comes to the office due to increasing vulvar pruritus and burning that is preventing sleep. The symptoms began about a year ago and have become more severe. In addition to the constant pruritus, the patient has had increasingly painful defecation. Two days ago, her vulva bled after intense scratching. She attributes her symptoms to dry skin and has been applying skin moisturizer daily. The patient is not sexually active. Medical history includes alopecia areata and symptomatic hot flashes that have occurred since menopause at age 51. Examination shows bilateral labia majora with excoriated, pale, thin skin. The labia minora are not visible, and there is severe narrowing of the introitus. The perianal skin is pale white, appears wrinkled, and has a small anal fissure. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
5.0/5 (77)
(77) A 39-year-old woman, gravida 4 para 0 aborta 3, at 35 weeks gestation comes to the hospital due to intense, constant lower abdominal pain. The patient conceived via in vitro fertilization; her prenatal course has been uncomplicated. Over the past 10 years, the patient has had 3 spontaneous abortions, all attributed to uterine leiomyoma. Two years ago, she had an abdominal myomectomy during which the uterine cavity was entered. Temperature is 36.7 C (98 F), blood pressure is 130/80 mm Hg, and pulse is 100/min. The fetal heart rate tracing shows a baseline rate in the 140s with moderate variability and persistent variable decelerations to the 90s. Contractions occur every 2-3 minutes and last for 45 seconds. The cervix is 4 cm dilated and 100% effaced. Which of the following is the best next step in management of this patient?
(Multiple Choice)
5.0/5 (66)
(66) A 38-year-old woman comes to the office for follow-up of cervical dysplasia. She has no chronic medical conditions, and her only surgery was a tubal ligation after the birth of her second child. The patient does not use tobacco, alcohol, or illicit drugs. Last month, routine cervical cancer screening revealed a high-grade squamous epithelial lesion. She then underwent a colposcopy, which confirmed high-grade cervical intraepithelial neoplasia (CIN) 3. Cervical conization was performed. The pathology report shows CIN 3 with all surgical margins free of disease. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (76)
(76) A 62-year-old nulligravid woman comes to the office for follow-up of a right adnexal mass. The patient was undergoing a pelvic examination and Pap testing 2 weeks ago when a right adnexal mass was palpated on bimanual examination. The Pap test was normal, and she has had no symptoms. Menopause occurred at age 52, and there has been no postmenopausal spotting. The patient's medical history is otherwise unremarkable. She does not use tobacco, alcohol, or illicit drugs. There is no family history of ovarian or breast cancer. Temperature is 36.7 C (98.1 F), blood pressure is 120/70 mm Hg, and pulse is 72/min. The abdomen is soft, nondistended, and has no palpable masses. A pelvic ultrasound reveals a 5-cm right ovarian cyst. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.7/5 (77)
(77) A 25-year-old woman, gravida 1 para 0, at 29 weeks gestation comes to the emergency department due to a headache. The patient has a history of migraines but has not had one during the pregnancy until today. She has no other chronic medical conditions. This morning, the patient woke with a left-sided frontal headache and blurry vision in the left eye. She took a dose of acetaminophen, but the headache did not improve and now is in the bilateral frontal region. The patient has no sick contacts but has had increased stress at work and is working longer hours. Her caffeine consumption has increased to 2-3 cups of coffee a day. Blood pressure is 156/92 mm Hg and pulse is 84/min. Fetal heart rate is 155/min. Repeat blood pressure a few hours later is 150/94 mm Hg. Cranial nerves are intact. There is no nuchal rigidity. The abdomen is soft, gravid, and nontender. Deep tendon reflexes are normal. The remainder of the examination is unremarkable. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (66)
(66) A 40-year-old woman, gravida 5 para 0 aborta 4, at 35 weeks gestation comes to labor and delivery triage because she has not felt her baby move for the past 24 hours. The patient has not eaten much all day and skipped dinner due to nausea. She has a 25-pack-year history of cigarette use but has cut down on her smoking during her pregnancy. Her last ultrasound at 32 weeks gestation showed a fetus in breech position measuring at the 15th percentile and placenta previa. A nonstress test shows a baseline fetal heart rate in the 130s with moderate variability and no decelerations. There are no accelerations after an hour of monitoring despite vibroacoustic stimulation. Tocometry shows no contractions. Item 1 of 2
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (90)
(90) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)