



 Chat with AI
Exam 5: Obstetrics & Gynecology

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 16-year-old girl comes to the emergency department with heavy vaginal bleeding for 3 days. The patient's menses have been irregular since menarche at age 14 and occur every 4-5 months; her previous menstrual period was almost 4 months ago. She has no medical problems and has had no surgeries. She does not use tobacco, alcohol, or illicit drugs. The patient is sexually active and uses condoms for contraception. Temperature is 37.2 C (99 F), blood pressure is 110/60 mm Hg, pulse is 90/min, and respirations are 16/min. On pelvic examination, there is a moderate amount of blood in the vaginal vault and active bleeding from the cervical os. Bimanual examination shows a small uterus and no adnexal masses. Pelvic ultrasound reveals a small uterus with a thick endometrial stripe and normal ovaries. Urine pregnancy test is negative. Laboratory results are as follows:  Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.9/5  (76)
(76) A 23-year-old woman, gravida 1 para 1, comes to the office due to pain in the right lower quadrant for 2 months. The pain is unrelieved by acetaminophen and worsens with physical activity. Menses are regular and occur every 28 days. The patient has a history of severe dysmenorrhea and takes oral contraceptive pills daily. Two years ago, she was treated for pelvic inflammatory disease. She has no chronic medical conditions and has had no surgeries. The patient smokes a pack of cigarettes a day but does not use alcohol or illicit drugs. Temperature is 36.7 C (98.1 F), blood pressure is 126/74 mm Hg, and pulse is 87/min. BMI is 36 kg/m2. The abdomen is soft and nontender. Pelvic examination reveals right adnexal fullness but is limited by habitus. Pregnancy test is negative. Pelvic ultrasonography shows a 4-cm ovarian mass. The patient undergoes laparoscopic ovarian cystectomy, and a photograph of the cyst is shown in the exhibit. 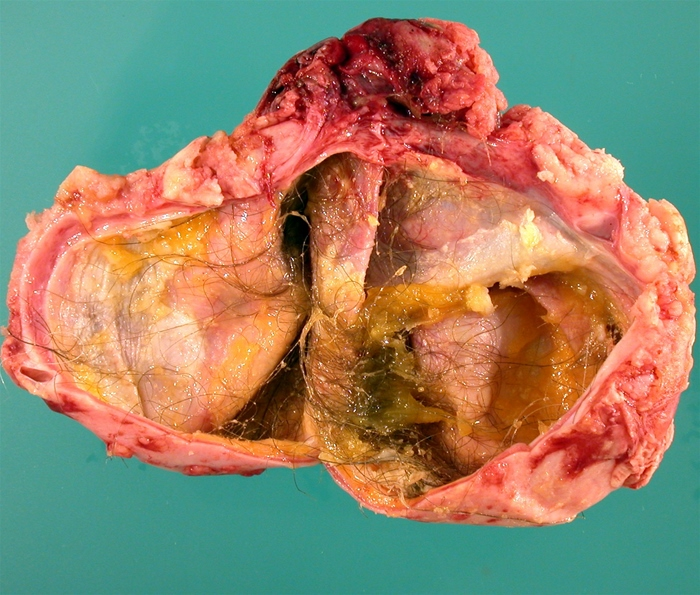 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.8/5 (63)
(63) A 32-year-old woman, gravida 3 para 2, at 38 weeks gestation comes to the hospital due to contractions. The patient's prenatal course has been uncomplicated. She had a cesarean delivery for breech presentation at 39 weeks gestation in her second pregnancy. Blood pressure is 100/60 mm Hg, pulse is 100/min, and respirations are 22/min. Fetal heart rate tracing shows moderate variability, multiple accelerations, and no decelerations. Uterine contractions are regular and occur every 4 minutes. The cervix is 6 cm dilated and 60% effaced, and the fetal vertex is at 0 station. After 2 hours, the patient is suddenly restless and has intense lower abdominal pain. Fetal heart monitoring shows recurrent late decelerations. On pelvic examination, there is moderate vaginal bleeding, the cervix is 6 cm dilated and 60% effaced, and the fetal vertex is at −3 station. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.9/5 (76)
(76) An ultrasound confirms an anterior placenta covering the cervical os and an amniotic fluid index of 1.5 with a single fluid pocket measuring 1.5 x 1 cm. Over a period of 45 minutes, there are 4 episodes of fetal movement, 3 flexion/extension events, and no fetal breathing movements. The fetus is breech. Which of the following is the most likely cause of the patient's biophysical ultrasound findings?
(Multiple Choice)
4.9/5 (66)
(66) A 39-year-old woman comes to the office due to intermittent episodes of involuntary loss of urine. Her symptoms started several months ago with drops of urine leaking while exercising or lifting her children. Coughing and laughing now cause her to pass large amounts of urine. The patient is embarrassed to go out with friends and has started wearing an adult diaper. Her children, ages 4 and 6, were delivered vaginally, and both pregnancies were complicated by gestational diabetes mellitus and fetal macrosomia. Temperature is 36.8 C (98.4 F), blood pressure is 120/82 mm Hg, and pulse is 80/min. BMI is 24 kg/m2. Urinalysis is negative for nitrites and leukocyte esterase. Which of the following is most likely to improve this patient's urinary symptoms?
(Multiple Choice)
4.8/5 (79)
(79) A 26-year-old woman, gravida 1 para 0, at 20 weeks gestation comes to the office due to a nonproductive cough, chest tightness, and shortness of breath for a month. The symptoms occur a few times a week, mostly at night, and have occasionally awakened the patient. They have recently been bothersome during the day. They are not worse during meals or while lying down. The patient is asymptomatic during her visit. Medical history is significant for asthma in middle school, but she has not experienced symptoms or needed an inhaler since her late teenage years. The patient has no known environmental or drug allergies. She has never used tobacco and has not been exposed to secondhand smoke. Blood pressure is 118/70 mm Hg and pulse is 74/min. Fetal heart rate is 152/min. The oropharynx is clear. Chest auscultation reveals normal breath sounds. The uterine fundus is palpable at the umbilicus, consistent with 20 weeks gestation. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (83)
(83) A 19-year-old woman, gravida 2 para 1, at 38 weeks gestation comes to the emergency department due to severe abdominal pain and vaginal bleeding. The patient had an ultrasound at 8 weeks gestation for vaginal spotting but has not otherwise received prenatal care this pregnancy. Her prior pregnancy two and a half years ago ended in a classical cesarean delivery at 24 weeks gestation for placental abruption. The patient smokes a pack of cigarettes daily and uses cocaine multiple times a week. Blood pressure is 90/60 mm Hg and pulse is 130/min. The abdomen is tender and has an irregular mass; no contractions are palpated. Bright red blood is noted on the perineal pad. Fetal heart tracing shows multiple prolonged decelerations to 100/min. Which of the following risk factors most likely contributed to this patient's presentation?
(Multiple Choice)
4.8/5 (68)
(68) A 28-year-old woman, gravida 2 para 0 abortus 1, at 32 weeks gestation comes to the emergency department because she has not felt her baby move for the past few hours. This pregnancy has been complicated by placenta previa, but she has had no contractions, vaginal bleeding, or leakage of fluid. The patient's other prenatal testing was normal. With her first pregnancy, she had a spontaneous abortion at 8 weeks gestation that required dilation and curettage. The patient's only medical condition is asthma, for which she uses corticosteroid and bronchodilator inhalers. On physical examination, fetal heart tones are not heard with a Doppler device. Transabdominal ultrasound is performed and reveals no fetal cardiac activity, a finding consistent with intrauterine fetal demise. The patient asks how this could have happened to her baby. Which of the following is the most appropriate response?
(Multiple Choice)
4.9/5 (75)
(75) A 23-year-old primigravida at 38 weeks gestation comes to labor and delivery for spontaneous rupture of membranes and painful contractions. The patient has had an uncomplicated prenatal course and a negative group B Streptococcus culture last week. Leopold maneuvers show an estimated fetal weight of 3.6 kg (8 lb). Cervical examination shows the cervix to be 8 cm dilated and 90% effaced with the fetal vertex at 0 station. The patient is admitted and epidural analgesia is administered. She reports increasing rectal pressure; repeat cervical examination is unchanged. An intrauterine pressure catheter is placed and shows contractions every 2-3 minutes, and the sum of contraction strength is 240 Montevideo units over 10 minutes. This contraction pattern continues, and 4 hours later the cervix remains unchanged. Fetal heart rate tracing is category 1. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (72)
(72) A 32-year-old woman comes to the office due to difficulty conceiving despite frequent, unprotected intercourse with her husband over the last 3 years. She has had multiple sexual partners in the past and never became pregnant despite inconsistent condom use. Menses started at age 12 and are irregular. The patient has had recurrent vaginal candidiasis for which she uses an over-the-counter vaginal suppository. Vital signs are normal. The thyroid is not enlarged. She has thick, dark, velvety plaques under her axillae. Breast examination is normal. Abdominal examination shows no masses. Pelvic examination reveals normal external genitalia; a small, mobile uterus with no cervical motion tenderness; and bilaterally enlarged ovaries. TSH, LH, and prolactin levels are normal. Which of the following is the most appropriate therapy for this patient's infertility?
(Multiple Choice)
4.8/5 (78)
(78) A 41-year-old woman comes to the emergency department for heavy vaginal bleeding. Her last normal menstrual period was 4 months ago, but she has had irregular spotting since. Earlier today, the patient began to have increasingly heavy vaginal bleeding with passage of small clots. She also has had increasing hot flashes, night sweats, and palpitations over the past 3 weeks but no chest pain, shortness of breath, or orthopnea. The patient had a Roux-en-Y gastric bypass 7 years ago and has lost 45 kg (99 lbs) since. Temperature is 37.7 C (99.9 F), blood pressure is 150/90 mm Hg, and pulse is 118/min. BMI is 35 kg/m2. Physical examination shows her to be anxious. The skin is warm and smooth. Cardiac examination reveals tachycardia but a regular rhythm; there are no rubs or murmurs. The lungs are clear to auscultation bilaterally. Pelvic examination shows a moderate amount of blood in the vaginal vault and a closed cervix. Bimanual examination is limited by the patient's obesity but reveals an enlarged uterus. Bedside pelvic ultrasound reveals an enlarged uterus filled with a heterogeneous mass composed of small, cystic structures. TSH is 0.1 µU/mL. Serum β-hCG level is elevated. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (77)
(77) A 13-year-old girl is brought to the office for evaluation of acne. She began to develop acne over her forehead and chin 4 months ago. She used over-the-counter topical salicylic acid, but the acne did not improve. Now, the patient has painful acne over her face and upper chest. She participates in a soccer league after school, and her mother feels that her exercise regimen is too strenuous and stressful and contributes to her acne. The patient has no medical conditions and has had no surgeries. She has not had a menstrual period. The girl has grown 10.1 cm (4 in) in the last year; her height and weight are at the 70th percentile for age. Vital signs are normal. Nodulocystic acne is present across the face and upper chest. There is no breast bud development. The abdomen is nontender and has no palpable masses. External pelvic examination shows the clitoris protruding from the clitoral hood and bilateral masses in the labia majora. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.9/5 (92)
(92) A 29-year-old woman, gravida 1 para 0, at 20 weeks gestation comes to the office for evaluation of a lesion on her hand. The patient first noticed the lesion a month ago after working in her garden and scratching her thumb. She initially used a topical antibiotic ointment, but the lesion continued to grow and occasionally bled. There has been no purulent drainage, and the patient has had no associated fever or chills. Her pregnancy has been uncomplicated, and she has no chronic medical conditions. Temperature is 36.7 C (98.1 F), blood pressure is 120/80 mm Hg, and pulse is 65/min. Fetal heart tones are 150/min. Examination of the hand is shown in the image below: 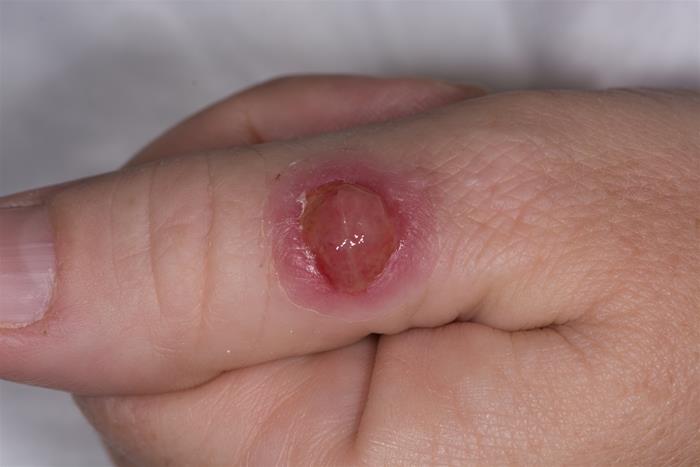 Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.9/5 (101)
(101) A 33-year-old woman, gravida 1 para 0, at 39 weeks gestation comes to the hospital for a scheduled elective induction. She has had no contractions, vaginal bleeding, or leakage of fluid. Fetal movement is normal. Her pregnancy has been uncomplicated except for a positive group B Streptococcus (GBS) rectovaginal culture at 36 weeks gestation with resistance to erythromycin. The patient has no chronic medical conditions and has had no prior surgeries. She developed a nonpruritic maculopapular rash after taking penicillin in her 20s. Vital signs are normal. Abdomen is soft, gravid, and nontender. The cervix is 1 cm dilated and 60% effaced with the fetal vertex at -2 station. Fetal heart rate tracing is category 1. Given this patient's penicillin allergy, which of the following is the most appropriate pharmacotherapy for this patient?
(Multiple Choice)
4.8/5 (81)
(81) A 17-year-old girl comes to the office for evaluation of vaginal discharge requiring the use of a panty liner. She has had this discharge intermittently for the past few months and notices it returns after menses end. The last menstrual period ended a week ago. For the last 6 months, she has been sexually active with a new partner and uses condoms for contraception. The patient has no medical problems or previous surgeries. She takes no medications and does not use tobacco, alcohol, or illicit drugs. Temperature is 36.7 C (98 F), blood pressure is 110/70 mm Hg, and pulse is 78/min. On pelvic examination, the external genitalia have no erythema or edema. There is copious white, mucoid, odorless vaginal discharge. Microscopic examination reveals a predominance of squamous cells and rare polymorphonuclear leukocytes. Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (81)
(81) A 34-year-old nulligravid woman comes to the office for evaluation of abdominal pain. For the last 3 months, the patient has had intermittent abdominal cramping but no nausea, vomiting, or changes in bowel patterns. She stopped taking her combined oral contraceptives 6 months ago to try for pregnancy. Since then, her menses have occured monthly with 5 days of moderate bleeding. The patient's mother had a hysterectomy at age 30 for heavy menstrual bleeding, and her paternal grandmother had breast cancer at age 64. BMI is 24 kg/m². Vital signs are normal. Pelvic examination reveals a palpable right adnexal mass. On ultrasound, there is a 4-cm right adnexal mass that appears thin-walled and has multiple irregular, thickened internal septations. The left ovary appears normal, and there is no free fluid in the pelvis. Urine pregnancy test is negative. Which of the following features indicates a need for additional evaluation in this patient?
(Multiple Choice)
4.8/5 (73)
(73) A 30-year-old primigravid woman at 10 weeks gestation comes to the office for an initial prenatal visit. The patient has no chronic medical conditions and no prior surgeries. While discussing what to expect during the pregnancy and delivery, the patient states that she would like a primary cesarean delivery performed. The patient's mother has struggled for years with urinary and fecal incontinence after having 3 vaginal deliveries, and the patient does not want the same complications. The physician discusses the complications associated with cesarean delivery, including the increased risk of complications in future pregnancies. Based on the lack of medical and obstetric indications, the physician is uncomfortable agreeing to perform the procedure. However, the patient states that she understands the risks and still wants a cesarean delivery. Which of the following is the most appropriate management of this patient?
(Multiple Choice)
5.0/5 (94)
(94) A 60-year-old woman comes to the office for evaluation of postmenopausal bleeding. The patient went through menopause at age 53 and did not use menopausal hormone therapy. Four months ago, she noticed some postcoital bleeding that resolved within a day. For the last 3 months, the patient has had daily vaginal spotting and sometimes has bleeding similar to the first day of her menstrual cycle. She has obstructive sleep apnea and hyperlipidemia. Pap test last year was normal. The patient does not use tobacco, alcohol, or illicit drugs. Blood pressure is 130/80 mm Hg and pulse is 68/min. BMI is 34 kg/m2. The abdomen is soft and nontender. Speculum examination shows a small amount of blood in the vaginal vault and a normal cervix. Bimanual examination reveals right adnexal fullness and a slightly enlarged uterus. Hemoglobin is 11.8 g/dL. Pelvic ultrasound shows an 11-cm solid ovarian mass and no free fluid in the pelvis. Endometrial biopsy shows complex hyperplasia without atypia. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (83)
(83) A 24-year-old primigravida comes to the office for her first prenatal visit. Her last menstrual period was 8 weeks ago and 2 home pregnancy tests have been positive. The patient feels generally well, although she has experienced mild intermittent nausea and anxiety during the pregnancy. Medical history is unremarkable, and her only medication is an over-the-counter prenatal vitamin. Thyroid function tests were normal on evaluation for fatigue and mild palpitations 6 months ago. The patient stopped drinking alcohol after finding out she was pregnant, and she does not use tobacco or illicit drugs. Blood pressure is 120/80 mm Hg and pulse is 82/min. Physical examination findings are normal. Pelvic ultrasound shows a gestational sac containing a fetal pole and a yolk sac. Thyroid function study results are as follows:  Which of the following is the most likely cause of this patient's current laboratory findings?
 (Multiple Choice)
4.9/5 (83)
(83) A 44-year-old woman comes to the office for evaluation of abnormal uterine bleeding. The patient has had intermenstrual bleeding over the past 3 months. Most of the time, she has had only spotting with wiping, but last week, she had slightly heavier bleeding that required her to use a menstrual pad. In addition to this intermenstrual bleeding, the patient also has monthly menses with 4-5 days of moderate bleeding and slight cramping on the first 2 days that typically resolves with ibuprofen. She has no chronic medical conditions and takes no daily medications. The patient had a bilateral tubal ligation after her last delivery at age 31. Vital signs are normal. BMI is 22 kg/m2. Speculum examination reveals a multiparous cervix with a small amount of bright red blood at the os and no visible cervical or vaginal lesions. On bimanual pelvic examination, the uterus is small, mobile, and nontender. No adnexal masses are palpated. FSH, TSH, and prolactin levels are normal. Urine pregnancy test is negative. Which of the following is the most likely cause of this patient's abnormal uterine bleeding?
(Multiple Choice)
4.7/5 (82)
(82) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)