



 Chat with AI
Exam 5: Obstetrics & Gynecology

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 30-year-old woman, gravida 1 para 0, at 24 weeks gestation comes to the office for a prenatal visit. The patient feels well and has no vaginal bleeding, leakage of fluid, or contractions. She has had no headaches, changes in vision, or right upper quadrant pain. The patient has no chronic medical conditions and has had an uncomplicated pregnancy. She does not use tobacco, alcohol, or illicit drugs. Temperature is 37.2 C (99 F), blood pressure is 152/88 mm Hg, pulse is 72/min, and respirations are 14/min. Oxygen saturation is 99% on room air. Physical examination is normal. Fetal heart rate is 150/min on Doppler ultrasound. Laboratory results are as follows:  A nonstress test is reactive. Repeat blood pressure is 154/86 mm Hg. Which of the following is the best next step in management of this patient's hypertension?
 (Multiple Choice)
4.8/5  (70)
(70) A 36-year-old nulligravid woman comes to the clinic for preconception counseling due to advanced maternal age. The patient has epilepsy that is well controlled on several antiepileptic medications. Her husband has no medical conditions. Temperature is 37.2 C (99 F), blood pressure is 128/76 mm Hg, pulse is 90/min, and respirations are 16/min. Examination shows a yellow-brown plaque with irregular borders measuring about 6 cm in diameter along the lower back. There are a few periungual fibromas on the hands and feet. Assume that the patient is heterozygous for her underlying disorder and that the couple will give birth to a boy. Which of the following is the likelihood that the boy will have this disorder?
(Multiple Choice)
5.0/5 (77)
(77) A 29-year-old woman comes to the office due to infertility. She has had unprotected intercourse with her husband regularly for the past year and has not become pregnant. The patient's last menstrual period was 3 weeks ago. Her menses occur every 28-30 days and last 4-5 days. The patient has severe lower abdominal pain that begins the day before her menses and is only partially relieved by ibuprofen. She was treated for gonococcal cervicitis at age 19. The patient takes a prenatal vitamin daily and does not use tobacco, alcohol, or illicit drugs. Her husband, age 31, recently had a normal semen analysis. The patient's blood pressure is 126/70 mm Hg and pulse is 85/min. BMI is 31 kg/m2. Examination reveals a small uterus with a cervix that appears laterally displaced; there is pain with cervical manipulation. Which of the following is the most likely cause of this patient's infertility?
(Multiple Choice)
4.7/5 (79)
(79) A 27-year-old woman comes to the office for advice regarding contraception. The patient has been using condoms consistently but now wants something more reliable. She has regular monthly menses, typically with 6 days of bleeding that requires wearing both a pad and a tampon simultaneously to prevent blood from getting on her clothing. Last year, the patient's mother was diagnosed with a pulmonary embolus and found to be a heterozygous factor V Leiden carrier. At that time, the patient also underwent screening and was also found to be a heterozygous factor V Leiden carrier. She has no personal history of venous thromboembolism and no other medical conditions. The patient does not use tobacco, alcohol, or illicit drugs. Blood pressure is 120/76 mm Hg and pulse is 70/min. BMI is 20 kg/m2. Physical examination is normal. Laboratory results are as follows:  Which of the following is the most appropriate contraceptive option for this patient?
 (Multiple Choice)
4.7/5 (79)
(79) A 24-year-old woman, gravida 2 para 1, at 28 weeks gestation comes to the office with her husband because she has felt no fetal movement for 3 days. She has no pain, leakage of fluid, or bleeding. All testing during this pregnancy has been normal, including an anatomy ultrasound at 20 weeks gestation. Her first child was delivered vaginally at term. Temperature is 36.7 C (98 F), blood pressure is 120/80 mm Hg, and pulse is 94/min. Fetal heart tones are not heard by Doppler. Ultrasound demonstrated an absence of fetal cardiac activity and a small for gestational age fetus in breech presentation. A digital cervical examination shows the cervix to be long and closed. Laboratory results are as follows:  Which of the following is the most appropriate management advice for this patient?
 (Multiple Choice)
4.9/5 (91)
(91) A 32-year-old woman comes to the office for evaluation of postcoital bleeding. She has monthly menstrual cycles with 4 days of light vaginal bleeding, but for the past 2 months she has also had postcoital bleeding. Three years ago, the patient was diagnosed with HIV, but she stopped taking antiretroviral therapy due to medication side effects and has not seen a provider since then. She does not use tobacco, alcohol, or illicit drugs. Vital signs are normal. On examination, the uterus is small, mobile, and nontender. There is an ulcerative lesion on the posterior aspect of the cervix that bleeds with contact. The rest of the cervix has no lesions, and there is no endocervical discharge. The left inguinal lymph nodes are enlarged and nontender. Which of the following pathogens is the most likely cause of this patient's presentation?
(Multiple Choice)
4.8/5 (75)
(75) A 22-year-old woman, gravida 1 para 0, at 36 weeks gestation comes to the office for a routine prenatal visit. The patient has had no contractions, vaginal bleeding, or leakage of fluid. Fetal movement is normal. The patient has a history of genital herpes simplex virus but has not had an outbreak in several years. She has had no vulvar pain or pruritus and has not noticed any vulvar lesions. Her pregnancy has otherwise been uncomplicated, and her only medication is a daily prenatal vitamin. Vital signs are normal. Fetal heart rate is 145/min. Fundal height is 36 cm. On pelvic examination, no lesions are noted on the vulva, vagina, or cervix. The remainder of the physical examination is unremarkable. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (69)
(69) A 26-year-old woman comes to the emergency department due to a bump on her vaginal introitus. The patient first noticed the mass 2 days ago, but it has increased in size and now causes discomfort when she walks or exercises. She had unprotected sex with a new partner 6 weeks ago and has had 10 lifetime partners. The patient had an abnormal Pap test last year but had a normal colposcopy. She smokes a half pack of cigarettes daily but does not use alcohol or illicit drugs. Temperature is 36.7 C (98.1 F), blood pressure is 110/60 mm Hg, and pulse is 80/min. On pelvic examination, the pubic hair is shaved. There is a 4-cm, mobile, soft, nontender cystic mass behind the right posterior labium majus that extends into the vagina. The remainder of the examination is normal. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
5.0/5 (85)
(85) A 32-year-old woman comes to the emergency department due to severe pelvic pain. The patient developed pelvic cramping 2 days ago, the day after her menstrual period ended. She describes the pain as "worse than labor contractions," and it has been unrelieved by ibuprofen. The patient has monthly menstrual cycles with heavy flow, and she occasionally passes clots. She has no chronic medical conditions. Her only surgery was a dilation and curettage for a spontaneous abortion 5 years ago. The patient is sexually active and does not use routine contraception. Blood pressure is 140/90 mm Hg and pulse is 113/min. Pelvic examination shows an irregularly enlarged uterus. The cervix is dilated 5 cm with a spherical mass visible through the external os. The mass is firm and round, and slight bleeding is noted around it. Which of the following is the most likely cause of this patient's presentation?
(Multiple Choice)
4.8/5 (83)
(83) A 39-year-old woman comes to the office for evaluation of vaginal discharge. For the past few days, the patient has had pink-tinged vaginal discharge, requiring her to wear a menstrual pad. She has had associated pelvic cramping, which has improved with ibuprofen. A week ago, the patient underwent a uterine artery embolization for symptomatic uterine fibroids. Temperature is 36.7 C (98 F), blood pressure is 122/76 mm Hg, and pulse is 82/min. The abdomen is soft, nontender, and without rebound or guarding. There is diffuse pelvic discomfort to deep palpation. On pelvic examination, there is profuse, blood-tinged, watery vaginal discharge. Wet mount microscopy shows multiple leukocytes, but no clue cells, pseudohyphae, or trichomonads. Complete blood count results are as follows:  Urine pregnancy testing is negative. Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (78)
(78) A 28-year-old woman, gravida 2 para 1, at 38 weeks gestation is admitted to labor and delivery due to prelabor rupture of membranes. Clear amniotic fluid has been leaking continuously for the last 2 hours. The patient has irregular, nonpainful contractions and no vaginal bleeding. Prenatal care during this pregnancy has been uncomplicated, and the patient's previous pregnancy ended in a term vaginal delivery. Temperature is 36.7 C (98.1 F), blood pressure is 120/70 mm Hg, and pulse is 78/min. The cervix is 3 cm dilated and 50% effaced with the fetal vertex at ?2 station. Fetal heart tracing on admission is as seen in the exhibit. After an oxytocin infusion is started for labor augmentation, the patient begins to have regular, painful contractions that require epidural anesthesia. Two hours later, temperature is 37.2 C (99 F), blood pressure is 120/80 mm Hg, and pulse is 80/min. On repeat examination the cervix is now 7 cm dilated, 100% effaced, with the fetal vertex at +1 station; and current fetal heart tracing is as seen in the exhibit. 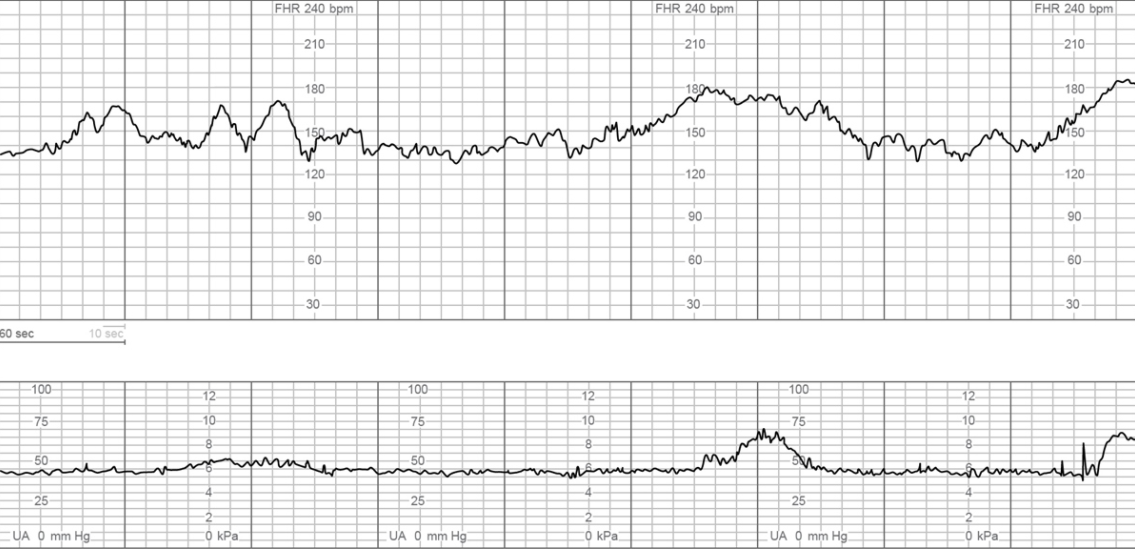 Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (80)
(80) A 33-year-old nulligravid woman comes to the office for evaluation of heavy menstrual bleeding. The patient has menses every 28 days with 7-8 days of heavy bleeding. She also has associated cramping, bloating, and pelvic fullness. The patient has episodic migraines with aura and takes preventive therapy. Family history is negative for ovarian, breast, and endometrial cancer. The patient recently started taking prenatal vitamins because she is getting married and planning on pregnancy in the next few months. BMI is 24 kg/m². Vital signs are normal. On pelvic examination, the uterus is enlarged with an irregular contour. Transvaginal ultrasound shows multiple intramural uterine fibroids and a homogeneous endometrial stripe. Hemoglobin is 10 g/dL. Which of the following is the best next step in management for this patient?
(Multiple Choice)
4.8/5 (80)
(80) A 33-year-old woman, gravida 2 para 2, is evaluated 5 days after an emergency cesarean delivery that was performed for fetal distress. Her postoperative course has been complicated by endometritis that is currently being treated with intravenous gentamicin and clindamycin. The patient received no prenatal care during this pregnancy and came to the hospital in active labor. She would like to breastfeed but had difficulty breastfeeding her first child and switched to formula at 6 weeks postpartum, after she developed lactational mastitis. The patient uses cocaine several times a week. Temperature is 36.7 C (98 F) and blood pressure is 110/60 mm Hg. Admission laboratory results are as follows:  After delivery, the infant received both hepatitis B immunoglobulin and the hepatitis B vaccination. Which of the following is a contraindication to breastfeeding in this patient?
 (Multiple Choice)
4.9/5 (89)
(89) A 28-year-old woman, gravida 1 para 0, at 34 weeks gestation comes to the emergency department due to sudden-onset lower abdominal pain. The patient initially had intermittent flank pain over the past 4 days that improved with acetaminophen. For the last 2 hours, she has had excruciating pain in the right flank that radiates to her groin. She has had some irregular contractions but no vaginal bleeding or leakage of fluid. Fetal movement is normal. Her pregnancy has been uncomplicated, and she has no chronic medical conditions. Temperature is 37.5 C (99.5 F), blood pressure is 130/86 mm Hg, and pulse is 98/min. Fetal heart rate tracing shows a baseline of 155/min, moderate variability, multiple accelerations, and no decelerations. Tocodynamometer reveals irregular contractions every 7-15 minutes. There is tenderness to palpation over the right flank and right inguinal region. The uterus is nontender and the cervix is closed. Urinalysis shows moderate blood but is negative for white blood cells, leukocyte esterase, and nitrites. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (87)
(87) A 27-year-old woman, gravida 2 para 1, at 28 weeks gestation comes to the office for follow-up of an abnormal Pap test. She feels fetal movement, has no vaginal bleeding or contractions, and has had an uneventful pregnancy to date. The patient's previous pregnancy 5 years ago was uncomplicated. She has not had a previous abnormal Pap test, but the last test was performed during her prior pregnancy. The patient has no medical issues or previous surgeries. She takes a multivitamin and an iron supplement. She does not use tobacco, alcohol, or illicit drugs. Blood pressure is 120/74 mm Hg and pulse is 82/min. Fetal heart tones are normal. Physical examination reveals a gravid, nontender uterus. The cervix is long, closed, firm, and posterior, and the fetal presenting part is high. The Pap test showed a high-grade squamous intraepithelial lesion. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (90)
(90) A 20-year-old woman, gravida 1 para 0, at 36 weeks gestation is brought to the emergency department by her mother due to a seizure. The patient was sitting outside when she suddenly had a 2-minute seizure with loss of urinary continence. She is still confused when she arrives in the emergency department. Her mother reports that the patient has had increasing anxiety and has been acting out for the past several days. Her only surgery was a splenectomy after a motor vehicle collision last year. Temperature is 37.7 C (99.9 F), blood pressure is 158/98 mm Hg, and pulse is 120/min. The patient is agitated and diaphoretic. The pupils are dilated bilaterally. The cranial nerves are intact. The neck is supple and nontender. Cardiopulmonary examination is normal. The abdomen is gravid without rebound or guarding, and the uterus is nontender. There is 2+ pitting pedal edema bilaterally. Sensation and strength are normal in the bilateral upper and lower extremities. Laboratory results are as follows:  CT scan of the head is normal. Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.8/5 (77)
(77) A 32-year-old primigravid woman at 37 weeks gestation and in active labor is admitted to the labor and delivery unit. On admission, the cervix is 4 cm dilated and 80% effaced, with the fetal vertex at 0 station. The membranes are grossly ruptured with thin, clear amniotic fluid. Fetal heart rate tracing is category I, and the patient receives epidural anesthesia for pain management; she reports complete pain relief. The fetal heart rate tracing 10 minutes later is shown in the following image: 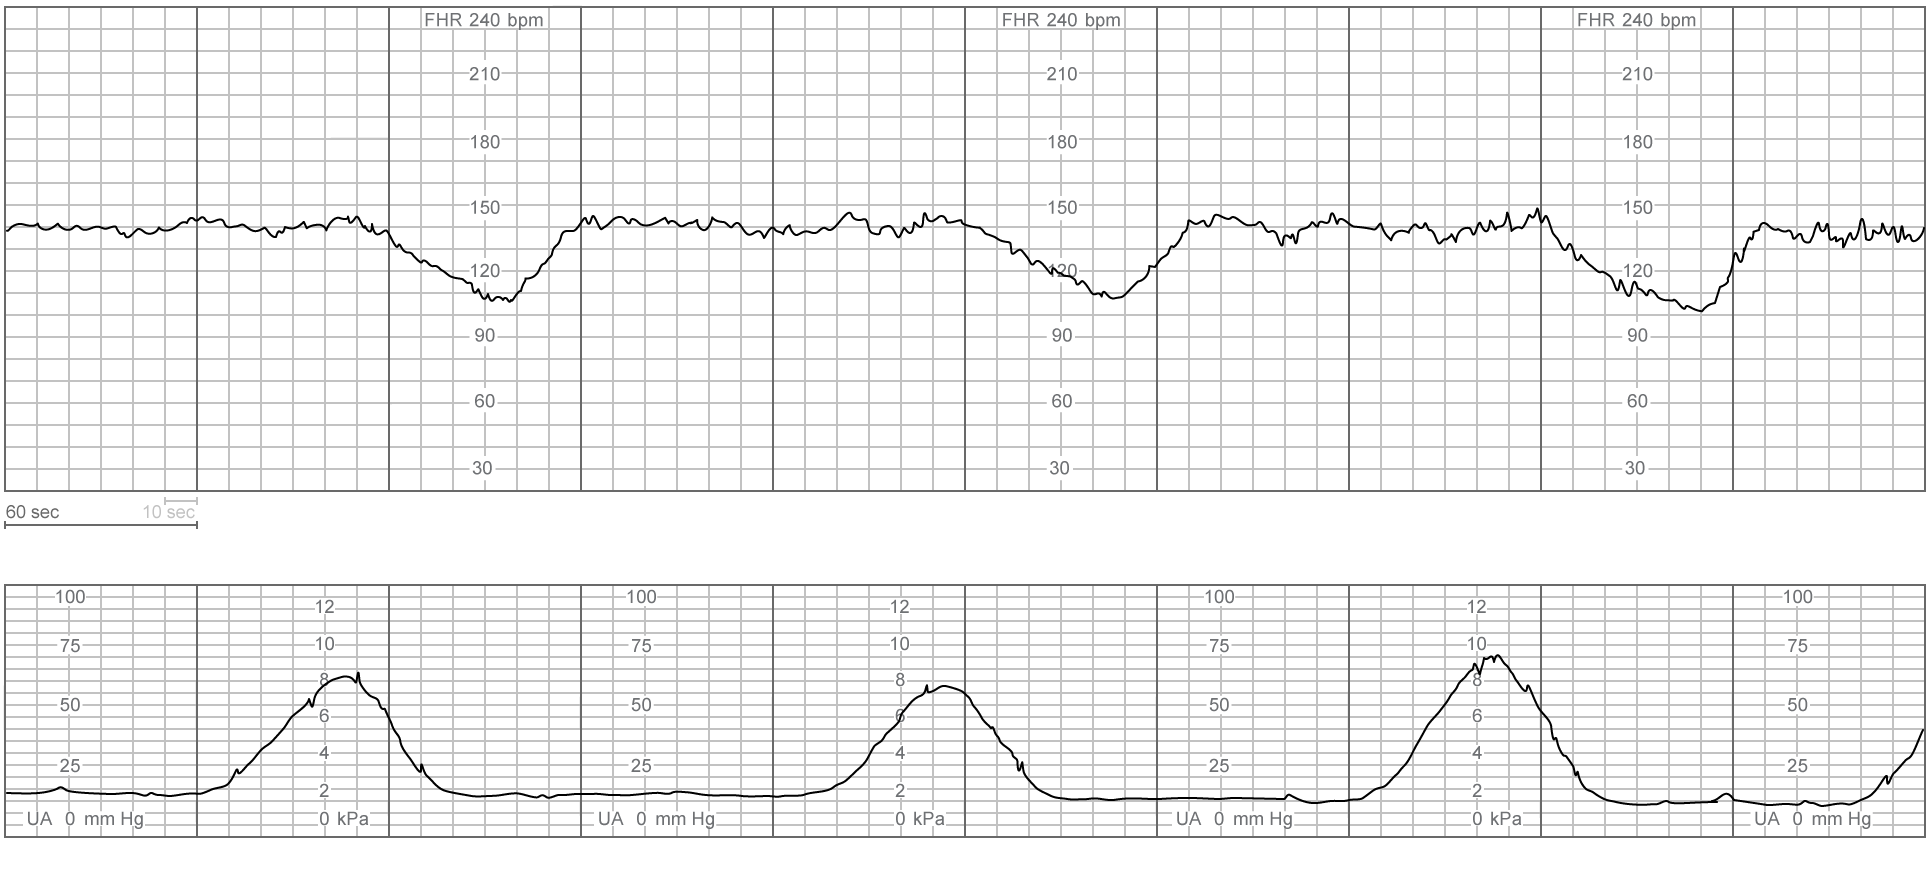 Maternal blood pressure is 60/40 mm Hg and pulse is 60/min. Repeat cervical examination shows the cervix to be 5 cm dilated and 100% effaced and the fetal vertex at +1 station. In addition to intravenous fluids, which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (64)
(64) A 38-year-old woman, gravida 1 para 0, comes to the office for her first prenatal visit. Her last menstrual period was 14 weeks ago. The patient has had nausea and vomiting occasionally over the past few weeks but no other symptoms. She has not seen a health care provider in years but has no known medical conditions. Her only daily medication is a prenatal vitamin. The patient does not use tobacco, alcohol, or illicit drugs. Supine blood pressure is 142/96 mm Hg and pulse is 92/min. Repeat measurement 15 minutes later is 138/92 mm Hg and pulse is 88/min. Cardiopulmonary examination is normal. Pelvic examination shows an enlarged uterus consistent with 14 weeks gestation. There is mild bilateral ankle edema. Doppler ultrasound shows a fetal heart rate of 160/min. Urinalysis is negative for protein and glucose.
Which of the following is the most likely cause of this patient's hypertension?
(Multiple Choice)
4.8/5 (69)
(69) A 34-year-old woman, gravida 3 para 2, at 35 weeks gestation is evaluated in the labor and delivery unit due to increasing mucoid vaginal bleeding and contractions. The patient has been undergoing an induction of labor for fetal growth restriction due to chronic hypertension. Pelvic examination an hour ago showed the cervix to be 6 cm dilated and 100% effaced after spontaneous rupture of membranes. Since then, the patient has developed increasing bloody discharge with some clots. Contractions have also increased in intensity and frequency. Group B Streptococcus rectovaginal culture performed last week was negative. Temperature is 37.2 C (99 F), blood pressure is 150/90 mm Hg, and pulse is 78/min. Fetal heart rate tracing shows a baseline of 120/min, moderate variability, multiple early decelerations, and no accelerations. Contractions occur every 2 minutes. The cervix is 8 cm dilated and 100% effaced with a moderate amount of mucus and blood on examination. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.7/5 (75)
(75) An 18-year-old nulligravid woman comes to the office for emergency contraception. The condom broke during sexual intercourse the previous night, and she does not want to become pregnant. The patient and her longtime boyfriend have always used condoms, and their evaluations for sexually transmitted infections have been negative. Her last menstrual period was 2 weeks ago. She takes no medications and does not use tobacco, alcohol, or recreational drugs. Blood pressure is 122/80 mm Hg and pulse is 86/min. BMI is 27 kg/m2. Physical examination is normal and a pregnancy test is negative. Which of the following is the most effective emergency contraceptive method for this patient?
(Multiple Choice)
4.9/5 (83)
(83) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)