



 Chat with AI
Exam 5: Obstetrics & Gynecology

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 32-year-old primigravid woman at 20 weeks gestation comes to the office for a routine prenatal visit. She has no vaginal bleeding, leakage of fluid, or contractions. The patient had mild nausea that resolved at 14 weeks gestation. A fetal anatomical sonogram performed a week ago revealed no abnormalities. The patient has no chronic medical issues or previous surgeries. She is taking a daily prenatal vitamin and does not use tobacco, alcohol, or illicit drugs. The patient works in a laboratory as a biotechnology research assistant. She has blood group O, Rh(D) positive, and her husband has blood group AB, Rh(D) positive. On physical examination, the fundus is palpable at the umbilicus, and the fetal heart rate is 140/min. The patient is concerned about different blood groups and the risk of pregnancy complications. Which of the following is the most appropriate response to this patient?
(Multiple Choice)
4.8/5  (80)
(80) A 46-year-old woman comes to the office for evaluation of an abdominal mass. The patient first noticed a small abdominal mass 2 months ago that was not painful and did not cause any issues. However, over the past month, the mass has slowly grown and sometimes causes mild abdominal discomfort. The patient has had no weight loss, nausea, vomiting, or changes in bowel patterns. She underwent a total abdominal hysterectomy and bilateral salpingo-oophorectomy for uterine sarcoma 6 years ago. Vital signs are normal. BMI is 32 kg/m2. The patient has a large, vertical midline abdominal scar consistent with her prior surgery. There is a small, nontender mass at the midline that is palpable while the patient is supine and increases in size with Valsalva. Bowel sounds are normal; there is no rebound or guarding. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (68)
(68) A 32-year-old woman, gravida 5 para 1 aborta 3, at 37 weeks gestation comes to the hospital due to rupture of membranes and contractions over the past hour. The patient is tolerating her contractions well. She has had 3 prior miscarriages, and her most recent pregnancy ended at 29 weeks gestation due to preeclampsia with severe features. The current pregnancy has been complicated by diet-controlled gestational diabetes mellitus and asymptomatic group B Streptococcus bacteriuria. Blood pressure is 134/86 mm Hg, and pulse is 98/min. The uterus is nontender and has palpable contractions. Fetal heart rate tracing is category 1. The cervix is 5 cm dilated and 80% effaced, with the fetal vertex at −1 station. Blood glucose is 110 mg/dL. Which of the following additional therapy is indicated at this time?
(Multiple Choice)
4.9/5 (73)
(73) A 37-year-old woman, gravida 1 para 0, at 25 weeks gestation is evaluated in the antepartum unit due to increasing chest pain. The patient describes a sharp, substernal chest pain that is worse with inspiration and radiates to the right upper quadrant. She has no fever, cough, or rashes. The patient has had no vaginal bleeding or leakage of fluid. She has a twin pregnancy and was admitted for inpatient monitoring for preterm labor 6 days ago. The patient has reduced her activity level because walking increases the contractions, and she has been receiving heparin for venous thromboembolism prophylaxis. Her pregnancy has been otherwise uncomplicated. Temperature is 37.2 C (99 F), blood pressure is 130/86 mm Hg, pulse is 116/min, and respirations are 24/min. Heart rates for both fetuses are 155/min. Lung auscultation shows decreased breath sounds over the right lung base. The uterus is nontender. The lower extremities have bilateral 1+ pitting edema to the knees. Laboratory evaluation is as follows:  Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.8/5 (88)
(88) A 48-year-old woman comes to the clinic because she is "urinating all the time." The patient initially had some leakage of urine with sneezing or coughing, but now she leaks while walking to the bathroom. She voids frequently during the day and several times each night. The patient sometimes has an intense urge to urinate but passes only a small amount when she tries to void. She now wears a pad every day and plans her social outings based on bathroom access. The patient has had no dysuria or hematuria. She had 2 vaginal deliveries in her 20s. She drinks alcohol socially, has 2 or 3 cups of coffee each morning, and "drinks lots of water throughout the day." When asked which urinary symptoms are the most troublesome, the patient is unsure. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (80)
(80) A 24-year-old woman, gravida 1 para 0, at 26 weeks gestation comes to the office due to increased urinary frequency and back pain. For the past 2 weeks, the patient has had to urinate almost hourly during the day and has awakened multiple times each night to void. She has also developed back pain and occasionally has a sharp, pulling pain in the right groin. The patient has no nausea, vomiting, dysuria, or hematuria. She has had no vaginal bleeding, leakage of fluid, or contractions. Fetal movement is normal. The patient has had recurrent nephrolithiasis outside of pregnancy. Temperature is 37.2 C (99 F), blood pressure is 130/80 mm Hg, and pulse is 72/min. There is tenderness to palpation throughout the lower back and along the paravertebral muscles. Laboratory results are as follows:  Renal and pelvic ultrasound of the mother reveals bilateral enlargement of the kidneys. The right kidney is larger than the left; there is dilation of the renal pelvis and proximal ureter on both sides. Which of the following is the best next step in management of this patient's condition?
 (Multiple Choice)
4.7/5 (83)
(83) A 29-year-old woman, gravida 1 para 0, comes to the office to establish prenatal care. The patient is at 16 weeks gestation by a sure, regular last menstrual period. She had nausea and vomiting for a few weeks, but her symptoms have gradually improved. She has had no vaginal bleeding or cramping. The patient has no chronic medical conditions and has not been taking a prenatal vitamin because she thinks it caused her nausea. She underwent a cold knife conization 2 years ago for cervical intraepithelial neoplasia 3 but has had no other surgeries. Family history is significant for her sister developing gestational diabetes mellitus during her last pregnancy. Temperature is 37 C (98.6 F), blood pressure is 100/64 mm Hg, and pulse is 72/min. BMI is 22 kg/m². Fetal heart rate is 140/min by Doppler ultrasound. Cardiopulmonary examination is normal. The abdomen is soft, nontender, and nondistended. On pelvic examination, there are no cervical lesions or abnormal discharge. Uterine size is consistent with 16 weeks gestation. In addition to routine prenatal care, which of the following additional interventions is indicated in this patient?
(Multiple Choice)
4.8/5 (73)
(73) A 38-year-old woman, gravida 3 para 2, at 37 weeks gestation comes to the labor and delivery unit for contractions. Her contractions started this morning and now are painful and occur every 5 minutes. The patient has had no leakage of fluid or vaginal bleeding. Fetal movement is normal. Previous pregnancies ended in uncomplicated term vaginal deliveries. The patient was diagnosed with HIV at her first prenatal visit during this pregnancy, and her viral load one week ago was 12,300 copies/mL. She does not always take her combination antiretroviral therapy but takes a daily prenatal vitamin. Blood pressure is 132/86 mm Hg and pulse is 98/min. The patient is tolerating labor well, and the uterus is soft and nontender between contractions. The fetal heart rate tracing is shown in the exhibit. 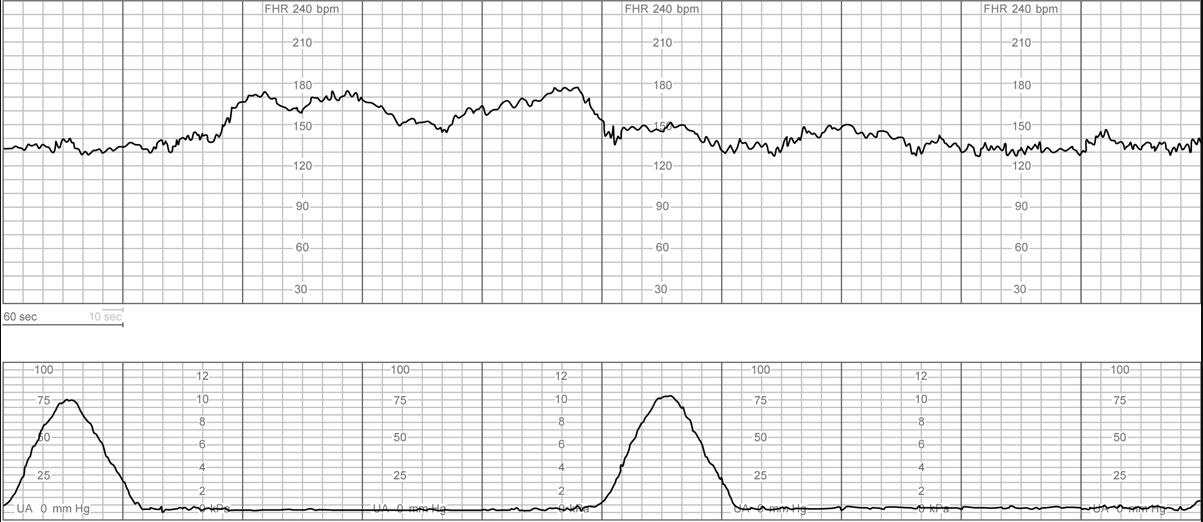 The cervix is 4 cm dilated and 100% effaced and the fetal vertex is at 0 station. The amniotic sac is tense and palpable. In addition to starting zidovudine, which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.7/5 (80)
(80) A 32-year-old primigravida at 16 weeks gestation comes to the office due to urinary frequency and increased thirst. Although she limits fluids before bed, she still urinates 6-8 times a night. The patient previously had intermittent urinary frequency, but symptoms have worsened since she became pregnant. Family history is significant for type 2 diabetes mellitus in her mother and father. Vital signs are within normal limits. Examination shows no abnormalities. Laboratory results are as follows:  A 24-hour urine collection shows a urine output of 5.5 L after an intake of 2 L. What is the most likely cause of this patient's urinary frequency?
 (Multiple Choice)
4.7/5 (64)
(64) A 28-year-old nulligravid woman comes to the office for a routine examination. She feels well but has tried to conceive for the past 12 months without success. The patient has had sexual intercourse with her husband 3 or 4 times a week without contraception. Her menses are irregular with frequent missed periods. Every time the patient misses a period, her home pregnancy tests are negative. She has no medical conditions and has had no surgeries. The patient takes a daily prenatal vitamin and does not use tobacco, alcohol, or illicit drugs. Vital signs are normal. There is no excess hair on physical examination. Breast examination shows no masses or nipple discharge. The abdomen is soft without masses. Pelvic examination shows normal external genitalia and a small, mobile uterus. Pelvic ultrasonography shows a normal uterus and bilateral ovaries. Laboratory results are as follows:  Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.8/5 (73)
(73) A 34-year-old woman comes to the office for a routine examination. The patient has regular menses every 28 days that last 5 days; the first 2 days are accompanied by crampy abdominal pain that is relieved with ibuprofen. Her last menstrual period was 2 weeks ago. She is sexually active with her husband, who has had a vasectomy. On review of systems, the patient reports intermittent dull pelvic pain that started 2 days ago; the pain is worse with physical activity. Similar pain episodes occasionally occur about a week before menses. The patient has had no abdominal swelling or bloating, nausea, vomiting, or changes in bowel or bladder habits. Vital signs are normal. The abdomen is nontender and nondistended and has normal bowel sounds. Speculum examination shows a normal-appearing cervix. Bimanual examination reveals a 4-cm, nontender, right adnexal mass. The remainder of the physical examination is unremarkable. Urine pregnancy test is negative. Which of the following is the best next step in management for this patient?
(Multiple Choice)
4.9/5 (70)
(70) A 43-year-old patient, gravida 6, para 5, at 39 weeks gestation has a brief generalized tonic-clonic seizure in the delivery room. She became disoriented, lightheaded, breathless, and cyanotic 20 minutes after an uncomplicated spontaneous vaginal delivery of a healthy neonate and placenta. Her pregnancy was uncomplicated, and she has no past medical history. Her blood pressure is 80/40 mm Hg, pulse is 110/min, and respirations are 30/min. Oxygen saturation is 75% on facemask. Examination shows an unconscious woman who is no longer seizing. A generalized purpuric rash and bleeding from the intravenous line site are seen. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.7/5 (82)
(82) A 27-year-old woman, gravida 2 para 1, at 40 weeks gestation has a forceps-assisted vaginal delivery after pushing for 2 hours. She was diagnosed with preeclampsia with severe features on admission and is receiving a magnesium sulfate infusion. Her first pregnancy ended with a cesarean delivery at 39 weeks gestation for breech presentation. Temperature is 37.2 C (99 F), blood pressure is 150/100 mm Hg, and pulse is 112/min. Ten minutes after delivery, the placenta delivers with gentle traction, and the patient develops profuse vaginal bleeding. Bimanual massage reveals a firm, nontender uterus with the fundus at the level of the umbilicus. Pelvic examination shows a right vaginal sidewall defect. There is minimal bleeding from the cervical os, and the perineum is intact. Which of the following is the most likely cause of this patient's bleeding?
(Multiple Choice)
4.9/5 (97)
(97) A 39-year-old woman, gravida 1 para 1, comes to the office due to breast pain. She had an uncomplicated vaginal delivery a week ago and is breastfeeding her infant. Four days ago, the patient began to have bilateral nipple soreness with breastfeeding. However, for the past few days, the pain has worsened, is present between feeds, and has prevented breastfeeding. She has also developed bloody nipple discharge. The patient's pregnancy was complicated by gestational diabetes mellitus, but otherwise, she has no chronic medical conditions. Temperature is 37.5 C (99.5 F). Bilateral nipples and areolae have open, bloody, linear abrasions. The breasts are diffusely engorged and mildly tender to palpation, but there are no palpable masses or lymphadenopathy. The remainder of the examination is unremarkable. Which of the following is the most likely underlying cause of this patient's presentation?
(Multiple Choice)
4.8/5 (84)
(84) A 33-year-old woman, gravida 2 para 1, comes to the clinic for a routine prenatal visit at 26 weeks gestation. Her pregnancy has been uncomplicated. The patient's BMI was 23 kg/m2 at her initial prenatal visit, and her laboratory results were as follows:  An ultrasound at 20 weeks gestation showed an anterior placenta and normal fetal anatomy. The patient's only concern today is lower leg swelling that occurs after prolonged standing but resolves with sitting or lying down. Her last pregnancy was complicated by Group B Streptococcus colonization requiring prophylaxis during delivery. The patient has no chronic medical problems and takes only prenatal vitamins. She is a radiologist and does not use tobacco, alcohol, or drugs. Blood pressure is 135/80 mm Hg and pulse is 65/min. Physical examination shows minimal pedal edema and negative Homan sign bilaterally. Fundal height is 27 cm and fetal heart rate is 140/min. Which of the following tests should be obtained at this visit?
 (Multiple Choice)
4.9/5 (72)
(72) A 28-year-old primigravida was admitted to the hospital in active labor. On admission, her cervix was 7 cm dilated and 100% effaced. She received epidural anesthesia and proceeded to complete cervical dilation with the fetal head at +3 station within a few hours. The patient has been pushing for 4 hours and is exhausted. She cannot feel her contractions and does not know when to push because of her epidural anesthesia. The patient has had no complications during the pregnancy and has no chronic medical conditions. The estimated fetal weight by Leopold maneuvers is 3.4 kg (7.5 lb). Vital signs are normal. Fetal heart rate tracing is category 1. Tocodynamometer indicates contractions every 2-3 minutes. A repeat cervical examination shows complete cervical dilation with the fetal head at +3 station and in the left occiput anterior position with no molding or caput. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (92)
(92) A 47-year-old woman comes to the office due to lower abdominal pain that is relieved with urination. The pain has worsened over the past 2 months and she now urinates hourly to minimize the pain. The patient is sexually active but has avoided intercourse recently because it has become painful. She had 4 vaginal deliveries in her 30s and a tubal ligation after her last delivery. The patient has irritable bowel syndrome and takes no medications. Vital signs are normal. BMI is 27 kg/m2. There is tenderness to palpation over the lower abdomen. On bimanual examination, the anterior vaginal wall is tender to palpation, but there is no cervical motion tenderness. The remainder of the pelvic examination is normal, and Valsalva does not elicit any noticeable changes. Urinalysis results are as follows:  A urine culture is negative. Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.8/5 (78)
(78) A 32-year-old woman, gravida 2 para 1, with dichorionic-diamniotic twins at 34 weeks gestation is brought to the emergency department after developing leakage of fluid an hour ago. While in the emergency department, the patient has a sudden large gush of fluid that is followed by heavy vaginal bleeding and constant lower abdominal pain. Her pregnancy has been complicated by gestational hypertension, but the patient has not required any antihypertensive therapy. The patient's last pregnancy ended in a cesarean delivery for breech presentation. Her prior prenatal ultrasounds showed 2 fundal placentas. Blood pressure is 160/100 mm Hg and pulse is 118/min. Fetal heart rate tracing shows both fetuses with baselines of 110/min and no variability. The uterus is firm, tender, and has a fundal height of 38 cm. Speculum examination shows approximately 75 mL of red blood in the vagina. After evacuation of the blood, a moderate amount of continued bleeding is observed coming from the cervical os that is 3 cm dilated. Which of the following is the most likely cause of this patient's presentation?
(Multiple Choice)
4.9/5 (89)
(89) A 29-year-old primigravida at 36 weeks gestation comes to the office with her husband for a routine prenatal visit. Her pregnancy has been uncomplicated, and she has no chronic medical conditions. Her only medication is a daily prenatal vitamin. Vital signs are normal. Fundal height is 36 cm, and fetal heart sounds are 150/min on Doppler ultrasound. The patient says she has created a detailed birth plan and would like to have a natural delivery. She says a vaginal birth is necessary for her to feel fully connected to her baby, and she is not interested in receiving any medication to decrease the pain. The patient's wishes are acknowledged and documented in the chart; however, the physician states that unexpected events can occur during labor and delivery that require a cesarean delivery. The patient replies, "A cesarean delivery is not part of my birth plan-I don't want to have one." Which of the following is the most appropriate response?
(Multiple Choice)
4.8/5 (76)
(76) A 15-year-old girl is brought to the office by her mother due to concerns that her daughter has not had a menstrual period. The patient was born at 36 weeks gestation but has had no developmental delay. She is doing well in school and plays on the tennis team. The patient is healthy and takes no medications. She is not sexually active and does not use tobacco, alcohol, or illicit drugs. Family history is significant for a maternal aunt with primary infertility and a maternal grandmother with ovarian cancer. Height is 174 cm (5 ft 7 in), and weight is 63 kg (138.9 lb). Vital signs are normal. There is no acne or excessive hair growth. Breast development is sexual maturity rating (Tanner) stage 5. There is scant axillary and pubic hair. On pelvic examination, the external genitalia appear normal and speculum examination shows a blind vaginal pouch. The uterus, cervix, and ovaries are absent on bimanual examination. Karyotype analysis of this patient is most likely to show which of the following?
(Multiple Choice)
4.9/5 (87)
(87) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)