



 Chat with AI
Exam 5: Obstetrics & Gynecology

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 28-year-old woman, gravida 1 para 0, at 35 weeks gestation comes to the emergency department due to nausea, vomiting, and right upper quadrant pain. The patient's symptoms began last night but have progressively worsened throughout the day. Temperature is 37.2 C (99 F), blood pressure is 160/94 mm Hg, and pulse is 80/min. Physical examination shows right upper quadrant tenderness without rebound or guarding. Fetal heart rate tracing shows a baseline of 140 with moderate variability, no decelerations, and no accelerations. Cardiopulmonary examination is unremarkable. The abdomen is tender to palpation over the right upper quadrant; the uterus is nontender. There is 2+ edema of the lower extremities. Laboratory results are as follows:  Which of the following is the most likely cause of this patient's presentation?
 (Multiple Choice)
4.8/5  (79)
(79) A 23-year-old woman, gravida 2 para 1, at 30 weeks gestation comes to the emergency department after having a sudden gush of clear vaginal fluid. The patient continues to have leakage of clear fluid but no abdominal pain or vaginal bleeding. Fetal movement has been normal. The patient had intermittent vaginal bleeding during the first trimester but no other complications during this pregnancy. Her prior pregnancy ended in a term vaginal delivery. Temperature is 37.2 C (99 F), blood pressure is 110/70 mm Hg, and pulse is 82/min. The uterine fundus is nontender. Sterile speculum examination reveals a closed cervix and vaginal pooling of nitrazine-positive, clear fluid. Ultrasound reveals a fetus in the breech presentation and decreased amniotic fluid. Fetal heart rate tracing has a baseline of 130/min, moderate variability, and no decelerations. Tocometry shows no contractions. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (64)
(64) An 18-year-old, nulliparous woman comes to the office with lower abdominal pain, nausea, and vomiting for the past day. She has been unable to tolerate food or water for the past 8 hours. The patient is sexually active and uses oral contraceptive pills. She has had 3 lifetime sexual partners. Her last menstrual period was 15 days ago. The patient has no medication allergies. Temperature is 39 C (102.2 F), blood pressure is 100/70 mm Hg, and pulse is 110/min. Physical examination reveals dry mucous membranes and delayed capillary refill. The abdomen has diffuse tenderness over the lower quadrants. The external genitalia have no abnormalities; speculum examination shows purulent discharge from the cervical os. The uterus is small, anteverted, and tender to palpation and motion. The adnexa are markedly tender bilaterally, with no palpable masses. Cervical nucleic acid amplification testing is pending. Urine pregnancy test is negative. Laboratory results are as follows:  Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (83)
(83) A 43-year-old primigravida at 37 weeks gestation comes to the labor and delivery department for evaluation of a severe headache that began this morning. The patient now has dark spots in her vision but no epigastric pain, nausea, or vomiting. She also has irregular, nonpainful contractions but no vaginal bleeding or loss of fluid. The patient has myasthenia gravis and takes pyridostigmine; she has no other chronic medical conditions or pregnancy complications. Rectovaginal screening for group B Streptococcus was positive at 35 weeks gestation. Blood pressure is 184/106 mm Hg and pulse is 88/min. The abdomen is soft, gravid, and nontender. The cervix is 3 cm dilated and 50% effaced, and the fetal vertex is at -1 station. Fetal heart rate tracing demonstrates a baseline of 130/min, moderate variability, multiple accelerations, and no decelerations. Tocodynamometry reveals contractions every 8-10 minutes. The patient is admitted for induction of labor due to preeclampsia with severe features. Which of the following medications is contraindicated in this patient?
(Multiple Choice)
4.8/5 (83)
(83) A 25-year-old woman, gravida 2 para 1, at 33 weeks gestation comes to the emergency department due to intermittent contractions that began after intercourse. The contractions initially occurred every 10-15 minutes and lasted 1 or 2 minutes. The patient drank some water and tried to rest, but the contractions continued. She has no vaginal bleeding or leakage of fluid. Fetal movement is normal. At 12 weeks gestation, the patient had a urinary tract infection caused by group B Streptococcus that was treated with antibiotics. Prenatal care has otherwise been uncomplicated. The patient's prior pregnancy ended with a term vaginal delivery. Temperature is 36.7 C (98.1 F) and blood pressure is 100/70 mm Hg. Fetal heart rate tracing has a baseline of 150/min, moderate variability, and multiple accelerations. Tocodynamometry shows contractions every 5-8 minutes. On speculum examination, the cervix is visibly 3 cm dilated and there is no evidence of rupture of membranes. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (67)
(67) A 23-year-old woman comes to the physician at 9 weeks gestation for prenatal counseling. This is her first pregnancy. She has no history of bleeding, and there is no history of hemophilia in her husband's family. However, the patient's father and other relatives have hemophilia A, and she is concerned about the possibility of her child having the disease. The following pedigree is created according to the patient's family history (arrow points to the patient). 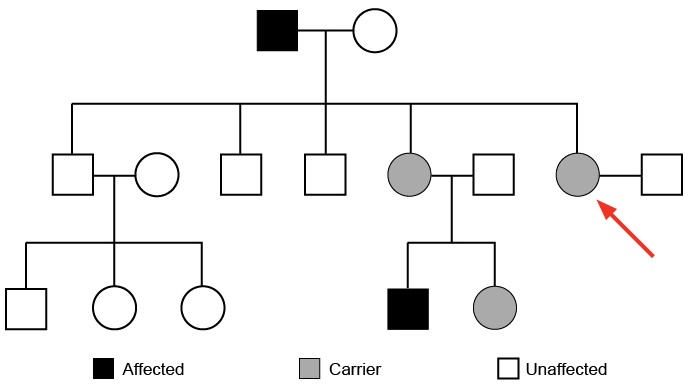 Which of the following is the best response to this patient's concern?
 (Multiple Choice)
4.9/5 (90)
(90) A 24-year-old woman, gravida 1 para 0, at 28 weeks gestation comes to the office for a routine prenatal visit. She reports active fetal movement and has had no vaginal bleeding, leakage of fluid, or contractions. The patient has no chronic medical conditions and has had no prior surgery. She does not use tobacco, alcohol, or illicit drugs. At her initial visit in the first trimester, prenatal testing results were as follows:  The patient and her partner were treated with azithromycin, and the patient had subsequent negative C trachomatis testing a month later. Blood pressure is 118/74 mm Hg and pulse is 90/min. BMI is 34 kg/m2. Fundal height is 28 cm and fetal heart tones are 130/min. A 1-hour glucose challenge, complete blood count, and C trachomatis test are ordered. Which of the following additional screening tests are indicated for this patient at today's 28-week gestation prenatal visit?
 (Multiple Choice)
4.9/5 (93)
(93) A 24-year-old primigravida comes to the emergency department for evaluation of pelvic pain. The pain began a week ago as mild cramping but is now constant and severe. The patient had a positive home pregnancy test 3 weeks ago and has also recently had some brown vaginal spotting. She has no chronic medical conditions or previous surgeries. Blood pressure is 110/60 mm Hg and pulse is 108/min. The abdomen is tender to palpation over the left lower quadrant and rebound is present. Initial laboratory results are as follows:  Pelvic ultrasound shows a small uterus with a thin endometrium, an 8-week fetal pole in the left adnexa with cardiac motion, and a large amount of free fluid in the pelvis. Laparoscopy confirms hemoperitoneum and a ruptured left fallopian tube; a left salpingectomy is subsequently performed. On postoperative day 1, the patient's blood pressure is 116/78 mm Hg and pulse is 88/min. Repeat laboratory results are as follows:
 Which of the following is the best next step in management of this patient?
Pelvic ultrasound shows a small uterus with a thin endometrium, an 8-week fetal pole in the left adnexa with cardiac motion, and a large amount of free fluid in the pelvis. Laparoscopy confirms hemoperitoneum and a ruptured left fallopian tube; a left salpingectomy is subsequently performed. On postoperative day 1, the patient's blood pressure is 116/78 mm Hg and pulse is 88/min. Repeat laboratory results are as follows: Which of the following is the best next step in management of this patient? (Multiple Choice)
4.9/5 (71)
(71) A 63-year-old woman comes to the office for evaluation of postmenopausal bleeding. The patient initially had post-coital bleeding only, but it has become more frequent despite the use of over-the-counter vaginal lubricants and moisturizers. For the last month, the patient has had daily vaginal spotting and is beginning to have pain with intercourse. Until 6 months ago, she had not been sexually active for 10 years. The patient has had no routine health care since the birth of her children over 30 years ago. She smokes a pack of cigarettes a day. BMI is 30 kg/m2. The vagina appears atrophic with minimal rugation and has a 1-cm ulcerated lesion in the upper third of the posterior wall. There is a malodorous watery discharge in the vagina. Numerous squamous epithelial cells with rare leukocytes are seen on wet mount microscopy. Potassium hydroxide test is negative. Pelvic ultrasound shows an anteverted uterus with a 3-mm endometrial stripe. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.7/5 (78)
(78) A 32-year-old woman comes to the office for evaluation of absent menses. The patient had a vaginal delivery 4 months ago, and she has not had a menstrual period since delivery. Her postpartum course was complicated by a postpartum hemorrhage, requiring blood transfusion and emergency suction and sharp curettage. At her postpartum visit 2 months ago, the patient was started on combination oral contraceptives and has had no vaginal bleeding or spotting during her week of placebo pills. Prior to this pregnancy, she had regular, monthly menstrual cycles with 3-4 days of moderate bleeding. The patient has had increased fatigue since returning to work and is bottle-feeding. She has no headaches, galactorrhea, or hot flushes. Vital signs are normal. BMI is 31 kg/m2. Pelvic examination shows clear vaginal discharge throughout the vault and a well-rugated vagina. The uterus is small and anteverted, and there are bilateral small, nontender ovaries. Urine pregnancy test is negative. FSH and TSH levels are normal. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (82)
(82) A 28-year-old woman comes to the emergency department due to nausea, vomiting, and abdominal pain. For the past 2 days, the patient has had increasing abdominal pain and distension, which are now severe and causing persistent vomiting. She had an episode of watery diarrhea but has had no fevers, chills, or sick contacts. The patient has no chronic medical conditions. She has been undergoing ovulation induction for infertility treatment. Her last hCG injection was 7 days ago, and her last menstrual period was 3 weeks ago. Blood pressure is 100/60 mm Hg, pulse is 104/min, and respirations are 24/min. BMI is 21 kg/m2. Cardiac examination reveals sinus tachycardia. The lungs have decreased breath sounds in bilateral bases. The abdomen is distended and has tympany but no rebound or guarding. Laboratory results are as follows:  Pelvic ultrasound reveals a small uterus with a thin endometrium, bilateral enlarged ovaries with multiple cysts, and a large amount of free fluid within the abdomen. Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.9/5 (89)
(89) A 34-year-old woman comes to the office due to a positive home pregnancy test, which she took after developing daily nausea and vomiting. The patient has had no vaginal bleeding or cramping. She has no chronic medical conditions and has had 2 cesarean deliveries. The patient's last delivery was 8 months ago, and she is still breastfeeding her infant. Temperature is 36.7 C (98.1 F), blood pressure is 120/70 mm Hg, and pulse is 76/min. Cardiopulmonary examination is normal. The abdomen is soft, nontender, and nondistended. Pelvic examination reveals a small, mobile uterus. Serum β-hCG level is 6,134 mIU/mL. A transvaginal ultrasound shows a uterus with a thin endometrial stripe and a 5-cm complex mass with fetal cardiac activity. The mass appears within the interstitial segment of the proximal fallopian tube and embedded in the myometrium. Bilateral adnexa appear normal. There is no free fluid in the pelvis. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (70)
(70) A 37-year-old woman, gravida 2 para 1, at 8 weeks gestation comes to the office for a follow-up visit. Earlier in the pregnancy, the patient had nausea and breast tenderness that resolved several days ago. She has no other concerns. At her initial prenatal visit a week ago, ultrasound revealed an intrauterine gestational sac with a yolk sac but no fetal pole. β-hCG level at that visit was 27,325 IU/L. She is taking a prenatal vitamin and does not use tobacco, alcohol, or illicit drugs. Current blood pressure is 140/80 mm Hg and pulse is 68/min. BMI is 23 kg/m2. Pelvic examination reveals a closed cervix and no vaginal discharge or bleeding. Bimanual examination reveals a normal-sized, retroverted uterus with no cervical motion or adnexal tenderness. A transvaginal ultrasound is repeated and is unchanged from the prior visit. β-hCG level is now 25,659 IU/L. Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5 (90)
(90) A 28-year-old primigravid woman at 30 weeks gestation comes to the office for a routine prenatal visit. The patient has had an uncomplicated prenatal course with normal prenatal laboratory results, including a negative urine culture during the first trimester. She feels well and has had no contractions, leakage of fluid, or vaginal bleeding. The patient has no chronic medical conditions or medication allergies. Temperature is 37.2 C (99 F), blood pressure is 110/70 mm Hg, and pulse is 88/min. Physical examination, including fetal heart tones, is normal. At the end of the visit, the patient mentions that her niece recently died from neonatal group B streptococcal infection after preterm delivery at 36 weeks gestation and she is afraid that this could happen to her baby. Which of the following is the most appropriate response to this patient?
(Multiple Choice)
4.8/5 (71)
(71) A 54-year-old woman, gravida 3 para 3, comes to the office due to difficulty voiding for the past few weeks. When the patient voids, she has difficulty initiating the urine stream and emptying completely, but has no dysuria or hematuria. The patient has 2 episodes of nocturia every night, but no involuntary leakage of urine. She also has pelvic pressure that is worse with standing. Ten months ago, the patient underwent a total abdominal hysterectomy with bilateral salpingo-oophorectomy for epithelial ovarian cancer and has completed a course of chemotherapy. Vital signs are normal. BMI is 36 kg/m2. The abdomen is without masses or ascites. Pelvic examination shows a protruding soft, nontender mass at the level of the hymen that descends past the introitus with the Valsalva maneuver, which does not cause leakage of urine. The uterus and ovaries are surgically absent. Sensation and deep tendon reflexes are intact. Urinalysis is normal. Which of the following is the most likely cause of this patient's symptoms?
(Multiple Choice)
4.9/5 (72)
(72) A 17-year-old girl is admitted to the hospital due to heavy menses and a hemoglobin of 5.2 g/dL. On admission, the patient is started on intravenous (IV) estrogen and receives 1 unit of packed red blood cell transfusion. She is then started on a second unit of blood. Five minutes later, the patient becomes anxious and short of breath. Temperature is 38.6 C (101.5 F), blood pressure is 104/66 mm Hg, pulse is 120/min, and respirations are 30/min. Pulse oximetry shows 98% on room air. The patient appears pale. The oropharynx is clear, and lung examination reveals clear breath sounds bilaterally. There is pain at the IV insertion site, and skin examination shows no rashes. The patient's urine appears dark. The transfusion is stopped. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.7/5 (92)
(92) A 20-year-old woman comes to the office for a refill of oral contraceptives. She is in a monogamous relationship that began 6 months ago and uses condoms as back-up contraception. The patient became sexually active at age 14 and has had 5 lifetime partners. Her last menstrual period was 2 weeks ago. She has regular menses lasting 4-5 days every 28 days. The patient has not received the human papillomavirus (HPV) vaccination series and has never had a Pap test. Three months ago, she had negative screening for sexually transmitted infection. The patient has no chronic medical conditions and has had no prior surgery. She smokes cigarettes socially but does not use alcohol or illicit drugs. Vital signs are normal. Physical examination shows normal external genitalia without any lesions. Which of the following is recommended for this patient?
(Multiple Choice)
4.9/5 (72)
(72) A 26-year-old woman, gravida 2 para 2, comes to the emergency department due to increased vaginal bleeding and abdominal cramping. A week ago, the patient underwent a prolonged induction of labor for gestational diabetes mellitus that was complicated by an intraamniotic infection treated with intravenous antibiotics. She had a vaginal delivery of a 4.7-kg (10.4-lb) male infant and was discharged from the hospital on postpartum day 3. The patient was doing well until this morning, when she started to bleed through a sanitary pad every hour and began to have increasing abdominal cramping. Temperature is 36.7 C (98 F), blood pressure is 110/80 mm Hg, and pulse is 98/min. The uterus is firm, palpable at 6 cm above the pubic symphysis, and nontender to palpation. On speculum examination, there is active bleeding from the cervical os with passage of large clots. Which of the following is the most likely diagnosis for this patient?
(Multiple Choice)
5.0/5 (90)
(90) A 37-year-old woman, gravida 2 para 1, comes to the emergency department due to decreased fetal movement for the last 2 days. She has had no contractions, vaginal bleeding, or leakage of fluid. The patient had no issues with this pregnancy until a few weeks ago, when she began to develop generalized itching that is worse on her hands and feet. She has also had nausea for the past 3 days but no vomiting or diarrhea. The patient recently immigrated to the United States and has had no prenatal care. Temperature is 37 C (98.6 F) and blood pressure is 134/76 mm Hg. Fundal height is 38 cm. There is no scleral icterus. Cardiac and pulmonary examinations are normal. The right upper quadrant is tender to palpation, but there is no rebound or guarding. Bilateral lower extremities have 1+ pitting edema. Diffuse excoriations are noted on the skin. Laboratory results are as follows: 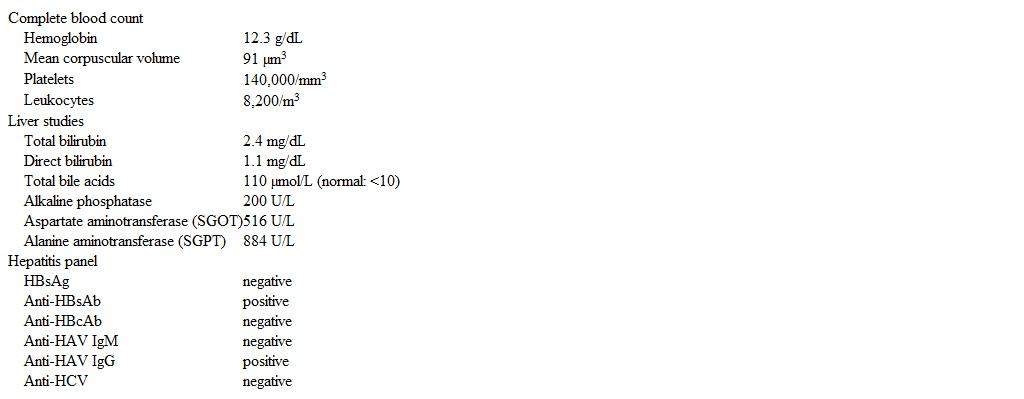 A transabdominal ultrasound reveals a 38-week intrauterine gestation with no fetal cardiac activity. Which of the following is the most likely cause of this patient's presentation?
 (Multiple Choice)
4.7/5 (73)
(73) A 29-year-old woman comes to the emergency department with chest pain and dyspnea for 10 days. The chest pain is bilateral, dull, persistent, and not worsened by exertion. The patient's medical history is significant for a normal spontaneous vaginal delivery 3 months ago, after which she has had frequent episodes of dark, bloody vaginal discharge. The most recent bleeding episode was 6 days ago. The patient has no fever, chills, hemoptysis, orthopnea, or leg pain. She does not use tobacco, alcohol, or illicit drugs. Temperature is 37.5 C (99.5 F), blood pressure is 110/68 mm Hg, pulse is 80/min, and respirations are 16/min. BMI is 26.2 kg/m2. Physical examination reveals bilaterally clear lungs. The extremities are warm and well perfused. There is no peripheral edema. Pelvic examination reveals an enlarged uterus, a closed cervix, and minimal dark blood in the vagina. Complete blood count and serum electrolytes are within normal limits. Chest x-rays reveal multiple bilateral infiltrates of various shapes. Which of the following would be most helpful in establishing this patient's diagnosis?
(Multiple Choice)
4.8/5 (65)
(65) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)