



 Chat with AI
Exam 5: Obstetrics & Gynecology

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 17-year-old girl, gravida 1 para 0, at 37 weeks gestation comes to the emergency department with headache, blurry vision, and fatigue. The patient has not had a prenatal visit for the past month due to final exams in school. She has no chronic medical conditions, and her only medication has been a daily prenatal vitamin. Blood pressure is 190/96 mm Hg and pulse is 106/min. Urinalysis shows 4+ protein. Physical examination shows increased ankle clonus but no neurologic deficits. Laboratory results are as follows:  The patient is admitted to labor and delivery for induction of labor and undergoes a spontaneous vaginal delivery of a male infant. Which of the following complications is most likely present in the neonate?
 (Multiple Choice)
4.9/5  (80)
(80) A 30-year-old woman, gravida 3 para 1 aborta 1, at 26 weeks gestation comes to the office for evaluation of increased vaginal discharge that started yesterday. She now changes her pad every hour and has noticed some spotting. Her initial prenatal visit was 2 weeks ago, and laboratory evaluation revealed a positive urine culture. The patient has not started her antibiotics because she has no symptoms. Her last delivery was 2 years ago via term cesarean delivery for recurrent late fetal decelerations. Vital signs are normal. The abdomen is soft, and the uterus is nontender. On speculum examination, there is pooling of clear, nitrazine-positive fluid in the vagina; the cervix is visibly closed. Fetal heart rate tracing shows a baseline of 150/min, accelerations, and no decelerations. There are irregular contractions on tocodynamometry. Transabdominal ultrasound shows an anterior placenta and an amniotic fluid index of 3 cm. Which of the following most likely contributed to this patient's presentation?
(Multiple Choice)
4.9/5 (82)
(82) A 29-year-old woman, gravida 2 para 1, comes to the office at 20 weeks gestation for a routine obstetric examination. The patient has felt normal fetal movement and has had no contractions, vaginal bleeding, or pelvic pain. She had diet-controlled gestational diabetes mellitus during her first pregnancy and underwent a cesarean delivery at 36 weeks gestation for preterm labor complicated by breech presentation. The patient has chronic hypertension, currently requiring 2 antihypertensive medications. She had a copper-releasing intrauterine device, placed after her first delivery, that was removed last year to try for pregnancy. The patient does not use tobacco, alcohol, or illicit drugs. Blood pressure is 144/96 mm Hg. BMI is 38 kg/m². Ultrasound shows a single cephalic fetus at the 40th percentile for growth. Cervical length is 4.4 cm and a posterior placenta extends over the cervix. Amniotic fluid index measures 18 cm. Which of the following is the greatest risk factor for this patient's ultrasound findings?
(Multiple Choice)
4.8/5 (84)
(84) A 28-year-old woman, gravida 1 para 0, at 37 weeks gestation comes to labor and delivery for induction of labor for severe polyhydramnios. The patient's 20-week anatomy ultrasound showed a male fetus with a tracheoesophageal fistula and a posterior fundal placenta. She developed increasingly severe polyhydramnios, with her most recent amniotic fluid index measuring 39 cm (normal: <24). The patient has been receiving an oxytocin infusion and is having painful contractions every 3 minutes with a category 1 fetal heart rate tracing. She has a sudden gush of copious clear amniotic fluid immediately followed by heavy vaginal bleeding and constant abdominal pain. Temperature is 36.7 C (98 F), blood pressure is 130/80 mm Hg, and pulse is 118/min. Fetal heart rate tracing shows a baseline of 120/min and minimal variability. Tocodynamometer shows contractions every minute. The uterus is smooth, gravid, and tender to palpation. The cervix is 5 cm dilated and 100% effaced with the fetal vertex at +1 station. Which of the following is the most likely cause of this patient's acute presentation?
(Multiple Choice)
4.8/5 (87)
(87) A 34-year-old woman, gravida 4 para 2 aborta 1, comes to the emergency department at 24 weeks gestation with vaginal bleeding that started after intercourse. The patient woke up in a pool of bright red blood and continues to soak through a pad every hour. She has not had routine prenatal care during this pregnancy but had a sonogram at 8 weeks gestation that showed a singleton intrauterine pregnancy. The patient has had 2 cesarean deliveries at term and a cervical conization earlier this year. She smokes a pack of cigarettes daily but does not use alcohol or illicit drugs. Blood pressure is 124/78 mm Hg and pulse is 92/min. Fetal monitoring shows a baseline of 140/min, accelerations, absent decelerations, and moderate variability. Irregular contractions are seen on tocodynamometry. Abdominal examination reveals a gravid, nontender uterus. On speculum examination, there are large clots in the vaginal vault, a closed cervix, and active bleeding from the os. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.7/5 (89)
(89) A 30-year-old woman, gravida 1 para 0, at 42 weeks gestation comes to the hospital with regular and painful uterine contractions. On admission, temperature is 36.1 C (97 F), blood pressure is 110/70 mm Hg, and pulse is 92/min. Estimated fetal weight is 3.8 kg (8.4 lb). Digital cervical examination shows the cervix to be 4 cm dilated and 100% effaced with the fetal vertex at 0 station. Fetal heart rate monitoring shows a baseline of 140/min, moderate variability, spontaneous accelerations, and no decelerations. An hour later, the patient is noted to have grossly ruptured membranes. Temperature is 37.2 C (99 F), blood pressure is 100/62 mm Hg, and pulse is 100/min. On repeat digital cervical examination, the cervix is 7 cm dilated and 100% effaced with the fetal vertex at +1 station. Fetal heart monitoring is shown in the exhibit. 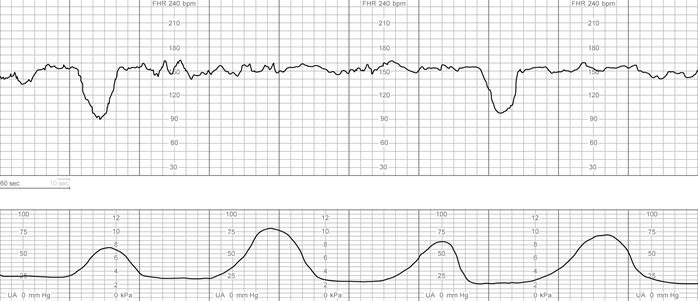 Which of the following is the most likely cause of this patient's fetal heart rate pattern?
 (Multiple Choice)
4.8/5 (80)
(80) A 24-year-old woman comes to the office due to intimacy issues with her husband. They have been married for a year and have been unable to have sexual intercourse. The husband has had erectile dysfunction for the past 3 months; he says that it is due to his wife experiencing dyspareunia and his fear of causing her more pain. They now attempt intercourse only once or twice a month due to lack of interest. The patient reports no dysuria, urinary frequency, vaginal pruritus, or pain in the perineum. She has no medical problems or previous surgeries. She has regular menses, lasting 4-5 days, with painful cramping on the first day. The patient has been unable to use tampons due to vaginal pain. She has had no previous sexual partners. The patient takes no medications and does not use tobacco, alcohol, or illicit drugs. Examination of the external genitalia shows no lesions and no pain on external touch. An internal pelvic examination is attempted but not completed due to the patient's intolerance. Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (83)
(83) During the patient's evaluation, her blood pressure increases to 170/115 mm Hg and pulse is 54/min. Fifteen minutes later, her blood pressure is 172/117 mm Hg and pulse is 53/min. The patient has a severe headache and an episode of emesis. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (63)
(63) A 39-year-old woman, gravida 1 para 0, at 38 weeks gestation comes to the hospital for induction of labor. The patient has a history of hypertension for which she takes nifedipine. She also has a history of asthma for which she takes albuterol as needed, but she has had no recent exacerbations. On admission, blood pressure is 140/80 mm Hg and pulse is 94/min. After a prolonged labor, the patient delivers a 4.1-kg (9-lb) boy via forceps-assisted vaginal delivery and develops a third-degree perineal laceration. During delivery of the placenta, excessive traction is placed on the cord, causing it to avulse, and the placenta is manually extracted. Ultrasound after the extraction reveals a thin endometrial stripe. The perineal laceration is repaired in layers. Sixty minutes after delivery, the patient's perineal pad becomes soaked with blood. On bimanual uterine examination, 1,000 mL of clotted blood is expressed from the lower uterine segment. The uterus is soft and 4 cm above the umbilicus after expression of the clots.
Which of the following is the most likely cause of this patient's bleeding?
(Multiple Choice)
4.7/5 (79)
(79) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)