



 Chat with AI
Exam 5: Obstetrics & Gynecology

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 24-year-old woman, gravida 2 para 1, comes to the office for a routine prenatal visit. The patient is at 37 weeks gestation based on her last menstrual period and first-trimester ultrasound. She has some irregular contractions but has had no vaginal bleeding or leakage of fluid. Fetal movement is normal. This pregnancy has been uncomplicated, and her last pregnancy ended with a term spontaneous vaginal delivery to a 4 kg (8 lb 8 oz) boy. The patient would like to have a vaginal delivery with this pregnancy. She has no chronic medical conditions and has had no previous surgeries. Vital signs are normal. Fetal heart tones are 135/min. Fundal height is 37 cm. Digital cervical examination reveals a closed cervix and an unengaged fetal presenting part. Ultrasonography shows a fundal placenta, a single deepest vertical pocket of amniotic fluid of 3 cm, and a fetus in incomplete breech presentation. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.7/5  (75)
(75) A 41-year-old woman comes to the office for evaluation of urinary incontinence. The patient has had intermittent leaking of urine for the past 2 years and now feels like she never empties her bladder completely. She voids every 1-2 hours and still finds her undergarments wet with urine. The patient has no dysuria, constipation, or pelvic pain. Her menses are every 26 days and last 6 days, with heavy bleeding and passage of clots on the first 2 days. She had 3 term vaginal deliveries in her 30s and has had a new sexual partner for the last 6 months. The patient drinks 2 cups of coffee daily and takes a thiazide diuretic for well-controlled chronic hypertension. She does not use tobacco, alcohol, or illicit drugs. Physical examination reveals an enlarged, anteverted, and anteflexed uterus with multiple irregular protrusions. The remainder of the pelvic examination is normal. Which of the following is the most likely cause of this patient's symptoms?
(Multiple Choice)
4.9/5 (68)
(68) A 58-year-old, postmenopausal woman comes to the office due to increasing vulvar pain. The pain was initially mild and intermittent when it began several months ago but has worsened over the past few weeks. In addition, the patient has now developed odorless, pink-tinged vaginal discharge with pruritus. She also has had a few painful oral lesions in the past several months that she treated with topical anesthetics with minimal improvement. Review of systems is otherwise negative. The patient is not sexually active. On examination, the gingivae have a lacelike, reticular appearance, and there are multiple white plaques on the tongue and palate. The vulva is diffusely erythematous, and the labia minora have multiple glazed, brightly erythematous erosions bordered by white striae. The vaginal introitus is stenotic, and a limited speculum examination reveals a friable, erythematous vaginal epithelium with a serosanguinous discharge. The remainder of the physical examination is normal. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (101)
(101) A 30-year-old woman is evaluated in labor and delivery for acute-onset dyspnea. An hour ago, the patient underwent an emergency cesarean delivery requiring intubation and general anesthesia for a category III fetal heart rate tracing due to placental abruption. The procedure was complicated by postpartum hemorrhage, and intraoperative transfusion of 2 units of packed red blood cells was required. The patient was extubated 15 minutes ago and now has significant shortness of breath and hypoxemia. Temperature is 38.3 C (101 F), blood pressure is 122/70 mm Hg, pulse is 114/min, and respirations are 24/min. Oxygen saturation is 84% on room air. Cardiac examination reveals no rubs or murmurs. Jugular venous pressure is normal. Pulmonary examination reveals bilateral crackles. The remainder of the examination is within normal limits. Chest x-ray shows infiltrates in the superior segments of the bilateral lower lobes. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.9/5 (81)
(81) A 60-year-old woman, gravida 3 para 3, comes to the office due to progressive bloating. The patient has noticed that she cannot fit into any of her pants despite recent nausea and a decreased appetite. She feels full quickly with meals and has increasing constipation. Menopause was at age 51, and she has had no postmenopausal bleeding or hormone replacement therapy. The patient has had no surgeries and all of her children were born via spontaneous vaginal delivery. Temperature is 36.7 C (98.1 F), blood pressure is 120/70 mm Hg, and pulse is 88/min. Cardiopulmonary examination is unremarkable. The abdomen is nontender and mildly distended. Bowel sounds are normal and there is no fluid wave. Pelvic examination reveals a firm, immobile mass in the left adnexa and rectovaginal nodularity. A pelvic ultrasound and CT scan of the abdomen and pelvis confirm the physical examination findings. CA-125 is 57 U/mL (normal: <35 U/mL). Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (67)
(67) A 30-year-old woman, gravida 3 para 2, at 37 weeks gestation comes to labor and delivery for regular, painful contractions. The contractions started an hour ago and are now 3-4 minutes apart. She has had no leakage of fluid or vaginal bleeding. Fetal movement has been normal. At her prenatal visit last week, examination showed a cephalic fetal presentation; group B Streptococcus rectovaginal culture was negative. Today, temperature is 36.7 C (98 F), blood pressure is 110/80 mm Hg, and pulse is 88/min. Fetal heart rate tracing shows moderate variability, multiple accelerations, and no decelerations. Tocodynamometer shows contractions every 3-4 minutes. The abdomen is nontender when contractions subside. On digital cervical examination, the cervix is 4 cm dilated, 90% effaced, and a taut, bulging bag is palpable with no presenting fetal part. Which of the following is the best next step in management of this patient?
(Multiple Choice)
5.0/5 (76)
(76) A 29-year-old woman, gravida 2 para 1, comes to the office at 10 weeks gestation for her first prenatal visit. The patient feels well and has had no vaginal bleeding or pelvic pain. Her first pregnancy ended in an uncomplicated vaginal delivery, but she required penicillin during labor for group B Streptococcus colonization. The patient has no chronic medical conditions and takes no daily medications. She does not use tobacco, alcohol, or illicit drugs. She has been in a monogamous relationship with her husband since they married 5 years ago. They live in a house built in 1983. Vital signs are normal. BMI is 24 kg/m². Uterine size is at 10 weeks gestation, and fetal heart tones are 162/min. The remainder of the physical examination is unremarkable. Which of the following screening tests is indicated at this visit?
(Multiple Choice)
4.9/5 (84)
(84) A 34-year-old woman comes to the office to discuss the progestin-releasing intrauterine device. The patient previously used condoms for contraception but is interested in starting a more reliable method. Her menses occur every 8 to 12 weeks, with heavy vaginal bleeding and passage of clots, and she has intermittent light spotting in between. The patient's last menstrual period was 1 week ago. She has no chronic medical conditions and takes no daily medications. The patient was treated for Trichomonas vaginitis at age 16. Her maternal grandmother had metastatic breast cancer in her 70s. Blood pressure is 118/64 mm Hg and pulse is 80/min. BMI is 44 kg/m². Pelvic examination shows a nulliparous cervix with scant physiologic discharge and a small, nontender uterus. Urine pregnancy test is negative. Which of the following is this patient's contraindication to a progestin-releasing intrauterine device?
(Multiple Choice)
4.8/5 (61)
(61) A 34-year-old woman, gravida 3 para 2, has a precipitous spontaneous vaginal delivery of a 4.2-kg (9 lb 5 oz) boy at 39 weeks gestation. After 15 minutes of gentle umbilical cord traction and fundal massage, the placenta is not delivered. Umbilical cord traction is continued; the umbilical cord abruptly avulses, and the patient suddenly develops severe abdominal pain. Blood pressure is 70/40 mm Hg and pulse is 62/min. On abdominal examination, the uterine fundus is not palpable at the umbilicus. There is copious vaginal bleeding with bright red blood and passage of large clots. On removal of the blood clots, a firm, rounded mass is visualized protruding from the vagina. Which of the following is the most likely cause of this patient's symptoms?
(Multiple Choice)
4.9/5 (88)
(88) A 19-year-old woman, gravida 1 para 0, comes to the emergency department for evaluation of right-sided abdominal pain and fever for the past 2 days. The pain has progressed over the last few hours and is now unbearable. The patient has had increasing fatigue, nausea, and anorexia but no vomiting or diarrhea. She has had some nonpainful contractions but no vaginal bleeding or discharge. The patient has had no prenatal care and is at 24 weeks gestation by date of her last sure, regular menstrual period. She has no chronic medical conditions and has had no prior surgeries. The patient does not use tobacco, alcohol, or illicit drugs. Temperature is 102.2 F (39 C), blood pressure is 116/70 mm Hg, and pulse is 120/min. There is tenderness over the right flank, but no abdominal rebound or guarding. The uterus is nontender. The cervix is closed, and amniotic membranes are intact. The fetal heart rate tracing is shown in the exhibit. 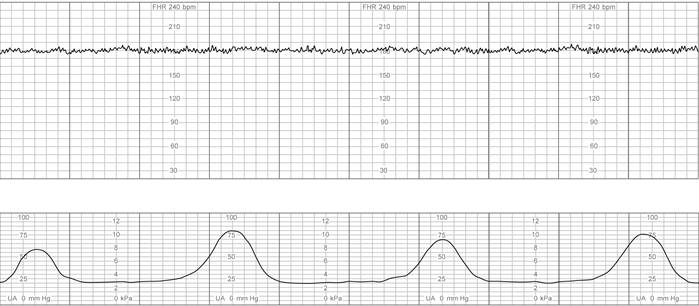 Which of the following is the most likely diagnosis for this patient?
 (Multiple Choice)
4.8/5 (76)
(76) A 24-year-old woman, gravida 2, para 1, at 37 weeks gestation comes to the office requesting induction of labor. The patient says that the last few weeks of pregnancy have been "very uncomfortable" due to exhaustion and shortness of breath when walking. She has bilateral leg swelling and is unable to fit into her shoes. The patient has difficulty sleeping at night due to bilateral crampy pain in her calves that is relieved by massage and stretching, and because the baby moves frequently at night. Review of systems is negative for contractions, vaginal bleeding, and loss of fluid. Temperature is 36.8 C (98.2 F), blood pressure is 110/70 mm Hg, pulse is 110/min, and respiratory rate is 18/min. Urinalysis shows trace protein. Physical examination shows symmetrical, bilateral pitting edema of the calves, ankles, and feet. Cardiac auscultation shows a 2/6 systolic ejection murmur. Her lungs are clear to auscultation. Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.9/5 (89)
(89) A 34-year-old woman, gravida 3 para 2, at 30 weeks gestation comes to the clinic for evaluation of an abdominal bulge. The patient first noticed this bulge 2 weeks ago when she was sitting up to get out of bed. She also sees the mass when she is straining to defecate or picking up her toddler. The patient has no nausea, vomiting, or abdominal pain, and her last bowel movement was 2 days ago. She has chronic constipation for which she takes a daily stool softener, and her prior surgeries include 2 cesarean deliveries. Temperature is 37.2 C (99 F), blood pressure is 124/76 mm Hg, and pulse is 92/min. Prepregnancy BMI is 19 kg/m2. When the patient sits up and performs the Valsalva maneuver, a nontender abdominal mass protrudes between the rectus abdominis muscles. When the patient is placed supine, no fascial defects are palpated. Bowel sounds are normoactive and there is no rebound or guarding. The uterus is nontender and the fundal height is 30 cm. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (84)
(84) A 34-year-old woman, gravida 5 para 4, at 39 weeks gestation is admitted to labor and delivery for contractions and spontaneous rupture of membranes. Her pregnancy has been uncomplicated, and her prior pregnancies ended in term vaginal deliveries. Prepregnancy BMI was 33 kg/m2 and she gained 18 kg (40 lb) this pregnancy. Two hours after admission, the patient receives neuraxial anesthesia and no longer feels contraction pain. After placement of neuraxial anesthesia, she has recurrent variable decelerations so an intrauterine catheter is placed. The variable decelerations resolve with amnioinfusion, and her labor continues. The patient's cervical examinations are shown on the labor curve below: 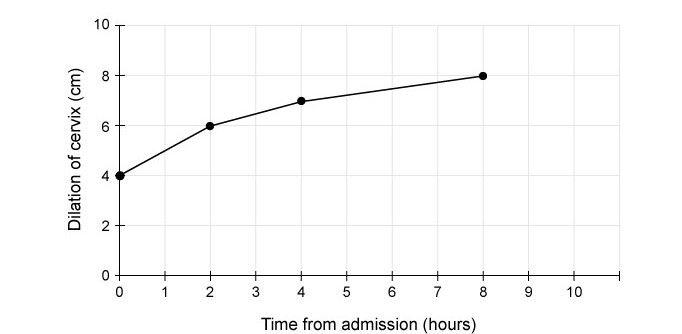 The fetal head is in the occiput posterior position. Fetal heart rate monitoring is category 1. An intrauterine pressure catheter shows 200 Montevideo units over 10 minutes for the past 4 hours. Which of the following is the most likely cause of this patient's labor curve?
 (Multiple Choice)
4.8/5 (81)
(81) A 40-year-old woman, gravida 3 para 2, at 33 weeks gestation comes to labor and delivery due to leakage of fluid. The patient has had intermittent leakage of clear vaginal fluid for the past few hours but no vaginal bleeding. She has had some irregular contractions for the past few weeks, but they are nonpainful. Fetal movement has been normal. The patient has type 2 diabetes mellitus and had polyhydramnios on her most recent fetal ultrasound. Temperature is 36.7 C (98 F), blood pressure is 120/70 mm Hg, and pulse is 70/min. BMI is 35 kg/m2. Fetal heart rate tracing shows a baseline of 140/min with moderate variability and multiple accelerations. Tocodynamometer reveals contractions every 15-18 minutes. The uterus is nontender. Speculum examination shows a closed cervix and clear fluid in the posterior fornix of the vagina. There is ferning on microscopy. A transabdominal ultrasound reveals a fetus in vertex presentation surrounded by minimal amniotic fluid; the deepest vertical pocket is 1 cm. Which of the following is the best next step in management of this patient?
(Multiple Choice)
5.0/5 (92)
(92) A 38-year-old woman, gravida 1 aborta 1, comes to the office for follow-up a week after suction curettage. The patient initially presented 7 weeks after her last menstrual period for an initial prenatal appointment. At that time, she had breast tenderness but no abdominal pain, nausea, or vaginal bleeding. During that visit, ultrasound revealed an empty gestational sac. β-hCG level was 53,256 IU/L. The patient returned a week later and repeat ultrasound confirmed a missed abortion. Suction curettage was performed and the pathological specimen from the procedure indicated a diagnosis of hydatidiform mole. Today, the patient has minimal bleeding but no pain, fevers, chills, or abnormal vaginal discharge. Blood pressure is 110/80 mm Hg and weight is 55 kg (121.3 lb). Pelvic examination shows minimal dark red blood in the vaginal vault and no active bleeding. On bimanual examination, the uterus is small and nontender. No adnexal masses are palpated. β-hCG level is 1,412 IU/L. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (80)
(80) A 28-year-old woman, gravida 1 para 0, comes to the office in November for her first prenatal visit. The patient has mild nausea and vomiting every morning but can tolerate food during the rest of the day. She has had no vaginal bleeding, abnormal discharge, or cramping. Her last menstrual period was 8 weeks ago. The patient has no medical conditions and takes only prenatal vitamins. She does not use tobacco, alcohol, or illicit drugs. Family history is significant for a father with type 2 diabetes mellitus who had a heart attack at age 55. The patient has had 2 lifetime sexual partners and has never had a sexually transmitted infection. Blood pressure is 118/78 mm Hg and pulse is 84/min. BMI is 23 kg/m2. Pelvic examination shows an 8-week anteverted uterus and a closed cervix. Transvaginal ultrasound reveals an 8-week intrauterine gestation with a normal fetal heartbeat. Which of the following is indicated at this visit?
(Multiple Choice)
4.8/5 (79)
(79) A 36-year-old nulligravida comes to the office for an infertility evaluation. Eight months ago, she was found to have a submucosal fibroid and underwent an uncomplicated hysteroscopic resection. The patient had light spotting for several days after surgery but no fever or abnormal vaginal discharge. Her last menstrual period was immediately prior to the procedure, but now she has monthly pelvic pain without bleeding. The patient has had regular, unprotected intercourse for the last 6 months without conception. She has no chronic medical conditions and has had no other surgeries. Vital signs are normal. The uterus is small, mobile, and nontender. Pregnancy test is negative. FSH, TSH, and prolactin levels are normal. Sexually transmitted infection screening is negative. A progesterone withdrawal test does not induce vaginal bleeding. Which of the following is the most likely cause of this patient's infertility?
(Multiple Choice)
4.9/5 (84)
(84) A 36-year-old woman, gravida 2 para 1, at 32 weeks gestation comes to the office with dull, low back pain radiating bilaterally to the buttocks and posterior thighs. The pain is minimal in the morning but increases with activity and at the end of the day. She also has ankle edema and numbness in her feet at the end of the day. The patient has urinary frequency and nocturia but no hematuria or dysuria. She had no back pain in her first pregnancy. During that delivery, the patient received epidural anesthesia and had a post-lumbar puncture headache after removal that was treated with an epidural blood patch. Temperature is 36.7 C (98.1 F), blood pressure is 120/80 mm Hg, and pulse is 90/min. She has gained 20 kg (44.1 lb) during this pregnancy. On physical examination, the patient ambulates with a wide, waddling gait. Walking forward or backward causes no change in pain level. There is no spinal or paravertebral tenderness. Deep tendon reflexes are 2+. The abdomen is soft, and the cervix is long, closed, and posterior. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (82)
(82) A 36-year-old woman, gravida 3 para 2, at 38 weeks gestation comes to the emergency department due to regular, painful contractions. The contractions began an hour ago, immediately after the patient had a "gush" of fluid. She has had no vaginal bleeding, and fetal movement has been normal. The patient's last prenatal visit was 6 weeks ago. She has no known medical conditions and does not use alcohol, tobacco, or illicit drugs. Vital signs are normal. Fetal heart rate tracing shows a baseline of 140/min with multiple accelerations and no decelerations. Contractions occur every 2 minutes on tocodynamometer. Pelvic examination shows a cluster of clear vesicles with an erythematous base on the right labium minus. Speculum examination shows a pool of clear fluid in the posterior vagina. The cervix is 6 cm dilated and 100% effaced with the fetal head at 0 station. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (71)
(71) A 38-year-old woman comes to the office due to breast pain. For the past 2 months, the patient has had intermittent bilateral breast pain that usually begins the week prior to menses and subsides on the first day of her menstrual cycle. The pain is primarily in the bilateral upper outer quadrants and does not radiate to the back or neck. Six months ago, the patient started a new job that requires long hours of sedentary work; she has gained 4.5 kg (10 lb). She has no chronic medical conditions and takes no daily medications. The patient has regular monthly menses, and her last menstrual period was a week ago. BMI is 26 kg/m2. Vital signs are normal. Breast examination shows bilateral, symmetric, large breasts with slight tenderness over the upper outer quadrants. There are no skin changes, nipple discharge, masses, or axillary lymphadenopathy. Which of the following is the best next step in management of this patient?
(Multiple Choice)
5.0/5 (79)
(79) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)