



 Chat with AI
Exam 5: Obstetrics & Gynecology

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 29-year-old primigravida at 30 weeks gestation comes to the office accompanied by her husband. She is concerned that she has not felt the baby move or kick for the past day. The pregnancy was planned, and her prenatal tests and fetal growth have been normal. The patient has no chronic medical conditions and takes a prenatal vitamin daily. On ultrasound, no fetal heartbeat is detected. The physician informs the parents about the loss of the fetus. They appear to be in shock, and the patient cries, "I can't believe this is happening. I was following all the recommendations, and I only missed one appointment. I should have come in sooner." Which of the following is the most appropriate response by the physician?
(Multiple Choice)
4.9/5  (76)
(76) A 57-year-old postmenopausal woman comes to the office due to vaginal spotting and increasing pelvic pressure. For the past few months, the patient has had pelvic pressure with some associated constipation, for which she takes fiber supplements with no relief. For the last week, she has also had vaginal spotting and occasional passage of small blood clots. The patient was diagnosed with breast cancer 3 years ago and has been taking tamoxifen for the past 2 years because she could not tolerate the adverse effects of aromatase inhibitors. She has no other chronic medical conditions, and her only surgeries were 3 cesarean deliveries in her 30s. Vital signs are normal. BMI is 23 kg/m2. A large, irregular mass is palpable above the symphysis pubis, but there is no fluid wave or tenderness to palpation. On pelvic examination, there are no cervical or vaginal lesions; a small amount of blood is seen at the cervical os. The uterus appears well supported and does not descend with the Valsalva maneuver. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.9/5 (72)
(72) A 26-year-old woman comes to the office for infertility evaluation with her husband, age 30. They have been unable to conceive after 12 months of unprotected intercourse. The patient's menstrual periods are regular, occurring every 26 days with painful cramps the first day that are relieved with ibuprofen. Her last period began 6 days ago. She had 3 previous sexual partners without pregnancy. Both the patient and her husband report normal puberty, and neither have had any medical conditions or previous surgeries. The patient takes a daily prenatal vitamin. She is 155 cm (5 ft 1 in) tall and weighs 55 kg (121.3 lb). BMI is 23 kg/m2. Blood pressure is 120/70 mm Hg and pulse is 70/min. Physical examination of the patient shows Tanner stage 5 breast development. Pelvic examination reveals a normal cervix; mobile, retroverted, nontender uterus; and no adnexal masses. Physical examination of the husband shows normal secondary sexual characteristics and bilaterally descended testes. Urine pregnancy test is negative. Which of the following is the best next step in evaluation of this couple's infertility?
(Multiple Choice)
4.8/5 (84)
(84) A 16-year-old girl comes to the office for a routine health maintenance examination. The patient is in high school, is performing well academically, and plays on the tennis team. She has no concerns today. On review of systems, the patient has not reached menarche, but she says that her mother did not start menstruating until this age. She recently started wearing contact lenses for myopia and uses an over-the-counter cream for acne. Height is at the 70th percentile and weight is at the 25th percentile for age. Blood pressure is 120/70 mm Hg and pulse is 60/min. Breast development is sexual maturity rating (Tanner stage) III. Pelvic examination shows sexual maturity rating (Tanner stage) III pubic hair development and normal external genitalia. Speculum examination reveals a well-rugated vagina but no cervix. FSH levels are within the normal pubertal range. Karyotype is 46, XX. Pelvic ultrasound reveals an absent uterus. Which of the following is the best next step in management of this patient?
(Multiple Choice)
5.0/5 (78)
(78) A 58-year-old woman, gravida 1 para 1, comes to the office for a health maintenance examination. She feels well and has no issues today. However, the patient states she would like screening for ovarian cancer because her cousin died of the disease last year and a close friend was recently diagnosed with advanced-stage ovarian cancer. She has well-controlled hypertension. During her 20s, the patient took combined oral contraceptives until she had a tubal ligation at age 30. Menopause occurred at age 56, and she took hormone replacement therapy for 2 years. The patient smokes half a pack of cigarettes a day and drinks alcohol occasionally. There is no other history of cancer in the family. Which of the following is the most appropriate strategy for ovarian cancer screening in this patient?
(Multiple Choice)
4.9/5 (80)
(80) A 48-year-old woman is undergoing evaluation of right nipple discharge that was first noticed last week during a clinical breast examination. The patient has schizophrenia, which was diagnosed in her 20s and is well controlled with antipsychotic therapy. She also takes acetaminophen intermittently for headaches. The patient plays tennis and goes to kickboxing classes regularly. She does not use tobacco, alcohol, or illicit drugs. Family history is significant for a paternal aunt who died from metastatic breast cancer at age 50. BMI is 28 kg/m². Vital signs are normal. On physical examination, scant reddish-brown fluid is expressed from the right breast. There are no breast masses and no supraclavicular or axillary lymphadenopathy. Which of the following is the most likely cause of this patient's findings?
(Multiple Choice)
5.0/5 (95)
(95) A 34-year-old woman, gravida 2 para 1, at 26 weeks gestation comes to the emergency department due to intermittent leakage of fluid for the past 6 hours. She has had no vaginal bleeding or contractions. The patient's previous pregnancy was complicated by preterm prelabor rupture of membranes at 29 weeks gestation; she delivered at 34 weeks gestation after inpatient management with corticosteroids and latency antibiotics. Temperature is 39.4 C (103 F), blood pressure is 100/70 mm Hg, and pulse is 114/min. Fetal heart rate is 170/min. The uterus is tender to palpation. On speculum examination, purulent amniotic fluid emerges from the cervix with Valsalva and turns the nitrazine paper blue. The cervix is visibly closed. Transabdominal ultrasound shows a vertex fetus consistent with gestational age. The amniotic fluid index is 8 cm. In addition to antibiotics, which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (83)
(83) A 22-year-old woman comes to the emergency department due to abdominal pain. The patient has had intermittent abdominal pain for the past 2 days, but today the pain has worsened and become constant. She has had no nausea, vomiting, or change in bowel or bladder patterns. The patient's medical history is significant for sickle cell disease, for which she is prescribed hydrocodone as needed; she began taking multiple hydrocodone tablets today when the pain got worse but had only minimal relief. Her last menstrual period was 4 months ago, and she has multiple sexual partners. Temperature is 37.1 C (98.8 F), blood pressure is 132/88 mm Hg, and pulse is 90/min. The abdomen is diffusely tender to deep palpation; there is no rebound or guarding. On pelvic examination, the uterus is enlarged and nontender and the cervix is closed. The remainder of the examination is unremarkable. Pelvic ultrasound reveals an intrauterine pregnancy at 12 weeks gestation with a fetal heart rate of 160/min. Bilateral adnexa have normal Doppler blood flow. Which of the following is the most likely cause of this patient's presentation?
(Multiple Choice)
4.9/5 (74)
(74) A 17-year-old nulligravid girl comes to the office due to 2 months of colicky left lower quadrant pain. The pain worsens with intercourse and exercise but resolves spontaneously. She has had no diarrhea, constipation, or urinary symptoms. Her last menstrual period was 3 weeks ago. Menses occur monthly and last 5-6 days with 2 days of heavy bleeding. The patient is sexually active with a new partner and uses condoms for contraception. She has no chronic medical conditions and has had no surgeries. She does not use tobacco, alcohol, or illicit drugs. Her older sister recently had in vitro fertilization due to infertility from endometriosis. Vital signs are normal. Pelvic examination shows a tender left adnexal mass and small, mobile uterus. Urine pregnancy test is negative. Neisseria gonorrhoeae and Chlamydia trachomatis testing is negative. Ultrasonography reveals an 8-cm left ovarian cyst with calcifications and hyperechoic nodules. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (77)
(77) A 26-year-old woman, gravida 2 para 1, at 35 weeks gestation comes to the labor and delivery department due to regular, painful contractions over the past 3 hours. The patient has had no prenatal care during this pregnancy. She has no chronic medical conditions, and her only surgery was a low transverse cesarean delivery 2 years ago. Her cervix on admission is 7 cm dilated and 100% effaced with the fetal head at +2 station. Fetal heart rate tracing on admission is category 1. Epidural analgesia is administered, and the patient has pain relief from the contractions. Rupture of membranes results in bright-red amniotic fluid. Blood pressure is 130/80 mm Hg and pulse is 112/min. Current fetal monitoring is as seen in the exhibit. 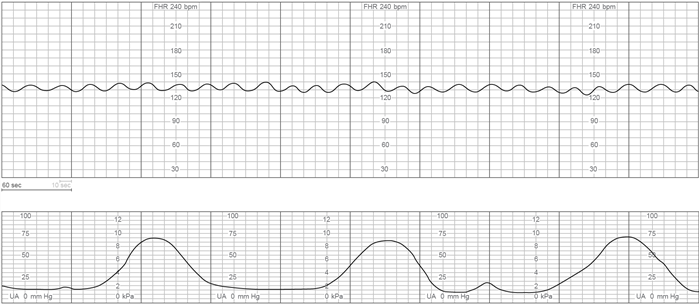 Which of the following is the most likely cause of this fetal heart rate tracing?
 (Multiple Choice)
4.9/5 (73)
(73) A 24-year-old primigravida with a twin pregnancy at 30 weeks gestation comes to the emergency department due to severe epigastric and right upper quadrant pain. The patient first developed the pain yesterday morning after eating breakfast. She took acetaminophen and an antacid but had no relief. She now has severe stabbing pain, has vomited 7 times today, and continues to have nausea. The patient has no chronic medical conditions or previous surgeries. Temperature is 37.2 C (99 F), blood pressure is 136/86 mm Hg, and pulse is 108/min. BMI is 23 kg/m2. Fetal heart rate monitoring shows 2 fetal heart rates with baselines of 160/min and moderate variability. The patient appears pale and has scleral icterus. The abdomen has tenderness to palpation over the right upper quadrant and epigastric region, but no rebound. The uterus is nontender and has no palpable contractions.  Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (93)
(93) A 29-year-old woman, gravida 1 para 1, comes to the office for a routine postpartum visit. Six weeks ago, she delivered a 4.2-kg (9 lb 5 oz) girl by cesarean delivery for cephalopelvic disproportion. The pregnancy was complicated by gestational diabetes mellitus, which was controlled with diet and exercise, and preeclampsia without severe features. Since the delivery, the patient has been feeling well but continues to have daily light vaginal bleeding of dark red or brown blood. She is breastfeeding exclusively and is not on contraception. She has no chronic medical conditions and has had no other surgeries. Her last Pap test 2 years ago was normal. Blood pressure is 122/78 mm Hg and pulse is 87/min. BMI is 30 kg/m2. The lower abdominal incision is well healed. On speculum examination, there is a small amount of scant brown discharge in the vaginal vault and no cervical lesions. The remainder of the physical examination is normal. Which of the following is the best next step in management of this patient?
(Multiple Choice)
5.0/5 (87)
(87) A 49-year-old woman, gravida 5 para 5, comes to the office due to involuntary, intermittent loss of urine over the past 5 months. The patient is an avid jogger and now must wear absorbent pads while jogging. She has no dysuria, urgency, or hematuria and usually awakens once a night to void. Three years ago, the patient was diagnosed with type 2 diabetes mellitus, which is treated with metformin. She does not use tobacco, alcohol, or illicit drugs. Vital signs are normal. BMI is 31 kg/m2. Pelvic examination shows normal external genitalia, a well-rugated vagina, and an anterior vaginal bulge. The patient loses a small amount of urine when asked to cough. Postvoid residual urine volume is 40 mL. Clean-catch urinalysis results are as follows:  Serum hemoglobin A1c is 7.7%. Which of the following is the most likely cause of this patient's symptoms?
 (Multiple Choice)
4.9/5 (79)
(79) A 35-year-old woman, gravida 2 para 1, at 31 weeks gestation comes to the office with severe heartburn and right upper quadrant pain. She has experienced several episodes of nausea and vomiting this morning. The patient has had gastroesophageal reflux disease throughout the pregnancy, but the symptoms have rapidly become much worse. During her visit last week, she was fatigued, and her blood pressure was 130/80 mm Hg. Current blood pressure is 160/90 mm Hg and pulse is 86/min. BMI is 42 kg/m2. Physical examination shows extreme tenderness to palpation in the midline and right upper quadrant of the abdomen but absence of peritoneal signs. Fetal heart tones are 130/min using Doppler ultrasound. Laboratory results are as follows:
 Urine dipstick shows 2+ protein. Which of the following is the most likely cause of this patient's upper abdominal pain?
 (Multiple Choice)
4.9/5 (88)
(88) A 25-year-old woman, gravida 1 para 1, comes to the office due to malodorous vaginal discharge for the past 2 weeks. She tried over-the-counter topical vaginal cleansers with no improvement of her symptoms. Four weeks ago, the patient had a forceps-assisted vaginal delivery complicated by a third-degree laceration, which was repaired with absorbable suture. After delivery, vaginal packing was placed for 24 hours to tamponade the traumatized vaginal tissue. Her lochia stopped a week ago, and she has had no additional bleeding. Vitals signs are normal. On pelvic examination, the perineum is intact, and there is a small, dark red, velvety area on the posterior vaginal wall with an associated malodorous, tan-brown discharge. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.9/5 (75)
(75) A 32-year-old primigravida woman at 24 weeks gestation comes to the office due to a change in bowel habits. For the past 4 weeks, the patient has had 3 or 4 loose, bloody stools per day and intermittent lower abdominal pain. On occasion, she experiences urgency to use the bathroom, but when she sits down on the toilet, she strains and produces very little stool. Two years ago, the patient had intermittent bloody stools that resolved without medication. Her pregnancy has been otherwise uncomplicated. Family history is noncontributory. She does not use tobacco, alcohol, or illicit drugs. At 20 weeks gestation, fetal ultrasound revealed a fetus at the 12th percentile for gestational age. Temperature is 37.5 C (99.5 F), blood pressure is 123/86 mm Hg, pulse is 98/min, and respirations are 16/min. The patient appears well and is in no apparent distress. There is no scleral icterus or conjunctival pallor. Cardiopulmonary examination is unremarkable. On abdominal examination, the uterus is at the umbilicus and fetal heart tones are 160/min; there is mild diffuse abdominal tenderness to palpation with no rebound or guarding. Which of the following is the most likely diagnosis for this patient?
(Multiple Choice)
4.8/5 (71)
(71) A 48-year-old woman comes to the clinic due to dyspareunia, which has worsened over the last 4 months. Five years ago, the patient underwent radiation and chemotherapy for stage II cervical cancer. She has not been sexually active for several years due to fear of cervical cancer recurrence. Now the patient has a new partner and is using over-the-counter lubricants during intercourse but still experiences pain with penetration. She has had no postcoital bleeding, dysuria, or abnormal vaginal discharge. The patient has a 20-pack-year smoking history. She has not had a menstrual period since completing radiation therapy. Vital signs are normal. Examination shows thin vulvar skin with shrinkage of clitoral tissue. The vaginal introitus is narrow, and the vaginal mucosa appears pale. The cervix appears scarred consistent with postradiation changes but has no raised, nodular, or friable lesions. Which of the following is the most likely cause of this patient's condition?
(Multiple Choice)
4.9/5 (97)
(97) A 29-year-old woman, gravida 1 para 0, at 36 weeks gestation comes to the office for a routine prenatal visit. The patient has noticed less fetal movement than normal. She has had no vaginal bleeding, contraction pain, or leakage of fluid. The patient has no chronic medical conditions and takes a daily prenatal vitamin. She previously smoked a pack of cigarettes daily but decreased to a quarter pack daily after becoming pregnant. Her prenatal course has been uncomplicated; a first-trimester ultrasound showed a viable intrauterine pregnancy and multiple intramural and submucosal leiomyomas. Vital signs are normal. Fundal height is 38 cm. A nonstress test is reactive. Ultrasound shows a fetus in frank breech presentation with an estimated fetal weight at the 80th percentile for gestational age, a fundal placenta, and an amniotic fluid index of 15 cm. Which of the following is the most likely cause of this patient's fetal presentation?
(Multiple Choice)
4.9/5 (70)
(70) In addition to broad-spectrum antibiotics, which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (77)
(77) Six weeks after a spontaneous, uncomplicated term vaginal delivery, a 32-year-old woman, gravida 1 para 1, comes to the emergency department due to left breast pain. The patient first noticed pain and redness on her left breast a week ago. She has continued to breast feed her infant from the unaffected breast. The patient has no chronic medical conditions and her only medication is a daily multivitamin. Temperature is 38.3 C (101 F). Physical examination shows an area of erythema extending from the areola to the lateral edge of the left breast and surrounding a well-circumscribed, 4-cm area of fluctuance. Axillary lymphadenopathy is present. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (72)
(72) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)