



 Chat with AI
Exam 5: Obstetrics & Gynecology

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 29-year-old woman comes to the clinic for evaluation of leakage of urine. For the past week, the patient has had to urinate every hour and has had leakage of urine while trying to run to the bathroom. She has had no hematuria, dysuria, or flank pain. The patient has no chronic medical conditions and has had no surgeries. She has had 2 vaginal deliveries without complications. The patient drinks multiple cups of coffee and diet soda daily. Temperature is 99 F (37.2 C), blood pressure is 122/76 mm Hg, and pulse is 84/min. BMI is 29 kg/m². On speculum examination, the bladder has no descent, but the patient leaks urine with Valsalva maneuver. Urine dipstick shows:  Pregnancy test is negative. Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5  (94)
(94) A 26-year-old primigravid woman at 14 weeks gestation comes to the office to establish prenatal care. The patient has had no vaginal bleeding or cramping. She has no chronic medical conditions, and her only medication is a daily prenatal vitamin. The patient follows a vegan diet and drinks 2 cups of coffee each morning. She is an avid runner and runs 5 miles most days. The patient does not use tobacco, alcohol, or illicit drugs. Vital signs are normal. Prepregnancy BMI was 22 kg/m2. Physical examination is normal. Transvaginal ultrasound shows a single intrauterine gestation with a heart rate of 155/min. The patient asks about possible lifestyle modifications needed during pregnancy. Which of the following is the most appropriate recommendation for this patient?
(Multiple Choice)
4.8/5 (80)
(80) A 27-year-old woman, gravida 1 para 1, comes to the office for evaluation of postpartum bleeding. Four days ago, the patient had a forceps-assisted vaginal delivery due to recurrent fetal decelerations. She had a third-degree perineal laceration that was repaired, and she went home on the second postpartum day. Since delivery, the patient has had continuous, dark red vaginal bleeding with small clots, requiring her to change a menstrual pad 6 to 7 times daily. She has no chest pain, shortness of breath, or orthostasis. Temperature is 99.5 F (37.5 C), blood pressure is 124/76 mm Hg, and pulse is 88/min. BMI is 33 kg/m2. The uterine fundus is firm, nontender, and palpable at 4 cm below the umbilicus. The perineal laceration repair is intact, and the cervix is 1 cm dilated with minimal dark red blood in the vagina. Laboratory results are as follows:  Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (83)
(83) A 25-year-old woman, gravida 1 para 0, at 24 weeks gestation comes to labor and delivery due to decreased fetal movement. The patient has felt decreased fetal movement for the past day and no fetal movement in the past hour. She has had no contractions, vaginal bleeding, or leakage of fluid. Last week, the patient went to a picnic and the next day she had nausea, watery diarrhea, and muscle aches, but no rashes or joint pain. Her symptoms resolved after 24 hours. She has no chronic medical conditions and takes no daily medications. Temperature is 98.9 F (37.2 C), blood pressure is 118/68 mm Hg, and pulse is 90/min. Cardiopulmonary examination is normal. There is no flank pain and the uterus is nontender. On pelvic examination, the cervix is closed, and membranes are intact. No fetal heart tones are detected on Doppler, and a transabdominal ultrasound confirms an intrauterine fetal demise. Which of the following pathogens is the most likely cause of this patient's presentation?
(Multiple Choice)
4.7/5 (92)
(92) A 51-year-old woman comes to the office for a routine health maintenance examination. She has no concerns today. The patient recently had a normal screening mammogram. She has type 1 diabetes mellitus and her last hemoglobin A1c level was 7.6%. The patient had an abnormal Pap test at age 35 that required cervical conization, but all subsequent Pap tests have been normal. She is currently sexually active and has had no pain with intercourse. Her last menstrual period was 2 weeks ago. The patient does not use tobacco, alcohol, or illicit drugs. Vital signs are normal. BMI is 26 kg/m2. Pelvic examination is shown below. 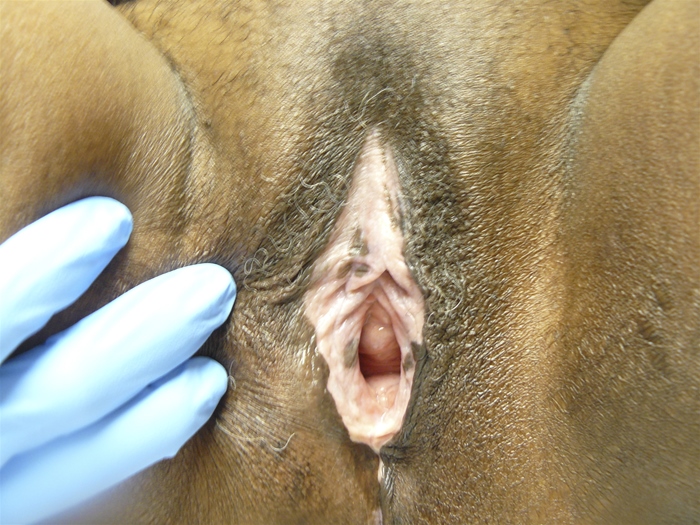 Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.8/5 (83)
(83) A 34-year-old woman comes to the labor and delivery unit via ambulance for contractions, rupture of membranes, and vaginal bleeding. The patient had rupture of membranes 4 hours ago, and her contractions have increased in intensity and frequency over the last hour, which required multiple doses of morphine in the ambulance. On arrival, temperature is 37.2 C (99 F), blood pressure is 130/80 mm Hg, and pulse is 94/min. On pelvic examination, the membranes are grossly ruptured with clear fluid, and there is scant, dark blood on the perineum. The cervix is 6 cm dilated and 80% effaced, and fetal position is occiput posterior. Fetal heart rate tracing is shown in the exhibit.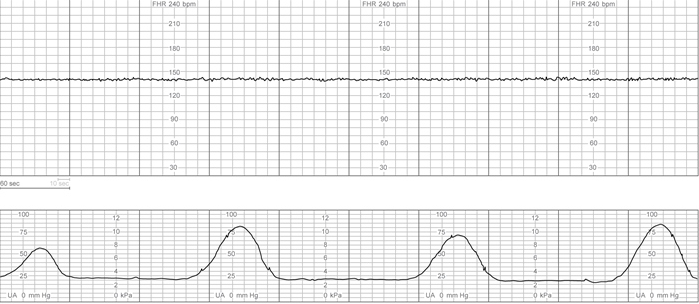 Which of the following is the most likely cause of this fetal heart rate tracing?
 (Multiple Choice)
5.0/5 (90)
(90) A 33-year-old woman, gravida 7 para 6, at 39 weeks gestation undergoes induction of labor for new-onset hypertension. The patient became pregnant 5 months after her most recent delivery; otherwise, this pregnancy had been uncomplicated. Her previous pregnancies ended in uncomplicated term vaginal deliveries. She has a history of several lower uterine segment fibroids. Blood pressure is 160/96 mm Hg. Prepregnancy weight was 115 kg (253.5 lb) and the patient gained 13.6 kg (30 lb) during the pregnancy. Fundal height is 43 cm. Twenty-two hours after labor induction and after 2 hours of pushing, the fetal head delivers and retracts into the maternal perineum. Gentle traction fails to deliver the anterior fetal shoulder. Which of the following is the greatest risk factor for this patient's clinical presentation?
(Multiple Choice)
4.9/5 (89)
(89) A 32-year-old woman, gravida 2 para 0 aborta 1, at 29 weeks gestation comes to the office for a prenatal visit. She has had no vaginal bleeding or contractions. Fetal movement is normal. The pregnancy is dated by an 8-week ultrasound because the patient was unsure of her last menstrual period. Ultrasound at that time showed a 2-cm, pedunculated fibroid at the fundus but was otherwise normal. Repeat ultrasound at 20 weeks gestation showed no fetal abnormalities; the fibroid again measured 2 cm. The patient has no chronic medical conditions. Laboratory results at 28 weeks gestation are as follows:  Vital signs at today's visit are normal. Fundal height is 35 cm. Fetal heart tones are 155/min. Which of the following is the most likely underlying cause of this patient's uterine size-dates discrepancy?
 (Multiple Choice)
4.8/5 (88)
(88) A 39-year-old woman, gravida 1 para 0, at 34 weeks gestation comes to the office for a routine prenatal visit. She has good fetal movement and some lower abdominal pressure. Other than a cough and nasal congestion during the first trimester, the patient has had an uneventful pregnancy. Her first trimester screening and fetal anatomy ultrasound were both normal. She was diagnosed with hypertension 5 years ago for which she takes labetalol. The patient drinks 2 cups of coffee daily but does not use tobacco, alcohol, or illicit drugs. She is a nurse in the neonatal intensive care unit and plans to work until her due date. Blood pressure is 142/82 mm Hg and fundal height is 30 cm. Ultrasound reveals a biparietal diameter consistent with 32 weeks and abdominal circumference consistent with 27 weeks gestation. A normal amount of amniotic fluid and a posterior placenta are present. Estimated fetal weight is at the 8th percentile for gestational age. Which of the following is the most likely cause of this fetus' condition?
(Multiple Choice)
4.9/5 (92)
(92) A 25-year-old woman, gravida 1 para 1, comes to the office for evaluation of amenorrhea. Twelve weeks ago, the patient vaginally delivered a healthy girl. The delivery was complicated by a retained placenta and postpartum hemorrhage that required manual extraction of the placenta and a blood transfusion. The patient is concerned as she has had no menstrual period since the delivery. She is breastfeeding exclusively and has not resumed sexual intercourse. She has no pelvic pain or vaginal discharge. Blood pressure is 100/70 mm Hg and pulse is 60/min. Examination shows a small uterus with no cervical motion tenderness and no blood in the vaginal vault. Which of the following is the most likely mechanism for this patient's amenorrhea?
(Multiple Choice)
4.8/5 (77)
(77) A 24-year-old woman comes to the office for evaluation of abnormal vaginal bleeding. The patient has a history of heavy, regular menstrual periods for which a progestin-releasing intrauterine device (IUD) was placed 2 years ago. After IUD insertion, the patient became amenorrheic. However, for the last month, she has had light vaginal spotting with wiping. The patient also recently developed intermittent pelvic pain that has now become constant and unrelieved with ibuprofen. She has no chronic medical conditions and does not use tobacco, alcohol, or illicit drugs. Family history is unremarkable. On bimanual pelvic examination, there is uterine and bilateral adnexal tenderness. The IUD strings are palpable at the cervix. Urine pregnancy test is negative. Which of the following is the most likely cause of this patient's symptoms?
(Multiple Choice)
4.9/5 (92)
(92) A 39-year-old woman, gravida 2 para 2, comes to the office for evaluation of increasing malaise. The patient has been exclusively breastfeeding her 3-month-old infant. For the past week, she has been taking dicloxacillin due to redness and pain in her right breast. Over the past few days, the patient has developed increasing malaise and a low appetite. She has had no nausea, diarrhea, or headache. The patient has no chronic medical conditions and takes no other daily medications. Her mother had breast cancer at age 54. Temperature is 37.7 C (99.9 F), blood pressure is 124/68 mm Hg, and pulse is 98/min. Both breasts have moderate engorgement. There is linear nipple cracking bilaterally. The right breast has tender nodularity, but the erythema has improved since last week's examination. The remainder of the physical examination is unremarkable. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (82)
(82) A 22-year-old nulligravid woman comes to the office for her first gynecologic examination and to discuss contraception options. Menarche was at age 13. Her last menses was 2 weeks ago; periods occur every 30 days and last for 4 days. The patient has no dysuria, urinary frequency, vaginal discharge, postcoital spotting, or abdominal pain. She became sexually active a few months ago with her boyfriend; she is monogamous and currently uses condoms for contraception. The patient takes no medications and has no allergies. She does not use tobacco, alcohol, or illicit drugs. The patient has received all recommended vaccinations except for the human papillomavirus series. Her mother was diagnosed with ovarian cancer at age 46 and is currently undergoing chemotherapy. Vital signs are normal. Complete physical examination, including pelvic examination, shows no abnormalities. A urine pregnancy test is negative. In addition to her first Pap test, which of the following is the best recommendation for this patient?
(Multiple Choice)
4.8/5 (74)
(74) A 32-year-old woman, gravida 1 para 1, is evaluated on postoperative day 1 for difficulty walking. Yesterday, the patient underwent a prolonged induction of labor for poorly controlled gestational diabetes mellitus and suspected fetal macrosomia at 39 weeks gestation. Epidural analgesia was placed during labor, and she required multiple epidural boluses and epidural replacement for adequate pain control. The patient pushed for 3 hours with minimal fetal descent, and a forceps-assisted delivery was attempted but failed. She then underwent a cesarean delivery via Pfannenstiel incision. Today, while attempting to walk to the bathroom, the patient almost fell and has been unable to ambulate without assistance. On examination, the Pfannenstiel incision is intact and mildly tender. The right patellar reflex is 2+ and the left 1+. Sensation is diminished on the left anterior and medial thigh, and there is weakness on knee extension. The remainder of the examination is normal. Which of the following is the most likely cause of this patient's presentation?
(Multiple Choice)
5.0/5 (76)
(76) A 40-year-old woman, gravida 2 para 1, comes to the office for her initial prenatal visit. She is at 10 weeks gestation based on her last menstrual period. The patient has no concerns today and feels well. She had light vaginal bleeding 6 weeks ago, but none since then. Her first pregnancy ended in a term vaginal delivery. The patient has no chronic medical conditions or prior surgeries and takes no daily medications. She does not use tobacco, alcohol, or illicit drugs. Blood pressure is 118/64 mm Hg and pulse is 82/min. BMI is 22 kg/m². Physical examination is unremarkable. Ultrasound reveals an intrauterine fetal pole at 10 weeks gestation with fetal heart rate at 160/min. In addition to routine prenatal laboratory testing, which of the following tests is recommended for this patient?
(Multiple Choice)
4.9/5 (85)
(85) A 28-year-old woman comes to the office after a positive home pregnancy test. The patient is at 5 weeks gestation by a sure, regular last menstrual period. She has had some breast tenderness but no dysuria, vaginal bleeding, or cramping. The patient has no chronic medical conditions or prior surgeries. This is her first pregnancy, and she has no history of sexually transmitted infections. Vital signs and physical examination are unremarkable. Transvaginal ultrasound shows a slightly thickened endometrial stripe but no intrauterine gestation or adnexal masses. Quantitative β-hCG is 1,100 mIU/mL and a repeat 48 hours later is 1,370 mIU/mL. The patient undergoes a diagnostic uterine dilation and curettage, and the next day β-hCG level is 1,566 mIU/mL. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (76)
(76) An 18-year-old woman comes to the office after fracturing her distal radius when she fell off a chair. The patient had ambiguous external genitalia noted at birth, and laparotomy performed at 17 months of age revealed a normal uterus and fallopian tubes. Ovarian biopsy performed at that time revealed normal-appearing primordial follicles. She has never had a menstrual cycle. Blood pressure is 120/78 mm Hg and height is 160 cm (5 ft 3 in). The patient has nodulocystic acne over the chest and back. No breast development, normal pubic and axillary hair, and marked clitoromegaly are present. Laboratory results show a normal female karyotype and normal glucose and serum electrolytes. Estradiol and estrone are undetectable in the serum. Serum FSH, LH, testosterone, and androstenedione concentrations are high. Pelvic imaging reveals multiple ovarian cysts. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.9/5 (75)
(75) A 19-year-old woman, gravida 1 para 0, at 39 weeks gestation comes to the hospital due to increasing nausea and vomiting. The nausea began after dinner last night and has progressively worsened. Over the past few hours, she has had 2 episodes of vomiting and constant lower abdominal pain. The patient has had constant clear vaginal discharge over the past 2 days and intermittent vaginal spotting. She reports urinary frequency throughout the pregnancy, but no dysuria or hematuria. The patient was treated for a Chlamydia trachomatis infection in the first trimester; her third-trimester C trachomatis screen was negative. She has no chronic medical conditions and has had no surgeries. Temperature is 39.4 C (103 F), blood pressure is 120/68 mm Hg, and pulse is 100/min. The abdomen is nontender with no rebound or guarding; there is diffuse uterine tenderness. The cervix is 2 cm dilated, the fetal vertex is at -1 station, and nitrazine-positive clear fluid is pooled in the posterior fornix. Fetal heart monitoring shows a rate of 165/min, moderate variability, and no decelerations. Tocometry shows contractions every 10 minutes. Laboratory results are as follows:
 Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.8/5 (75)
(75) A 33-year-old woman, gravida 2 para 2, comes to the office for evaluation of nipple discharge. The nipple has intermittently leaked pale gray discharge for the past week. The patient had a progestin-releasing intrauterine device placed for contraception 3 years ago and has been amenorrheic for the past 2 years. Family history is significant for 2 maternal aunts with breast cancer in their 60s. The patient does not use tobacco, alcohol, or illicit drugs. Temperature is 36.7 C (98.1 F), blood pressure is 100/70 mm Hg, and pulse is 70/min. Examination shows large, pendulous breasts without palpable masses or nipple abnormalities. Brownish-gray discharge is expressed from both nipples and is guaiac negative. A urine pregnancy test is negative. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (74)
(74) A 20-year-old woman comes to the office due to dysuria for the past 2 days. She also has had urinary frequency but no fevers, chills, nausea, or hematuria. The patient became sexually active with her boyfriend 6 months ago. Since then, she has had 3 episodes of cystitis. The patient has no other medical conditions and no prior surgery. She takes no medications and does not use tobacco, alcohol, or illicit drugs. The patient uses condoms for contraception, and her last menstrual period was 2 weeks ago. Temperature is 37.2 C (99 F). On abdominal examination, there is mild suprapubic tenderness. No costovertebral or flank tenderness is present. Antibiotic therapy is prescribed. A urine culture grows Escherichia coli. When the patient is called with the results, she reports complete resolution of her symptoms. Repeat urine culture 2 weeks later is negative. Which of the following is the best next step in management of this patient's recurrent cystitis?
(Multiple Choice)
4.9/5 (81)
(81) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)