



 Chat with AI
Exam 5: Obstetrics & Gynecology

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 27-year-old woman comes to the emergency department due to vaginal spotting. The patient recently learned she was pregnant and is at 9 weeks gestation based on a sure, regular last menstrual period. She has had dark red vaginal spotting for the past day but no abdominal pain, cramping, or passage of tissue. The patient had chlamydial cervicitis as a teenager but has no chronic medical conditions. She has started taking a daily prenatal vitamin and does not use tobacco, alcohol, or illicit drugs. Blood pressure is 120/70 mm Hg and pulse is 72/min. Pelvic examination shows a 14-week-sized uterus, a visibly closed cervix, and minimal dark red discharge from the cervical os. Urine pregnancy test is positive. Transvaginal ultrasound is shown below: 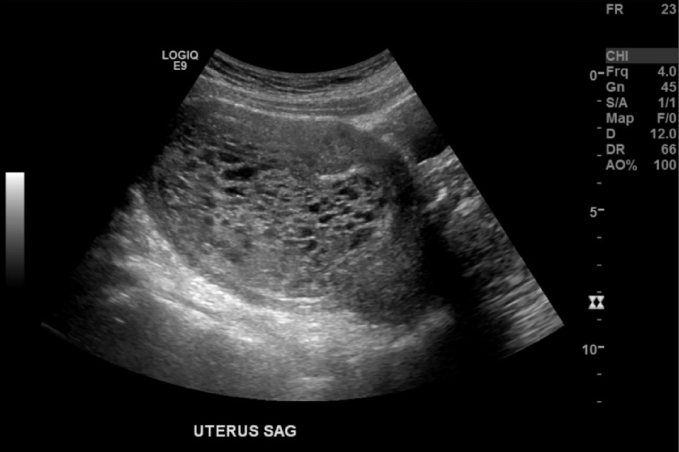 Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.8/5  (64)
(64) A 48-year-old woman, gravida 3 para 3, comes to the office for a follow-up visit due to a history of stage I hormone receptor-positive lobular breast carcinoma. She was diagnosed using needle-guided biopsy after a screening mammogram revealed irregular densities. The patient's condition was treated with mastectomy, radiation therapy, and adjuvant chemotherapy. She also has a history of hypertension and hyperlipidemia, which are controlled with daily medications. The patient quit smoking after the cancer diagnosis and tries to exercise 3 times a week. She is prescribed tamoxifen therapy for an anticipated duration of at least 5 years. As a result of tamoxifen initiation, this patient is at greatest risk for developing which of the following?
(Multiple Choice)
5.0/5 (77)
(77) A 24-year-old woman comes to the office due to painful bumps in her groin. She has had these before, and they typically resolve within a few weeks, sometimes after draining spontaneously. Now the bumps occur more frequently and last longer, and sitting has become painful. The patient has no chronic medical conditions or prior surgeries. Temperature is 36.7 C (98 F). BMI is 35 kg/m2. Physical examination is shown below: 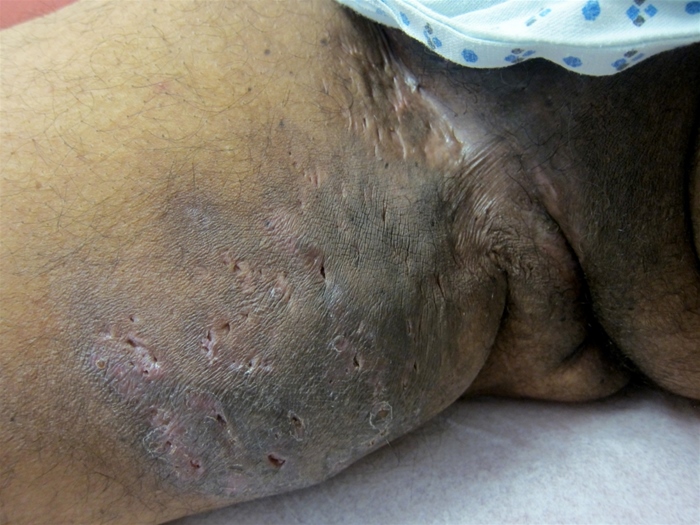 Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.8/5 (71)
(71) A 22-year-old woman with type 1 diabetes mellitus is evaluated in the labor and delivery department due to drowsiness. The patient is somnolent but rouses to sternal rub. An hour ago, the patient underwent a cesarean delivery after a failed induction of labor for preeclampsia with severe features. Her delivery was complicated by postpartum hemorrhage with an estimated blood loss of 2,000 mL due to a torn uterine artery. She is currently receiving a magnesium sulfate infusion and a basal-bolus insulin regimen. Temperature is 99.7 F (37.6 C), blood pressure is 148/96 mm Hg, pulse is 70, and respirations are 10/min. The lungs are clear to auscultation bilaterally. Abdominal examination shows a firm uterus with normal tenderness to palpation. The Pfannenstiel incision is intact and has minimal bleeding. The patellar reflexes are absent bilaterally. There is minimal, dark urine in the Foley catheter. Fingerstick blood glucose level is 240 mg/dL. Which of the following is the most likely cause of this patient's symptoms?
(Multiple Choice)
4.9/5 (93)
(93) A 38-year-old woman comes to the office for evaluation of fatigue. The patient says that she has been "beyond exhausted" for the past 5 months since the birth of her twins. She has had difficulty keeping track of all of the new responsibilities and often forgets to eat. She feels "disappointed" that she was unable to breastfeed despite multiple visits with a lactation consultant. The patient had a vaginal delivery complicated by uterine atony and bleeding which required multiple transfusions. She also has a history of depression treated with an antidepressant that was discontinued against medical advice when she realized she was pregnant. Her last menstrual period was before her last pregnancy. Weight is 52 kg (116 lb), same as her pre-pregnancy weight. BMI is 18 kg/m2. Blood pressure is 85/55 mm Hg and pulse is 65/min. Physical examination shows a thin, tired-appearing woman. Hemoglobin is 10.1 g/dL. Which of the following processes is most likely the primary cause of this patient's symptoms?
(Multiple Choice)
4.9/5 (75)
(75) A 34-year-old woman comes to the office for evaluation of vulvar lesions that have worsened over the past 3 months. She has had 2 sexual partners in the last year. Medical history includes genital infection with herpes simplex virus diagnosed at age 23; when she was 25, her sexual partner was diagnosed with syphilis. Cervical cancer screening last year revealed atypical squamous cells of undetermined significance, with negative testing for high-risk human papillomavirus. The patient smokes cigarettes but does not use alcohol or illicit drugs. Examination reveals multiple nontender, fleshy, verrucous growths clustered at the vestibule of the vulva and over the labia majora. A few lesions are friable and bleed on manipulation. The remainder of the physical examination is normal. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.9/5 (95)
(95) An 11-year-old girl is brought to the office due to vulvar itching. The patient first had the pruritus intermittently, but her symptoms have worsened over the past several months despite nightly application of a moisturizing ointment. She now has trouble sleeping due to the constant itching. The patient has no known medical conditions and has had no surgeries. She has not reached menarche and is not sexually active. The patient is on a community swim team and has swim practice multiple times a week and uses the same bathing suit. Vital signs are normal. Examination of the vulva reveals thin, white skin with excoriations extending to the perianal area. The superior portions of the labia minora are adherent at the midline. A small anal fissure is also noted. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (89)
(89) Ten minutes later, the fetal heart rate tracing appears as shown in the exhibit. 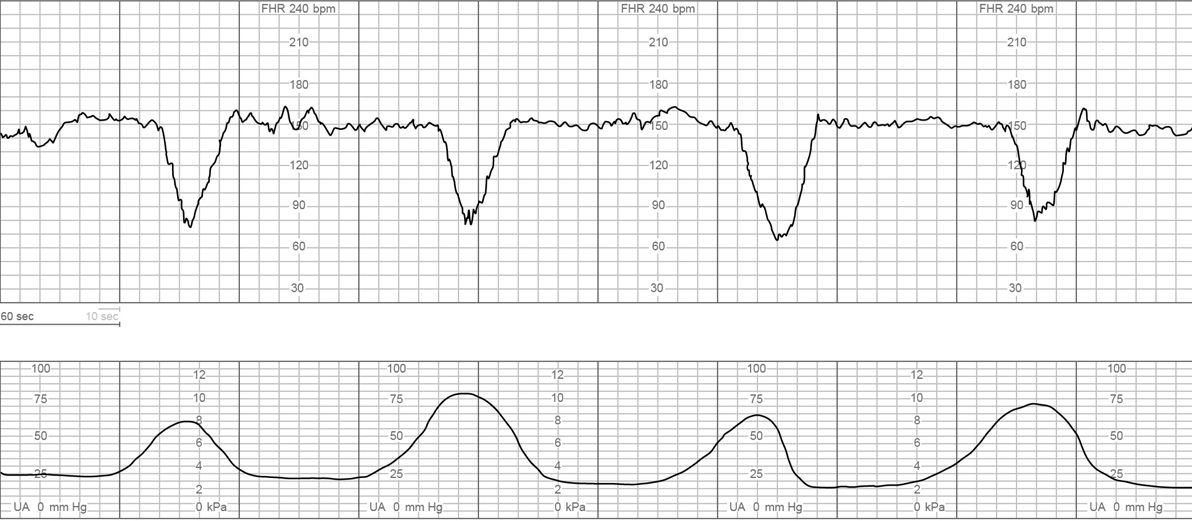 Digital cervical examination is unchanged. Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (76)
(76) A 16-year-old girl comes to the office due to recurrent, intermittent lower abdominal pain. The pain typically begins the day prior to the onset of menses and subsides on the second day of bleeding. She has associated nausea and diarrhea during this time but has no constipation or pain with defecation. These symptoms began 5 months ago and have progressively worsened, causing the patient to miss 2 days of school last month. Menarche was at age 13 and her menses were irregular until 6 months ago; now menses occur every 28 days with 4 to 5 days of moderate bleeding. The patient recently became sexually active and uses condoms for contraception. Her last menstrual period was 2 weeks ago. Vital signs are normal. On speculum examination, a small amount of physiologic discharge is noted throughout the vaginal vault, and the cervix is nonfriable. The uterus is small, mobile, and nontender. Pregnancy test is negative. Which of the following is the most likely cause of this patient's pain?
(Multiple Choice)
4.7/5 (71)
(71) A 12-year-old girl is brought to the office for evaluation of increasing lower abdominal pain. The pain began last week, was initially colicky, and was relieved with ibuprofen. Now the pain is constant and the patient has pain with defecation and a sense of incomplete bowel evacuation. She has had decreased appetite for the last 3 days due to the pain but has had no fever, vomiting, diarrhea, or bloody stool. The patient has had intermittent lower abdominal pain for the last 6 months, but the pain usually resolves after a few days without intervention. She has no medical conditions or prior surgeries. She has not reached menarche. BMI is 19 kg/m2. There is a tender, symmetric suprapubic mass to the level of the umbilicus. External genitalia are normal and breast and pubic hair development is Tanner stage 2. There is a blue-tinged bulge between the labia. Rectal examination reveals an anterior tender, central mass. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (75)
(75) A 27-year-old woman, gravida 2 para 2, comes to the office for follow-up for postpartum depression. Five months ago, she underwent an operative vaginal delivery complicated by a second-degree perineal laceration. After delivery, the patient was started on a selective serotonin reuptake inhibitor for postpartum depression. Her mood has improved, but she is now having relationship issues. The patient reports no change in libido, but she has been avoiding sexual intimacy since delivery due to pain and dryness during intercourse. She is exclusively breastfeeding, and her menses have not returned. Vital signs are normal. The perineal laceration is intact. The vulva is nontender and normal perianal sensation and wink reflex are present. Pain is not reproducible on speculum examination. The vagina has minimal rugation with scant clear discharge. Which of the following is the most likely underlying cause of this patient's symptoms?
(Multiple Choice)
4.8/5 (78)
(78) A 29-year-old woman comes to the emergency department due to vaginal spotting and discharge. She had a positive pregnancy test last week after missing her last menstrual period and estimates that she is at 5 weeks gestation. The patient has had increased vaginal discharge for the past 2 days but no pelvic pain or cramping. Today, she started having vaginal spotting, which prompted her to come to the emergency department. The patient had a spontaneous abortion 3 years ago that was treated with medication, but she has no chronic medical conditions. Temperature is 37.6 C (99.7 F), blood pressure is 100/60 mm Hg, and pulse is 90/min. The abdomen is soft, nontender, and without rebound or guarding. The cervix appears closed and without lesions, and there is bloody, yellow mucus at the external cervical os. The remainder of the physical examination is normal. Quantitative β-hCG level is 5,200 IU/L and blood type is O, Rh positive. Ultrasound shows an intrauterine fetal pole with a positive fetal heartbeat. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (86)
(86) A 29-year-old primigravid woman at 30 weeks gestation comes to the office for evaluation of decreased fetal movement. The patient has had minimal fetal movement for the past few hours. She has had no vaginal bleeding or contractions. The patient has sickle cell disease and is taking low-dose aspirin. Her pregnancy is dated by a 10-week ultrasound, and she had a normal fetal anatomy ultrasound at 18 weeks gestation. At 24 weeks gestation, the patient had an abnormal glucose challenge test, but a normal glucose tolerance test. Blood pressure is 134/82 mm Hg and pulse is 90/min. BMI is 32 kg/m2. Fetal heart rate is 140/min. Fundal height is 26 cm. Ultrasound reveals a cephalic male fetus measuring at the 16th percentile and an amniotic fluid index of 4 cm (normal: >5 cm). Which of the following is the most likely cause of this patient's presentation?
(Multiple Choice)
4.8/5 (70)
(70) A 23-year-old woman comes to the office due to 3 days of fever and dysuria. The patient also has had a pruritic, erythematous vulvar rash that is particularly painful during urination. She is sexually active with one partner, and they use condoms inconsistently. Temperature is 38.7 C (101.7 F), blood pressure is 120/80 mm Hg, and pulse is 84/min. There is suprapubic fullness on abdominal examination. Pelvic examination shows several tender, ulcerated lesions with circular borders on the inside of the left labia minora. Speculum examination shows no cervical friability or mucopurulent discharge. The left inguinal lymph nodes are enlarged and tender. Urethral catheterization is performed due to difficulty with spontaneous voiding. Urinalysis results are as follows:  Urine pregnancy test is negative. Which of the following tests would most likely establish this patient's diagnosis?
 (Multiple Choice)
4.9/5 (77)
(77) A 32-year-old primigravid woman comes to the clinic for a routine prenatal visit and anatomy ultrasound. The patient has no chronic medical conditions and is at 18 weeks gestation. The patient would like to undergo genetic testing because she had a cousin whose child died from Tay-Sachs disease a few years ago. Examination is unremarkable, and ultrasound confirms a male fetus at 18 weeks gestation. Genetic testing in the woman detects a pathogenic variant for the HEXA gene, consistent with Tay-Sachs disease. Which of the following is the best initial statement to the patient?
(Multiple Choice)
4.7/5 (79)
(79) A 70-year-old woman comes to the office for worsening constipation. The patient has chronic constipation for which she takes over-the-counter fiber supplements and stool softeners; however, for the past 3 months, the patient has had to push 2 fingers into her vagina to defecate. She has had increased bloating but no nausea, diarrhea, or abdominal pain. The patient has 1 son. Medical history includes hypothyroidism and type 2 diabetes mellitus for which she takes levothyroxine and metformin. A colonoscopy last year was normal. BMI is 32 kg/m2. Vital signs are normal. The abdomen is soft and nontender with normoactive bowel sounds. On rectal examination, the resting sphincter tone is normal and there are no palpable masses. With Valsalva maneuver, the posterior vaginal wall extends outside the hymenal ring. There is no fecal incontinence with Valsalva maneuver. Anocutaneous reflex is intact bilaterally. TSH is 3.9 mU/L and serum hemoglobin A1c is 7.5%. Fecal occult blood testing is negative. Which of the following is the most likely underlying cause of this patient's presentation?
(Multiple Choice)
4.9/5 (64)
(64) A 42-year-old woman, gravida 2 para 2, comes to the office for evaluation of pelvic pain. The patient's menses are painful, with heavy bleeding that requires her to change her tampon every hour during the first 2 days. She did not have painful menstrual periods until a few years ago. The pelvic pain used to subside after menses but has become constant over the past few months and is unrelieved by ibuprofen. Her menstrual cycles are regular, occur every 28-30 days, and last 4 days. She has had no dysuria, urinary frequency, or constipation. The patient had a tubal ligation after her last delivery. She has not had cervical cancer screening within the past 5 years and is not sexually active. Temperature is 36.7 C (98 F), blood pressure is 120/70 mm Hg, and pulse is 78/min. Examination shows a boggy uterus that is tender to palpation. Which of the following additional findings is most likely present in this patient?
(Multiple Choice)
4.7/5 (71)
(71) A 24-year-old woman comes to the office due to vulvar pain and dysuria for the past 2 days. The patient has not had these symptoms before and has had no increased urinary frequency or flank pain. She returned from a trip to the Caribbean 2 weeks ago and had an intermittent fever and malaise for the last week. The patient is sexually active and has had 3 new male partners over the last 6 months. She has no chronic medical conditions, and her only medication is a combination oral contraceptive. Vital signs are normal. Physical examination shows grouped, shallow ulcers with surrounding erythema on the left labia minora. The left inguinal lymph nodes are tender to palpation. Urinalysis shows 5-10 leukocytes/hpf and 1-2 erythrocytes/hpf. Urine culture is negative. Which of the following pathogens is the most likely cause of this patient's symptoms?
(Multiple Choice)
4.9/5 (74)
(74) A 34-year-old woman, gravida 2 para 2, comes to the emergency department due to a 2-day history of fever, rash, and focal perineal pain. The patient was discharged from the hospital 10 days ago after an uncomplicated spontaneous vaginal delivery at 38 weeks gestation. She had a second-degree perineal laceration that was repaired with suture. The patient has been using a perineal pad, but no intravaginal packing after delivery. She has no chronic medical conditions and no medication allergies. Temperature is 40 C (104 F), blood pressure is 86/54 mm Hg, pulse is 132/min, and respirations are 24/min. The neck is supple. Pulmonary examination reveals bilateral crackles. The abdomen is soft and nontender. A diffuse macular rash is present over the trunk. On pelvic examination, the perineal laceration is tender, but there is no redness or swelling. The uterus is nontender on bimanual examination. Leukocyte count is 20,400/mm3 with 95% neutrophils. Which of the following is the most appropriate pharmacotherapy for this patient?
(Multiple Choice)
4.9/5 (69)
(69) A 22-year-old woman, gravida 1 para 0, at 37 weeks gestation comes to labor and delivery for intermittent leakage of fluid for the past 6 hours. The patient has had some intermittent green-tinged fluid and is now having regular, painful contractions every 3-4 minutes. She has had no vaginal bleeding, and fetal movement is normal. The patient has had an uncomplicated pregnancy, and her group B Streptococcus culture was negative a week ago. She has no chronic medical conditions and has had no surgeries. Temperature is 37.2 C (99 F), blood pressure is 90/68 mm Hg, and pulse is 98/min. Fetal heart rate tracing is shown in the exhibit. 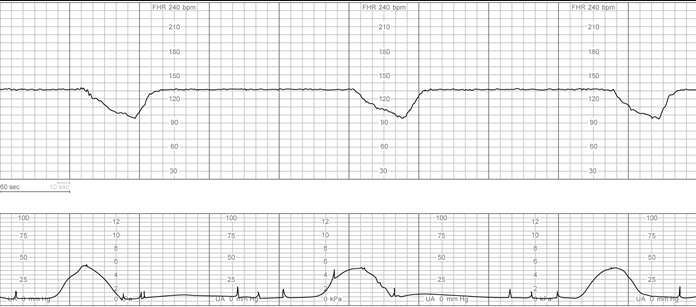 Sterile speculum examination confirms rupture of membranes with meconium-stained amniotic fluid. On digital cervical examination, the cervix is 6 cm dilated, 90% effaced, and the fetal vertex is at +1 station. The fetal heart rate pattern is unchanged with maternal repositioning and oxygen administration. Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (73)
(73) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)