



 Chat with AI
Exam 5: Obstetrics & Gynecology

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 37-year-old woman, gravida 1 para 0, at 37 weeks gestation comes to the emergency department due to severe epigastric pain. The pain started yesterday and has progressively worsened. She developed nausea today but has had no fever, vomiting, or diarrhea. The patient has no contractions, leakage of fluid, or vaginal bleeding. Fetal movement is normal. She has no chronic medical conditions and has had no surgeries. Temperature is 37.3 C (99.1 F), blood pressure is 168/94 mm Hg, and pulse is 98/min. BMI is 29 kg/m2. Fetal heart tones are 140/min. The patient appears anxious and in moderate distress. The abdomen is tender in the epigastrium with no rebound, rigidity, or guarding. The uterus is gravid and nontender. Urinalysis shows 3+ protein. Ultrasound of the right upper quadrant is normal. This patient is at increased risk for developing which of the following complications?
(Multiple Choice)
4.7/5  (86)
(86) A 20-year-old woman comes to the emergency department due to vaginal bleeding and lower abdominal pain that began 3 days ago. The patient describes the bleeding as heavier than a period; she passed some vaginal clots a few hours ago. Menarche was at age 13, and she has often gone months without a menstrual period. The patient's last menstrual period was approximately 7 weeks ago. She is sexually active and uses condoms for contraception. Temperature is 37.2 C (99 F), blood pressure is 120/74 mm Hg, and pulse is 80/min. Abdominal examination shows mild lower abdominal tenderness but no rebound or guarding. On speculum examination, there is no active vaginal bleeding, and the cervical os is closed. Laboratory results are as follows:  A transvaginal ultrasound does not visualize an intrauterine pregnancy, free fluid, or adnexal masses. Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (77)
(77) A 16-year-old girl comes to the office for evaluation of acne. Around the time of her first menstrual period at age 10, the acne appeared only on her face, but over the past 6 years, it has spread to her chest and back. Topical preparations are not effective, and the patient feels anxious regarding social situations at school. She quit the soccer team and has since gained 9.1 kg (20 lb). The patient has never been sexually active. Menses are irregular and her last menstrual period was 3 months ago. She has not had a Pap test but has completed the human papillomavirus vaccination series. The patient takes no medications and does not use tobacco. Family history is noncontributory. Physical examination shows cystic and nodular acne over the face, back, and upper chest. There is no goiter or thyroid masses. Terminal hairs are notable on the upper lip and around the nipples. Development is Tanner stage V. The abdomen is obese and nontender, with no masses and normal bowel sounds. Serum total testosterone and dehydroepiandrosterone sulfate levels are normal. This patient is at greatest risk for developing malignancy of which of the following?
(Multiple Choice)
4.8/5 (68)
(68) A 29-year-old woman comes to the office due to painful sores on her labia. The patient first noticed the sores 3 days ago and has not had these symptoms before. She has also had a headache and intermittent fever for the past 5 days that temporarily resolved with acetaminophen. The patient recently became sexually active with a new male partner and uses a progestin-containing intrauterine device for contraception. She has no chronic medical conditions and takes no medications. Temperature is 38.4 C (101.2 F), blood pressure is 110/70 mm Hg, and pulse is 88/min. Physical examination shows several clusters of multiple small, vesicular lesions on the right labium minora and tender, right inguinal lymphadenopathy. Speculum examination is normal. Urine pregnancy test is negative. If left untreated, this patient's clinical course would most likely result in which of the following?
(Multiple Choice)
4.7/5 (90)
(90) A 26-year-old primigravida at 12 weeks gestation comes to the office for a routine prenatal visit. She reports no concerns with her pregnancy but for the past month the patient has had episodes of dyspnea and wheezing twice a week. She has a 10-year history of asthma that had previously been well-controlled with a low-dose inhaled corticosteroid and an as-needed albuterol inhaler. She has no other medical conditions and takes a daily prenatal vitamin. Vital signs and pulse oximetry are normal. BMI is 32 kg/m2. The patient has gained 4 kg (8.8 lb) during this pregnancy. Lung auscultation reveals normal breath sounds. The remainder of the physical examination shows no abnormalities. Which of the following is the most appropriate response by the physician?
(Multiple Choice)
4.8/5 (60)
(60) A 19-year-old nulligravid woman comes to the emergency department due to abnormal vaginal discharge for the last 2 weeks. The patient has douched twice with no change in the discharge. She had an episode of postcoital vaginal bleeding a few days ago, followed by return of the abnormal yellow discharge. Her last menstrual period was 3 weeks ago. The patient is sexually active and has had the same partner for 6 months; they use the withdrawal method for contraception. Physical examination shows yellow cervical discharge. The cervix is friable and bleeds easily on cotton tip manipulation. Urine pregnancy test is negative. Nucleic acid amplification testing is not available. A sample of the discharge is obtained for microscopic examination. Which of the following is the most likely microscopic finding in this patient?
(Multiple Choice)
4.9/5 (99)
(99) A 47-year-old woman comes to the office due to abnormal uterine bleeding. The patient has had several days of heavy bleeding every 2-3 weeks for the past 4 months. Last week, she had heavy bleeding with passage of large clots, which prompted her to be evaluated. Menarche was at age 16 and the patient was on estrogen/progestin-containing oral contraceptives during most of her 20s and 30s for treatment of dysmenorrhea. She stopped taking oral contraceptives at age 33 when she underwent a tubal ligation after the delivery of her last child. She had a cervical conization at age 29 after an abnormal Pap test, but all subsequent Pap tests have been normal. The patient takes no daily medications. She smokes a pack of cigarettes daily and has a 20-pack-year history. Vital signs are normal. BMI is 39 kg/m2. An endometrial biopsy is performed and shows endometrial adenocarcinoma. Which of the following is the most significant risk factor for this patient's biopsy result?
(Multiple Choice)
4.8/5 (81)
(81) A 33-year-old woman, gravida 2 para 1, at 40 weeks gestation is admitted to the hospital due to contractions and spontaneous rupture of membranes. The patient underwent a cesarean delivery with her first child due to breech presentation; this pregnancy has been uncomplicated. She has no chronic medical conditions and is taking only a prenatal vitamin. Her pre-pregnancy BMI was 20 kg/m2 and she has gained 15.9 kg (35 lb) during the pregnancy. Blood pressure is 130/80 mm Hg. The patient is admitted, epidural anesthesia is administered, and an intrauterine pressure catheter is placed. She quickly dilates to 10 cm with the fetal vertex at 0 station, occiput transverse. Four hours later, the pelvic examination is unchanged but there is molding and caput on the fetal head. Fetal monitoring is category I. Contractions occur every 2-3 minutes and the patient pushes with each contraction. The contraction strength is an average of 210 Montevideo units every 10 minutes. Which of the following is the most likely etiology for this patient's clinical presentation?
(Multiple Choice)
4.7/5 (77)
(77) A 35-year-old woman, gravida 1 para 0, at 35 weeks gestation is evaluated in the labor and delivery unit for fever and chills. Three days ago, she was admitted for acute pyelonephritis and started on broad-spectrum intravenous antibiotics. The patient continues to have a fever and developed chills an hour ago. She has had no painful contractions, leakage of fluid, or vaginal bleeding. Fetal movement is normal. Temperature is 38.3 C (101 F), blood pressure is 118/64 mm Hg, and pulse is 112/min. Fetal heart rate monitoring is 180/min with moderate variability, multiple accelerations, and no decelerations. Tocometry reveals irregular contractions. There is tenderness over the right flank. On pelvic examination, the cervix is 1 cm dilated and 25% effaced. Amniotic membranes are intact, and the fetal presentation is vertex. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (79)
(79) A 22-year-old woman comes to the emergency department with right upper quadrant pain that has worsened over the past day. The pain initially began in the lower abdomen 5 days ago, after she returned from a trip to South America. The right upper quadrant pain increases with deep breathing. She now has fevers, chills, and vomiting. The patient has no diarrhea, constipation, or changes in stool color. She has no medical conditions or previous surgeries. The patient is sexually active with a male partner and does not use contraception. She is currently on her menstrual period but reports increasingly irregular menses over the last 3 months, with occasional spotting. The patient does not use tobacco, alcohol, or illicit drugs. Temperature is 38.9 C (102 F), blood pressure is 100/70 mm Hg, and pulse is 104/min. BMI is 21 kg/m2. Examination shows right upper quadrant tenderness, and the lower abdomen is diffusely tender without guarding. Bowel sounds are present. There is no costovertebral angle tenderness. Skin is normal without rash. A urine pregnancy test is negative. Which of the following is the most likely diagnosis for this patient?
(Multiple Choice)
4.8/5 (79)
(79) A 29-year-old woman comes to the office and says, "my interstitial cystitis is getting worse." Six months ago, the patient developed chronic urinary frequency and suprapubic pain relieved with voiding. She was diagnosed with interstitial cystitis and prescribed amitriptyline, which initially improved her symptoms. However, for the past week, the patient has had worsening urinary urgency and pain with voiding. She has no other chronic medical conditions and has no medication allergies. The patient recently started a relationship with a male partner and uses oral contraceptives. Temperature is 37.2 C (99 F), blood pressure is 126/74 mm Hg, and pulse is 88/min. The abdomen is soft with diffuse lower abdominal discomfort to deep palpation. A clean-catch urinalysis shows:  Urine culture and pregnancy testing are negative. Which of the following is best next step in management of this patient?
 (Multiple Choice)
4.8/5 (91)
(91) A 24-year-old primigravid woman comes to the office for her first prenatal visit. The patient's last menstrual period was 2 months ago, and she has had no vaginal bleeding or cramping. She has a history of intravenous heroin use but stopped when she was diagnosed with HIV infection last year. The patient has completed a methadone program and currently does not use tobacco, alcohol, or illicit drugs. She started combination antiretroviral therapy last year but stopped taking her medications 2 weeks ago when she found out she was pregnant. Vital signs are normal. Serum laboratory results are as follows:  Urine β-hCG is positive and toxicology screen is negative. Ultrasound confirms a 6-week intrauterine pregnancy. Which of the following is the best next step in management of this patient?
 (Multiple Choice)
5.0/5 (79)
(79) A 34-year-old woman is brought to the emergency department after a syncopal episode. The patient was at work when she became lightheaded, started sweating, and then fell to the floor. Now, she feels better and has no chest pain, dyspnea, or palpitations. The patient is currently on day 10 of her menstrual cycle. She reports that her menstrual periods still occur monthly but have become progressively heavier and longer over the past year, despite being on combination oral contraceptives. Temperature is 36.7 C (98.1 F), blood pressure is 100/60 mm Hg, and pulse is 112/min. BMI is 27 kg/m2. On speculum examination, multiple blood clots are removed from the vaginal vault. The cervix has no lesions, but there is active bleeding from the cervical os. Bimanual examination shows a 12-week-size, irregularly shaped, enlarged uterus. Hemoglobin is 4.9 g/dL. Urine pregnancy test is negative. Which of the following is the most likely cause of this patient's symptoms?
(Multiple Choice)
4.9/5 (87)
(87) A 38-year-old woman, gravida 2 para 1, at 28 weeks gestation comes to the office for a routine prenatal visit. The patient has had no abdominal pain, vaginal bleeding, or leakage of fluid. She reports active fetal movement. The patient has been on antiretroviral therapy since being diagnosed with HIV 3 years ago, and her last viral load was undetectable. She had negative syphilis and hepatitis C screening at her initial prenatal visit. Blood pressure is 122/74 mm Hg, and pulse is 86/min. The abdomen is nontender, and fundal height is 28 cm. Fetal heart tones are 140/min. The rest of the examination is normal. Laboratory results are as follows: 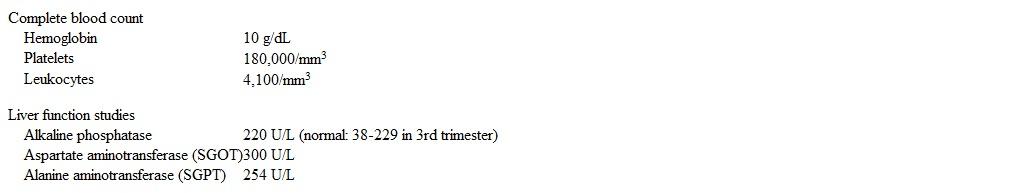 Ultrasound of the right upper quadrant shows no stones or dilation of the common bile duct. Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (91)
(91) A 32-year-old woman, gravida 3 para 2, at 41 weeks gestation comes to the office for a routine prenatal visit. She has had no contractions, vaginal bleeding, or leakage of fluid. Fetal movement is normal. The patient's pregnancy has been uncomplicated. An ultrasound at 18 weeks gestation showed normal fetal anatomy and a posterior placenta. She has no chronic medical conditions and has had no previous surgeries. Her other pregnancies ended in vaginal deliveries at term. The patient takes a daily prenatal vitamin and does not use tobacco, alcohol, or illicit drugs. Blood pressure is 110/80 mm Hg and pulse is 80/min. BMI is 28 kg/m2. Fundal height is 40 cm. The cervix is 1 cm dilated and 10% effaced. Nonstress test is reactive. The patient would like to await spontaneous labor rather than undergo an induction. Delaying delivery to 42 weeks gestation in this patient increases the risk of which of the following pregnancy-related complications?
(Multiple Choice)
4.9/5 (87)
(87) A 40-year-old woman comes to the emergency department due to nausea, vomiting, and dizziness. The patient has been unable to tolerate any oral intake over the last 2 days. She has had no fevers, chills, diarrhea, or constipation. She reports no sick contacts. The patient has a history of migraines for which she takes daily preventive treatment, but she has been unable to take her medications for the past several days due to nausea. Her last menstrual period was approximately 8 weeks ago, and she has a history of irregular menses. Temperature is 36.7 C (98 F), blood pressure is 90/60 mm Hg, and pulse is 112/min. BMI is 32 kg/m2. Physical examination shows dry mucous membranes, decreased skin turgor, and prolonged capillary refill. The abdomen is soft and nontender. Pelvic examination shows a 12-week-size uterus and bilateral adnexal masses. Pelvic ultrasound shows a uterus filled with multiple small cysts but no embryo. The ovaries are 10 cm bilaterally with a multilocular cystic appearance. Urine pregnancy test is positive. Which of the following is the most likely mechanism of this patient's adnexal pathology?
(Multiple Choice)
4.8/5 (82)
(82) A 27-year-old woman, gravida 3 para 2, at 14 weeks gestation comes to the office for an initial prenatal visit. The patient has had no vaginal bleeding, pelvic pain, or abnormal vaginal discharge. Her first 2 pregnancies ended at 22 weeks gestation; both deliveries occurred after light vaginal spotting followed by a precipitous, nonpainful vaginal delivery. The patient has no chronic medical conditions or prior surgeries. Her only medication is a prenatal vitamin. She does not use tobacco, alcohol, or illicit drugs. Vital signs are normal. BMI is 22 kg/m2. Fetal heart tones are 160/min. Ultrasound reveals a single intrauterine fetus measuring 14 weeks gestation, a cervical length of 2.9 cm (normal: >2.5), and no adnexal masses. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (72)
(72) A 31-year-old woman, gravida 2 para 1, at 10 weeks gestation comes to the office for an initial prenatal visit. The patient has had no vaginal bleeding or cramping. Her first pregnancy was uncomplicated and ended with a term spontaneous vaginal delivery. She has no chronic medical conditions and has had no previous surgeries. The patient takes a daily prenatal vitamin and does not use tobacco, alcohol, or illicit drugs. Blood pressure is 120/70 mm Hg and pulse is 68/min. BMI is 24 kg/m2. The uterine fundus is palpated above the pubic symphysis. Pelvic ultrasound shows 2 viable intrauterine gestations, a single fundal placenta, and a thin intertwin membrane that meets the placenta at a 90-degree angle. This patient is at highest risk for which of the following complications?
(Multiple Choice)
4.8/5 (83)
(83) A 32-year-old nulligravid woman comes to the office for evaluation of possible infertility. The patient underwent removal of a progestin-releasing intrauterine device (IUD) 13 months ago, and since then she has been having unprotected intercourse 3 or 4 times per week with her husband. The patient's menstrual cycles occur every 28-31 days with 3-5 days of light to moderate bleeding and no associated fatigue, cramping, or bloating. Her last menstrual period was 3 weeks ago. BMI is 28 kg/m². Vital signs are normal. Pelvic examination and transvaginal ultrasonography reveal an anteverted uterus and normal, bilateral adnexa. The remainder of the examination is normal. Her husband's semen analysis is normal. Hysterosalpingogram shows a normal uterine cavity and bilateral tubal patency. Which of the following is the best next step for this patient?
(Multiple Choice)
4.7/5 (88)
(88) A 32-year-old primigravid woman comes to the office for a follow-up appointment at 28 weeks gestation. The patient has gestational diabetes mellitus diagnosed at 25 weeks gestation and has been managing it with dietary modification. She follows a low-carbohydrate diet and eats 3 small meals and 2 snacks daily, as recommended by her dietitian. Fasting blood glucose levels have been 110-130 mg/dL for the past 3 weeks, and most of the patient's 2-hour postprandial blood glucose levels have been >140 mg/dL. Review of systems is negative for polyuria or polydipsia. BMI is 38 kg/m2. Blood pressure is 134/80 mm Hg, and pulse is 76/min. Physical examination is unremarkable. Urinalysis results are as follows:
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (66)
(66) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)