



 Chat with AI
Exam 5: Obstetrics & Gynecology

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 37-year-old primigravid woman at 34 weeks gestation comes to labor and delivery from the office due to a blood pressure of 152/96 mm Hg. The patient has a spontaneous dichorionic diamniotic twin gestation, but her prenatal course has otherwise been uneventful, with normal blood pressure measurements throughout the pregnancy. She has no known medical conditions and has exercised throughout her pregnancy. The patient reports no contractions, vaginal bleeding, or leakage of fluid. She has no headaches or visual changes. Repeat blood pressure is 150/102 mm Hg. Deep tendon reflexes are 3+. Nonstress test is reactive for both fetuses. Laboratory results are as follows:
 Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.9/5  (82)
(82) A 41-year-old woman, gravida 2 para 1, at 35 weeks gestation comes to the emergency department with contractions. The patient began to have contractions 5 hours ago after spending the day at the beach. She is now having 3-5 contractions every hour that sometimes are relatively painful. The patient has had no vaginal bleeding or leakage of fluid. She has iron deficiency anemia, for which she takes a prenatal vitamin and iron supplementation. The patient had a positive rectovaginal culture for group B Streptococcus at her prenatal visit earlier this week. She had a vaginal delivery at term with her prior pregnancy. Blood pressure is 110/80 mm Hg and pulse is 92/min. A contraction is palpated on abdominal examination, but the uterus is nontender between contractions. The cervix is closed on digital cervical examination. A nonstress test has a baseline of 120/min, moderate variability, and multiple accelerations. Tocodynamometry reveals irregular uterine contractions. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (74)
(74) A 39-year-old woman, gravida 4 para 3, comes to the emergency department after 2 days of fever, heavy vaginal bleeding, and lower abdominal pain. Six days ago, she had an elective abortion at an outside clinic at 8 weeks gestation. Since the procedure, the patient has had bleeding that has become increasingly heavy and malodorous and is now soaking through a pad every 2-3 hours. She has no medical problems, takes no medications, and has no allergies. Temperature is 39.8 C (103.7 F), blood pressure is 100/65 mm Hg, pulse is 108/min, and respirations are 16/min. Physical examination reveals lower abdominal tenderness but no rigidity or guarding. Pelvic examination shows copious foul-smelling, purulent, and bloody discharge from the cervical os. Bimanual examination shows a tender, anteverted, soft uterus that is 12 weeks in size. Transvaginal ultrasound reveals a 12-cm uterus with an irregularly thickened echogenic endometrial stripe with active blood flow. The adnexa are normal bilaterally, and there is a small amount of free fluid in the pelvis. She is started on broad-spectrum intravenous antibiotics. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (92)
(92) A 32-year-old woman, gravida 2 para 1, at 30 weeks gestation comes to the emergency department due to abdominal pain. Twelve hours ago the patient began to have right-sided abdominal pain that has become progressively worse, and she now has nausea and vomiting. She has irregular contractions but no vaginal bleeding or leakage of fluid. The patient has no chills, dysuria, or urinary frequency. She has chronic hypertension. Her only surgery was a term cesarean delivery for superimposed preeclampsia and breech presentation. Temperature is 38 C (100.4 F), blood pressure is 146/98 mm Hg, and pulse is 102/min. Fetal heart rate tracing shows a baseline of 170/min with moderate variability and no decelerations. Contractions occur every 5-12 minutes. There is moderate tenderness to palpation over the right lateral flank and rebound and guarding on the right side of the abdomen. The uterine fundus is nontender and the cervix is closed. Urinalysis is normal. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (77)
(77) A 31-year-old woman at 12 weeks gestation comes to the office for recurrent headaches. The patient has a history of episodic migraines that typically resolve with nonsteroidal anti-inflammatory drugs; but since becoming pregnant, the headaches have become more severe and frequent. Over the past month, the patient has had 5 migraine headaches with associated nausea and vomiting that required treatment in the emergency department. In addition, she has had to go to a dark room and rest for a few hours before recovering. The patient has no other chronic medical conditions and her only other medication is a daily prenatal vitamin. Temperature is 36.7 C (98 F), blood pressure is 120/80 mm Hg, and pulse is 76/min. Fetal heart rate is 160/min. Cranial nerves are intact. Deep tendon reflexes are 2+. Strength and sensation are normal in all extremities. Which of the following is the most appropriate preventive therapy for this patient?
(Multiple Choice)
4.9/5 (80)
(80) A 54-year-old postmenopausal woman comes to the office due to involuntary loss of urine. The patient is unable to hold her urine during the day but has no loss of urine while sleeping. She is sexually active but has been avoiding intercourse for the past few months because she sometimes has leakage of urine during intercourse. The patient also loses urine when laughing and coughing. She has no chronic medical conditions and takes no daily medications. Her only surgery was a cesarean delivery at age 30 for a pregnancy complicated by pyelonephritis and preterm labor at 34 weeks gestation. Vital signs are normal, and BMI is 38 kg/m2. Pelvic examination shows dribbling of urine when the patient coughs. A postvoid residual is 30 mL. Urinalysis shows no abnormalities. Which of the following is the most appropriate treatment for this patient's incontinence?
(Multiple Choice)
4.8/5 (78)
(78) A 27-year-old woman, gravida 1 para 1, is evaluated on the postpartum floor due to a generalized tonic-clonic seizure that occurred 30 hours after a vaginal delivery. The patient was induced at 37 weeks gestation for preeclampsia with severe features via an oxytocin infusion for 48 hours. She also received magnesium sulfate for maternal seizure prophylaxis, which was discontinued 24 hours after delivery. The patient had a spontaneous vaginal delivery complicated by a postpartum hemorrhage that was treated with bimanual uterine massage and an oxytocin bolus and infusion. Temperature is 37.1 C (98.7 F), blood pressure is 128/82 mm Hg, pulse is 78/min, and respirations are 18/min. Physical examination shows a lethargic patient with no focal neurologic deficits. Laboratory results on serum drawn immediately after the seizure are as follows:  Which of the following is the most likely underlying cause of this patient's seizure?
 (Multiple Choice)
4.8/5 (88)
(88) A 28-year-old woman, gravida 2 para 1, at 24 weeks gestation comes to the office for a routine prenatal visit. She has had increasing shortness of breath but no cough or chest pain. The patient has had no vaginal bleeding, leakage of fluid, or contractions. Fetal movement is normal. She has no chronic medical conditions, and her only prior surgery is a cesarean delivery with her first pregnancy. The patient had a fetal anatomy ultrasound at 18 weeks gestation, but not all structures were well visualized. Blood pressure is 116/70 mm Hg and pulse is 68/min. Fundal height is 32 cm. Ultrasound reveals an amniotic fluid index of 40 cm (normal: 8-24 cm). The fetus is in breech presentation and has an estimated fetal size consistent with 24 weeks gestation. An isolated tracheoesophageal fistula is visualized. The placenta is located posteriorly. This patient is at increased risk for which of the following obstetric complications?
(Multiple Choice)
4.9/5 (82)
(82) A 32-year-old woman, gravida 2 para 1, at 40 weeks gestation is admitted to the hospital due to spontaneous rupture of membranes and regular, painful contractions. This pregnancy has been uncomplicated, but her last pregnancy resulted in an operative vaginal delivery for a non-reassuring fetal status. The patient has no chronic medical conditions and no prior surgeries. Her digital cervical examinations since admission are shown below: 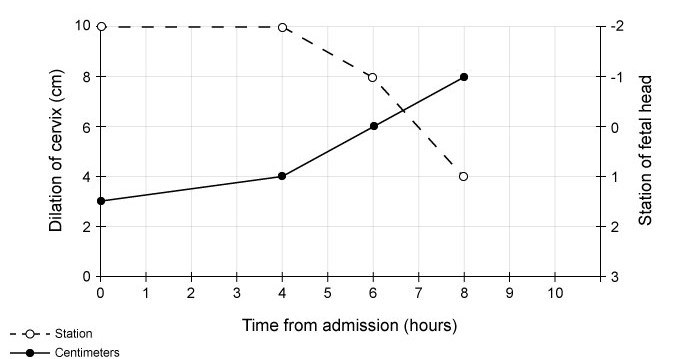 Current temperature is 37.2 C (99 F), blood pressure is 120/70 mm Hg, and pulse is 68/min. Fetal heart rate monitoring is category I and tocodynamometer shows contractions every 2-3 minutes. Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.7/5 (87)
(87) A 29-year-old woman, gravida 2 para 1, at 12 weeks gestation comes to the office for an initial prenatal visit. The patient has had no nausea, abdominal pain, or vaginal bleeding. Her first pregnancy ended in an operative vaginal delivery after induction of labor at 42 weeks gestation. She has no chronic medical conditions and has had no surgeries. The patient takes a daily prenatal vitamin and does not use tobacco, alcohol, or illicit drugs. Blood pressure is 118/74 mm Hg and pulse is 76/min. BMI is 27 kg/m2. The uterine fundus is 2 cm below the umbilicus. Pelvic examination is normal. Ultrasound shows an intrauterine 12-week twin gestation with 2 posterior-fundal placentas. The fetal heart rates are normal. Compared to patients with singleton gestations, this patient is at increased risk for which of the following obstetric-related complications?
(Multiple Choice)
4.8/5 (86)
(86) A 25-year-old nulligravid woman comes to the office due to continued pelvic and lower back pain. The pain has worsened over the past year. It is constant but intensifies a few days before the patient's menstruation and improves toward the end of her cycle. The patient has been in a monogamous relationship for the past 4 years. She started taking ibuprofen and combined oral contraceptives 9 months ago when she began having pelvic pain, and they have minimally improved her pain. Temperature is 37.2 C (99 F) and blood pressure is 120/78 mm Hg. BMI is 24 kg/m2. Examination shows tenderness in the posterior vaginal fornix, decreased uterine mobility, and thickening of the uterosacral ligaments. No adnexal masses are palpated. Urine β-hCG is negative. Hemoglobin is 12 g/dL and leukocytes are 8,200/mm3. Transvaginal ultrasound reveals normal pelvic anatomy.
Which of the following is the best next step in evaluation of this patient?
(Multiple Choice)
4.8/5 (85)
(85) An 88-year-old woman is brought to the emergency department due to postmenopausal bleeding. The patient has had bright red vaginal bleeding and pelvic pain for the past week. She lives in a nursing home and was brought by her caregiver, who states that she is also refusing to bathe or leave her room. Vital signs are normal. BMI is 36 kg/m2. The abdomen is soft and nontender. The vulva is edematous and tender and there is a friable posterior perineal laceration. The vagina is dry and pale, and the cervix is stenotic. The remainder of the physical examination is unremarkable. On ultrasound, the uterus is small with a 3-mm endometrial lining, the ovaries are not visualized, and no adnexal masses are present. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (76)
(76) A 14-year-old girl is brought to the office due to heavy vaginal bleeding. Since menarche at age 13, menses have been irregular but not painful. Her last menstrual period was 6 weeks ago, and her current menses started 7 days ago. She is soaking through a thick pad every 2 or 3 hours and bled through her clothing overnight. She has no history of recurrent epistaxis or bruising. The patient has no chronic medical conditions or previous surgeries. Her mother required a blood transfusion with delivery, but has had no other bleeding episodes. Blood pressure is 110/60 mm Hg and pulse is 65/min. The external genitalia are normal and consistent with sexual maturity rating (Tanner stage) 4 development. The abdomen is nontender, nondistended, and has no masses. On pelvic examination, there is dark red bleeding from the cervical os. Urine pregnancy test is negative. Which of the following is the most likely cause of this patient's symptoms?
(Multiple Choice)
4.8/5 (83)
(83) A 16-year-old girl is brought to the office because she has not started her menstrual period. The patient's 14-year-old sister underwent menarche a few months ago and her mother began menstruating at age 13. The girl has had no headaches, changes in vision, weight gain, nipple discharge, or abdominal pain. She has no chronic medical conditions and has had no surgeries. The patient is not sexually active and is not on contraception. She plays basketball for her high school team. Height is at the 85th percentile and weight is at the 25th percentile for age. Vital signs are normal. Breast, axillary, and pubic hair development are sexual maturity rating (Tanner stage) IV. The abdomen is soft, nontender, and has no palpable masses. On pelvic examination, the external genitalia appear normal and the vagina ends in a blind pouch. Pelvic ultrasound reveals bilateral ovaries, but no uterus or cervix. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
5.0/5 (84)
(84) A 32-year-old woman, gravida 2 para 1, at 18 weeks gestation comes to the office for her first prenatal visit. She has noticed new facial hair and acne over the past few weeks. The patient has had no vaginal bleeding or abdominal pain. Some mild nausea earlier in the pregnancy has resolved. The patient has had no vomiting and is eating 5 small meals a day. Her prepregnancy BMI was 24 kg/m2 and she has gained 2.3 kg (5 lb) over the past 2 months. Examination shows acne on her chest and back and coarse hair in the distribution of the upper lip, chin, periareolar area, chest, and lower abdomen. The uterus is nontender and fundal height is 2 cm below the umbilicus. Ultrasonogram shows an intrauterine gestation consistent with dates and bilateral 7-cm solid masses in the ovaries. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (85)
(85) A 39-year-old primigravid woman at 7 weeks gestation comes to the emergency department for vaginal bleeding. She has had dark brown vaginal spotting and mild uterine cramping for the past day. The patient has felt extreme fatigue and has had daily nausea and vomiting for the past week. Blood pressure is 112/68 mm Hg and pulse is 86/min. The abdomen is soft and without rebound or guarding. On pelvic examination, there is scant dark blood in the vagina, and the cervix is visually closed. Pelvic ultrasound is shown in the image below: 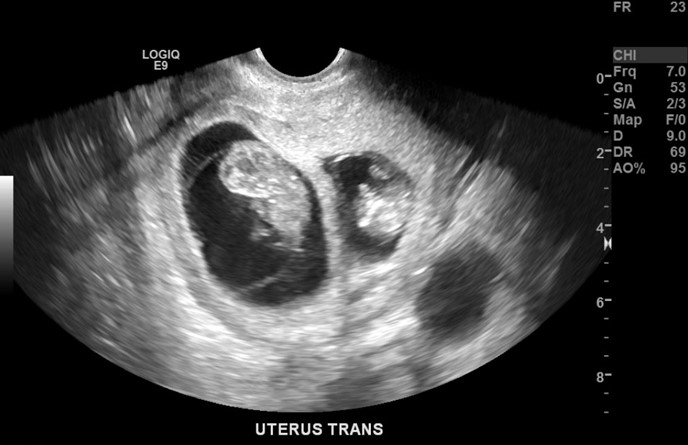 Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.7/5 (83)
(83) A 48-year-old woman comes to the office due to clear, watery vaginal discharge for the past 2 weeks following a hysterectomy and bilateral salpingo-oophorectomy for endometriosis. Her surgery was complicated by severe pelvic adhesions. The discharge occurs throughout the day and night, and as a result, the patient has been using several pads a day. She has no fever, vaginal bleeding, or pelvic pain. The patient does not use tobacco, alcohol, or illicit drugs. Vital signs are normal. The patient's abdomen is soft and nontender with a well-healed laparotomy incision. Genitourinary examination shows a well-rugated vaginal mucosa and a pool of clear fluid in the vaginal canal. The vaginal apex appears normal. Wet mount microscopy shows a few squamous epithelial cells and rare leukocytes. Which of the following is the most likely cause of this patient's symptoms?
(Multiple Choice)
4.8/5 (75)
(75) This patient is at increased risk for which of the following obstetric complications?
(Multiple Choice)
4.7/5 (78)
(78) A 19-year-old woman comes to the office with a 6-month history of amenorrhea. Menarche occurred at age 11 and her menstrual cycles were regular until 9 months ago. The patient has no changes in vision or recent weight loss. She has no medical problems or previous surgeries. She eats a high-protein/low-fat diet and is a collegiate soccer player. The patient is sexually active and has no history of sexually transmitted infections. She does not use tobacco, alcohol, or illicit drugs. Blood pressure is 120/70 mm Hg and pulse is 78/min. BMI is 20 kg/m2. On pelvic examination, the uterus is small, mobile, and nontender. The adnexae are not palpable. A pregnancy test is negative. Prolactin and TSH levels are normal. No menstrual bleeding occurred after a 10-day challenge with medroxyprogesterone acetate. Compared to the general population, this patient is at greatest risk for which of the following?
(Multiple Choice)
4.9/5 (79)
(79) A 26-year-old woman, gravida 2 para 2, is in the postpartum unit after an uncomplicated spontaneous vaginal delivery with involuntary dribbling of small amounts of urine. It has been 6 hours since the delivery and the patient has been unable to empty her bladder. During labor, she received epidural anesthesia for severe pain with contractions and her bladder was intermittently catheterized. The patient has no chronic medical conditions, takes no medications, and has no known allergies. Vital signs are normal. Examination shows a firm uterine fundus palpable at the umbilicus and fullness and tenderness above the pubic symphysis. The perineum and vagina are edematous but without lacerations. Sensation is intact in the lower extremities, but the patient is unable to void a measurable amount. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.7/5 (61)
(61) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)