



 Chat with AI
Exam 5: Obstetrics & Gynecology

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A physician goes to labor and delivery on Friday evening to check on the labor progression of her patient. The patient has had a protracted labor course throughout the day. Her cervical dilation has increased 1 cm over the last 3 hours, and she is now at 8 cm dilation. The patient's vital signs are normal, and the fetal heart rate tracing is category 1. The physician is leaving town for vacation in a few hours, but an on-call obstetrician will be available for deliveries. The physician recommends a cesarean delivery to the patient because of the protracted labor course and the physician's inability to be at the delivery in a few hours. This situation demonstrates which of the following ethical principles?
(Multiple Choice)
4.9/5  (61)
(61) A 34-year-old woman, gravida 3 para 0 aborta 2, at 18 weeks gestation comes to the office for a routine prenatal visit. The patient feels well and has no concerns. She has no chronic medical conditions, and her only medication is a daily prenatal vitamin. The patient's prior pregnancies ended in 2 dilation and curettage procedures for spontaneous abortions due to fetal aneuploidy. She does not use tobacco, alcohol, or illicit drugs. Blood pressure is 126/84 mm Hg and pulse is 88/min. Prepregnancy BMI was 22 kg/m2, and she has gained 4.5 kg (10 lb) so far during this pregnancy. Fetal heart tones are 148/min. Transabdominal ultrasound shows a singleton fetus in breech presentation measuring 18 weeks gestation. Amniotic fluid index and fetal anatomy are within normal limits. The placenta is anterior and low-lying, with numerous lacunae and myometrial thinning. Cervical length is 3.8 cm (normal: >2.5 cm). This patient is at greatest risk for which of the following pregnancy-related complications?
(Multiple Choice)
4.7/5 (79)
(79) A 39-year-old woman, gravida 3 para 2, comes to the office at 20 weeks gestation for prenatal care and follow-up of a prenatal ultrasound. The patient has had no pelvic pain, leakage of fluid, or vaginal bleeding. Fetal movement has been normal. Prior pregnancies were uncomplicated and delivered vaginally at term. This pregnancy was conceived via in vitro fertilization with normal preimplantation genetic testing. Blood pressure is 110/60 mm Hg and pulse is 78/min. BMI is 32 kg/m2. Ultrasound performed earlier today showed a single fetus in the breech presentation, a placenta covering the internal cervical os, and a cervical length of 4.2 cm. The anatomical survey is normal, and estimated fetal weight is at the 50th percentile. Based on the ultrasound findings, which of the following is the best next step in the treatment of this patient?
(Multiple Choice)
4.9/5 (76)
(76) A 26-year-old nulligravid woman comes to the office to discuss treatment of cervical intraepithelial neoplasia 3, which was revealed on a Pap test 4 weeks ago and confirmed by colposcopic biopsies. The patient has one dose remaining of catch-up human papillomavirus vaccination. She has smoked a pack of cigarettes daily for 10 years and does not use alcohol or illicit drugs. The patient recently married and is planning to have children in the next few years. She currently receives progesterone injections for contraception and takes no other medications. Her father is currently undergoing chemotherapy for pancreatic cancer. Risks and benefits of treatment options are discussed. Which of the following is the most likely complication of treatment for this patient?
(Multiple Choice)
4.7/5 (84)
(84) A 24-year-old woman comes to the office due to postcoital bleeding for the past week. She has had 3 new male sexual partners over the last 6 months and uses condoms inconsistently. The patient has mild, persistent asthma for which she takes low-dose, inhaled glucocorticoids. She is also taking oral contraceptives, and her last menstrual period was 3 weeks ago. Vital signs are normal. Pelvic examination shows a thin, malodorous vaginal discharge and erythema of the vulva and vaginal mucosa. The cervix is erythematous and has multiple macular lesions that easily bleed when probed with a cotton swab. Wet mount microscopy of the discharge shows motile, ovoid-shaped organisms. Urine pregnancy test is negative. Which of the following is the most appropriate treatment for this patient?
(Multiple Choice)
4.8/5 (94)
(94) A 52-year-old postmenopausal woman comes to the office for evaluation of vulvar irritation. The patient wears sanitary napkins due to stress urinary incontinence and occasionally notices streaks of blood on the napkin. She is sexually active and has had some pain with sexual intercourse. The patient underwent a hysterectomy and bilateral salpingo-oophorectomy at age 48 for adenomyosis. She has had abnormal Pap tests previously but normal colposcopy results. The patient currently uses a nicotine patch for smoking cessation. Vital signs are normal. Pelvic examination shows multiple vulvar excoriations with surrounding erythema. There is an erythematous, friable plaque on the left labium majus. On speculum examination, the vagina has no lesions or abnormal discharge. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.9/5 (73)
(73) A 21-year-old woman comes to the emergency department due to severe right lower quadrant pain. The pain began 3 weeks ago and was initially intermittent and dull. However, over the last 4 hours the pain has become constant and severe. She is now having nausea and vomiting, but no diarrhea or dysuria. The patient has no chronic medical conditions and has had no surgeries. She has regular, monthly menses, and her last menstrual period was 2 weeks ago. Temperature is 37.8 C (100 F), blood pressure is 140/70 mm Hg, and pulse is 93/min. BMI is 19 kg/m². Abdominal examination reveals right lower quadrant tenderness with rebound and guarding. Pelvic examination shows scant physiologic cervical discharge and no cervical motion tenderness. A tender, right adnexal mass is palpated. Pregnancy test is negative. Pelvic ultrasound reveals a 6-cm, partially calcified, right ovarian mass with multiple thin, echogenic bands. There is decreased Doppler flow to the right ovary. Which of the following is the most likely cause of this patient's mass?
(Multiple Choice)
4.8/5 (82)
(82) A 44-year-old woman comes to the office with a 6-month history of painful sexual intercourse. She has no associated itching or abnormal vaginal discharge. The patient has never had these symptoms before and has had no problems with sexual desire or orgasm. She has been monogamous with her husband for 15 years. The patient's menstrual periods are regular and are not associated with unusual pain. She has no urinary or gastrointestinal symptoms. Her medical history is notable for mild hypertension that has been well controlled with dietary changes and exercise. The patient has no history of pelvic inflammatory disease or gynecologic surgery. Her only medications include a daily multivitamin and saline eye drops for chronic dry eyes. The patient does not use tobacco, alcohol, or illicit drugs. Temperature is 36.5 C (97.7 F), blood pressure is 136/88 mm Hg, pulse is 72/min, and respirations are 12/min. The neck is supple. The patient has mild dental caries. Chest auscultation reveals no abnormalities. The abdomen is soft and nontender. Pelvic examination shows normal-appearing external genitalia and dry vaginal mucosa. The uterus and adnexa are normal with no cervical motion tenderness. Which of the following is the most likely cause of this patient's current condition?
(Multiple Choice)
4.9/5 (73)
(73) A 15-year-old girl is brought to the emergency department due to a severe headache, abdominal pain, nausea, and vomiting. The patient reports an occipital headache that began 4 days ago and has increased in severity despite treatment with acetaminophen. The nausea and vomiting began a day ago, and now the patient is unable to tolerate liquids. The abdominal pain is constant but worsens with vomiting. She has no chills, photophobia, changes in vision, or dizziness. The patient is sexually active. Her last menstrual period was 4 months ago. She does not use tobacco, alcohol, or illicit drugs. Temperature is 37.2 C (99 F), blood pressure is 150/90 mm Hg, and pulse is 90/min. Cardiopulmonary examination is normal. Abdominal examination shows right upper quadrant tenderness without rebound or rigidity. There is a nontender, palpable mass that extends from the suprapubic bone up to the umbilicus. Neurologic examination shows intact cranial nerves, no nystagmus, and no pain with neck flexion. Bilateral lower extremities have 3+ deep tendon reflexes and sustained ankle clonus. Serum β-hCG is elevated. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.9/5 (74)
(74) A 33-year-old woman, gravida 3 para 2, at 37 weeks gestation is admitted in active labor. The patient's first child was born via cesarean delivery for breech presentation, and her second was born via spontaneous vaginal delivery. She receives epidural analgesia on admission and her contractions become nonpainful. An intrauterine pressure catheter is placed due to variable decelerations, which resolve with amnioinfusion. The patient reaches a cervical dilation of 10 cm and 100% effacement; the fetal vertex is at +1 station. After she pushes for 20 minutes, there is a sudden onset of abdominal pain, which is initially intermittent but becomes constant after a few minutes. The fetal heart rate tracing is shown in the following exhibit. 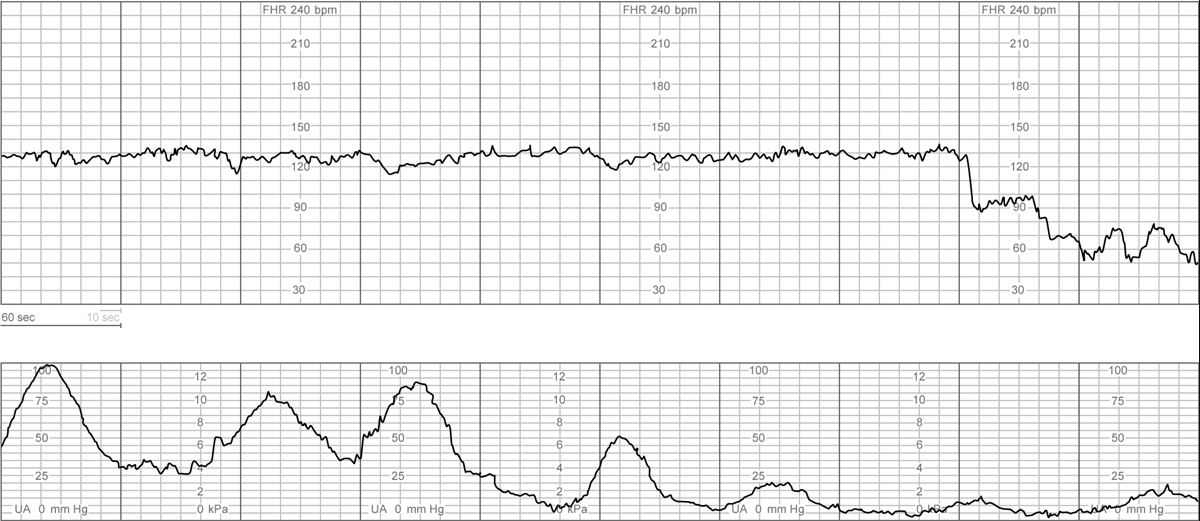 On repeat examination, the cervix is 10 cm dilated and 100% effaced, and the fetal vertex has retracted to ?2 station. Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (82)
(82) A 45-year-old woman comes to the office for evaluation of irregular menstrual bleeding. For the past 8 months, the patient has had some intermenstrual spotting. The bleeding initially occurred for 1-2 days between menstrual cycles but now has become progressively prolonged and heavy, and she now bleeds almost daily. The patient previously used a progestin-releasing intrauterine device for contraception, but had it removed 2 years ago when her husband had a vasectomy. She takes no daily medications and does not use tobacco, alcohol, or illicit drugs. Vital signs are normal. BMI is 38 kg/m2. Bimanual examination shows no abnormalities. On speculum examination, dark-red blood is seen at the cervical os. There are no cervical or vaginal lesions. An endometrial biopsy reveals endometrial hyperplasia. Which of the following is the most likely cause of this patient's condition?
(Multiple Choice)
4.9/5 (85)
(85) A 30-year-old primigravida at 8 weeks gestation comes to the emergency department due to pelvic pain. The patient has had intermittent right lower quadrant pain for the last week, but yesterday it became constant and severe with associated nausea and vomiting. She takes a prenatal vitamin daily and has no chronic medical conditions. Blood pressure is 128/82 mm Hg and pulse is 104/min. BMI is 23 kg/m2. Ultrasound shows an intrauterine fetal pole measuring 8 weeks gestation with cardiac motion at 160/min. There is free fluid in the pelvis, and the right ovary is enlarged and has decreased blood flow on Doppler. The patient undergoes emergency laparoscopy for ovarian torsion, and the right ovary containing the corpus luteum is removed due to necrosis of the ovary. Postoperative ultrasound shows positive intrauterine fetal cardiac activity and free fluid in the pelvis. Which of the following is the best next step in management of this patient?
(Multiple Choice)
5.0/5 (78)
(78) A 25-year-old woman, gravida 1 para 0, at 10 weeks gestation comes to the office due to a malodorous vaginal discharge. She is sexually active, has no chronic medical conditions, and has no medication allergies. Vital signs are normal. BMI is 26 kg/m2. Fetal heart tones are 160/min. Speculum examination reveals a thin, gray discharge that coats the vaginal walls, but no erythema or edema is present on the vaginal walls or the vulva. There is no cervical or adnexal tenderness. A saline wet mount examination reveals numerous epithelial cells coated with bacteria. No white blood cells or motile organisms are seen. Which of the following is the best management option for this patient?
(Multiple Choice)
4.8/5 (80)
(80) A 59-year-old postmenopausal woman comes to the office for evaluation of breast tenderness. The patient first noticed intermittent breast tenderness 4 months ago, which at first was relieved with ibuprofen, but for the past several weeks the tenderness has occurred daily. She has had no breast masses or nipple discharge. The patient has also noticed an increase in her weight, particularly around the abdomen, despite not being able to eat as much. She went through menopause 5 years ago. Mammogram history is normal, including one performed earlier this year. The patient has no chronic medical conditions and has had no previous surgeries. There is no family history of breast, ovarian, or endometrial cancer. Vital signs are normal. BMI is 24 kg/m2. Breast examination shows bilateral, diffuse fibrocystic changes. The abdomen is distended, and a large right lower quadrant mass is palpable. Pelvic ultrasound reveals a 12-cm complex right ovarian mass with solid components and multiple septations, a slightly enlarged uterus, and a 9-mm endometrial stripe. Which of the following tumor markers is most likely to be elevated in this patient?
(Multiple Choice)
4.7/5 (72)
(72) A 57-year-old woman comes to the office for evaluation of vaginal pruritus, pain with urination, and increased urinary frequency. The patient's symptoms have been present for several months but have intensified recently. Her husband passed away 4 years ago, and the patient had not been sexually active until 6 months ago with a new partner. She has had some pain with intercourse and has tried over-the-counter, water-based lubricants with little relief. Her last menstrual period was 7 years ago. She has poorly controlled type 2 diabetes mellitus with a recent hemoglobin A1c of 8.4%. BMI is 28 kg/m2. Vital signs are normal. Pelvic examination shows thin vulvar skin with reduced elasticity. The vagina appears pale, dry, and has multiple areas of petechiae. There is minimal clear discharge in the vault. Vaginal pH is 6.5. Urinalysis is normal. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (63)
(63) A 34-year-old woman, gravida 3 para 2, at 33 weeks gestation comes to the emergency department due to continued leakage of fluid. The patient reports intermittent vaginal spotting but has had no contractions. Fetal movement is normal. Her prenatal course has been complicated by group B Streptococcus bacteriuria treated in the first trimester. The patient has no other chronic medical conditions or previous surgeries. Temperature is 39.2 C (102.5 F), blood pressure is 90/56 mm Hg, and pulse is 109/min. Fundal height measures 30 cm. Speculum examination shows pooled fluid in the posterior fornix that turns nitrazine paper blue; the cervix appears visibly closed. A ferning pattern is visualized on microscopy. Fetal heart monitoring shows a rate of 170/min with moderate variability. Tocometry shows no contractions. A transabdominal ultrasound reveals a fetus in transverse lie; the single deepest vertical pocket of amniotic fluid is 1 cm. Which of the following is an indication for delivery in this patient?
(Multiple Choice)
4.8/5 (88)
(88) A 26-year-old woman comes to the office due to insomnia and fatigue. She is accompanied by her husband, who is concerned that his wife is exhausted and seems overwhelmed by the responsibilities of being a new mother. The patient had an uncomplicated vaginal delivery and took an extended maternity leave to care for their daughter, who is now 3 months old. The patient feels very tired because she awakens early at 4:00 AM and is unable to return to sleep. She frequently lies awake in bed and worries that she is a bad mother. During the day she has little energy and forces herself to take showers and care for the baby. Physical examination is unremarkable. The patient appears sad but says, "I'm sure I would feel better if I could just get some rest." Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (86)
(86) A 32-year-old woman at 14 weeks gestation comes to the office for an initial prenatal care visit. She has had no headaches, chest pain, abdominal pain, or lower extremity swelling. Medical history is significant for type 1 diabetes mellitus managed with multiple daily insulin injections. Blood pressure is 154/94 mm Hg and pulse is 86/min. Fetal heart tones are 152/min on Doppler ultrasonography. Laboratory results are as follows:  Urinalysis reveals 2+ protein but no red or white blood cells. Which of the following is the most likely direct cause of this patient's proteinuria?
 (Multiple Choice)
4.8/5 (64)
(64) A 23-year-old primigravid woman comes to the labor and delivery department due to decreased fetal movement for the past few days. She also has some regular, nonpainful uterine contractions but no vaginal bleeding or leakage of fluid. The patient has had no prenatal care but is estimated to be at 38 weeks gestation by her last menstrual period. She has no known medical conditions but has had fatigue and joint stiffness for the past month. Temperature is 99.1 F (37.2 C), blood pressure is 128/86 mm Hg, and pulse is 94/min. Fundal height is 37 cm. Physical examination shows an erythematous, confluent facial rash. The neck is supple. Cardiopulmonary examination is normal. The uterus is nontender. Fetal heart rate tracing is shown in the following exhibit. 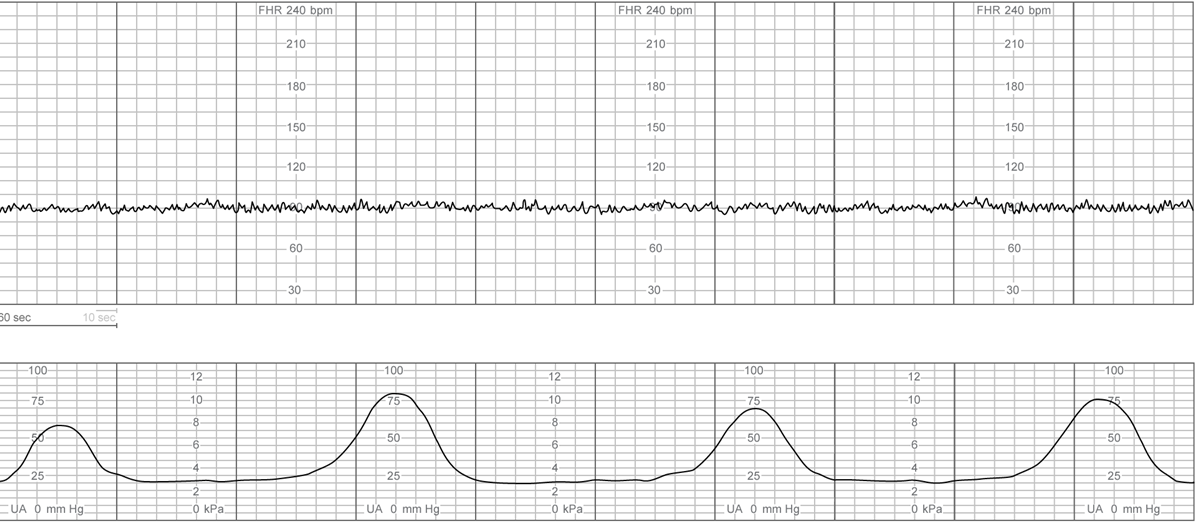 Which of the following is the most likely cause of this patient's fetal heart rate tracing?
 (Multiple Choice)
4.7/5 (69)
(69) A 16-year-old girl comes to the office for evaluation of excessive facial hair. The patient has used multiple creams and makeup over the last year but is still embarrassed by the facial hair. She also has had irregular menstrual cycles since menarche at age 12; her last menstrual period was 6 weeks ago. She is an avid runner. Blood pressure is 122/70 mm Hg and pulse is 87/min. BMI is 20 kg/m2. Physical examination shows hirsutism. The patient has normal external female genitalia; the rest of the examination is unremarkable. Urine pregnancy test is negative. Laboratory results are as follows:  Serum glucose and electrolytes are normal. Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.9/5 (85)
(85) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)