



 Chat with AI
Exam 4: Surgery

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 74-year-old man is evaluated for acute agitation beginning 20 minutes after arrival to the post-anesthesia care unit (PACU) following abdominal surgery. He was admitted 5 days ago for a small bowel obstruction and failed nonoperative management. The patient received lorazepam for preoperative anxiety, and lysis of adhesions was performed under general anesthesia. His immediate postoperative course was uneventful, and he was responsive and following commands shortly after extubation and on arrival to the PACU. Medical history is significant for posttraumatic stress disorder. Temperature is 37.2 C (99 F), blood pressure is 142/86 mm Hg, pulse is 98/min, and respirations are 18/min. The patient is anxious, confused, and restless in bed. He now responds only to questions in Spanish despite being fluent in English minutes before. His muscles seem tense, but screening neurologic examination reveals no focal abnormalities. Arterial blood gas shows PaO2 of 86 mm Hg and PaCO2 of 38 mm Hg. Point-of-care electrolytes, glucose, and hematocrit are all normal. What is the most appropriate initial management of this patient?
(Multiple Choice)
4.9/5  (82)
(82) A 72-year-old man comes to the emergency department due to a weeklong history of malaise, fever, dry cough, shortness of breath, and pain in the right upper abdomen. Two months ago, the patient was diagnosed with unresectable adenocarcinoma of the head of the pancreas. He refused chemotherapy, and a palliative biliary stent was placed. Temperature is 38.4 C (101.1 F), blood pressure is 110/64 mm Hg, pulse is 108/min, and respirations are 20/min. Physical examination reveals decreased breath sounds at the right lung base and guarding and tenderness in the right upper quadrant. Laboratory results are as follows:  Chest x-ray reveals a pleural effusion on the right side. In addition to intravenous fluids and empiric antibiotics, which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (81)
(81) A 62-year-old woman is brought to the emergency department due to an acute right-sided headache, ocular pain, and nausea. She was watching television in the evening after dinner when the symptoms began; initial treatment with cold compresses and acetaminophen was ineffective. The patient then developed decreased vision in the right eye and called for an ambulance. On examination, she appears uncomfortable and has episodic retching. The right eye has red conjunctival flushing; the right pupil is mid-dilated and nonreactive to light. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (99)
(99) A 50-year-old man undergoes surgery for a peptic ulcer perforation. The patient's early postoperative course is complicated by fever and hypotension, which are treated with broad-spectrum antibiotics and intravenous fluid support. He recovers until postoperative day 7, when he develops nausea, abdominal cramps, and profuse watery diarrhea. The patient is not currently on antibiotics. Temperature is 38.9 C (102 F), blood pressure is 112/70 mm Hg, pulse is 120/min and regular, and respirations are 18/min. The lungs are clear to auscultation. Abdominal examination shows a well-healing midline scar and no distension. Tenderness is present in the left lower quadrant. Testing of stool for occult blood is negative. Laboratory results are as follows: Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.7/5 (63)
(63) A 34-year-old man is brought to the emergency department after being shot in the right thigh during an attempted robbery. The patient is awake, alert, and in moderate distress. Blood pressure is 101/49 mm Hg and pulse is 122/min. Records indicate that his last tetanus vaccine was a year ago. Physical examination shows a gunshot entry wound on the anteromedial upper right thigh with an exit wound on the lateral thigh. There is a hematoma at the entry site but no active bleeding from either wound. The right lower extremity is cool to the touch and distal pulses are feeble. Radiography of the lower extremity shows no fracture. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.7/5 (69)
(69) A 75-year-old man comes to the clinic due to a gradual onset of blurred vision in both eyes and difficulty reading over the past 2 months. He also has difficulty driving at night and reports seeing halos around bright lights. Medical history is notable for longstanding diabetes and hypertension. The patient has a 40 pack-year smoking history. Vital signs are normal. Corrected vision is OD (right eye) 20/80 and OS (left eye) 20/100 with normal findings on visual field testing. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.7/5 (74)
(74) A 61-year-old woman comes to the office due to 3 months of constipation and pain in the left lower abdomen. The pain is crampy, continuous, and nonradiating and is not affected by bowel movements or meals. The patient reports hard, pelletlike stools and early satiety but no vomiting, hematochezia, melena, or weight changes. The patient does not have a history of chronic constipation. She is postmenopausal and has not had a period in >5 years. Medical history is significant for hypertension. Family history is unremarkable, and the patient does not use tobacco or alcohol. Temperature is 37.5 C (99.5 F), blood pressure is 145/87 mm Hg, pulse is 80/min, and respirations are 12/min. No scleral icterus or palpable lymphadenopathy is present. Cardiopulmonary examination is unremarkable. The abdomen is mildly distended and tender to palpation in the left lower quadrant without rebound or guarding. Rectal examination is unremarkable and negative for fecal occult blood. Colonoscopy results are unremarkable. Which of the following is the best next step in management?
(Multiple Choice)
4.9/5 (76)
(76) A 65-year-old man comes to the office with 2 weeks of dysuria and turbid, foul-smelling urine. He has also noticed air bubbles while urinating. He has no fever, hematuria, hematochezia, weight loss, or pelvic or flank pain. The patient has a long history of straining on urination and a weak urine stream and is currently being treated for benign prostatic hyperplasia. Four weeks ago, he was seen in the emergency department for persistent lower quadrant abdominal pain and diagnosed with acute diverticulitis. He was discharged on an oral antibiotic. Current temperature is 98.7 F (37.1 C), blood pressure is 132/84 mm Hg, and pulse is 72/min. The abdomen is soft and mildly tender in the left lower quadrant. There is no costovertebral angle tenderness. Rectal examination shows a smooth, enlarged, nontender prostate. Laboratory studies show normal complete blood count and serum chemistries, including serum creatinine. Urinalysis is positive for numerous white cells and bacteria. Urine culture grows Escherichia coli, Proteus mirabilis, and Klebsiella pneumoniae. Which of the following is the most likely cause of this patient's current condition?
(Multiple Choice)
4.8/5 (64)
(64) A 24-year-old bicycle courier is brought to the emergency department after he was struck by a car. The patient was thrown approximately 6.1 m (20 ft) through the air and was initially unconscious when other eyewitnesses reached him. On arrival, blood pressure is 84/54 mm Hg, pulse is 130/min, and respirations are 28/min. Oxygen saturation is 88% on 100% oxygen via a nonrebreather mask. The patient appears extremely anxious and in respiratory distress. When he sees the trauma team preparing supplies for intubation, the patient says, "No, no tube!" However, soon afterward, the patient loses consciousness while resuscitative efforts and trauma survey examination are ongoing. Which of the following is the most appropriate course of action?
(Multiple Choice)
4.8/5 (66)
(66) A 60-year-old man is evaluated for a right lung mass, which was discovered on a chest x-ray performed one month ago due to persistent cough. He has had no chest pain, dyspnea, or hemoptysis. The patient has no other medical conditions and takes no medications. He is an ex-smoker with a 20-pack-year history. Physical examination shows clear lungs, normal heart sounds, and no lymphadenopathy or abdominal organomegaly. CT scan shows a 4-cm mass in the right oblique fissure with no enlarged lymph nodes. Bronchoscopy-guided biopsy reveals squamous cell carcinoma. A subsequent PET scan shows no metastatic lesions, and a right pneumonectomy is planned. Which of the following is likely to provide the best assessment of postoperative pulmonary morbidity in this patient?
(Multiple Choice)
4.9/5 (78)
(78) A 50-year-old man comes to the office due to a few weeks of fatigue and back pain. The patient has a history of hypertension and major depressive disorder. He does not use alcohol or intravenous drugs. The patient emigrated from Vietnam with his family when he was a child. BMI is 21 kg/m2. Vital signs are within normal limits. Physical examination reveals temporal wasting. Cardiopulmonary examination is normal, and no abdominal masses or tenderness is present. Spine palpation reveals significant pain over a mid-lumbar spinous process. There are no palpable testicular lesions, and digital rectal examination reveals a smooth, normal-sized prostate. Laboratory results are as follows:  Spine imaging shows osseous blastic and lytic lesions in multiple vertebral bodies. Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (76)
(76) A 40-year-old man is evaluated in the hospital after being admitted for acute alcohol-induced pancreatitis 24 hours ago. He has been receiving aggressive intravenous hydration and pain control. Over the past 2 hours, the patient has become increasingly restless and now reports difficulty breathing and abdominal distension. Blood pressure is 80/60 mm Hg, pulse is 122/min, and respirations are 28/min. Heart and lung sounds are normal. The abdomen is significantly distended and tense. Bowel sounds are decreased. Bilateral lower extremity and flank edema are present. Chest x-ray reveals basilar atelectasis but no other infiltrates. His urine output has markedly decreased over the past 2 hours. Which of the following pathophysiologic changes are most likely present in this patient at this time compared to a few hours earlier?
(Multiple Choice)
4.9/5 (89)
(89) A previously healthy, 36-year-old man is hospitalized following a motor vehicle collision. He sustained a concussion and fracture of the right femur, and open reduction and internal fixation of the fracture are planned. Medical history is insignificant, and the patient takes no medications for chronic conditions. Blood pressure is 150/90 mm Hg and pulse is 70/min. Oxygen saturation is 98% on room air. BMI is 24 kg/m2. Laboratory results are as follows:  Finger-stick glucose measurement is 156 mg/dL. Hemoglobin A1c is 5.5%. Which of the following is the best next step in management of this patient's glucose values?
 (Multiple Choice)
4.9/5 (80)
(80) A 35-year-old woman is being evaluated for a breast mass first noticed during a routine physical examination last week. The patient had bilateral reduction mammoplasty for mammary hyperplasia 2 years ago. She takes no medications and has no allergies; her paternal grandmother died at age 65 of breast cancer. Breast examination shows a fixed mass palpated in the upper outer quadrant of the right breast. Mammography shows a 3 x 3-cm spiculated mass with coarse calcifications in the upper outer quadrant of the right breast. Ultrasonography of the breast shows a hyperechoic mass. Core biopsy shows foamy macrophages and fat globules, and the mass is excised with concordant pathologic findings. Which of the following is the most appropriate course of action in management of this patient?
(Multiple Choice)
4.8/5 (92)
(92) A 54-year-old man comes to the office after a year of progressive fatigue and frequent loose stools. He describes voluminous, foul-smelling stools that float and are difficult to flush. The patient has lost about 9 kg (20 lbs) in the past 6 months. He was hospitalized on multiple occasions several years ago for epigastric pain radiating to the back, nausea, and vomiting. Lately, the patient has had intermittent episodes of similar pain lasting for 15-30 minutes after meals. He has had no hematemesis, hematochezia, or melena. The patient stopped drinking alcohol several years ago and does not use tobacco or recreational drugs. Temperature is 37 C (98.6 F), blood pressure is 118/80 mm Hg, and pulse is 78/min. BMI is 19.5 kg/m2. Abdominal examination shows epigastric tenderness on deep palpation. Bowel sounds are normal. Which of the following is most likely to improve this patient's symptoms?
(Multiple Choice)
4.8/5 (85)
(85) A 56-year-old woman comes to the office for evaluation of a leg ulcer. The patient bumped her left leg on a chair 2 weeks ago and noticed painful papules at the injury site several days later. The lesions rapidly enlarged and opened, causing worsening pain and drainage. The ulcer progressively enlarged despite the use of topical antiseptics. The patient has a history of rheumatoid arthritis and does not use tobacco, alcohol, or illicit drugs. Temperature is 37.2 C (99 F), blood pressure is 130/78 mm Hg, and pulse is 86/min. Physical examination shows a tender ulcer on the lower left extremity, as shown in the exhibit. 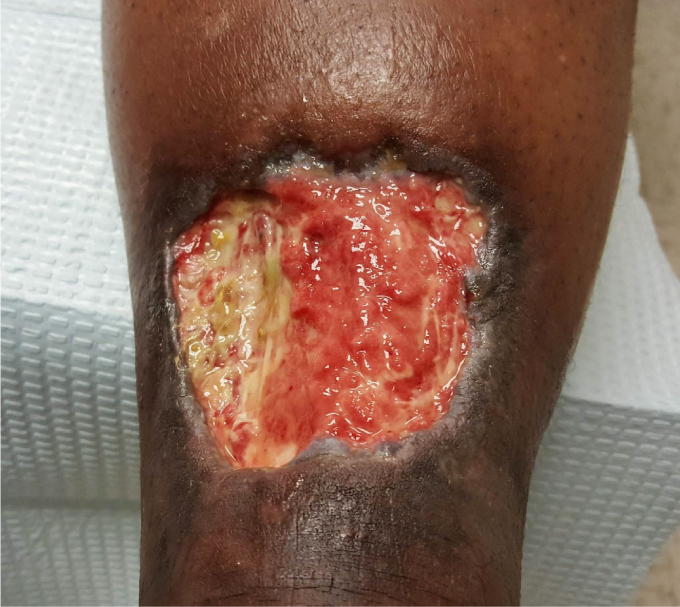 There are no other lesions. Which of the following is the most likely cause of this patient's skin condition?
 (Multiple Choice)
4.8/5 (68)
(68) A 32-year-old woman is brought to the emergency department an hour after developing acute-onset, right upper quadrant abdominal pain followed by syncope. The patient works at her family farm and felt well prior to the onset of these symptoms. She has no chronic medical conditions. She is sexually active and uses combined estrogen-progestin oral contraceptives. She does not use tobacco, alcohol, or illicit drugs. Temperature is 38.1 C (100.6 F), blood pressure is 80/50 mm Hg, pulse is 120/min, and respirations are 20/min. Oxygen saturation is 95% on room air. The patient appears anxious and pale. Examination shows abdominal distention, diffuse abdominal tenderness, and tender hepatomegaly. Bowel sounds are decreased. Extremities are cold, and capillary refill is delayed. Laboratory results are as follows:  Abdominal ultrasound of the right upper quadrant shows a solid liver mass and free fluid in the abdomen. Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (76)
(76) A 62-year-old man comes to the office due to increasing discomfort and bulging at the right groin. He was previously diagnosed with a direct inguinal hernia but had no operative repair. The patient recently had acute bronchitis with an incessant dry cough, which caused the hernia to enlarge. He has had no abdominal pain, nausea, vomiting, or constipation. Medical history includes hypothyroidism, seasonal allergy, and several previous episodes of sinusitis. Medications are levothyroxine and a glucocorticoid nasal spray. The patient smokes a pack of cigarettes daily and drinks alcohol occasionally. Vital signs are within normal limits. BMI is 24 kg/m2. Physical examination shows a nontender, easily reducible groin mass. Surgical hernia repair is planned. Which of the following most increases the risk for postoperative wound infection in this patient?
(Multiple Choice)
4.9/5 (80)
(80) A 28-year-old man is admitted to the intensive care unit after a motor vehicle collision. The patient was intubated and received volume resuscitation at the scene. The patient sustained bladder injury, open fractures of the tibia and fibula bilaterally, a complicated pelvic ring injury, and fractures of the right 4th-7th ribs. No head or spinal injuries were detected. Over the course of 8 days, the patient undergoes laparotomy and daily surgeries to address extremity fractures, which require the patient to remain supine and intubated until all the surgeries are completed. On day 9, the respiratory therapist notes 4 hours of increasing secretions and worsening oxygenation: the patient requires an increase in FiO2 from 30% to 70% in order to maintain oxygen saturation of 92%. Vital signs reveal new-onset tachycardia. Temperature is 39.2 C (102.6 F), blood pressure is 125/80 mm Hg, pulse is 125/min, and respirations are 22/min. Portable chest radiograph reveals new right and left lower lobe infiltrates with a left-sided pleural effusion. What is the most likely diagnosis?
(Multiple Choice)
4.8/5 (83)
(83) A 65-year-old man comes to the office due to 4 weeks of persistent epigastric pain and nausea. The pain is constant and does not improve or worsen with activities, position, or diet. The patient lost approximately 4.5 kg (9.9 lb) over this period. He has no fever, vomiting, constipation, or diarrhea. He was diagnosed with type 2 diabetes mellitus 6 months ago, which is controlled with a low-carbohydrate diet. The patient has never had surgery and has no other chronic medical conditions. He has a 45-pack-year history of smoking. He does not use alcohol or illicit drugs. Temperature is 36.5 C (97.7 F), blood pressure is 122/72 mm Hg, pulse is 68/min, and respirations are 16/min. BMI is 24 kg/m2. Mucous membranes are moist. No lymphadenopathy is present in the cervical or axillary chains. Bowel sounds are present, and the abdomen is soft with mild epigastric tenderness to deep palpation. No hepatosplenomegaly or shifting dullness is present. The remainder of the examination is normal. Complete blood count, serum chemistry, and liver function studies is all normal except a fasting blood sugar of 130 mg/dL. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (88)
(88) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)