



 Chat with AI
Exam 4: Surgery

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 74-year-old man comes to urgent care due to persistent back pain at L1 to L4 spinal levels. The patient's symptoms started suddenly while he was having breakfast yesterday. The pain is constant, deep, and dull. He reports no trauma or having had similar pain previously. The symptoms do not change with climbing stairs or lumbar flexion/extension activities. The patient had difficulty falling asleep last night because of increased pain in his lower back. Medical history is significant for hypertension. The patient has a 40 pack-year smoking history, but he does not use alcohol. Medications include amlodipine and enalapril. He is afebrile; blood pressure is 140/90 mm Hg and pulse is 88/min. BMI is 27 kg/m2. Physical examination shows normal range of motion of the spine without point tenderness. Straight leg raise test is normal. The abdomen is soft. Mild tenderness is present with deep palpation from the epigastric to supraumbilical regions. Bowel sounds are normal. Femoral, popliteal, and pedal pulses are symmetric. Erythrocyte sedimentation rate is normal. X-ray of the spine reveals no vertebral abnormalities, but prevertebral calcifications are present. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5  (82)
(82) A 55-year-old man is brought to the emergency department due to a gunshot wound to the left abdomen. He undergoes an exploratory laparotomy involving a partial small bowel resection and a left nephrectomy. His postoperative hemoglobin is 10.4 mg/dL. The patient has no other medical history and takes no medications. Recovery is uneventful until postoperative day 4 when he develops fever, tachypnea, and shortness of breath. The patient is lethargic but responsive. Temperature is 38.9 C (102 F), blood pressure is 75/50 mm Hg, pulse is 110/min and regular, and respirations are 22/min. There is no jugular venous distention. Lung auscultation reveals crackles at the right lung base. There are no cardiac murmurs. Abdominal examination shows a well-healing abdominal wound and a soft, nondistended abdomen. His urine output over the last 12 hours is 100 mL. Laboratory results are as follows: Broad-spectrum antibiotics are started. Which of the following additional treatments is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (75)
(75) A 65-year-old man comes to the office for evaluation of new-onset pain in the right knee. The patient first noticed the pain 3 weeks ago after a long hike in the mountains. The pain has not improved with acetaminophen, and he is now unable to sleep because of it. He has also had intermittent low-grade fevers. The patient has Paget disease of bone, which was diagnosed 10 years ago, and type 2 diabetes mellitus. He drinks alcohol socially but does not use tobacco or illicit drugs. Temperature is 37.2 C (99 F), blood pressure is 120/70 mm Hg, and pulse is 80/min. BMI is 23 kg/m2. The right knee has diffuse soft tissue swelling and a small effusion with no surrounding erythema. The distal aspect of the thigh is tender to palpation. X-ray of the right knee reveals medullary and cortical bone destruction with lucent areas and a surrounding periosteal elevation along the distal femur. Which of the following is the most likely cause of this patient's knee pain?
(Multiple Choice)
4.9/5 (94)
(94) An 84-year-old woman with Alzheimer dementia is brought to the emergency department for evaluation after refusing to get out of bed. She has been known to wander the halls at her facility, and a nursing aide reported finding her on the floor next to her bed earlier that day. Vital signs are within normal limits. On examination, the patient is in pain. Her right leg appears shorter than her left. She is able to wiggle her toes but has significant external rotation of the right lower extremity compared with the left. There is no evidence of head trauma and the lower leg compartments are soft. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (86)
(86) A 65-year-old woman comes to the hospital due to vague left flank pain, fatigue, and sweats for 12 days. For the past 2 days she has also had fever and nausea. The patient was treated with oral antibiotics for a urinary tract infection 4 weeks ago and has had no dysuria since, but she has lost 2.3 kg (5 lb) in the interim. Other medical conditions include type 2 diabetes mellitus and hypertension. The patient smokes a pack of cigarettes daily and uses alcohol occasionally. Temperature is 38.7 C (101.7 F), blood pressure is 130/80 mm Hg, pulse is 94/min, and respirations are 16/min. Cardiopulmonary examination is normal. Marked left flank tenderness is present. Laboratory results are as follows:  Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.8/5 (72)
(72) A 78-year-old woman comes to the office due to worsening clumsiness and weakness of her hands for the past several months. The patient has had difficulty performing daily activities such as buttoning shirts or tightly holding garden tools. She also reports stiffness in her legs and neck. Medical history is significant for hypertension and osteoarthritis. Physical examination shows bony outgrowth at distal and proximal interphalangeal joints. There is wasting of the intrinsic hand muscles, and grip strength is decreased bilaterally. Neck flexion elicits an electric shock-like sensation down the patient's back. Ankle reflexes are 3+ bilaterally. Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (67)
(67) A 27-year-old painter comes to the emergency department due to severe pain in his left hand. Towards the end of the workday yesterday, he was using an industrial sprayer to paint a deck when he accidentally placed his left index finger over the sprayer nozzle, injecting paint into the finger. The patient initially had only localized soreness in the finger, but he awoke in the middle of the night with severe pain. The patient has no chronic medical conditions, and immunizations including tetanus are up to date. Blood pressure is 144/86 mm Hg, pulse is 100/minute, respirations are 18/minute, and temperature is 37.3 C (99.1 F). On examination, the patient's left index finger, hand, and forearm are swollen. There is a 4 mm puncture wound on the flexor surface of the left index finger near the proximal interphalangeal joint. There is tenderness along the flexor surface of the entire digit, and passive extension of the index finger causes severe pain radiating up the arm. Capillary refill is <2 seconds in the hand and all digits. Which of the following is the best next step in management of this patient's condition?
(Multiple Choice)
4.8/5 (72)
(72) A 65-year-old man is brought to the hospital due to sudden-onset shortness of breath. He could not lie flat due to breathing difficulty. There is no associated chest pain. Six months ago, the patient was hospitalized with similar symptoms and responded well to diuretic therapy. Medical history is significant for hypertension, coronary artery disease, and transient ischemic attacks. The patient has undergone several percutaneous coronary interventions for stable angina in the past and had a right carotid endarterectomy 2 years ago. He has good adherence to his daily medication regimen but smokes a pack of cigarettes daily. Blood pressure is 210/100 mm Hg, pulse is 104/min and regular, and respirations are 22/min. Oxygen saturation is 86% on room air. Examination shows distended neck veins and bilateral lung crackles. The abdomen is soft, obese, and nontender. The extremities have no edema. Laboratory results are as follows:  Cardiac troponin I levels are not elevated. ECG shows sinus tachycardia with left ventricular (LV) hypertrophy. Echocardiogram reveals LV hypertrophy, preserved LV ejection fraction, and no regional wall motion abnormalities. The patient improves markedly with diuresis and antihypertensive therapy. Which of the following is the next best step in management?
 (Multiple Choice)
4.9/5 (70)
(70) A 68-year-old man comes for outpatient follow-up after recent coronary artery bypass grafting surgery. He describes anterior chest "clicking" and "shifting" when he bends or moves his upper extremities. The patient has no chest pain, dyspnea, fever, chills, or abdominal pain. He underwent uncomplicated surgery with internal thoracic artery harvesting 6 days ago for severe coronary artery disease. The patient is afebrile, and vital signs are within normal limits. Medical history includes diabetes mellitus, obesity, and chronic obstructive pulmonary disease. Examination reveals a midsternal wound that is clean with well-approximated sutures and minimal serous discharge at the lower edge but without erythema. On palpation the sternum appears to be rocking and clicking with patient coughing. Which of the following is the best management for this patient?
(Multiple Choice)
4.8/5 (88)
(88) A 48-year-old woman comes to the hospital for elective cholecystectomy to treat symptomatic cholelithiasis. She has had increasingly severe, intermittent biliary colic pain, and ultrasonography revealed several gallstones. The patient has a history of hypertension and obesity. Preoperative medical evaluation and laboratory testing were unremarkable. The patient receives cefazolin for surgical site infection prophylaxis, and surgery is performed under general anesthesia. A Foley catheter is placed preoperatively. The planned laparoscopic procedure is converted to open approach due to difficult anatomy; otherwise, the surgery is uneventful with minimal blood loss. Two hours later, the patient is noted to have a temperature of 38.9 C (102 F). Her blood pressure is 140/85 mm Hg, pulse is 104/min, and respirations are 18/min. The patient is awake and alert but reports mild pain at the surgical site. A right-sided internal jugular central venous catheter, which was placed in the operating room, is in a good position with no redness at the insertion site. The lungs are clear on auscultation, and heart sounds are normal. The surgical site is clean with minimal serosanguinous discharge. There is no lower extremity edema. Current laboratory results are as follows: 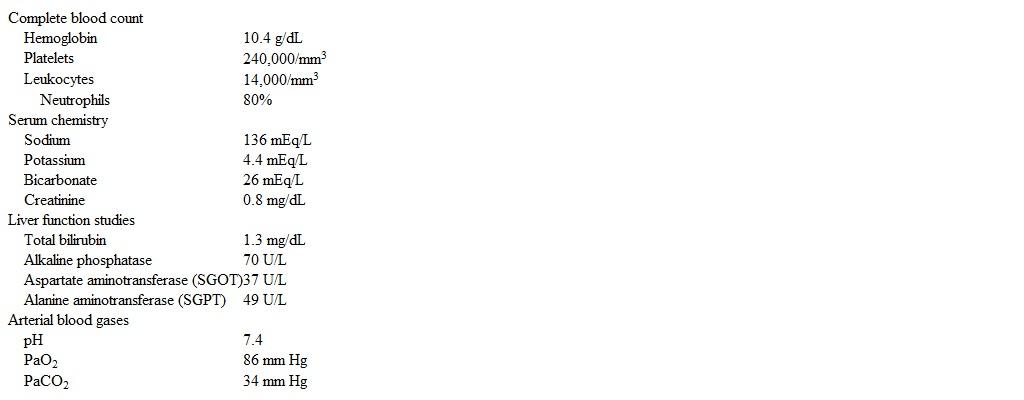 Chest x-ray reveals decreased lung volumes and small areas of subsegmental thickening bilaterally. Which of the following is the most appropriate next step in management of this patient's fever?
 (Multiple Choice)
4.8/5 (92)
(92) A 28-year-old man is brought to the emergency department due to a construction site accident in which a heavy concrete slab fell on his legs. The patient was trapped from the waist down for about 15 minutes until other workers were able to rescue him. He sustained no injury to the head or upper torso and did not lose consciousness. The patient has no significant medical history and takes no medications. He drinks 1 or 2 beers daily but does not use tobacco or illicit drugs. Blood pressure is 140/90 mm Hg, and pulse is 110/min. Bilateral breath sounds are equal and normal. Heart sounds are not muffled. The abdomen is soft and nontender. There are obvious deformities, abrasions, and lacerations on both lower limbs. Radiographs reveal multiple bilateral lower extremity fractures. After the patient is cleared of other major trauma, he is taken for surgical stabilization and fixation of the lower extremity fractures. Succinylcholine is considered for rapid-sequence intubation. With the use of succinylcholine, this patient is at greatest risk for which of the following?
(Multiple Choice)
4.8/5 (82)
(82) A 65-year-old tennis player comes to the office due to worsening right heel pain for the past 4 weeks. In the last week, she had to end several practices early because the pain had become increasingly unbearable toward the end of the day. The patient has had no acute trauma to the foot. She has a history of osteopenia for which she takes calcium and vitamin D. On examination, there is significant tenderness over the medioplantar region of the right heel, worsened by passive dorsiflexion of the big toe. The ankle has full range of active motion without pain. Sensation of the foot is intact. Foot x-ray reveals a decrease in bone density and a calcaneal bone spur but no fracture. Which of the following is the best initial treatment of the patient's condition?
(Multiple Choice)
4.7/5 (78)
(78) A 63-year-old man comes to the emergency department due to left leg pain. The patient typically has pain in both legs after walking a couple of blocks, but several hours ago, severe left leg pain suddenly developed while he was resting. He reports numbness in the left leg, and he is also experiencing intermittent palpitations. Medical history includes hypertension and hyperlipidemia. The patient has smoked a pack of cigarettes daily for 45 years. Blood pressure is 130/80 mm Hg, and pulse is 116/min and irregular. On examination, hair is sparse on both legs. Distal pulses are absent on the left and diminished on the right. Sensation to light touch is decreased on the dorsum of the left foot and leg, and ankle dorsiflexion is weaker on the left. Which of the following is the best first step in management of this patient?
(Multiple Choice)
4.8/5 (81)
(81) A 65-year-old man comes to the office due to 4-week history of weakness and vague postprandial epigastric pain. Medical history is insignificant. He does not take any medications. The patient smokes 1 pack of cigarettes daily and drinks alcohol occasionally. Fecal occult blood test is positive. Gastroduodenoscopy shows an antral ulcer. Four of seven biopsies taken from the margins of the ulcer are consistent with adenocarcinoma. Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.8/5 (73)
(73) A 73-year-old man comes to the physician because of right anterior thigh pain that is worse with walking. He has a history of stable angina, hypertension, hypercholesterolemia, and COPD with periodic exacerbations. He takes ipratropium, aspirin, metoprolol and pravastatin. He smokes 2 packs a day and drinks alcohol occasionally. Physical examination shows a small pulsatile mass in the right groin area. Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (76)
(76) A 52-year-old woman comes to the emergency department for rectal pain that started 2 hours ago. The pain is described as severe, burning, and exacerbated while sitting. Medical history is significant for chronic idiopathic constipation, for which she takes a fiber supplement. The patient has 4 children, all of whom were vaginally delivered. Family history is unremarkable. She does not use tobacco, alcohol, or illicit drugs. Temperature is 37.2 (99 F), blood pressure is 138/84 mm Hg, and pulse is 90/min. On physical examination, the patient appears in moderate distress due to pain. The abdomen is soft, nondistended, and nontender. Bowel sounds are normoactive. Anal examination reveals a small, exquisitely tender, bluish lesion at the anal verge. Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (88)
(88) A 49-year-old woman comes to the emergency department for evaluation of back pain. The patient underwent a total abdominal hysterectomy and bilateral salpingo-oophorectomy for ovarian cancer 1 week ago. She had an uncomplicated postoperative course, with her Foley catheter removed on postoperative day 2. She was discharged home on postoperative day 4. The patient noted some right-sided back pain after surgery that improved with pain medications. However, the pain has become progressively more severe and is no longer responding to pain medications. The pain does not radiate, and now she has associated nausea and vomiting. Temperature is 37.2 C (99 F), blood pressure is 128/72 mm Hg, and pulse is 92/min. BMI is 38 kg/m2. The abdominal incision is closed and has no erythema, drainage, or fluctuance. There is mild right costovertebral angle tenderness; the left side is nontender. Serum creatinine is 0.8 mg/dL. Catheterized urinalysis is normal. Which of the following is the most likely cause of this patient's pain?
(Multiple Choice)
4.8/5 (75)
(75) A 25-year-old man is brought to the emergency department after a high-speed motor vehicle collision. The patient was restrained, but there was prolonged extrication due to extensive vehicular damage. Supplemental oxygen and intravenous fluids were administered on the way to the hospital. On arrival, the patient is alert and can speak but appears to have increased work of breathing. Blood pressure is 110/66 mm Hg, pulse is 120/min, and respirations are 34/min. Pulse oximetry is 88% on 10 L oxygen via nonrebreather mask. The trachea is midline and the neck veins are flat. There are several chest wall and abdominal bruises. A portion of the anterior left chest moves inward during inspiration. Breath sounds are diminished in the anterior left lung but normal elsewhere. The abdomen is nondistended, soft, and nontender to palpation. The left thigh is deformed, but compartments are soft and distal pulses are intact. There are no focal neurologic deficits. Which of the following is the most likely cause of this patient's hypoxia?
(Multiple Choice)
4.9/5 (86)
(86) An 18-year-old woman is brought to the emergency department with severe vomiting, diarrhea, and dizziness that started this morning. Three days ago, she had nasal bleeding that required anterior packing in the emergency department. Yesterday, she had pain and a sensation of pressure under her left eye and scant blood-tinged nasal discharge. The pain was relieved by acetaminophen and ibuprofen. The patient, who has no sick contacts, has a history of asthma and allergic rhinitis. Her last menstrual period was 3 weeks ago. She does not use tobacco, alcohol, or illicit drugs. Her temperature is 38.9° C (102.2° F), blood pressure is 90/60 mm Hg supine and 66/45 mm Hg standing, pulse is 120/min, and respirations are 23/min. She appears alert but restless. On examination, there are diffuse, confluent erythematous macules on her trunk and extremities. The oropharynx appears hyperemic. Laboratory results are as follows:
 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (81)
(81) A 73-year-old man is brought to the emergency department after his daughter found him on the floor. The patient says that he fell and now his left hip "hurts a lot," but he does not recall any details of the fall. Over the past several days, he has felt short of breath with a cough and intermittent palpitations that he attributed to "coming down with the flu." His other medical problems include hypertension, type 2 diabetes mellitus, chronic obstructive pulmonary disease, and benign prostatic hyperplasia. His temperature is 37.3 C (99.2 F), blood pressure is 118/76 mm Hg, pulse is 116/min, and respirations are 24/min. Pulse oximetry shows 95% on 2 L/min of oxygen by nasal cannula. Breath sounds are decreased at the right lung base, and crackles are present at the left lung base. The left lower extremity is shortened and externally rotated. Initial laboratory studies, including complete blood count, glucose, and serum chemistries, are normal. The pain improves with a dose of hydromorphone. X-ray findings are shown below. 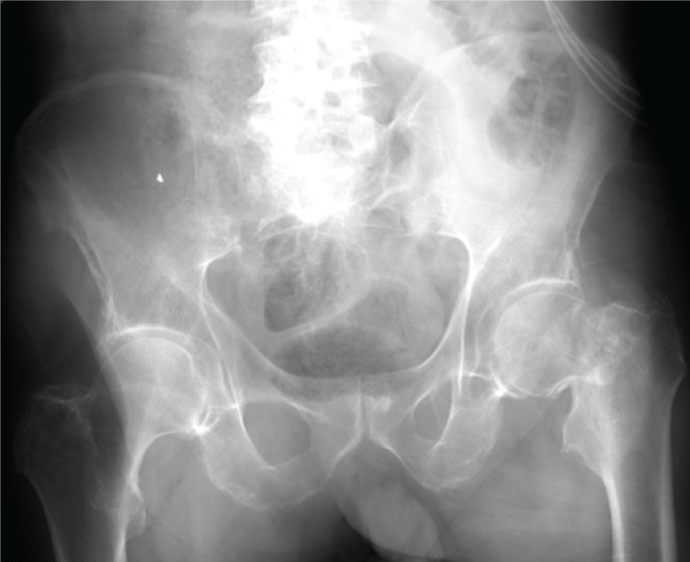 Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (83)
(83) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)