



 Chat with AI
Exam 4: Surgery

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 44-year-old man is brought to the emergency department after he was found unresponsive at the scene of a high-speed motor vehicle collision. The paramedics report that that he was the unrestrained driver, and the passenger in his car was pronounced dead at the scene. The patient was intubated and rushed to the hospital. On arrival, his blood pressure is 78/40 mm Hg, pulse is 135/min, and pulse oximetry is 96% on mechanical ventilation with 40% oxygen. Rapid infusion of isotonic fluids is initiated. Trauma primary survey reveals an intubated man with appropriate spinal precautions. There is bruising and the imprint of the steering wheel across the anterior chest. The trachea is midline, and breath sounds are clear on the right but diminished on the left. Neck veins are collapsed bilaterally. Heart sounds are normal. All four extremities are pale and cool to the touch. There is no obvious external hemorrhage. Portable chest x-ray shows multiple rib fractures, opacification of the left hemithorax, and a widened mediastinum. ECG shows sinus tachycardia. Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5  (77)
(77) A 34-year-old man is brought to the emergency department after being rescued from a burning building. His temperature is 36.9 C (98.6 F), blood pressure is 90/60 mm Hg, pulse is 100/min, and respirations are 28/min. Examination shows second and third degree burns over 15% of his body. His oropharynx shows erythema and scattered blisters. His lungs are clear to auscultation and his abdomen is soft and nondistended. His blood carboxyhemoglobin concentration is 20%. Which of the following is the best management for this patient?
(Multiple Choice)
4.8/5 (72)
(72) A 66-year-old man comes to the emergency department due to worsening abdominal pain. Over the past week, he has had vague lower abdominal discomfort, nausea, anorexia, and constipation. This morning, the patient had sudden, severe lower abdominal pain accompanied by lightheadedness and an episode of vomiting. The pain initially improved but then gradually intensified to involve the entire abdomen. Medical history is significant for coronary artery disease and remote appendectomy. Temperature is 38.3 C (100.9 F), blood pressure is 110/54 mm Hg, pulse is 108/min, and respirations are 20/min. On physical examination, the patient is alert and cooperative but appears uncomfortable. Heart and lung sounds are normal. Bowel sounds are diminished. The abdomen is diffusely tender with guarding and rebound tenderness. Abdominal imaging is most likely to reveal which of the following findings in this patient?
(Multiple Choice)
4.9/5 (90)
(90) A 21-year-old hospitalized man is evaluated for confusion. He was admitted 2 days ago after an all-terrain vehicle rolled on top of him. He frequently binge-drinks alcohol and was drinking just prior to the incident. The patient has a right femoral midshaft fracture and right metatarsal fractures. He underwent operative fixation of the femoral fracture and received intravenous fluids and a blood transfusion. Cast immobilization of the metatarsal fractures was also performed. Temperature is 37.7 C (99.9 F), blood pressure is 130/80 mm Hg, pulse is 120/min, and respirations are 24/min. Pulse oximetry is 90% on room air and improves to 95% on 2 L of oxygen. The patient is restless, agitated, and confused. Breath sounds are normal and equal in both lungs. Cardiac auscultation is normal except for tachycardia. The abdomen is soft and nondistended. Left arm weakness is noted. Which of the following is the most likely cause of this patient's neurologic condition?
(Multiple Choice)
5.0/5 (76)
(76) A 50-year-old woman comes to the emergency department with 2 days of abdominal pain, nausea, and vomiting. The pain was initially intermittent, coming in waves, but over the past 6 hours it has become severe and continuous. She has vomited 3 times over the last several hours but has not passed gas or had a bowel movement for the last 3 days. The patient's medical history is notable only for a large benign ovarian cyst, which was removed 10 years ago. Temperature is 38.5 C (101.3 F), blood pressure is 91/64 mm Hg, pulse is 122/min, and respirations are 24/min. Pulse oximetry shows 97% on room air. Mucous membranes are dry. Cardiopulmonary examination shows tachycardia but no abnormalities. The abdomen is distended, tympanic, and tender to palpation in all 4 quadrants. There is mild guarding and bowel sounds are decreased. Digital rectal examination shows no stool in the rectal vault. Laboratory results are as follows:  Plain abdominal x-ray shows distended loops of small bowel with air-fluid levels. A nasogastric tube is placed. In addition to intravenous fluids and analgesics, which of the following is the best next step in management?
 (Multiple Choice)
4.7/5 (75)
(75) A 62-year-old man comes to the office for a follow-up visit a week after undergoing percutaneous coronary intervention. In the past 2 months, he has had several episodes of retrosternal chest pain, and a myocardial perfusion scan revealed an area of reversible ischemia on the lateral wall. Coronary angiography was performed through a right femoral access, and a drug-eluting stent was placed in the left circumflex artery. The patient has had some discomfort in the right groin since the procedure. He has had no further episodes of chest pain or dyspnea. Other medical issues include hypertension and hyperlipidemia. The patient has smoked a pack of cigarettes daily for 35 years and stopped smoking after he was diagnosed with heart disease. Temperature is 37.1 C (98.8 F), blood pressure is 130/70 mm Hg, and pulse is 86/min. Heart sounds and lung auscultation are normal. There is mild swelling in the right inguinal area with a palpable thrill and a continuous murmur on auscultation. Lower extremity deep tendon reflexes are normal. Which of the following is the most likely cause of this patient's current findings?
(Multiple Choice)
4.8/5 (91)
(91) An 80-year-old woman is brought to the hospital with progressively increasing abdominal pain, nausea, vomiting, and an inability to keep food down since yesterday. Her only medical condition is chronic paroxysmal atrial fibrillation, for which she takes metoprolol and apixaban, and she has never had any surgeries. The patient does not use tobacco or alcohol. Temperature is 37.1 C (98.8 F), blood pressure is 150/80 mm Hg, pulse is 96/min and regular, and respirations are 16/min. Oral examination shows dry mucous membranes. Cardiopulmonary examination reveals no abnormalities. The abdomen is distended and tympanic, but there is no tenderness, rebound, or rigidity. Bowel sounds are increased and high-pitched. Rectal examination shows no stool in the rectal vault and no masses. Fullness and tenderness are noted in the right groin area. The extremities are without cyanosis, clubbing, or edema. Laboratory testing yields a hemoglobin level of 13.2 g/dL, blood urea nitrogen of 38 mg/dL, and creatinine of 1.6 mg/dL. Abdominal x-ray reveals distended bowel loops with air-fluid levels. Which of the following most likely predisposed this patient to her current condition?
(Multiple Choice)
4.8/5 (82)
(82) A 50-year-old woman is evaluated in the post-anesthesia care unit due to sudden onset of severe nausea and right flank pain. The patient underwent a total abdominal hysterectomy and tumor debulking for metastatic ovarian cancer. The procedure was complicated by bleeding and a ureteral laceration that was repaired intraoperatively. Immediately afterwards, her hemoglobin level was 6.8 g/dL. A packed red blood cell transfusion was initiated 10 minutes ago. Now, in addition to nausea and right flank pain, she has developed pain and oozing along the IV site. Temperature is 38.5 C (101.3 F), blood pressure is 90/50 mm Hg, pulse is 130/min, and respirations are 26/min. Cardiac examination reveals tachycardia with weak pulses. The lungs are clear bilaterally. The skin examination is normal. The urine is dark red. Which of the following would most likely establish the diagnosis in this patient?
(Multiple Choice)
4.8/5 (83)
(83) A 6-year-old boy is brought to the emergency department by his mother due to new-onset chest pain. A week ago, he developed a low-grade fever with nasal congestion and a dry cough. Over the past few days, he has had paroxysms of coughing that seem to be worse at night. Last night, the patient developed pain in his chest that did not improve after he was given acetaminophen. He has no chronic medical conditions and takes no daily medications. Temperature is 37.3 C (99.1 F), blood pressure is 106/76 mm Hg, pulse is 130/min, respirations are 36/min, and pulse oximetry is 98% on room air. There is clear rhinorrhea. The posterior oropharynx and tonsils are erythematous. There is mild swelling of the neck and crepitus over the anterior chest. Pulmonary examination reveals clear and equal breath sounds bilaterally. Cardiac examination shows a normal S1 and S2 with no murmurs, rubs, or gallops. Which of the following is the best next step in evaluation of this patient?
(Multiple Choice)
4.9/5 (81)
(81) A 15-year-old boy comes to the physician with left shoulder joint pain and swelling. He has had these symptoms for the past 3 months and they are getting progressively worse. He has no fever, weight loss, or night sweats. The patient lifts weights and plays baseball 5 days a week. He has taken acetaminophen and ibuprofen with little relief. Examination shows a tender mass at the left proximal humerus. Range of motion is normal. Laboratory evaluation shows elevated alkaline phosphatase, erythrocyte sedimentation rate, and lactate dehydrogenase. X-ray of the shoulder is shown in the photograph below. 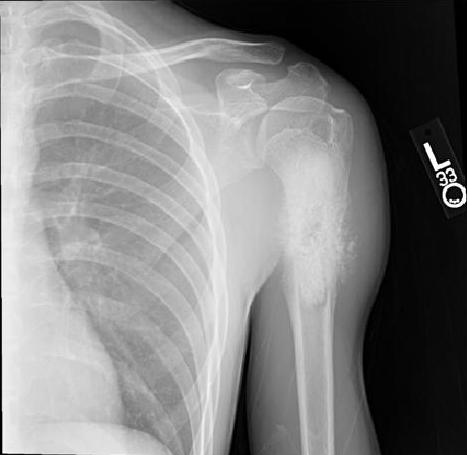 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (97)
(97) A 68-year-old man comes to the office due to right knee pain and swelling. Three days ago, the patient spent most of the day on his knees while replacing the kitchen floor. The next day, the right knee started to become increasingly red and painful. Medical history includes hypertension and type 2 diabetes mellitus. Temperature is 37.8 C (100 F), blood pressure is 130/80 mm Hg, and pulse is 92/min. On examination, erythema and warmth are present at the anterior right knee, as shown in the exhibit. 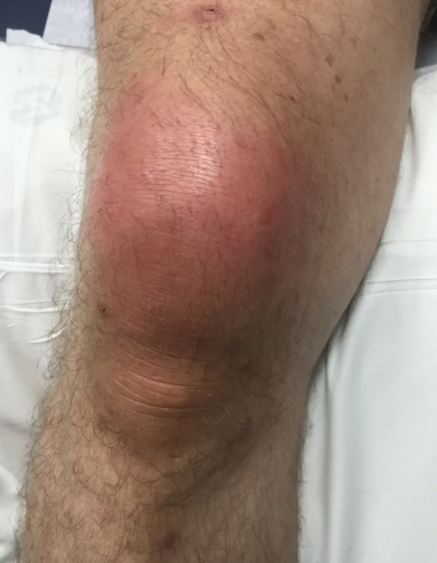 Palpation reveals a 5-cm, tender, fluctuant swelling just anterior to the patella. Range of motion of the knee is intact but produces mild pain at the end-range of flexion and extension. Pedal pulses are 2+, and sensation in the lower extremities is intact. Gait is normal. Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.9/5 (92)
(92) A 74-year-old man comes to the office due to difficulty swallowing food. The symptoms began 4 months ago when the patient was eating steak and felt like a bite got stuck in the middle of his chest, which resolved after drinking a glass of water. Since then, he has had several similar episodes when eating bread or meat and has modified his diet to soft foods. He has no difficulty drinking liquids and has had no chest or abdominal pain, vomiting, melena, or weight loss. The patient has occasional nighttime heartburn, especially after eating spicy food, and takes antacids as needed. His other medical conditions include hypertension, for which he takes lisinopril. He does not use tobacco, alcohol, or illicit drugs. Family history is unremarkable. Vital signs are within normal limits. Physical examination shows normal dentition and oropharyngeal mucosa. Tonsils are normal. The lungs are clear on auscultation, and heart sounds are normal. The abdomen is soft and nontender with no organomegaly. The remainder of the physical examination shows no abnormalities. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (84)
(84) A 78-year-old man is brought to the emergency department due to an episode of syncope while working in his garden. He is now alert and oriented. He has chest and neck pain that developed just prior to the syncopal episode. Over the past week, he has had a cough, chest tightness, and whitish sputum production. Medical history is significant for long-standing hypertension, hyperlipidemia, and type 2 diabetes mellitus. The patient is a lifetime nonsmoker. Temperature is 37.3 C (99.2 F), blood pressure is 144/92 mm Hg on the right arm and 142/90 mm Hg on the left arm, and pulse is 109/min. ECG shows sinus tachycardia, voltage criteria for left ventricular hypertrophy, and no ST-segment or T-wave changes. Chest x-ray is shown in the exhibit. 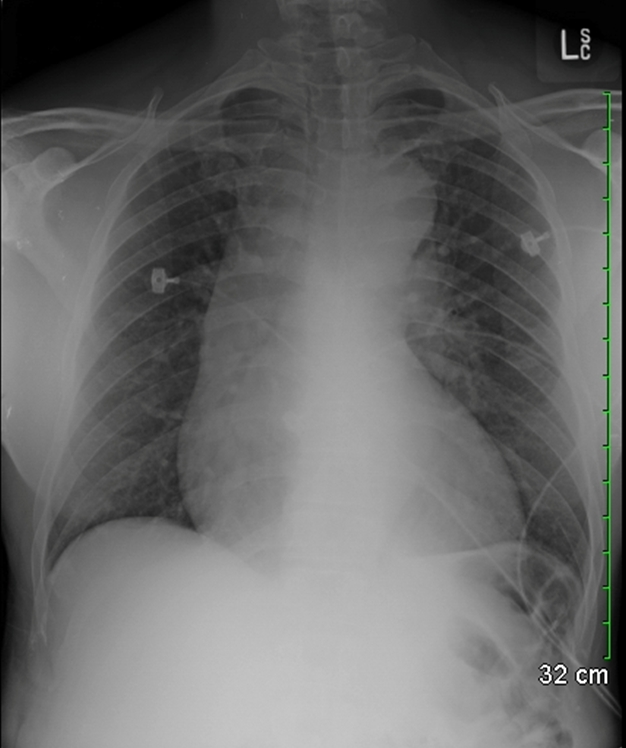 A bedside transthoracic echocardiogram shows a small pericardial effusion. Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (69)
(69) A 64-year-old man comes to the office due to urinary urgency, straining to urinate, a sensation of incomplete bladder evacuation, and frequent nocturia over the past several months. He has had no dysuria, fever, chills, abdominal or perineal pain, or penile discharge. The patient had similar symptoms in the past, which had improved after undergoing transurethral resection of the prostate (TURP) 5 years ago. He has no other medical conditions and takes no medications. Vital signs are within normal limits. Physical examination shows a soft and nontender abdomen. There are no external genital lesions, and the perineal sensation is normal. Digital rectal examination shows normal anal sphincter tone and a nontender prostate. Urine dipstick is negative for blood, leukocyte esterase, or nitrites. Which of the following is the most likely cause of this patient's current symptoms?
(Multiple Choice)
4.9/5 (68)
(68) A 36-year-old woman comes to the office due to intermittent abdominal pain. She has had 5 episodes of pain over the past several weeks. The pain is dull, is located in the right upper quadrant and epigastrium, and often radiates to her back. The pain occurs only after eating and lasts 30-60 minutes. It is not relieved by antacids. The pain is occasionally associated with nausea and vomiting, but the patient has no hematemesis, melena, or weight loss. She does not use nonsteroidal anti-inflammatory drugs, tobacco, or alcohol. Her father died of pancreatic cancer at age 64. Temperature is 37.5 C (99.5 F), blood pressure is 142/89 mm Hg, pulse is 67/min, and respirations are 12/min. BMI is 32 kg/m2. The abdomen is tender to palpation in the right upper quadrant and epigastrium but is nondistended and without rebound or guarding. Laboratory results are as follows:  Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (87)
(87) A 60-year-old woman with a history of poorly controlled type 2 diabetes mellitus comes to the emergency department due to worsening perianal pain. The patient is febrile, hypotensive, and tachycardic. Physical examination reveals tenderness and swelling in the perianal and gluteal region with dusky overlying skin and palpable crepitus. Leukocyte count is 27,000/mm3, and CT scan shows edema of the gluteal and perineal subcutaneous tissue with free gas. Intravenous fluids and antibiotics are initiated, and the patient undergoes urgent surgical debridement of the necrotic tissue. Several hours later, she experiences increasing dyspnea and hypoxemia. Chest x-ray reveals new bilateral lung infiltrates. Bedside echocardiography shows a hyperdynamic left ventricle with no significant valve disease. Which of the following best describes this patient's current pulmonary condition?
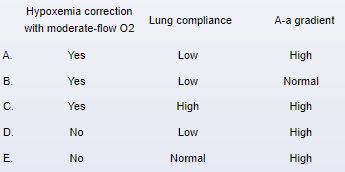
(Multiple Choice)
5.0/5 (81)
(81) A 65-year-old man comes to the emergency department due to acute right flank pain. The pain started an hour ago and he has vomited twice. The pain is 10 on a scale of 0-10 in severity, is crampy, and waxes and wanes. The patient has never before had similar pain. He reports passing "sand" occasionally in his urine. Medical history is significant for obesity, hyperlipidemia, hypertension, gout, and claustrophobia. The patient does not use tobacco, alcohol, or illicit drugs. He is afebrile. Blood pressure is 160/100 mm Hg, pulse is 98/min, and respirations are 16/min. BMI is 54 kg/m2. The abdomen is obese and bowel sounds are decreased. Mild tenderness is present over the right flank. Urinalysis shows hematuria and a urine pH of 5. Abdominal ultrasonogram shows right-sided hydronephrosis and dilation of the proximal ureter. Which of the following is the most likely cause of this patient's current symptoms?
(Multiple Choice)
4.8/5 (74)
(74) A 70-year-old male presents to the emergency room complaining of weakness, dizziness and back pain. He denies nausea, vomiting, diarrhea, chest pain, palpitations, shortness of breath, urinary symptoms, or black stools. His past medical history is significant for diabetes mellitus, diabetic nephropathy and retinopathy, hypertension, atrial fibrillation and chronic leg cellulitis. He takes warfarin for chronic anticoagulation. On physical examination, his blood pressure is 120/70 mmHg and his heart rate is 110 and irregular. His WBC count is 10,500/mm3, hemoglobin level is 7.0 g/dL and platelet count is 170,000/mm3. An abdominal CT image is shown on the slide below. 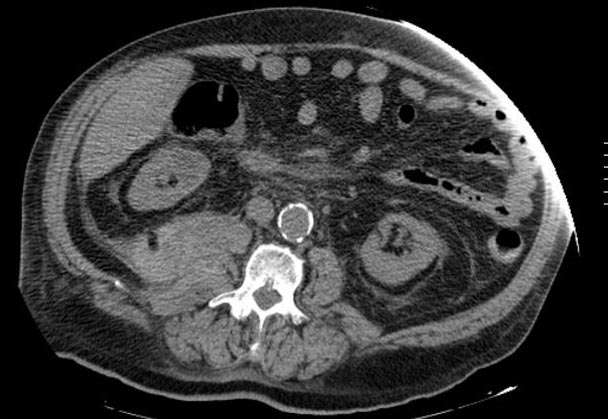 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.8/5 (72)
(72) A 45-year-old man comes to the emergency department due to left wrist pain after a fall. The patient was walking in his house when he tripped over a rug and landed on his outstretched hand. His wrist swelled and he applied ice, which did not improve the swelling or pain. Medical history is notable for celiac disease, hypertension, and hypothyroidism for which he is on thyroid hormone supplementation. The patient does not use tobacco, alcohol, or illicit drugs. He has no known medication allergies. BMI is 20 kg/m2. Examination shows a "dinner-fork" deformity at the left wrist. The wrist is swollen and tender to palpation. Sensation over the left hand is intact, and the patient is able to move all his fingers. X-ray of the left wrist is shown below. 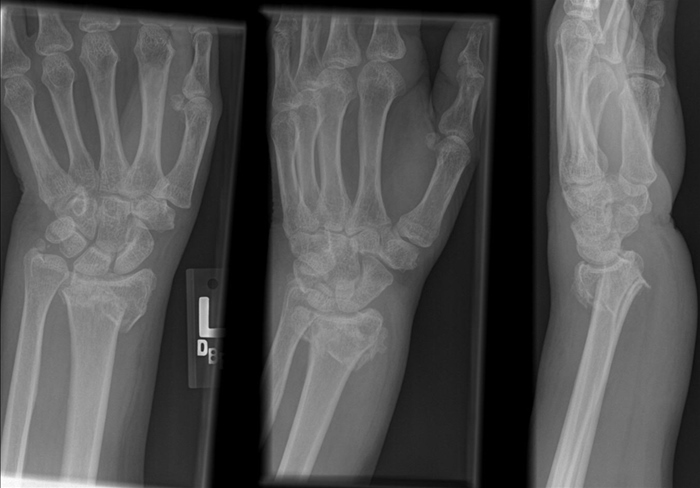 Which of the following is the most significant risk factor for bone fracture in this patient?
 (Multiple Choice)
4.9/5 (74)
(74) A 21-year-old man comes to the office requesting a refill of an opioid medication for new-onset left hip pain. The pain started 3 weeks ago and was initially only with weightbearing, but has progressively worsened and is now present at rest and overnight. He has no history of trauma. Medical history is notable for sickle cell disease with several hospitalizations for acute pain crisis. His last hospitalization was 3 months ago. The patient has been taking some leftover opioid pain medications from that hospitalization, in addition to regularly scheduled folic acid and hydroxyurea. He is sexually active with a new female partner. The patient does not use alcohol, tobacco, or illicit drugs. His temperature is 37.2 C (99 F), blood pressure is 100/70 mm Hg, pulse is 80/min, and respirations are 16/min. Physical examination reveals no local tenderness, but there is restriction of abduction and internal rotation of the left hip. The right hip and other joints are normal. Hip x-rays and erythrocyte sedimentation rate are normal. Which of the following is the most likely diagnosis?
(Multiple Choice)
5.0/5 (96)
(96) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)