


 Chat with AI
Exam 1: Medicine

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 68-year-old woman comes to the office due to gradually worsening shortness of breath. Over the past several months, she has bothersome dyspnea on exertion, now developing with even light housework. She also reports cough in the mornings that is productive of minimal white sputum. The patient has had no chest pain or fever. She smoked approximately 10 cigarettes daily from age 18 to 50. Blood pressure is 128/76 mm Hg, pulse is 80/min, and respirations are 14/min. Oxygen saturation is 94% on room air. On physical examination, the patient is breathing comfortably without using accessory muscles of respiration. The trachea is central, and jugular venous pressure is normal. Lung auscultation reveals bilateral vesicular breath sounds with occasional rhonchi that clears after the patient is asked to cough. Heart sounds are normal. Chest x-ray reveals no abnormalities. Pulmonary function testing shows that FEV1 is 65% of predicted, and the FEV1/FVC ratio is 50%. These values are unchanged after administration of albuterol. Which of the following is the best next step in management of this patient?
(Multiple Choice)
5.0/5  (80)
(80) A 21-year-old woman comes to the office due to a 7-day history of sore throat, extreme fatigue, myalgias, and headaches. She recently returned from a winter break vacation to Jamaica. The patient has no significant medical history and takes no medications. She smokes half a pack of cigarettes daily and occasionally consumes alcohol. Temperature is 38 C (100.4 F), heart rate is 78/min, blood pressure is 114/76 mm Hg, and respirations are 14/min. Examination of the oropharynx shows palatal petechiae and enlarged, erythematous tonsils with exudates. There is generalized lymphadenopathy and mild splenomegaly. Complete blood count is as follows:  Peripheral blood smear is performed. Rapid streptococcal antigen and heterophile antibody tests are negative. Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.9/5 (85)
(85) A 31-year-old woman comes to the emergency department due to shortness of breath and anxiety. She has no associated chest pain or palpitations. She recently returned from a trip to Thailand. The patient does not smoke and drinks alcohol occasionally. She is married and uses barrier contraception. The patient has a history of anxiety and sleep problems, and her family history is negative for heart attack or blood clots but positive for colon cancer (her uncle at age 58). She is afebrile. Blood pressure is 110/70 mm Hg, pulse is 96/min, and respirations are 24/min. Estimated jugular venous pressure is normal. The chest is clear to auscultation. There is no extremity edema and no skin rashes are present. Arterial blood gas analysis shows:  Chest x-ray and D-dimer are normal. Her symptoms resolve over the next hour. Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.7/5 (92)
(92) A 15-year-old boy is brought to the clinic due to fatigue, malaise, fever, and sore throat for the past 6 days. The patient has been in bed most of this time, uninterested in reading or playing video games due to tiredness. He has no chronic medical conditions and takes no medications. The patient is sexually active and uses condoms inconsistently. He does not use tobacco, alcohol, or illicit drugs. Temperature is 38.3 C (101 F), blood pressure is 115/70 mm Hg, pulse is 90/min, and respirations are 18/min. Physical examination shows pharyngeal hyperemia with exudates along with cervical and axillary lymphadenopathy. Breath sounds are normal. There are no heart murmurs. The abdomen is soft and nontender. Mild hepatosplenomegaly is present. Joints have a normal range of motion. There is no skin rash. A rapid streptococcal antigen test is negative. Which of the following is the most appropriate management for this patient?
(Multiple Choice)
4.8/5 (88)
(88) A 36-year-old man comes to the office due to progressive fatigability. Medical history is significant for infiltrative pulmonary tuberculosis diagnosed 2 months ago. His current treatment includes isoniazid, rifampin, ethambutol, and pyrazinamide. Laboratory results are as follows:  Microscopy reveals 2 populations of red blood cells: hypochromic and normochromic. Which of the following is the next best step in the management of this patient?
 (Multiple Choice)
4.8/5 (72)
(72) An 82-year-old woman comes to the emergency department with sudden-onset epigastric pain. The pain started an hour ago and is 8/10 in severity. The patient has been nauseated and vomited twice in the past hour. Her past medical history includes type 2 diabetes mellitus, hyperlipidemia, hypertension, peptic ulcer disease 10 years ago, and cholelithiasis. She has a 40-pack-year smoking history and drinks alcohol occasionally. Her temperature is 36.8 C (98.2 F), blood pressure is 140/80 mm Hg, pulse is 90/min, and respirations are 14/min. The lungs are clear to auscultation. Abdominal examination shows a soft abdomen with no tenderness. Murphy's sign is negative. Which of the following studies should be performed first in this patient?
(Multiple Choice)
5.0/5 (69)
(69) A 32-year-old man comes to the office due to occasional palpitations. The patient's medical history is unremarkable, and he considers himself healthy. His maternal uncle died suddenly at age 40, and a cousin underwent heart surgery at a young age. The examiner asks the patient to sit upright, lean forward, and hold his breath in full expiration as the stethoscope diaphragm is placed at the left sternal border and firm pressure is applied. There is a decrescendo early diastolic murmur. The rest of the physical examination is unremarkable. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (67)
(67) A 64-year-old man comes to the emergency department with a 3-day history of progressively increasing pain, swelling, and redness of his right knee. The pain is severe with weight bearing, and he is unable to ambulate without assistance. The patient reports no recent trauma to the knee but has had subjective fever. He was diagnosed with gout 10 years ago and had several recurrences of acute gout involving multiple joints, but has had good control since he started taking allopurinol. Six weeks ago, he went on a camping trip in the mountains of New Hampshire. Medical history is notable for type 2 diabetes mellitus and hypertension. Current medications include lisinopril and metformin. The patient does not use tobacco, alcohol, or illicit drugs. His temperature is 38.3 C (100.9 F), blood pressure is 110/65 mm Hg, and pulse is 110/min. Examination shows a tender, swollen, erythematous right knee with markedly decreased range of motion. The remainder of the examination is unremarkable. Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.8/5 (74)
(74) A 26-year-old woman is brought to the emergency department by coworkers due to agitated behavior. She appears distracted by unseen stimuli during the initial interview, strikes out at a nurse taking her vital signs, and attempts to lift a hospital cart. The patient has a history of depression as well as alcohol and drug use, but she is not currently in treatment. She has no other underlying illness. Temperature is 37.2 C (99 F), blood pressure is 160/90 mm Hg, pulse is 126/min, and respirations are 18/min. The patient is confused and agitated during the examination, frequently yelling and talking to herself. Physical examination shows equal and reactive pupils, intact extraocular movements, and nystagmus. There is mild rigidity that is most prominent in the upper extremities. Upper and lower limb deep tendon reflexes are 1+. The remainder of the examination is unremarkable. Intoxication with which of the following substances is the most likely explanation in this patient?
(Multiple Choice)
4.8/5 (96)
(96) A 34-year-old man comes to the office due to a 5-month-history of exertional dyspnea without associated chest pain, palpitations, dizziness, or syncope. The patient recently emigrated from Brazil. Medical history is significant for an episode of megacolon, which was treated 2 years ago. On physical examination, there is 1+ pedal edema and mild jugular venous distension. Cardiac examination is significant for the presence of an S3. No murmurs are heard. Chest x-ray reveals prominent cardiomegaly. Which of the following is most likely causing his symptoms?
(Multiple Choice)
4.9/5 (72)
(72) A 68-year-old man comes to the clinic due to palpitations that have been especially prominent over the past 2 days. Medical history is significant for myocardial infarction and heart failure with reduced ejection fraction. Medications include aspirin, digoxin, furosemide, sacubitril-valsartan, metoprolol, and atorvastatin. Blood pressure is 126/74 mm Hg, pulse is 102/min, and respirations are 15/min. Physical examination reveals no murmurs or extra heart sounds. The lungs are clear to auscultation. No peripheral edema is present. ECG shows atrial tachycardia with second-degree atrioventricular block. Which of the following is most likely responsible for this patient's presentation?
(Multiple Choice)
4.9/5 (71)
(71) A 55-year-old male presents with face and arm swelling that he says is worst when he wakes in the morning. He also notes a 10 pound unintentional weight loss over the past three months, plus new-onset exertional dyspnea. His past medical history is significant for hypertension, for which he takes hydrochlorothiazide. He has smoked cigarettes for the past 40 years and drinks alcohol occasionally. On physical examination, he is afebrile and his vital signs are within normal limits. His face is plethoric and dark-appearing. The veins on the anterior chest wall appear engorged. His abdomen is soft, non-tender, and non-distended, and there is no organomegaly. The lower extremities are non-edematous. What is the most appropriate next step in the management of this patient?
(Multiple Choice)
4.7/5 (81)
(81) A 66-year-old man comes to the office due to several weeks of severe constipation and increasing back pain. The patient notes that he has always had regular bowel movements; however, for the last 2 months, he has required over-the-counter laxatives to produce any stool. During this period, he has also had increasing pain in his lower back. He has had no trauma to that area. There is no radiation down the legs, bowel incontinence, or lower extremity weakness. The patient takes lisinopril for hypertension and ibuprofen as needed for back pain. He does not use tobacco or alcohol. Temperature is 36.1 C (97 F), blood pressure is 134/80 mm Hg, and pulse is 78/min. Mucosal pallor is present. He is anicteric. Cardiopulmonary and abdominal examinations are normal. Rectal examination reveals a smooth, nonenlarged prostate. The stool is negative for occult blood. Strength and reflexes are intact in his lower extremities. Laboratory results are as follows:  Which of the following is the best explanation for this patient's constipation?
 (Multiple Choice)
4.8/5 (74)
(74) A 55-year-old man is hospitalized after a massive hemorrhage from a duodenal ulcer. The bleeding is stopped with endoscopic manipulation. The patient receives 2 L of intravenous fluids, followed by 2 units of packed red blood cells. Two hours after the transfusion is started, he develops chills and malaise. Temperature is 38.7 C (101.7 F), blood pressure is 120/76 mm Hg, pulse is 100/min, and respirations are 20/min. The transfusion is stopped, and the patient is given acetaminophen. Direct antiglobulin and plasma-free hemoglobin level tests are negative. Urinalysis is within normal limits. The symptoms resolve within 6 hours of transfusion discontinuation. Which of the following is the best procedure for preventing this type of transfusion reaction?
(Multiple Choice)
4.9/5 (74)
(74) A 75-year-old man is being evaluated for a heart murmur. He has had no exertional chest pain, shortness of breath, palpitations, fatigue, dizziness, or syncope. The patient's only other medical condition is hypertension, for which he takes chlorthalidone and amlodipine. He has a 20-pack-year smoking history but quit 25 years ago. Temperature is 36.9 C (98.4 F), blood pressure is 130/80 mm Hg, pulse is 80/min, and respirations are 16/min. Physical examination shows a sustained apical impulse. S1 is normal; a single, soft S2 and an S4 are present. A grade 3/6 late-peaking systolic murmur is heard best at the right 2nd intercostal space, with radiation to the right carotid artery. Carotid pulses are delayed. Transthoracic echocardiogram shows a thickened left ventricular wall with no regional wall motion abnormalities. The ejection fraction is 45%. There is a trileaflet aortic valve with heavy calcification, valve area of 0.9 cm2, and transvalvular gradient consistent with severe aortic stenosis. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (99)
(99) A 47-year-old man is evaluated for progressively worsening dyspnea on exertion for several months. The patient has frequent awakenings at night due to a choking sensation and feels tired all the time, limiting his physical activity. He does not use tobacco, alcohol, or illicit drugs. Blood pressure is 166/100 mm Hg and pulse is 80/min. BMI is 48 kg/m2. Jugular venous pressure is difficult to assess due to neck fat. Heart sounds are distant with no murmurs or gallops. Bilateral breath sounds are normal with no crackles or wheezes. Trace bilateral pitting edema is present. Chest x-ray reveals poor inspiratory effort but clear lung fields. Which of the following additional findings is most likely present in this patient?
(Multiple Choice)
4.8/5 (72)
(72) An 18-year-old man seeks advice before going to central Africa for a class project at his university. He was diagnosed with Crohn disease 3 years ago but currently feels well and has been asymptomatic on methotrexate and adalimumab for the last year. A review of medical records shows documentation of meningococcal polysaccharide vaccine at age 11. The patient has had no vaccines since then but believes that he received all of the recommended childhood vaccinations prior to that. His vital signs and physical examination are normal. Which of the following vaccines should be recommended for this patient?
(Multiple Choice)
4.8/5 (81)
(81) A 56-year-old woman comes to the office for evaluation of chronic diarrhea. The patient began experiencing daily watery bowel movements several months ago and tried eliminating dairy products, but the diarrhea continued to worsen. Lately, she has been having 5-6 bowel movements daily and occasionally at night. The patient has had no melena, hematochezia, fever, abdominal pain, nausea, vomiting, or weight loss but does have fecal urgency. Medical history is significant for obesity, hypertension, and knee osteoarthritis. Home medications include hydrochlorothiazide and naproxen. She drinks a glass of wine with dinner daily but does not smoke cigarettes. Vital signs are within normal limits. The abdomen is nondistended, soft, and nontender with no organomegaly. Bowel sounds are normoactive. Stool testing for occult blood is negative. Colonoscopy reveals a normal-appearing colon. Random colonic biopsies demonstrate mononuclear cell infiltration of the lamina propria and a thickened subepithelial collagen band. Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (82)
(82) A 25-year-old, previously healthy man comes to the office due to 3 months of progressive dyspnea and nonproductive cough. The patient feels short of breath when cycling 2 miles to his office, which he could do without difficulty in the past. He does not use tobacco or alcohol. The patient works at a publishing firm in New York and has not traveled recently. Family history is significant for asthma in his father. Temperature is 36.7 C (98.1 F), blood pressure is 130/80 mm Hg, pulse is 78/min, and respirations are 16/min. Pulse oximetry is 97% on room air. The lungs are clear on auscultation and heart sounds are normal. Laboratory results are as follows:  Chest x-ray shows mediastinal fullness and scattered reticular opacities in the upper lungs. Which of the following pulmonary function test patterns is most likely to be observed in this patient?
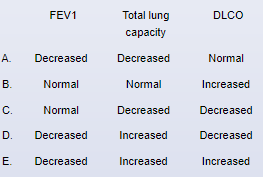
Chest x-ray shows mediastinal fullness and scattered reticular opacities in the upper lungs. Which of the following pulmonary function test patterns is most likely to be observed in this patient?
(Multiple Choice)
4.9/5 (76)
(76) A 45-year-old man comes to the office due to loss of sexual desire and failure to attain satisfactory erections during intercourse. He has no morning erections. The patient has no leg or buttock pain with exertion but has had intermittent bilateral hand pain. Medical history is significant for type 2 diabetes mellitus and recent-onset peripheral neuropathy. He does not use tobacco or alcohol. The patient has a 12-year-old child from a previous marriage and now lives with his second wife. Blood pressure is 120/70 mm Hg and pulse is 70/min. BMI is 24 kg/m2. The neck is supple with no thyromegaly or lymphadenopathy. Cardiopulmonary examination is normal. The abdomen is soft and nontender with palpable hepatomegaly. Genital examination shows small testes bilaterally but otherwise normal secondary sexual characteristics. Peripheral pulses are 2+, and capillary refill in the feet is normal. Neurologic examination demonstrates normal deep tendon reflexes and muscle strength; sensation is mildly decreased in both ankles. Visual field testing is normal. What is the best next step in management of this patient?
(Multiple Choice)
4.7/5 (85)
(85) Showing 741 - 760 of 1702
 Prev
- 1
- ...
- 2
- ...
- 3
- ...
- 4
- ...
- 5
- ...
- 6
- ...
- 7
- ...
- 8
- ...
- 9
- ...
- 10
- ...
- 11
- ...
- 12
- ...
- 13
- ...
- 14
- ...
- 15
- ...
- 16
- ...
- 17
- ...
- 18
- ...
- 19
- ...
- 20
- ...
- 21
- ...
- 22
- ...
- 23
- ...
- 24
- ...
- 25
- ...
- 26
- ...
- 27
- ...
- 28
- ...
- 29
- ...
- 30
- ...
- 31
- ...
- 32
- ...
- 33
- ...
- 34
- ...
- 35
- ...
- 36
- ...
- 37
- ...
- 38
- ...
- 39
- ...
- 40
- ...
- 41
- ...
- 42
- ...
- 43
- ...
- 44
- ...
- 45
- ...
- 46
- ...
- 47
- ...
- 48
- ...
- 49
- ...
- 50
- ...
- 51
- ...
- 52
- ...
- 53
- ...
- 54
- ...
- 55
- ...
- 56
- ...
- 57
- ...
- 58
- ...
- 59
- ...
- 60
- ...
- 61
- ...
- 62
- ...
- 63
- ...
- 64
- ...
- 65
- ...
- 66
- ...
- 67
- ...
- 68
- ...
- 69
- ...
- 70
- ...
- 71
- ...
- 72
- ...
- 73
- ...
- 74
- ...
- 75
- ...
- 76
- ...
- 77
- ...
- 78
- ...
- 79
- ...
- 80
- ...
- 81
- ...
- 82
- ...
- 83
- ...
- 84
- ...
- 85
- ...
- 86
- ...
- Next

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)