


 Chat with AI
Exam 1: Medicine

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 15-year-old girl is brought to the emergency department due to pain in her arms, legs, and lower back. The patient has sickle cell disease and in the past has been hospitalized for pain crises and pneumococcal sepsis. Her current symptoms began this morning, but she is out of her medications, including oxycodone, hydroxyurea, and penicillin. Temperature is 37.6 C (99.7 F), blood pressure is 158/88 mm Hg, pulse is 110/min, and respirations are 24/min. Pulse oximetry is 99% on room air. The patient is alert but anxious. Cardiac examination shows a flow murmur. The lungs are clear to auscultation. The abdomen is soft with no organomegaly. The legs and back are moderately tender to palpation. Morphine is given for pain control, and 1 hour afterward the patient is suddenly unable to move her left side. Examination shows 1/5 strength in the left upper and lower extremities and 5/5 strength in the right upper and lower extremities. Sensation is also diminished on the left side. Fingerstick glucose is 110 mg/dL. CT scan of the head shows no acute pathology. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5  (84)
(84) An 18-year-old woman is brought to the emergency department due to 3 days of fever, severe headache, nausea, and vomiting. She attends college in North Carolina and has been sexually active with a male partner. Temperature is 39.4 C (102.9 F), blood pressure is 80/55 mm Hg, and pulse is 146/min. The patient is ill-appearing and poorly arousable. The neck is supple, with no jugular venous distension, nuchal rigidity, or lymphadenopathy. Chest examination reveals bilateral rales. A diffuse maculopapular rash with numerous petechiae is seen on the trunk, extremities, hands, and feet. Lumbar puncture reveals the following:  Which of the following organisms is the most likely cause of this patient's clinical presentation?
 (Multiple Choice)
4.9/5 (70)
(70) A 64-year-old man is admitted to the hospital with palpitations and lightheadedness for the past several days. He has experienced palpitations previously, but recently they have seemed sustained and "uncomfortable." The patient has had no chest pain or shortness of breath. He has a history of coronary artery disease and prior percutaneous coronary interventions. He is treated with metoprolol, lisinopril, aspirin, clopidogrel, and rosuvastatin. Echocardiogram shows mild left ventricular dilation, a left ventricular ejection fraction of 30%, and no major valvular abnormality. Serum potassium is 4.2 mEq/L and magnesium is 1.9 mg/dL. On day 2 of hospitalization, the patient develops sudden-onset palpitations that feel like "fluttering in my chest." Blood pressure is 122/60 mm Hg. He is alert and does not appear to be in distress. Examination shows clear lungs bilaterally. His ECG strip is shown below. 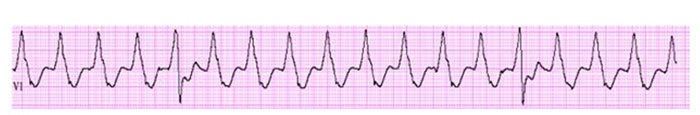 Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (71)
(71) A 27-year-old woman is admitted to the hospital urgently for labor. The patient has had no prenatal care. Delivery is complicated by premature rupture of membranes and prolonged labor. On day 3 of hospitalization, she develops fever, chills, lower abdominal pain, and hypotension. Postpartum endometritis is suspected. The patient is prescribed broad-spectrum antibiotics and intravenous fluids. Over the next 24 hours, she develops increasing shortness of breath. The patient receives a total of 5 L of normal saline to treat the hypotension. Temperature is 38.5 C (101.3 F), blood pressure is 110/66 mm Hg, pulse is 110/min, and respirations are 24/min. BMI is 34 kg/m2. Pulse oximetry is 80% on a 100% nonrebreather mask, and the decision is made to intubate. There is no evidence of jugular venous distension. Cardiac examination is normal except for tachycardia. Lung auscultation reveals diffuse bilateral crackles. Mild bilateral pitting edema is present in the lower extremities. Chest x-rays 24 hours earlier (left) and at intubation (right) are shown in the images below: 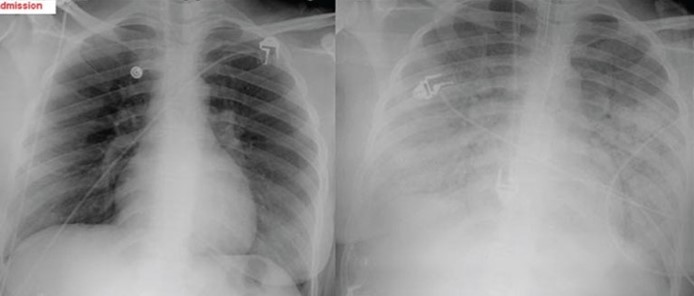 After intubation, an arterial blood gas test shows a PaO2 of 60 mm Hg on 100% oxygen and a PaCO2 of 34 mm Hg. Which of the following best explains this patient's respiratory symptoms?
 (Multiple Choice)
4.8/5 (67)
(67) A 64-year-old man comes to the physician due to shortness of breath and abdominal distension. He was treated for Hodgkin lymphoma with radiation and chemotherapy 18 years ago and was told that he was cured. The patient drinks alcohol on a regular basis. His temperature is 36.7 C (98 F), blood pressure is 120/76 mm Hg, pulse is 92/min, and respirations are 20/min. Neck examination shows jugular venous pulsations 9 cm above the sternal angle. The abdomen is distended with a positive fluid wave. The liver edge is palpated 5 cm below the right costal edge. There is bilateral lower-extremity pitting edema. Initial laboratory results are as follows:  Which of the following is the most likely cause of this patient's condition?
 (Multiple Choice)
4.7/5 (68)
(68) A 65-year-old man with chronic obstructive pulmonary disease comes to the emergency department with increased dyspnea and worsening cough for the last 2 days. He has been unable to rest due to increased symptoms. The patient has increased sputum production compared to his baseline. He tried 3 nebulizer treatments with albuterol and ipratropium bromide at home with no relief. His most recent spirometry during an office visit a month ago showed FEV1 of 60% of predicted. His temperature is 37.2 C (99 F), blood pressure is 150/90 mm Hg, pulse is 110/min, and respirations are 23/min. The patient's oxygen saturation is 87% on room air. He appears to be in mild respiratory distress. Lung examination shows bilateral wheezing and prolonged expiration. ECG shows sinus tachycardia. Chest x-ray reveals a flattened diaphragm and no infiltrates. Initial laboratory studies show a white blood cell count of 11,000/mm3. He is started on supplemental oxygen, bronchodilators, and glucocorticoids. Which of the following additional therapies would also benefit this patient in the acute setting?
(Multiple Choice)
4.9/5 (77)
(77) A 46-year-old woman suffering from systemic lupus erythematosus (SLE) develops hematuria and proteinuria. She was diagnosed with SLE four years ago and has been treated with hydroxychloroquine and prednisone. A renal biopsy is performed and shows diffuse proliferative glomerulonephritis. She is started on cyclophosphamide, and hydroxychloroquine is stopped. This new therapeutic regimen puts her at an increased risk for which of the following conditions?
(Multiple Choice)
4.9/5 (75)
(75) A 28-year-old kindergarten teacher complains of a gritty sensation and discharge from the right eye for 3 days. She also has rhinorrhea, mild sore throat, and low-grade fever of 37.9 C (100.3 F). The symptoms began a week after classes started in the fall. Her medical history is significant for genital herpes and endometriosis. Eye examination shows mild injection and granular appearance of the tarsal conjunctiva of the right eye with profuse watery discharge. Nasal mucosa is normal, and the pharynx has mild erythema without exudates. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
5.0/5 (81)
(81) A 45-year-old woman comes to the clinic due to fatigue, weakness, and diffuse bone pain. She was diagnosed with celiac disease 5 years ago but continues to consume gluten-containing foods on occasion. The patient takes over-the-counter folic acid and iron supplements. Laboratory results are as follows:  Which of the following is directly responsible for this patient's bone pain?
 (Multiple Choice)
4.9/5 (87)
(87) A 25-year-old man comes to the office due to a dry cough that has persisted since he contracted an upper respiratory tract infection 10 days ago. The cough is worse at night and is not associated with nasal congestion, facial pressure, sore throat, abdominal discomfort, or vomiting. Medical history is notable only for childhood asthma, which the patient reports he "outgrew." All recommended vaccinations are up to date. The patient is afebrile, and other vital signs are normal. Nasal and pharyngeal examinations are unremarkable. Scattered wheezes are heard on lung auscultation. There are no heart murmurs. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (85)
(85) A 73-year-old man comes to the office due to 3 days of fever, facial pain over his right cheek, and bloody nasal discharge. Last night he was able to see without difficulty, but this morning, he developed double vision. He has had no recent trauma to the face or dental procedures. The patient has a 30-year history of type 2 diabetes mellitus complicated by nephropathy and retinopathy. His medical history also includes hypertension and hyperlipidemia. He is widowed and lives alone. He does not use tobacco or alcohol. Temperature is 39 C (102.2 F), blood pressure is 130/76 mm Hg, and pulse is 102/min. The patient appears ill. Chemosis and mild proptosis of the right eye are present. There is tenderness over the right maxillary sinus. Nasal examination shows right nasal congestion and necrosis of the right nasal turbinate. Necrosis of the hard palate is present. Cardiopulmonary examination is normal. The patient has no skin rash. CT scan reveals opacification and bony erosion of the right maxillary sinus. Hemoglobin A1c is 11%. Which of the following is the most likely causative organism?
(Multiple Choice)
4.7/5 (92)
(92) A 32-year-old woman comes to the office due to intermittent abdominal pain and nonbloody diarrhea for the past 3-4 months. She describes the pain as crampy and located in the mid-abdomen and right lower quadrant. The patient thinks she has lost some weight during this period. She modified her diet several times in an attempt to decrease the symptoms, believing that heavy meals exacerbate the pain and diarrhea. The patient underwent appendectomy with abscess debridement one year ago. She has no other medical issues and takes no medication other than oral contraceptives. She has not traveled outside the United States and does not use tobacco, alcohol, or recreational drugs. Temperature is 36.7 C (98 F), blood pressure is 120/70 mm Hg, pulse is 85/min, and respirations are 14/min. A few shallow ulcers are present in her mouth. Abdominal examination shows mild tenderness in the right lower quadrant without rebound. Laboratory results are as follows:  Which of the following is the most likely diagnosis for this patient?
 (Multiple Choice)
4.9/5 (77)
(77) A 32-year-old man comes to the office to "check up on my liver." He was seen about 2 years ago due to fatigue, anorexia, and jaundice, which developed after sharing needles with another injection drug user. Viral hepatitis serology testing at that time was positive for hepatitis B surface antigen but negative for all other antigens and antibodies, including hepatitis C. The patient has not sought medical care since then and has been asymptomatic. He stopped using injection drugs and is now sober. He does not use tobacco or alcohol and is in a monogamous relationship with his girlfriend. Physical examination is unremarkable. This patient's hepatitis B virus serology testing is most likely to show which of the following?
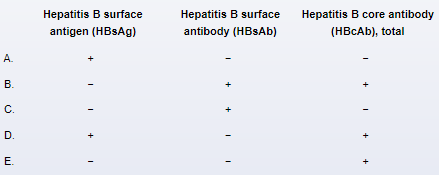
(Multiple Choice)
5.0/5 (79)
(79) A 45-year-old man comes to the emergency department due to a 4-week history of progressively worsening shortness of breath. The patient has no history of cardiopulmonary disease, although his wife, who accompanies him, states that he snores heavily at night. In addition, over the last 6 months his hands and feet have become enlarged; he is unable to take off his wedding ring and his shoes no longer fit. The patient has no significant medical history and takes no medications. He does not use tobacco or alcohol. On examination, he has coarse facial features with prominent frontal bones and jaw and crowding of the pharyngeal space. The extremities show enlarged, swollen hands and feet. There are fine crackles at the lung bases. Which of the following is most likely to be found on echocardiogram?
(Multiple Choice)
4.9/5 (78)
(78) A 62-year-old man comes to the office due to several months of fatigue. The patient has no chest pain, vomiting, diarrhea, weight loss, or back pain. Review of systems is significant for occasional leg cramps. He takes lisinopril for hypertension and atorvastatin for hyperlipidemia. The patient no longer smokes cigarettes but has a 30-pack-year history. He does not consume alcohol. Blood pressure is 132/80 mm Hg and pulse is 95/min. Conjunctiva are pale. Cardiopulmonary auscultation reveals clear lungs and a soft 2/6 ejection murmur at the right upper sternal border. The abdomen is soft and nontender without palpable masses. There are no skin rashes or peripheral edema. Laboratory results are as follows:  Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.7/5 (85)
(85) A 20-year-old previously healthy woman is brought to the emergency department due to lethargy. According to her mother, the patient had a "stomach bug" 2 days ago, with nausea, vomiting, and abdominal pain that began after eating in a restaurant. Her vomiting has resolved since that time, but she continues to have nausea and abdominal pain. Review of systems is positive for excessive thirst and a 4-kg (9-lb) weight loss over the past 2 weeks. She is not sexually active, and her last menstrual period was 10 days ago. The patient occasionally drinks beer but does not smoke or use illicit drugs. Temperature is 37.2 C (99 F), blood pressure is 100/56 mm Hg, pulse is 120/min, and respirations are 28/min. Pulse oximetry is 97% on room air. On examination, the patient is lethargic but easily arousable; she responds to questions in short sentences and moves all extremities spontaneously. Mucous membranes are dry, and the neck is supple. Other than tachycardia, cardiopulmonary examination is normal. There is diffuse abdominal tenderness without rebound tenderness, guarding, or rigidity. Which of the following is the best immediate next step in management of this patient's illness?
(Multiple Choice)
4.8/5 (80)
(80) A 20-year-old previously healthy woman comes to the office due to intermittent diarrhea and abdominal pain over the past several months. The patient has had bouts of diarrhea alternating with normal bowel movements, but lately the diarrhea has become more persistent. She reports 4-6 loose brown stools each day, which frequently awaken her at night. The diarrhea is associated with crampy abdominal pain in both lower quadrants that subsides after a bowel movement. Both the pain and the diarrhea frequently occur after eating. There are also days when she feels constipated and passes a small amount of mucus only. The patient has not had hematochezia, melena, or weight changes. There is no family history of gastrointestinal diseases. She does not use tobacco, alcohol, or illicit drugs. Vital signs are within normal limits. Physical examination, including abdominal and rectal examination, shows no abnormalities. Stool testing for occult blood is negative, and blood cell counts and serum chemistry studies are within normal limits. C-reactive protein is normal. Serologic testing for celiac disease is negative. Further testing may be indicated in this patient due to which of the following findings?
(Multiple Choice)
4.8/5 (83)
(83) A 35-year-old man is brought to the emergency department due to deteriorating vision for the past week. He initially experienced eye pain and mild redness of both eyes, followed by visual blurring and photophobia over the previous few days. The patient has a history of HIV diagnosed 10 years ago and has not been taking his antiretroviral medications. Temperature is 37.2 C (99 F), blood pressure is 110/81 mm Hg, and pulse is 82/min. Profuse clear drainage and crusting of the eyes is noted bilaterally. Slit-lamp examination reveals marked linear branching keratitis. Funduscopy shows a normal-appearing retina and optic nerve. Oral examination reveals numerous white plaques over the buccal mucosa, palate, and tongue. Which of the following organisms is the most likely cause of this patient's ocular findings?
(Multiple Choice)
4.9/5 (75)
(75) A 30-year-old man comes to the office due to a rash. For the last 3 weeks, he has had a slowly enlarging, pruritic rash at the left groin. The patient had a similar rash 2 months ago that resolved after topical treatment with miconazole; he has since been careful to dry his skin thoroughly after bathing. Medical history is unremarkable. The patient has 1 long-term sexual partner and does not use tobacco, alcohol, or illicit drugs. Vital signs are normal. BMI is 24 kg/m2. Examination shows an annular plaque with a scaly border in the left groin; scrotal skin is normal. Potassium hydroxide microscopy of skin scrapings from the lesion reveals segmented hyphae. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.7/5 (95)
(95) A 70-year-old man with a 10-year history of well-controlled Parkinson disease is brought to the clinic for evaluation of dizziness. He was able to walk 1 mile daily until he developed occasional episodes of dizziness and syncope when standing. His medications include levodopa, carbidopa, and a multivitamin. Seated blood pressure is 120/70 mm Hg with a heart rate of 66/min; standing blood pressure is 89/60 mm Hg with a heart rate of 68/min. Cardiopulmonary examination is normal. Neurologic examination shows mild tremor and bradykinesia. A complete blood count, basic metabolic panel, and ECG are normal. Which of the following is the most likely cause of this patient's dizziness?
(Multiple Choice)
4.8/5 (86)
(86) Showing 381 - 400 of 1702
 Prev
- 1
- ...
- 2
- ...
- 3
- ...
- 4
- ...
- 5
- ...
- 6
- ...
- 7
- ...
- 8
- ...
- 9
- ...
- 10
- ...
- 11
- ...
- 12
- ...
- 13
- ...
- 14
- ...
- 15
- ...
- 16
- ...
- 17
- ...
- 18
- ...
- 19
- ...
- 20
- ...
- 21
- ...
- 22
- ...
- 23
- ...
- 24
- ...
- 25
- ...
- 26
- ...
- 27
- ...
- 28
- ...
- 29
- ...
- 30
- ...
- 31
- ...
- 32
- ...
- 33
- ...
- 34
- ...
- 35
- ...
- 36
- ...
- 37
- ...
- 38
- ...
- 39
- ...
- 40
- ...
- 41
- ...
- 42
- ...
- 43
- ...
- 44
- ...
- 45
- ...
- 46
- ...
- 47
- ...
- 48
- ...
- 49
- ...
- 50
- ...
- 51
- ...
- 52
- ...
- 53
- ...
- 54
- ...
- 55
- ...
- 56
- ...
- 57
- ...
- 58
- ...
- 59
- ...
- 60
- ...
- 61
- ...
- 62
- ...
- 63
- ...
- 64
- ...
- 65
- ...
- 66
- ...
- 67
- ...
- 68
- ...
- 69
- ...
- 70
- ...
- 71
- ...
- 72
- ...
- 73
- ...
- 74
- ...
- 75
- ...
- 76
- ...
- 77
- ...
- 78
- ...
- 79
- ...
- 80
- ...
- 81
- ...
- 82
- ...
- 83
- ...
- 84
- ...
- 85
- ...
- 86
- ...
- Next

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)