



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


A 63-year-old man comes to the emergency department due to easy fatigability and mild abdominal discomfort over the past several days. He also has had intermittent episodes of black-colored stool but has had no chest pain, palpitations, or syncope. His medical history is significant for hypertension, hyperlipidemia, and osteoarthritis. The patient takes amlodipine, lisinopril, and simvastatin. He also takes over-the-counter ibuprofen for hip and back pain that has been "acting up" over the past few weeks. The patient does not use tobacco or illicit drugs and drinks alcohol occasionally. Temperature is 37 C (98.6 F), blood pressure is 106/64 mm Hg supine and 100/72 mm Hg after 3 minutes of standing, and pulse is 98/min. The patient appears pale but is otherwise in no distress. Lung auscultation is normal. Cardiac examination is unremarkable. The abdomen is soft and nondistended with mild epigastric tenderness and hyperactive bowel sounds. Rectal examination shows occult blood-positive melenic stool. Laboratory results are as follows:  Adequate venous access is established, and intravenous crystalloids and pantoprazole are started. Preparation for upper gastrointestinal endoscopy is made. Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.9/5  (90)
(90) A 19-year-old woman, gravida 1 para 0, at 10 weeks gestation comes to the emergency room due to sudden-onset nausea, vomiting, and worsening abdominal pain. The nausea and vomiting began 3 days ago and were initially responsive to an over-the-counter antiemetic. However, for the last day, she has been unable to tolerate food and is now unable to tolerate liquids. For the past few hours, the patient has had severe pain in the right upper quadrant. She has not had any sick contacts, hematemesis, diarrhea, changes in stool color, or weight loss. The patient has sickle cell disease and had multiple episodes of dactylitis as a toddler; however, the last acute pain episode requiring hospitalization occurred several years ago. She was on penicillin prophylaxis until age 5 and is taking no daily medications. The patient is up to date on vaccinations. She was treated for trichomoniasis 2 years ago; recent sexually transmitted infection screening was negative. Temperature is 38.3 C (100.9 F), blood pressure is 140/80 mm Hg, pulse is 88/min, and respirations are 20/min. Pulse oximetry is 98% on room air. BMI is 21 kg/m2. Examination shows darkening of the sclerae. Cardiac examination is normal, and the lungs are clear to auscultation. The right upper quadrant is tender on abdominal examination, but there is no lower abdominal pain, rebound, or guarding. Pelvic examination shows no uterine tenderness. Deep tendon reflexes are 2+. Laboratory results are as follows:  Ultrasound reveals a 10-week intrauterine gestation with fetal cardiac activity. Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.8/5 (75)
(75) A 46-year-old truck driver comes to the office due to fatigue. He has consumed energy drinks during the past 3 months to complete his driving routes. He sleeps most of the day on weekends and avoids his wife and kids. The patient says, "I even slept through my son's baseball game. I felt really bad about that." He has a history of chronic back and knee pain due to a motorcycle accident. The patient's medications include naproxen. He drinks a few beers with friends but has not socialized much lately. The patient's wife says that he is never there for her and they fight constantly. He has no history of manic symptoms or other psychiatric history. Physical examination and routine laboratory studies are unremarkable. Mental status examination shows depressed mood and sad affect. The patient says he has had thoughts of suicide but would never do anything because of his children. He is diagnosed with depression and started on sertraline. He returns for a 3-week follow-up, reporting little change. The patient says, "Some days I think I'm feeling a little better, but other days are really bad. I don't know about these pills. I've been taking them and don't have any side effects, but I still feel pretty bad."
Additional history shows that the patient was drinking 4 or 5 beers at the end of the day to help him fall asleep. He also obtained amphetamine/dextroamphetamine and some oxycodone pills from a friend and used these daily to manage his back pain and stay alert during his most recent road trip. The physician counsels the patient on the adverse effects of substance use and explains how alcohol, stimulants, and opiates may be contributing to his symptoms. The patient says he plans to take a medical leave of absence from work and abstain from alcohol, stimulants, and pain medications. He continues taking sertraline for his depression. At the patient's next follow-up a month later, he is doing well and not using any alcohol, stimulants, or opiates. His depression has improved, and he is attending Alcoholics Anonymous meetings. The physician receives a letter from the patient's employer asking when he can return to work and if there are any restrictions or safety concerns. The patient has signed a release of information.
Which of the following would be the most appropriate response to the employer?
(Multiple Choice)
4.8/5 (88)
(88) A 3-day-old boy is in the nursery for routine evaluation. He is breastfed exclusively and is passing adequate urine and stool. He was born to a 22-year-old African American woman with an unremarkable prenatal course. Prenatal laboratory studies showed a maternal blood type O positive. The infant was delivered by repeat cesarean section at 39 weeks gestation, and his blood type is O positive. A transcutaneous bilirubin level obtained at 24 hours of life was 3.4 mg/dL, which was considered low risk. He has a healthy older sister who did not have jaundice in the newborn period. Vital signs are normal. Physical examination shows jaundice extending from the head to the thighs. The lungs are clear to auscultation. Abdominal examination reveals no tenderness, distension, or organomegaly. Laboratory results from 72 hours of life are as follows: 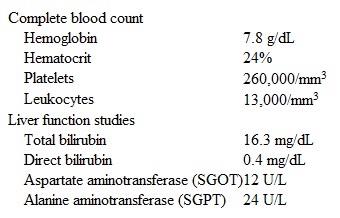 Direct Coombs test is negative. Serum bilirubin repeated 4 hours later is 20 mg/dL, and phototherapy treatment is initiated. Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.7/5 (71)
(71) A 64-year-old man comes to the physician for follow-up of an abnormal test. He was hospitalized a week earlier for an episode of acute urinary retention provoked by amitriptyline. His other medical problems include post-herpetic neuralgia, hypertension, hyperlipidemia, and a stable abdominal aortic aneurysm. He is a former smoker and his father had prostate cancer. Physical examination during the admission showed a moderately enlarged, nontender prostate with no nodularity. The obstruction was relieved by a Foley catheter, and amitriptyline was stopped. The patient has had no voiding difficulties or other urinary symptoms since being discharged. Blood tests at the time of hospital admission showed a white blood cell count of 12,000/µL, creatinine of 1.4 mg/dL, and serum prostate-specific antigen of 7.5 ng/mL (normal <4 ng/mL). No prior prostate-specific antigen levels are available for comparison. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (73)
(73) A 35-year-old Caucasian man is seen in the emergency department for the evaluation of fever, weakness, generalized abdominal pain, and bloody stools. He denies any vomiting but his appetite has been poor. He was diagnosed with ulcerative colitis six months ago and he has been on and off sulfasalazine treatment. His flare-up started four days ago, and rapidly progressed to his having multiple bloody bowel movements and severe abdominal pain. He is a current smoker, but he has been trying to quit. He has not been taking any antibiotics recently and he denies recent travel. His temperature is 100 F (37.8 C), heart rate is 124/min, and blood pressure is 106/72 mmHg. His mucous membranes appear dry. Bowel sounds are hypoactive. There is generalized abdominal tenderness and distension without any rebound tenderness or guarding. The percussion note is tympanitic. Item 1 of 2
Which of the following is the best initial step for managing this patient?
(Multiple Choice)
4.9/5 (93)
(93) A 28-year-old woman, gravida 1 para 0, at 37 weeks gestation comes to the emergency department due to leakage of fluid and painful uterine contractions that occur every 2-5 minutes. The patient has a spontaneous dichorionic/diamniotic twin gestation; her pregnancy has otherwise been uncomplicated. Serial ultrasounds throughout the pregnancy have consistently shown concordant growth of the twins. The patient has no chronic medical conditions and has had no surgery. She takes a daily prenatal vitamin. Examination confirms rupture of membranes; on digital examination the cervix is 5 cm dilated. Bedside ultrasound reveals that both twins are in vertex presentation. The patient is admitted to the hospital for labor, and epidural analgesia is administered. Twin A is delivered vaginally 8 hours after admission, with Apgars of 8 and 9 at 1 and 5 minutes, respectively. The patient is reexamined and the cervix has contracted to 9 cm, 100% effaced, with the vertex of twin B at −2 station. The amniotic membranes are intact. Fetal heart tracing is category 1. Tocometry shows contractions every 2-3 minutes. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (90)
(90) A 30-year-old woman comes to the office for preconception counseling. She has a history of rheumatic heart disease and underwent mechanical mitral valve replacement 5 years ago. The patient has been taking warfarin and low-dose aspirin since the procedure and has had no complications or adverse reactions. She has no history of other chronic medical conditions or surgeries. The patient recently began taking folic acid daily and is planning on discontinuing her progestin-releasing intrauterine device in the next few months. She does not use tobacco, alcohol, or illicit drugs. Family history is significant for a grandmother with a recent hip replacement complicated by a postoperative pulmonary embolism. Blood pressure is 110/70 mm Hg and pulse is 78/min. BMI is 23 kg/m2. Physical examination is without abnormalities, other than a large sternotomy scar. The patient expresses concern about the possible adverse effects of warfarin on the baby and her pregnancy. Which of the following is the most appropriate recommendation for this patient?
(Multiple Choice)
4.9/5 (77)
(77) A 51-year-old woman comes to the office due to bilateral nipple discharge that she first noticed 3 weeks ago. The discharge is expressed only with manipulation and is not bloody or rust-colored. The patient has had no breast pain, masses, or skin changes. Since menopause at age 50, she has taken soy and vitamin E for frequent hot flashes. In addition, she has hypertension that is well controlled by a single medication. She had 2 cesarean deliveries. The patient drinks a glass of wine occasionally and does not use tobacco or illicit drugs. Her grandmother died from metastatic breast cancer at age 85. Blood pressure is 140/80 mm Hg and pulse is 80/min. BMI is 27 kg/m2. Bilateral breast examination reveals no masses, tenderness, or skin changes. A clear yellow discharge is expressed from the nipples bilaterally. There is no axillary or supraclavicular lymphadenopathy. Urine pregnancy test is negative, and other laboratory results are as follows:  Bilateral mammogram and breast ultrasound are both normal. Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (75)
(75) An 18-year-old man comes to the physician for daytime sleepiness lasting several months. The patient recently started college, has difficulty staying awake during classes, and often falls asleep suddenly even though he "gets a good night's sleep." He typically goes to bed at 2 am and sleeps until at least 9 am, usually later. The patient's sleep pattern at night is fragmented. He wakes frequently but is usually able to go back to sleep within a few minutes. He does not snore or wake up gasping. The patient feels like "someone is in the room with me when I'm just falling asleep and I sometimes hear my name being called." His past medical history is otherwise insignificant. The patient does not use tobacco or alcohol. Blood pressure is 120/70 mm Hg and heart rate is 70/min. His body mass index is 23 kg/m2. The appropriate treatment is initiated, but the patient returns in 4 weeks and says that his symptoms have not improved. He recently had "some little troubles" in his family, and has felt sudden onset of muscle weakness and falls, especially during arguments with his family members. What is the best next step in management of this patient?
(Multiple Choice)
5.0/5 (77)
(77) A 38-year-old man with a history of schizophrenia is brought to the emergency department by police for a court-ordered evaluation. His mother requested that the patient be involuntarily committed after he refused voluntary hospitalization. She says that his illness was controlled with an injectable antipsychotic. She does not remember the name of the medication, but he received it once a month. Four months ago, the patient stopped going to his psychiatrist to receive the injection. His mother has seen a continuous deterioration in his overall functioning, especially within the last few weeks. Temperature is 37 C (98.6 F), blood pressure is 132/80 mm Hg, pulse is 88/min, and respirations are 14/min. Laboratory results are within normal limits, and a urine toxicology screen is negative. During the evaluation, the patient does not respond to any questions. He sits motionless on the edge of the bed, staring at the wall in front of him. During the physical examination, the resident picks up the patient's arm and places it over his head to evaluate range of motion. When the resident releases the arm, the arm stays in place above the patient's head. The resident then purposefully moves it down 30 degrees and the arm, once again, stays in the new location. Which of the following would be the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (70)
(70) A 7-year-old boy is brought to the emergency department due to rash, abdominal pain, and nausea. The rash first appeared 2 days ago. According to his father, a few initial red, round lesions on the back of both thighs now seem to have "merged together" and spread "all over his legs and buttocks." The rash is not itchy or painful. The abdominal pain and nausea began today and have been intermittent. The boy's appetite is decreased but he has no vomiting or diarrhea. His last bowel movement was yesterday and appeared normal. Other than an upper respiratory infection last week, the patient has been healthy and takes no medications. He went to a family barbeque last week and ate a hamburger and hot dog. Vaccinations are up to date and he has no allergies. His temperature is 36.7 C (98 F), blood pressure is 110/65 mm Hg, and pulse is 105/min. On physical examination, his abdomen is soft, nondistended, and mildly tender to palpation in the periumbilical region. Skin examination shows a non-blanching purple rash on his lower extremities and buttocks. Stool guaiac is positive. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (73)
(73) An elderly male is brought to the emergency department by the police when he was found wandering on the street in the night. He is confused, disoriented, and intermittently complaining of generalized abdominal pain and thirst. Any further history is unobtainable. His blood pressure is 110/80 mmHg, pulse is 98/min, temperature is 36.7C (98 F) and respirations are 22/min. There is no abdominal rigidity or rebound tenderness. Laboratory examination shows that his urine is positive for ketones. His plasma glucose level is 167 mg/dL. Other laboratory results are pending.
What is the best next step in the management of this patient?
(Multiple Choice)
4.9/5 (72)
(72) A 40-year-old woman is brought to the emergency department by paramedics after a motor vehicle collision. She was driving and wearing a seatbelt when her car was hit by another vehicle from the opposite direction. Her car went off the road and hit a tree. When paramedics arrived at the scene, the patient was noted to have an open femur fracture but was alert and oriented. Her medical issues include hyperlipidemia and mitral valve prolapse with mild regurgitation. She takes no medications. The patient undergoes open reduction and internal fixation of the femur fracture. She receives intravenous fluids and pain control postoperatively. The next morning she experiences left-sided chest discomfort and shortness of breath. Temperature is 37.6 C (99.7 F), blood pressure is 120/70 mm Hg, pulse is 100/min, and respirations are 30/min. Pulse oximetry shows 84% on room air. Physical examination reveals an area of tenderness over the left chest wall where the seatbelt was placed. On pulmonary examination, the patient has rales over the left upper lung. A 2/6 holosystolic murmur is present over the cardiac apex. Laboratory results are as follows:
 ECG shows sinus tachycardia with no ST-segment or T-wave changes. Chest x-ray shows irregular opacification predominantly of the left upper lung.
What is the most likely cause of this patient's respiratory symptoms?
ECG shows sinus tachycardia with no ST-segment or T-wave changes. Chest x-ray shows irregular opacification predominantly of the left upper lung.
What is the most likely cause of this patient's respiratory symptoms? (Multiple Choice)
4.9/5 (76)
(76) A 58-year-old woman comes to the office for follow-up for smoking cessation. Four weeks ago, the patient asked to be started on nicotine replacement therapy and was prescribed a maximal-dose nicotine transdermal patch with nicotine gum. Since then, smoking has been reduced from 2 packs a day to less than a pack a day. Medical history includes hypertension, type 2 diabetes mellitus, and peripheral artery disease. Blood pressure is 132/84 mm Hg and pulse is 86/min. BMI is 32 kg/m2. She is determined to quit smoking and requests that varenicline be added to her therapy. In combining these two therapies, this patient is at increased risk for which of the following serious complications?
(Multiple Choice)
4.9/5 (98)
(98) A 69-year-old man comes to the office for a follow-up visit. During a recent screening colonoscopy, he underwent complete excision of an 18-mm pedunculated polyp found in the ascending colon. Biopsy showed a high-grade dysplastic villous adenoma without involvement of the stalk or its margins There was no vascular or lymphatic invasion or other features of adenocarcinoma. The patient reports no symptoms and has no family history of colon polyps or colorectal cancer. He is otherwise in good health and has no other medical conditions. No abnormalities are noted on physical examination. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (77)
(77) A 53-year-old man comes to the office due to intermittent abdominal pain for the past 6 months. He describes the pain as sharp, located across his mid-abdomen, and relieved with sitting upright. The patient also describes postprandial bloating and discomfort during these episodes. He has observed that the pain is more noticeable shortly after meals. The painful episodes last minutes to hours at a time and then spontaneously resolve. His symptoms are becoming progressively more severe and frequent, but currently he is not experiencing pain. The patient has frequent large, loose stools that require multiple flushes. He reports being hospitalized multiple times in the past for abdominal pain but does not recall a specific diagnosis, and no records of these hospitalizations are available. The patient has no dysphagia, odynophagia, vomiting, black stools, or blood in the stool. He reports a 6.8-kg (15-lb) weight loss over the last 6 months. The patient drinks 4 or 5 bottles of beer daily and occasionally liquor. He does not smoke or use illicit drugs. Medications include over-the-counter antacids and acetaminophen. Temperature is 36.4 C (97.5 F), pulse is 86/min, blood pressure is 122/78 mm Hg, and respirations are 12/min. BMI is 21 kg/m2. The lungs are clear to auscultation. The abdomen is tender to palpation, but soft and nondistended. There is no rebound tenderness, rigidity, hepatomegaly, or splenomegaly. The remainder of the physical examination is normal. Laboratory results are as follows:
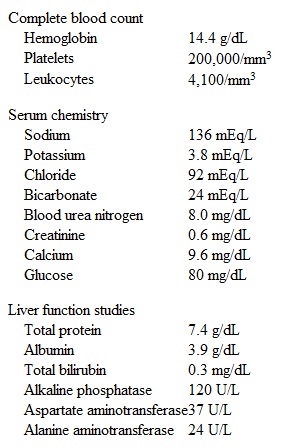 Which of the following tests is most likely to provide the diagnosis?
 (Multiple Choice)
4.8/5 (74)
(74) A 62-year-old man comes to the emergency department due to periumbilical abdominal pain. The patient says, "The pain suddenly began one hour ago and has been constant. I never had such severe pain in my life, and nothing makes it better. I also have nausea, and I vomited green-colored liquid once." Two weeks ago, the patient was hospitalized after experiencing chest and epigastric pain and was diagnosed with ST elevation myocardial infarction. He underwent percutaneous coronary intervention with stenting to the left anterior descending artery. He has been taking dual antiplatelet therapy since then. The patient's other medical conditions include hypertension, hyperlipidemia, and obstructive sleep apnea. He is a former smoker with a 20-pack-year smoking history and does not use alcohol or illicit drugs. On examination, the patient appears to be in significant pain. Temperature is 37.2 C (99 F), blood pressure is 140/85 mm Hg, pulse is 90/min, and respirations are 22/min. Lungs are clear to auscultation, and heart sounds are normal with no murmur. The abdomen is nondistended and soft with mild generalized tenderness. There is no guarding or rebound tenderness. Bowel sounds are normal. Stool testing for occult blood is negative. Laboratory results are as follows: 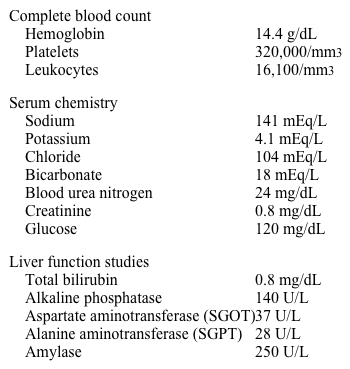 ECG shows normal sinus rhythm with deep Q waves in the anterior leads. Which of the following is most likely to establish the diagnosis in this patient?
 (Multiple Choice)
4.8/5 (80)
(80) A 26-year-old woman comes to the emergency department due to diarrhea. For the last 2 days she has had abrupt-onset diarrhea associated with crampy lower abdominal pain and fatigue. The patient is experiencing 4-6 watery bowel movements daily with visible blood throughout the stool. She reports no ill contacts and has not traveled outside the United States in the last 2 years. Medical history is notable only for a severe peanut allergy, and her only medication is an oral contraceptive. The patient does not use alcohol, but smokes up to 5 cigarettes daily and occasionally uses marijuana. Temperature is 37.5 C (99.5 F), blood pressure is 110/76 mm Hg, and pulse is 90/min. Abdominal examination reveals normal bowel sounds with mild diffuse tenderness and no peritoneal signs. Laboratory results are as follows:  Which of the following is the most appropriate response to this patient?
 (Multiple Choice)
4.8/5 (71)
(71) A newborn boy is evaluated on arrival in the nursery. He was born 3 hours ago by spontaneous vaginal delivery at 40 weeks gestation after an uncomplicated pregnancy. Apgar scores were 9 at 1 minute and 10 at 5 minutes after birth. His mother has no significant medical history and does not take any medications. Temperature is 36.7 C (98 F), pulse is 124/min, and respirations are 26/min. He is awake, alert, and active with a strong cry. His head is normocephalic and atraumatic with an open flat anterior fontanelle. Pupils are equal and reactive to light and accommodation, and red reflexes are present bilaterally. The nares are patent, there is no cleft lip or palate, and the pharynx is not erythematous. Clavicles are intact without crepitus. S1 and S2 are normal without murmurs, and lungs are clear to auscultation bilaterally. The abdomen is soft, nontender, and nondistended with normal bowel sounds and no organomegaly. Femoral pulses are normal and symmetrical. All extremities move spontaneously and there is no edema. There are no rashes, skin lesions, or jaundice, but the complexion appears ruddy with generalized erythema. Blood samples obtained from the heel through simple prick method reveal a hematocrit of 70%. Repeat testing revealed a hematocrit of 65%. The patient is re-evaluated in the nursery and appears comfortable, with no tachycardia or respiratory distress. He feeds slowly but has no emesis, and voids spontaneously after his first feed. A decision is made to observe the child without intervention. Approximately 12 hours later, he appears irritable and lethargic. The infant has refused all subsequent feeds and has had decreased urine output. Nursery staff observed an episode of apnea. Temperature is 37.4 C (99.3 F), pulse is 170/min, and respirations are 60/min. Physical examination shows a drowsy, hypotonic, poorly responsive newborn. The fontanelle is open and flat. Pupils are equal and reactive with normal red reflexes. There is no rhinorrhea. Oral mucosa is moist. S1 and S2 are present without murmurs. On pulmonary examination there are no wheezes or rales, but there are intercostal retractions. The skin is erythematous and ruddy, and there is cyanosis of the fingertips. There are no focal neurologic deficits. Laboratory results from peripheral blood draw are as follows:
 The patient is transferred to the neonatal intensive care unit, and treatment with intravenous fluids and glucose is initiated. His symptoms fail to improve, and his hematocrit after several hours is 71%. What is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.8/5 (79)
(79) Showing 601 - 620 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)