



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


A 5-week-old boy is brought to the office by his mother due to vomiting. The mother explains, "Over the past 4 days, my son has been vomiting forcefully right after drinking his formula. He used to spit up after feeding, but it has been getting worse, and now, he seems to throw up everything he eats." The emesis is the color of milk. The patient has had fewer wet diapers today and a single stool yesterday. He was born at 39 weeks gestation after an uncomplicated pregnancy. Newborn metabolic screening was normal. Medical history is notable for switching to formula at age 2 weeks due to low breast milk production. At that time, the patient was at the 25th percentile for length, weight, and head circumference. Today, he is at the 10th percentile for weight, although length and head circumference remain at the 25th percentile. Temperature is 36.7 C (98.1 F) and pulse is 169/min. Physical examination shows an awake, alert, slightly fussy infant. The anterior fontanelle is open and mildly sunken. The lips and mucous membranes are slightly dry. Cardiopulmonary examination shows no abnormalities. The abdomen is soft and nondistended with active bowel sounds, although waves of peristalsis are visible. There is no hepatosplenomegaly or tenderness to palpation. Serum chemistry is pending. The diagnosis is confirmed. Which of the following is the best next step in management of this patient?
(Multiple Choice)
5.0/5  (78)
(78) A 40-year-old man comes to the office for follow-up of type 1 diabetes mellitus. He was diagnosed 3 years ago when he was admitted to the hospital for diabetic ketoacidosis. The diabetes is treated with a continuous subcutaneous insulin infusion via an insulin pump, and most blood glucose levels are within 80-120 mg/dL with no significant hypoglycemic episodes. The patient exercises 5 days a week and follows strict dietary restrictions; he has avoided eating "junk food" apart from a small slice of cake on his birthday 3 months ago. Medical history is notable only for mild vitiligo, and his only other medication is a daily multivitamin. The patient does not use tobacco, alcohol, or illicit drugs. Family history is negative for diabetes mellitus and premature coronary artery disease. Blood pressure is 126/80 mm Hg and pulse is 68/min. BMI is 23.4 kg/m2. Physical examination, including lower extremity monofilament testing, is normal. Laboratory results are as follows: 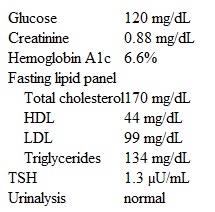 Which of the following is the best next step in management of this patient's condition?
 (Multiple Choice)
4.9/5 (73)
(73) A 30-year-old woman comes to the emergency department due to 12 hours of severe abdominal pain, which radiates to her back and is associated with nausea and vomiting. She has no chronic medical conditions. There is no family history of premature coronary artery disease. She does not use tobacco or alcohol. Temperature is 37.7 C (99.9 F), blood pressure is 120/90 mm Hg, pulse is 85/min, and respirations are 18/min. BMI is 34 kg/m2. The abdomen is tender to palpation but without rebound or involuntary guarding. Laboratory results are as follows: 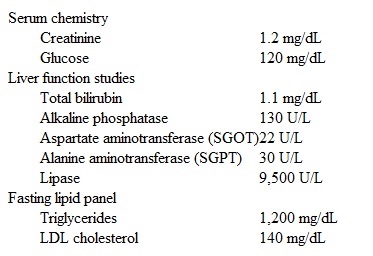 Ultrasound of the right upper quadrant shows pancreatic edema but is otherwise unrevealing. In addition to an infusion of lactated Ringer solution and pain medication, the patient is treated with intravenous insulin and dextrose solution. Her symptoms and laboratory studies improve after 3 days. Which of the following is recommended to prevent recurrence in this patient?
 (Multiple Choice)
4.7/5 (81)
(81) A 6-year-old boy is brought to the emergency department by his parents due to a dog bite. Approximately 16 hours ago, the patient was playing with the family dog in their backyard when the dog bit his left hand. The parents immediately washed the wound with soap and water and applied topical antibiotic ointment. When the child woke up this morning, he had increased pain exacerbated by making a fist. The dog is up to date with recommended immunizations. The boy has no medical issues and is current with his immunizations. Vital signs are within normal limits. On physical examination, a 2-cm × 1-cm ragged laceration is seen on the dorsal left hand. There is minimal amount of serous drainage from the wound, and no redness or streaking is seen. Full range of motion is present. The wound is copiously irrigated with normal saline. X-ray of the hand is normal. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (83)
(83) A 63-year-old man with hypertension comes to the clinic for follow-up. He was last seen a year ago and has been maintained on amlodipine for the past 3 years. The patient has no symptoms and describes good exercise tolerance. He takes rosuvastatin for hyperlipidemia. The patient does not use tobacco, alcohol, or illicit drugs. Blood pressure is 132/78 mm Hg, and pulse is 82/min and regular. Oxygen saturation is 99%. Examination reveals a 2/6 ejection-type systolic murmur at the right second intercostal space. The patient's lungs are clear, and there is no peripheral edema. ECG shows normal sinus rhythm with nonspecific T wave abnormalities. He is referred for an echocardiogram, which reveals mild aortic sclerosis and left ventricular dilation with an ejection fraction of 35%. There are no regional wall motion abnormalities. Cardiac stress test is negative for ischemia. Which of the following is the best management for this patient?
(Multiple Choice)
4.9/5 (79)
(79) A 29-year-old woman with chronic anemia comes to the emergency department with fatigue and progressive dyspnea. Physical examination shows pallor but no jaundice. Lungs are clear on auscultation and abdominal examination is benign. Laboratory results are as follows:  Packed red blood cell transfusion is started. Thirty minutes later, the patient complains of severe bilateral flank pain. She has received multiple blood transfusions in the past, but all were uncomplicated. Her temperature is 38.3 C (101 F), blood pressure is 100/70 mm Hg, pulse is 120/min, and respirations are 16/min. Pulse oximetry is 97% on room air. Urine is dark. Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (78)
(78) A 12-year-old girl is brought to the office for evaluation of diarrhea that has been persistent over the past month. The patient has had 2 or 3 loose, greasy, foul-smelling stools a day and describes feeling "bloated and gassy." Her appetite is significantly decreased, and she has lost approximately 0.91 kg (2 lb). She has had no emesis or fever. Her parents and 16-year-old sister do not have diarrhea, and the family is not sure if the patient had any sick contacts with similar symptoms. Medical history is unremarkable and she takes no medications. She and her classmates went on a wilderness hiking trip 6 weeks ago, but there has been no other recent travel. Physical examination reveals hyperactive bowel sounds in all 4 quadrants but is otherwise unremarkable. Stool microscopy is positive for multiple cysts and several flagellated trophozoites with 2 nuclei, and the patient is started on antimicrobial therapy. In light of these results, classmates at her school undergo screening at the community health center, and stool samples from 4 of 26 students are positive for the same cysts. Which of the following is the best strategy to eliminate further spread of this infection?
(Multiple Choice)
4.8/5 (83)
(83) A 48-year-old man comes to the physician with a red skin lesion on his abdomen. He first noticed it 6 months ago and says that it has been enlarging recently. The lesion bleeds occasionally when disturbed but is otherwise asymptomatic. The patient has a history of hypertension and actinic keratosis. He has a 25-pack-year smoking history and drinks a 6-pack of beer daily. Physical examination findings are shown in the image below. 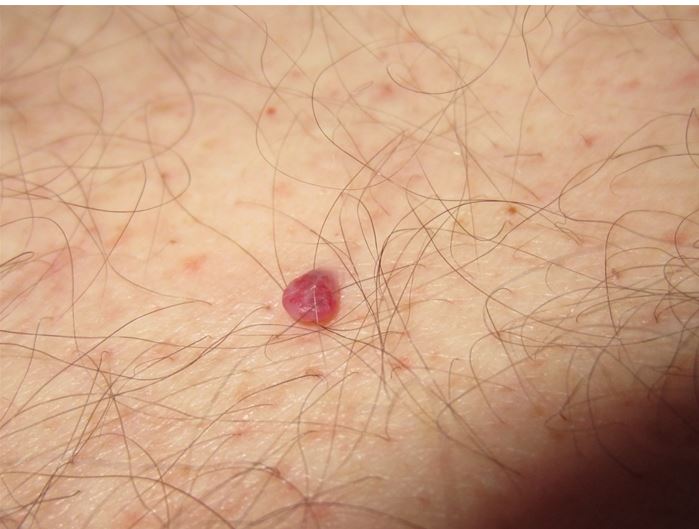 Which of the following is the most appropriate next step in management of this patient's skin lesion?
 (Multiple Choice)
4.9/5 (91)
(91) A 26-year-old woman comes to the clinic for routine HIV care. She mentions that she had "low platelets" when she was tested 2 months ago in an emergency department following a minor motor vehicle collision. The patient has no mucosal bleeding and does not bruise easily. Her menses have been normal. Two years ago, she was diagnosed with HIV after attempting to donate blood. The patient has not begun antiretroviral therapy, and she takes a multivitamin daily. Her temperature is 36.9 C (98.4 F), blood pressure is 116/78 mm Hg, pulse is 70/min, and respirations are 14/min. On examination, the patient's nasal and oropharyngeal mucosae appear normal. Her abdomen is nontender and nondistended, but the tip of the spleen is palpable on inspiration. There are no purpura or petechiae. Laboratory results are as follows:  Which of the following treatments is the best next step in management?
 (Multiple Choice)
4.8/5 (68)
(68) A 5-week-old boy is brought to the office by his mother due to vomiting. The mother explains, "Over the past 4 days, my son has been vomiting forcefully right after drinking his formula. He used to spit up after feeding, but it has been getting worse, and now, he seems to throw up everything he eats." The emesis is the color of milk. The patient has had fewer wet diapers today and a single stool yesterday. He was born at 39 weeks gestation after an uncomplicated pregnancy. Newborn metabolic screening was normal. Medical history is notable for switching to formula at age 2 weeks due to low breast milk production. At that time, the patient was at the 25th percentile for length, weight, and head circumference. Today, he is at the 10th percentile for weight, although length and head circumference remain at the 25th percentile. Temperature is 36.7 C (98.1 F) and pulse is 169/min. Physical examination shows an awake, alert, slightly fussy infant. The anterior fontanelle is open and mildly sunken. The lips and mucous membranes are slightly dry. Cardiopulmonary examination shows no abnormalities. The abdomen is soft and nondistended with active bowel sounds, although waves of peristalsis are visible. There is no hepatosplenomegaly or tenderness to palpation. Serum chemistry is pending.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (85)
(85) A 72-year-old man with diet-controlled diabetes mellitus comes to the emergency department with chest pain for the last 4 hours. He has never had similar pain before. The pain is accompanied by nausea and epigastric discomfort. Electrocardiogram shows normal sinus rhythm and ST-segment elevation in leads II, III, and aVF. Sublingual nitroglycerine and intravenous morphine are administered and the on-call interventional cardiologist is informed. Several minutes later, the patient complains of lightheadedness, nausea, and weakness. His blood pressure is 75/45 mm Hg, pulse is 60/min, and respirations are 15/min. The patient is diaphoretic and his extremities are cold. The lungs are clear on auscultation and no murmurs are appreciated on cardiac auscultation. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (80)
(80) A 29-year-old woman, gravida 1 para 0, at 26 weeks gestation comes to the office for a routine prenatal visit. She reports no contractions, vaginal bleeding, or leakage of fluid. There is good fetal movement. The patient has a history of polycystic ovarian syndrome. This pregnancy was conceived through ovulation induction but has otherwise been uncomplicated. She has no other chronic medical conditions or previous surgeries. The patient walks for 30-45 minutes 5 days a week. She takes prenatal vitamins and folate supplementation daily. She does not use tobacco, alcohol, or illicit drugs. Blood pressure is 130/80 mm Hg and pulse is 89/min. BMI is 27 kg/m2. Fetal heart tones are 150/min. Fundal height is 28 cm. Third-trimester laboratory results are as follows:  The appropriate evaluation is completed and the patient is diagnosed with gestational diabetes mellitus. She is started on a diabetic diet and continues to exercise regularly, with an hour of brisk walking on most days. The patient returns 3 weeks later for a routine prenatal visit and for evaluation of her glycemic control. She reports compliance with her diet and checks her fasting and post-prandial blood glucose values daily. Blood pressure is 136/70 mm Hg and pulse is 80/min. Fetal heart tones are 140/min. During the third week of the patient's regimen, fasting blood glucose values are 100-110 mg/dL, and 2-hour post-prandial glucose values are 122-158 mg/dL. Which of the following is the most accurate?
 (Multiple Choice)
4.9/5 (78)
(78) A 68-year-old Caucasian female is brought to the emergency room after she was found in her apartment obtunded with a fingerstick glucose level of 34 mg/dL. Two ampules of intravenous 50% dextrose are administered en route to the hospital. Her past medical history is significant for severe depression, type 2 diabetes mellitus, and osteoarthritis. Her home medications include glyburide and sertraline. Her blood pressure is 155/93 mmHg and her heart rate is 122/min. On examination in the ER, the patient is obtunded and diaphoretic. While she is being examined, she has an episode of generalized tonic-clonic seizures. A repeat blood glucose level is 33 mg/dL. Two ampules of intravenous 50% dextrose are given and the patient is started on 10% dextrose infusion. Which of the following is the best additional therapy for this patient?
(Multiple Choice)
4.9/5 (89)
(89) A 70-year-old woman is brought to the office by a friend who became concerned at finding her very weak and pale during a recent visit. The friend had not seen the patient in more than 6 months and was shocked at her condition. The patient says, "I feel very tired and have to sit down a lot to rest." She has had these symptoms for the past 10 months, but they are becoming progressively worse. She was diagnosed with primary myelofibrosis 2 years ago. The patient was not offered bone marrow transplantation due to her age; instead, she has received blood transfusions on more than 10 occasions, as well as erythropoietin and androgens, which have yielded poor results. She has no other medical problems and takes no other medication. The patient is widowed and lives with her son, who cares for her. Temperature is 36.7 C (98 F), blood pressure is 120/70 mm Hg, pulse is 110/min, and respirations are 20/min. She appears pale and undernourished, with significant muscular wasting. Auscultation reveals tachycardia. Hepatosplenomegaly is present. Laboratory results are as follows:  Three months ago, when her hemoglobin level was 8.0 g/dL and her hematocrit was 24%, the patient stated that she did not want any more blood transfusions or treatment. She understands that her condition is worsening but has not changed her mind, and continues to refuse any type of therapy. Which of the following is the most appropriate course of action?
 (Multiple Choice)
4.8/5 (83)
(83) A 32-year-old woman, gravida 2 para 0, comes to the office at 11 weeks gestation for a follow-up prenatal visit. The patient has no vaginal bleeding, abdominal cramping, or pelvic pain. At 6 weeks gestation, a transvaginal ultrasound revealed an intrauterine pregnancy consistent with gestational age and a 12-cm complex right adnexal mass with multiple septations. The patient has no chronic medical conditions. Previous surgeries include an appendectomy and suction curettage for a missed abortion. Menarche was at age 10 and she has regular menstrual cycles. Before attempting to conceive, the patient used a copper-containing intrauterine device for contraception, which was removed 8 months ago. She takes a prenatal vitamin and iron supplementation daily. The patient does not use tobacco, alcohol, or illicit drugs. Family history is significant for a grandmother who died from breast cancer at age 40. Temperature is 36.7 C (98 F), blood pressure is 100/60 mm Hg, and pulse is 80/min. She has gained 2 kg (4.4 lb) during this pregnancy. The abdomen is soft, nontender, and without rebound or guarding. A repeat ultrasound demonstrates a fetus measuring 11 weeks gestation with a heart rate of 160/min. The right adnexal mass has no change in appearance, but has increased to 13 cm in size. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (71)
(71) A 58-year-old female is complaining of weight gain for the past two years. She suspects a hormonal cause for her weight gain because she has not changed her activity or diet for the last several years. She also feels very tired and weak. She experiences difficulty in climbing the stairs and in combing her hair. She has mild hypertension and type II diabetes mellitus. She is currently on metformin, hydrochlorothiazide, and atenolol. She does not smoke cigarettes or drink alcohol. She had menopause when she was 48 years old. Her blood pressure is 130/70 mm Hg, heart rate is 88/min, and temperature is 98F (36.7C). She weighs 200 lbs, and is 5'2" tall (she was 5' 4" tall 5 years ago). Physical examination reveals a significantly overweight patient with prominent fat distributed in the trunk region. Her extremities seem thin when compared to her trunk. Her face is round and plethoric. She has a buffalo hump. She does not have any significant hirsutism or temporal balding. Her abdomen is distended and has wide, multiple, violaceous striae. There is mild proximal weakness of her lower extremities. The 24-hour urinary cortisol level is over three times above the upper limit of normal range. High-dose dexamethasone suppression test does not suppress the serum cortisol level. Plasma ACTH levels are undetectable. What is the next best step in the management of this patient?
(Multiple Choice)
4.8/5 (78)
(78) A 22-year-old woman is brought to the emergency department after overdosing on benzodiazepines. On presentation, her speech is slurred and her gait is unsteady. She is admitted to the hospital and improves with supportive care. When questioned later, she states that she had wanted to die because her boyfriend of 4 months ended their relationship a week ago. Currently she is less depressed and no longer suicidal, and feels that "he was the worst person for me." The patient describes "mood swings" since she was a teenager characterized by feelings of severe depression lasting from a few hours to several days. She has a history of 2 suicide attempts involving medication overdose. The patient has been treated with fluoxetine but stopped taking it 6 months ago because "it didn't seem to make a difference in how low I was feeling." Which of the following is the most effective treatment for this patient's condition?
(Multiple Choice)
4.8/5 (82)
(82) A 54-year-old woman comes to the emergency department with palpitations. She has experienced paroxysmal atrial fibrillation for the past 6 months. She has had extensive investigations for an underlying cause, including echocardiography and thyroid function testing, which were normal. The patient was started on amiodarone 6 weeks ago by her cardiologist and did well in the interim. She has had no change in her weight or intolerance to hot or cold temperatures. Her other medications include atenolol and low-dose aspirin. On physical examination, the patient appears comfortable. Her blood pressure is 132/82 mm Hg and heart rate is 112/min and irregular. Laboratory studies show a normal complete blood count and basic metabolic panel. ECG shows atrial fibrillation with rapid ventricular response. Thyroid function markers are as follows: 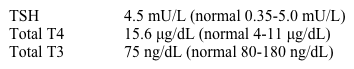 What is the best management for this patient?
 (Multiple Choice)
5.0/5 (83)
(83) A 52-year-old Caucasian woman comes to the office for a routine follow-up visit. She complains of weakness and fatigue for the past two weeks. She 'feels tired' even while doing minor household chores. She denies fever or any changes in appetite or weight. Three months ago, she underwent surgery for carcinoma of the breast and has been on chemotherapy ever since. She is a retired nurse and lives at home with her husband. She was diagnosed with hypertension twenty years ago. Her current therapy includes cyclophosphamide, methotrexate, 5-flurouracil, ondansetron, atenolol and famotidine. Her vital signs are within normal limits. Examination is unremarkable, except for moderate pallor. Rectal examination shows no abnormalities. Her lab results reveal the following: 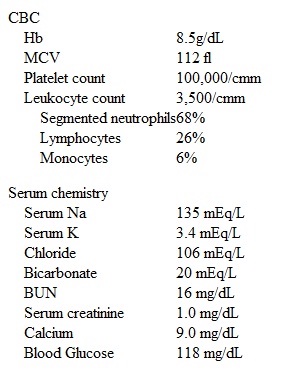 Which of the following is the most appropriate pharmacotherapy for this patient?
 (Multiple Choice)
4.7/5 (88)
(88) A 58-year-old man is brought to the emergency department 30 minutes after a generalized tonic-clonic seizure. His wife witnessed the event and says the patient was watching television, suddenly developed twitching of the left hand, and then lost consciousness and had generalized shaking. The event lasted approximately 1 minute. He spontaneously regained consciousness but has been confused. The patient has no history of seizure, head trauma, or other medical problems, but over the past few months he has had a persistent cough, anorexia, and fatigue and has lost 10 kg (22 lb). He has not seen a physician in 20 years and takes no medications. The patient is a current smoker with a 30-pack-year history and drinks alcohol occasionally. Temperature is 37.2 C (99 F), blood pressure is 138/86 mm Hg, and pulse is 94/min and regular. The patient is somnolent but easily arousable. Bilateral pupils are equal and briskly reactive to light. There is no focal weakness, and deep tendon reflexes are 2+ throughout. Digital clubbing is present and there are several right-sided, enlarged, nonmobile supraclavicular lymph nodes. Blood cell counts and serum chemistry studies are within normal limits, except for a serum calcium level of 10.6 mg/dL. MRI of the brain reveals a 1-cm mass in the gray-white junction of the right frontal lobe with mild surrounding edema. Imaging of the chest and abdomen reveals a 6-cm right lung mass, multiple enlarged hilar and mediastinal lymph nodes, and several liver lesions of 1-3 cm. Which of the following is the most appropriate next step in establishing the diagnosis in this patient?
(Multiple Choice)
4.9/5 (71)
(71) Showing 781 - 800 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)