



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


A 37-year-old woman comes to the office for evaluation of a left breast mass. The patient has had left breast discomfort before menses for the past year, with continuous pain over the past 3 months. She noticed the mass last week and reports no associated trauma or skin changes. At age 29, the patient underwent an excisional biopsy for a benign fibroadenoma in the right breast. She has type 2 diabetes mellitus that is well controlled with oral medications. The patient also has polycystic ovary syndrome and takes a combined estrogen progestin oral contraceptive for menstrual regulation. There is no family history of breast or ovarian cancer. She has no known allergies. The patient drinks 2 glasses of wine with dinner every night but does not use tobacco or illicit drugs. Blood pressure is 128/70 mm Hg and pulse is 73/min. BMI is 31 kg/m2. A 2-cm, smooth, tender, mobile mass is palpated in the upper outer quadrant of the left breast, 10 cm from the nipple. Both breasts are diffusely nodular, and a small biopsy scar is noted on the right breast. There is no nipple discharge or lymphadenopathy. Mammogram shows no calcifications. Ultrasound of the breast reveals a 2-cm, cystic mass with smooth borders, thin walls, and no internal septations. Fine-needle aspiration shows a thin, green fluid; after the procedure, the mass resolves completely and the patient's pain is gone. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5  (90)
(90) A 25-year-old man comes to the emergency department because of headache, palpitations, sweating, and irritability. He came directly from the health club, which he joined a few weeks ago. He states that after every exercise session during evening, before dinner, he develops similar symptoms and he gets symptomatic relief by consuming granola bars. He was diagnosed with type 1 diabetes mellitus eight years ago. He takes a combination of NPH and regular insulin before breakfast and supper. He states that he is very compliant with his insulin and meals. He does not have any other symptoms or chronic complications of diabetes. His blood pressure is 110/80 mmHg, pulse is 100/min, temperature is 36.7C (98F) and respirations are 14/min. He is slightly diaphoretic but completely alert and awake. His neurological examination is nonfocal. The rest of the examination is unremarkable.
Hypoglycemia is defined as a plasma glucose level of:
(Multiple Choice)
4.9/5 (83)
(83) A 22-year-old woman comes to the emergency department with fever and abdominal pain. A week ago, the patient had an elective termination of pregnancy at an outside facility. For the last 3 days, she has had increasingly purulent vaginal discharge, bleeding, and intermittent headaches. She has no nausea, vomiting, or diarrhea. The patient takes valacyclovir daily for recurrent herpes simplex. She has no other chronic medical problems or previous surgeries. The patient drinks alcohol once or twice a week and smokes 1 or 2 cigarettes daily. Temperature is 39 C (102.2 F), blood pressure is 93/52 mm Hg, pulse is 120/min, and respirations are 18/min. Neurologic examination is grossly normal. Lungs are clear to auscultation bilaterally. Abdominal palpation shows bilateral lower quadrant tenderness but no masses, rebound, or guarding. Purulent cervical discharge is noted on speculum examination. Bimanual pelvic examination reveals an 8-week-sized tender uterus with cervical motion tenderness; no adnexal masses are palpated. Bedside ultrasound reveals a 2×2 cm (0.8×0.8 in) echogenic mass in the endometrial cavity near the uterine fundus. A urine pregnancy test is positive. Intravenous fluid and antibiotics are administered. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (64)
(64) A 53-year-old woman comes to the office due to 3 days of fever, headaches, severe myalgias, and weakness. She has had dry cough but no wheezing, shortness of breath, or chest pain. The patient's sister recently had similar symptoms. The patient received the influenza vaccine a week ago. She has no other medical problems and takes no medications except over-the-counter supplemental vitamins. The patient does not use tobacco, alcohol, or illicit drugs. She is not allergic to any medications. Temperature is 38.2 C (100.8 F), blood pressure is 133/78 mm Hg, pulse is 101/min, and respirations are 14/min. BMI is 30 kg/m2. The patient appears flushed but in no distress. The oropharynx is hyperemic with no exudates. Mild cervical lymphadenopathy is present. Cardiopulmonary examination reveals no abnormalities. The abdomen is soft with no organomegaly. Throat swab for influenza A viral antigen is positive. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (80)
(80) A 32-year-old woman comes to the office for prenatal counseling. The patient recently married and hopes to start a family soon. She has a history of severe bipolar disorder and chronic insomnia. The patient has been treated previously with quetiapine, valproate, and citalopram. After several hospitalizations for severe manic and depressive episodes in her late 20s, she has been stable on lithium for the past 2 years. She also takes lorazepam occasionally for sleep. The patient has a history of 2 suicide attempts. She says, "I can't wait to be a mother, but I am worried about the effects of medication on the baby. I also don't want to get manic or depressed again. Being in the hospital is so awful and I am doing so well now. I have such a supportive husband and my work is going well." The patient receives counseling regarding management of her condition and treatment options during pregnancy. Which of the following is the most important medication to avoid prescribing at this time?
(Multiple Choice)
4.9/5 (81)
(81) A 26-year-old man is brought to the emergency department by his roommate, who found him lethargic in his apartment an hour ago. Earlier that day, the patient complained of headache and asked for aspirin. He also has felt weak and "exhausted" for the last 10 days. His past history is notable for intravenous heroin abuse, but periodic HIV screening has been negative. His temperature is 38.3 C (101 F), blood pressure is 112/70 mm Hg, and pulse is 102/min. The patient appears somnolent but follows simple commands. Needle tracks are seen on both arms. Pupils are symmetric and reactive. There are a few palatal petechiae on oral examination. The patient's neck is stiff. A 3/6 holosystolic murmur is heard at the apex. Lungs are clear to auscultation and the abdomen is nontender. He moves all extremities, and deep-tendon reflexes are symmetric. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (84)
(84) A 29-year-old man comes to the emergency department complaining of palpitations, sweating, and severe headache. His symptoms resolve spontaneously by the time he is evaluated. He has had at least 2 similar episodes during the past 2 months. The patient's family history is unremarkable. He does not use tobacco, alcohol, or illicit drugs. His primary care provider saw him after the first episode and prescribed an anxiolytic medication. However, the patient felt drowsy at his job and stopped the medication. Physical examination shows a thin man who appears anxious and diaphoretic. The thyroid is normal to palpation without any obvious nodules. His temperature is 36.7 C (98 F), blood pressure is 126/84 mm Hg, pulse is 86/min, and respirations are 16/min. During his prior emergency department visit for an identical episode, his blood pressure was 150/100 mm Hg and pulse was 120/min. The laboratory results at that time showed normal thyroid function tests. Endocrine studies yield results highly suspicious of a neuroendocrine tumor. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (76)
(76) A 32-year-old woman, gravida 1 para 0, at 19 weeks gestation comes to the emergency department due to vaginal pressure and spotting. Over the last few days, the patient has had clear vaginal discharge for which she has used sanitary napkins. Today she has had increasing pelvic pressure and has noticed blood spots on the sanitary napkins. She has had no cramping or pelvic pain; fetal movement has been normal. The patient's pregnancy was previously uncomplicated; initial prenatal laboratory testing was normal. She was scheduled to have an anatomy ultrasound later in the week. The patient has no chronic medical conditions and has had no previous surgeries. She takes a prenatal vitamin daily and acetaminophen as needed for headaches. She was treated for Chlamydia trachomatis cervicitis at age 20. She does not use tobacco, alcohol, or illicit drugs. Temperature is 36.7 C (98.1 F), blood pressure is 110/70 mm Hg, pulse is 65/min, and respirations are 18/min. Fetal heart rate is 145/min by Doppler ultrasound. Speculum examination shows amniotic membranes bulging at the vaginal introitus. There is no blood or pooling of fluid in the vaginal vault. Nitrazine paper does not turn blue on application of the vaginal discharge. The cervix is 3 cm dilated and 100% effaced on digital examination. The patient is informed of examination findings. She asks about the prognosis for this pregnancy. Which of the following is the most appropriate response to this patient at this time?
(Multiple Choice)
4.8/5 (70)
(70) A 55-year-old man comes to the office due to severe pain and swelling in his right big toe. He has hypertension, osteoarthritis, glucose intolerance controlled with diet, and recent peptic ulcer disease. The patient is not on medication for hypertension. On physical examination, his first metatarsophalangeal joint has diffuse swelling, and the skin surrounding the joint is erythematous. The joint is exquisitely tender to palpation and has severe restrictions in movement. Aspiration of the joint fluid reveals an inflammatory effusion with multiple negatively birefringent, needle-shaped crystals within polymorphonuclear cells. The patient is treated with colchicine and shows good response to therapy. Two weeks later, he comes for follow-up. Blood pressure is 152/93 mm Hg and pulse is 78/min. BMI is 36 kg/m2. Serum uric acid is 8.2 mg/dL, potassium is 4.1 mEq/L, serum creatinine is 1.2 mg/dL, and liver function tests are within normal limits. Which of the following is the best additional therapy for this patient?
(Multiple Choice)
4.9/5 (90)
(90) A 34-year-old woman comes to the office due to malaise and jaundice. The patient was in good health until about 4 weeks ago, when she developed joint pain, fatigue, and a pruritic rash over her trunk and extremities. The joint pain and rash resolved about a week ago, but the fatigue has persisted. Two days ago, the patient noticed some yellowish discoloration of the whites of her eyes and began to experience decreased appetite. However, she has been able to eat and drink without difficulty. Medical history includes irritable bowel syndrome and allergic rhinitis. Medications include docusate and intranasal fluticasone. She does not use any other over-the-counter medications. Immunization history is unknown. She is sexually active with 2 male partners and uses condoms inconsistently. The patient drinks on social occasions and does not use tobacco or illicit drugs. Temperature is 36.7 C (98 F), blood pressure is 110/64 mm Hg, and pulse is 68/min. BMI is 25 kg/m2. Physical examination is notable for moist mucous membranes, scleral icterus, and normal jugular venous pressure. Heart and lung sounds are normal. Abdominal examination reveals a palpable liver edge approximately 2 cm below the costal margin without tenderness. Bowel sounds are normoactive. The extremities are warm and without edema. The joints are nontender and without erythema. Neurologic examination is normal with no asterixis. The remainder of the physical examination is unremarkable. Laboratory results are as follows:
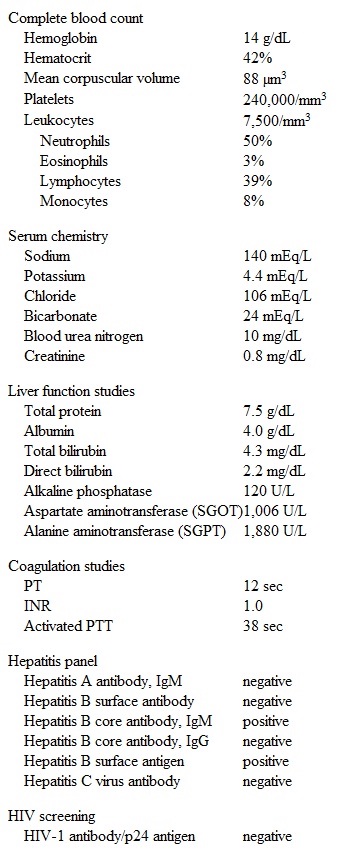 The patient voices concern about her prognosis. Which of the following is the approximate likelihood she will develop chronic hepatitis B?
 (Multiple Choice)
4.7/5 (78)
(78) A 79-year-old woman is brought to the emergency department by her daughter due to bloody stools. The patient has a 3-day history of occasionally passing blood with her stools but this morning she filled up the toilet bowl with bloody stools. She has not had another bowel movement since. She does not have any associated symptoms such as nausea, vomiting, or abdominal pain. Her past medical history includes mild dementia, hypertension, diet-controlled diabetes mellitus, and osteoarthritis. She does not smoke or drink alcohol. The patient takes a baby aspirin daily and nonsteroidal anti-inflammatory agents occasionally for hip pain. Her temperature is 36.7 C (98 F), heart rate is 89/min, blood pressure is 146/82 mm Hg, and respiratory rate is 16/min. She appears pale. Abdominal examination is unremarkable. Rectal examination reveals bright red blood in the rectal vault, without tenderness. Nasogastric aspirate shows copious amounts of bilious fluid. Laboratory results are as follows:  She is started on intravenous fluids and blood work is ordered including blood type and cross-match. Which of the following is the most appropriate next step in the management of this patient?
 (Multiple Choice)
4.9/5 (88)
(88) A 65-year-old woman comes to the office with a 6-month history of dry mouth. She says that she feels dry all day long and has to drink water. She also has had a sandy sensation in her eyes, especially after watching television for a while. Medical history is significant for long-term hypertension that is controlled with metoprolol. She does not smoke or consume alcohol. Her recent fasting blood glucose level was normal. Physical examination findings are within normal limits. Which of the following is the best next step in the management of this patient?
(Multiple Choice)
4.9/5 (74)
(74) A 38-year-old woman comes to the physician for a routine checkup. She has no current complaints. The patient's past medical history is significant for hypertension and type 2 diabetes mellitus. Her medications include low-dose hydrochlorothiazide, lisinopril, metformin, and glyburide. She smokes 1/2 pack of cigarettes daily and drinks alcohol occasionally. Her last menstrual period was 2 weeks ago. Blood pressure is 130/85 mm Hg and pulse is 85/min. The patient's body mass index is 32 kg/m2. The remainder of the physical examination is within normal limits. Her fasting blood glucose is 120 mg/dL and HbA1C level is 6.7%. Which of the following factors is the most significant predictor of future cardiovascular events in this patient?
(Multiple Choice)
4.8/5 (73)
(73) A retrospective, matched-cohort study is conducted to examine the effect of medical care provided by overnight physicians on the outcomes of their scheduled elective procedures performed during the day. Patients undergoing 1 of 5 elective daytime procedures performed by a physician who worked overnight were matched to patients undergoing the same procedure by the same physician on a day when the physician did not work overnight. The study outcome was a composite of patient death and complications. The study reported that the risk of the composite outcome was higher in patients who underwent a daytime procedure performed by a physician who had worked overnight compared to patients who underwent a procedure performed by a physician who had not worked overnight (22% vs. 20%, p = 0.04). Based on these results, what is the approximate percentage of deaths and complications that can be attributed to the physician having worked overnight before the scheduled elective procedures during the day?
(Multiple Choice)
4.7/5 (82)
(82) A 27-year-old man comes to the emergency department with sudden onset of shortness of breath. He ran out of his asthma medication 10 days ago. He has been intubated twice in the past 6 months due to severe asthma exacerbations. On physical examination, his temperature is 37.2 C (99 F), blood pressure is 142/64 mm Hg, heart rate is 110/min, and respirations are 28/min. His oxygen saturation is 84% on room air and improves to 94% on nonrebreather mask. The patient is alert but appears to be in respiratory distress with some use of accessory muscles of respiration. His lung examination shows equal, bilateral air entry with diffuse wheezing throughout both lung fields. His peak expiratory flow rate is 60% of his personal best, based on his prior admissions.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (79)
(79) A 46-year-old truck driver comes to the office due to fatigue. He has consumed energy drinks during the past 3 months to complete his driving routes. He sleeps most of the day on weekends and avoids his wife and kids. The patient says, "I even slept through my son's baseball game. I felt really bad about that." He has a history of chronic back and knee pain due to a motorcycle accident. The patient's medications include naproxen. He drinks a few beers with friends but has not socialized much lately. The patient's wife says that he is never there for her and they fight constantly. He has no history of manic symptoms or other psychiatric history. Physical examination and routine laboratory studies are unremarkable. Mental status examination shows depressed mood and sad affect. The patient says he has had thoughts of suicide but would never do anything because of his children. He is diagnosed with depression and started on sertraline. He returns for a 3-week follow-up, reporting little change. The patient says, "Some days I think I'm feeling a little better, but other days are really bad. I don't know about these pills. I've been taking them and don't have any side effects, but I still feel pretty bad."The patient returns for another follow-up 4 weeks later. He says, "At first, I really thought the medication was working and things were finally turning around for me. For a couple of weeks I felt less depressed, almost normal. I had more energy and was doing more activities with my kids and arguing less with my wife. Then I went on a long truck route halfway across the country, and things just started falling apart. Now, I'm not only depressed again, but I feel shaky and hyper at the same time. I needed to stay awake to drive for 16 hours straight, and then afterward I still couldn't fall asleep. My back has been hurting badly, too, and I had to take something stronger for the pain. One night, I even thought that my wife might be having an affair, but I know that's crazy!" On mental status examination, the patient is alert, anxious, and mildly tremulous. He has no suicidal thoughts. He is concerned that the sertraline has stopped working.
Which of the following is the most likely explanation for the patient's symptoms?
(Multiple Choice)
4.9/5 (75)
(75) A 45-year-old man comes to the office due to 2 months of worsening mid-abdominal pain, abdominal cramps, and black stools. He has also had fatigue and a 5-kg (11-lb) weight loss over the same period. The patient has a history of chronic diarrhea since adolescence and was diagnosed with celiac disease 10 years ago. His baseline diarrhea improves when he avoids dietary gluten, but he has difficulty doing so due to frequent work-related travel. The patient has no other chronic medical issues and takes a daily multivitamin. He does not use tobacco, alcohol, or illicit drugs. Vital signs are within normal limits. The patient appears thin and pale. The abdomen is mildly distended with mild generalized tenderness. There is no guarding or rebound tenderness. Bowel sounds are increased. Stool is positive for occult blood. Which of the following is the most likely cause of this patient's current symptoms?
(Multiple Choice)
5.0/5 (87)
(87) A 20-year-old college student comes to see you in the office for a physical exam before leaving for a vacation. She plans to go to the Caribbean for a two-week summer break. She has no medical problems. She takes an oral contraceptive pill regularly. She denies smoking, but admits to occasional alcohol intake on weekends. She plans to be out in the sun a lot, and is concerned about the possible skin damage from excessive sun exposure. You counsel her on sun protective behaviors and advise her to use a sunscreen with a SPF of 15 or more. Which of the following measures should you recommend to help her prevent or reduce further skin damage?
(Multiple Choice)
4.8/5 (79)
(79) A 60-year-old woman is transferred from an outpatient surgery facility to the emergency department due to diffuse abdominal pain, nausea, and vomiting. She developed these symptoms while waiting to be discharged following a routine colonoscopy. The patient has type 2 diabetes mellitus, which is managed with sitagliptin, canagliflozin, and insulin detemir; the insulin was held the night before the procedure. She was previously treated with metformin but was switched to canagliflozin due to persistent diarrhea. Since that time, the patient has had significant weight loss and an improvement in blood glucose levels. Other medical issues include hypertension and hyperlipidemia, for which she takes losartan, hydrochlorothiazide, and atorvastatin. Blood pressure is 110/70 mm Hg, pulse is 100/min, respirations are 24/min, and oxygen saturation is 99% on room air. BMI is 34 kg/m2. Oral mucous membranes are dry, but the remainder of the physical examination is unremarkable. Laboratory results are as follows:  Which of the following is the most likely cause of this patient's laboratory findings?
 (Multiple Choice)
4.9/5 (85)
(85) A girl at 39 weeks gestation is born via vaginal delivery to a 25-year-old primigravida. The patient's mother has no significant medical history and took no medications during pregnancy, but the parents moved several times, making prenatal care inconsistent. Family history is notable for a paternal cousin with cystic fibrosis and a maternal aunt with iron-deficiency anemia. Ultrasonography performed at 35 weeks gestation by the mother's current health care provider demonstrated a cystic sac over the infant's lumbar spine. Group B Streptococcus screening at 36 weeks gestation was negative. At birth, the infant's Apgar scores are 7 and 8, with a birth weight of 3.5 kg (7 lb 11 oz). Physical examination shows a red sac with an overlying membrane over the infant's lumbar spine. The suspected diagnosis is discussed with the infant's parents. Which of the following is the most common complication of this patient's condition?
(Multiple Choice)
4.9/5 (79)
(79) Showing 721 - 740 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)