



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


A 54-year old Caucasian man comes to the office complaining of fatigue, poor exercise tolerance, and an unexplained weight loss over the last 6 months. He does not use tobacco, alcohol, or drugs. His family history is noncontributory. He takes no medications. His vital signs are within normal limits. Examination reveals mild splenomegaly but no lymphadenopathy. Laboratory tests show the following:
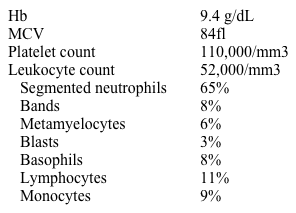 Cytogenetic testing reveals a bcr/abl translocation. Which of the following is the best initial treatment option for this patient?
 (Multiple Choice)
4.9/5  (94)
(94) An 82-year-old woman comes to the emergency department due to chest pain. The pain began when the patient was vacuuming and "felt as if someone placed my chest in a vise." The pain improved after resting for 30 minutes, but she called her daughter, who brought her to the hospital. The pain began again while she was walking into the waiting room. The patient also reports mild nausea, weakness, and lightheadedness. She has a history of hypertension, for which she takes losartan, and a prior upper gastrointestinal bleed for which she underwent treatment for Helicobacter pylori. She has hyperlipidemia but did not tolerate simvastatin in the past due to muscle aches. The patient is a nonsmoker. She drinks a glass of wine on social occasions. She has a younger brother who recently underwent coronary artery bypass graft surgery. Blood pressure is 152/92 mm Hg, pulse is 92/min, and oxygen saturation is 96% on room air. The patient appears mildly uncomfortable. Examination reveals jugular venous distension and diffuse lung crackles. On cardiac auscultation, a low-pitched extra heart sound just after S2 is appreciated at the apex. The abdomen is soft and there is trace lower extremity edema bilaterally. ECG shows ST-segment depression in leads I, aVL, and V3-V6. Which of the following medications should be avoided in this patient at this time?
(Multiple Choice)
4.9/5 (75)
(75) A 12-year-old girl is brought to the office for a preventive health maintenance examination. The patient's mother has noticed that over the last few months, her daughter "seems to sit sideways" and does not sit up straight when asked. The patient occasionally takes acetaminophen in the morning due to mild "aches and pains." She fractured her left femur in a horse-riding accident at age 8. Height and weight are at the 75th and 50th percentiles, respectively. Physical examination shows a well-appearing, nondysmorphic girl. Forward bend test demonstrates a right thoracic prominence that measures a 9-degree angle of trunk rotation and does not improve when a block is placed under the left foot. Flexion of the lumbar spine is normal and the patient is able to touch her toes. Lower extremity strength is normal. Patellar and Achilles deep tendon reflexes are 2+. Gait is normal. Posteroanterior and lateral x-rays of the spine are obtained, which reveal a Cobb angle of 5 degrees. Which of the following is the best next step in management of this patient's spinal problem?
(Multiple Choice)
4.8/5 (72)
(72) A 72-year-old woman is brought to the emergency department after a fall. The patient landed on her side and has extensive bruising over the right hip area. She was able to reach her phone and call an ambulance to bring her to the hospital. She says, "I lost my balance on the way to the bathroom. I usually have to get up to go to the bathroom once or twice a night." The patient has no history of lightheadedness, dizziness, or syncope. She leads an active lifestyle and walks 2 miles every day. Her medical problems include type 2 diabetes mellitus, urge incontinence, chronic insomnia, transient ischemic attacks, and osteoarthritis. Her daily medications include aspirin, glyburide, lorazepam, and naproxen. The patient lives alone. She does not use tobacco, alcohol, or illicit drugs. Vital signs are within normal limits. Physical examination and subsequent x-rays reveal a right-sided femoral neck fracture. Neurological examination is normal. The patient is admitted to the hospital and undergoes a hemiarthroplasty of her right hip. Her medications in the hospital include aspirin, insulin, calcium, vitamin D, subcutaneous heparin for deep venous thrombosis prevention, and oxycodone for pain control. Lorazepam was discontinued as it was thought to have contributed to her fall. Following surgery, the patient appears to be recovering well. On day 3 of hospital admission, however, she becomes very restless and agitated. She is oriented to person only and insists that she is in her own home. The patient demands to know "who stole my clothes and jewelry" and is verbally abusive toward the nursing staff. She is observed to be talking to her herself and says she sees her deceased father and hears his voice. Temperature is 37.8 C (100 F), blood pressure is 160/90 mm Hg, pulse is 106/min, and respirations are 24/min. Pulse oximetry is 98% on room air. Physical examination shows generalized tremors and is otherwise unchanged. All laboratory studies are normal. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (73)
(73) A 45-year-old woman comes to the office due to progressive stiffness, pain, and swelling of the joints in the hands and wrists for the past 3 months. The symptoms are worse when she wakes up and gradually improve after several hours. The patient also feels fatigued but has had no skin rashes, oral lesions, or fever. She recently began taking chlorthalidone for hypertension and takes no other medications. She works in a daycare center. The patient drinks alcohol occasionally and does not use tobacco or illicit drugs. Her mother had "arthritis" in her older age, and her sister has systemic lupus erythematosus. Temperature and other vital signs are within normal limits. Physical examination shows warmth, swelling, and tenderness of the second and third proximal interphalangeal joints, the metacarpophalangeal joints, and the wrists of both hands. The remainder of the examination shows no abnormalities.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (89)
(89) A 62-year-old man is brought to the emergency department due to shortness of breath, chest pain, and palpitations that started earlier today. For the past month, he has had intermittent palpitations accompanied by shortness of breath. This time the symptoms persisted and he called 911. Medical problems include hypertension, obesity, chronic obstructive pulmonary disease, myocardial infarction, and carotid artery stenosis. The patient underwent coronary artery bypass grafting surgery 4 years ago. He follows up with a cardiologist twice a year, and there has been no recent change in his medical regimen. He is an ex-smoker and consumes no alcohol. He has no known drug allergies. On initial evaluation in the emergency department, he appears uncomfortable and tachypneic. Immediate ECG shows atrial fibrillation with a rapid ventricular response (140-150/min), narrow QRS complexes, and T-wave inversion in leads V4 to V6. The patient is connected to a cardiac monitor. While the team is securing intravenous access, the patient becomes unresponsive. He has no palpable pulses over the major arteries. The cardiac monitor continues to show a narrow-complex tachycardia consistent with atrial fibrillation. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.7/5 (74)
(74) A 36-year-old woman, gravida 3 para 2, at 32 weeks gestation comes to the emergency department due to abdominal pain. The patient's symptoms started a day ago as mild right-sided abdominal pain. Since then, the pain has become increasingly severe and is accompanied by fever, heartburn, and diarrhea. The patient has had no contractions, vaginal bleeding, or leakage of fluid. Fetal movement is normal. The pregnancy has been uncomplicated. She has no chronic medical conditions and has had no surgeries. The patient takes a daily prenatal vitamin and does not use tobacco, alcohol, or illicit drugs. Temperature is 38.9 C (102 F), blood pressure is 140/80 mm Hg, and pulse is 112/min. Fetal heart rate monitor shows a baseline of 160/min, moderate variability, and no decelerations. Tocometry shows no contractions. Cardiopulmonary examination reveals tachycardia but a regular rhythm and no rubs. The lungs are clear to auscultation. Abdominal examination reveals tenderness throughout the right lower quadrant and flank but no uterine fundal or costovertebral angle tenderness. There is no rebound or guarding. McBurney point is nontender. Pelvic examination reveals no adnexal masses or tenderness. Laboratory results are as follows:  Item 1 of 2 Which of the following is the best next step in diagnosing this patient's condition?
 (Multiple Choice)
4.9/5 (91)
(91) A 39-year-old man with schizoaffective disorder comes to the office for a follow-up appointment. The patient has a history of 4 hospitalizations for manic and psychotic episodes and lives in a supervised group home. Three months ago, he was hospitalized for a manic episode characterized by euphoria, racing thoughts, and grandiose delusions of being a famous performer. At the time, he heard voices telling him that he was "chosen" and commanding him to "sing for glory." During the hospitalization, the patient was successfully treated with valproate and risperidone and continued on these medications following discharge. One month ago, a trial of lowering his risperidone dose was terminated when it resulted in an increased frequency of auditory hallucinations. At today's visit, the patient's mood remains stable but he feels restless and uncomfortable, reporting, "I can't seem to sit still or relax." The patient appears nervous and shakes his right leg constantly during the examination. At one point, he gets up and paces around the room. Vital signs and physical examination are unremarkable. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (85)
(85) A 32-year-old woman comes to the emergency department due to 7 days of fever and dry cough. She has also had progressive shortness of breath with minimal walking and climbing stairs. The patient was diagnosed with HIV infection a year ago and is not currently on antiretroviral treatment. She does not use tobacco, alcohol, or illicit drugs. Temperature is 38.4 C (101.1 F), blood pressure is 110/64 mm Hg, pulse is 106/min, and respiratory rate is 26/min. Pulse oxymetry is 87% on room air and decreases to 82% with minimal walking. Oropharyngeal thrush is present. Lung auscultation reveals scattered bilateral crackles and rhonchi. The abdomen is soft and nontender without organomegaly. No cyanosis, clubbing, or edema is present. Chest x-ray reveals diffuse interstitial opacities bilaterally. CD4 count is 85/mm3. The patient is admitted and started on empiric therapy. Twenty-four hours after admission, the induced sputum analysis is negative for Pneumocystis. On day 2 of hospitalization, the patient develops worsening dyspnea and hypoxia. Repeat chest x-ray reveals worsened interstitial infiltrate. Due to significant tachypnea and poor oxygenation, the patient is intubated. The patient is currently receiving trimethoprim-sulfamethoxazole, prednisone, ceftriaxone, and azithromycin. Blood cultures from admission are negative at 48 hours. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.7/5 (91)
(91) A 60-hour-old boy is evaluated in the newborn nursery prior to anticipated discharge. He was born via vaginal delivery with vacuum assistance at 38 weeks gestation. Prenatal maternal group B streptococcus screen was positive, for which the mother received antibiotics during labor and delivery. Other prenatal laboratory studies were normal. Maternal blood type is A+. On day of life 1, the patient was noted to have a well-demarcated scalp swelling that has remained stable in size. He is breastfed exclusively and has had 3 wet diapers in the last 24 hours. Physical examination shows an alert and active boy with appropriate tone and a strong cry. He has icteric sclerae, jaundice from the face to the lower abdomen, and a 2 x 3 cm scalp swelling over the right parietal area. The remainder of the examination is unremarkable. Laboratory results are as follows:  Phototherapy is initiated, and repeat total bilirubin 6 hours later is 17.1 mg/dL. The father says, "We really want to take our baby home. Can we supplement with formula and keep him by the window to get sunlight?" Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (78)
(78) A 70-year-old man is brought to the emergency department by his nephew due to redness and pain in his right leg. The patient lives alone and has no family except for the nephew, who occasionally checks on him. Other than a history of gastrointestinal bleeding, little is known about the patient's medical history. In the emergency department he is mildly febrile, but vital signs are otherwise normal. On physical examination, there is cellulitis of his lower right extremity and mildly tender hepatomegaly. Laboratory examination is normal except for a white blood cell count of 12,400/mm3, aspartate aminotransferase of 332 U/L, and alanine aminotransferase of 158 U/L. Chest x-ray and urinalysis are normal. The patient is admitted to the hospital and intravenous antibiotics are started. At the time of admission he appears calm and agrees to hospitalization. That night, the patient becomes irritable and restless. He is unable to sleep and becomes increasingly tremulous and diaphoretic, as well as argumentative with the nurse, whom he slaps on the hand as she tries to help him. Temperature is 37.2 C (99 F), blood pressure is 160/90 mm Hg, pulse is 108/min, respirations are 18/min, and pulse oximetry is 93% on room air. The patient appears cognitively intact. Which of the following is the most appropriate pharmacotherapy for this patient?
(Multiple Choice)
4.7/5 (78)
(78) A 34-year-old woman is admitted with a diagnosis of acute lymphoblastic leukemia (ALL). She is scheduled to receive induction chemotherapy with vincristine, doxorubicin, and prednisone. She has no other past medical history. She has never smoked or used recreational drugs. Which of the following tests is the most appropriate for monitoring this patient's condition while on chemotherapy?
(Multiple Choice)
4.8/5 (73)
(73) A 49-year-old woman comes to the physician requesting treatment for "this unattractive redness of my skin." In the past 3 months, she developed blemishes on her nose, cheeks, and chin. She now flushes intensely in response to hot or cold temperatures, emotion, and the consumption of spicy foods or alcohol. She has no history of dermatological problems. Physical examination shows a reddening of the central face, erythematous papules on the nose, and sporadic telangiectasias on the nose and cheeks as shown below. 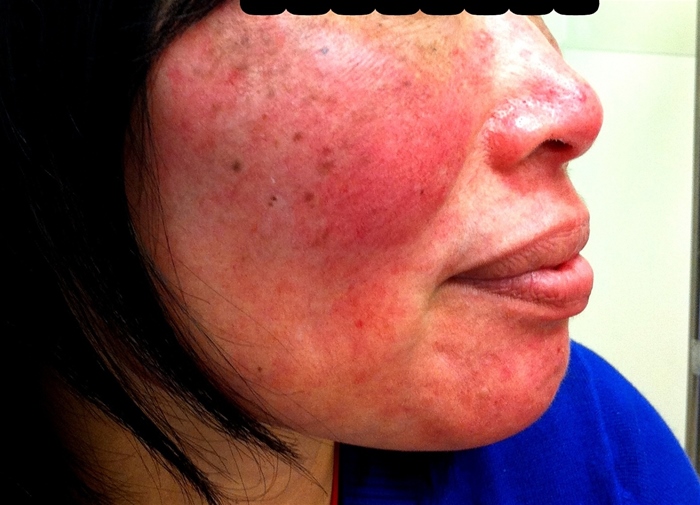 The appropriate action was taken. Which of the following complications is most frequently associated with this condition?
 (Multiple Choice)
4.7/5 (65)
(65) A 26-year-old man comes to the office after learning that one of his sexual partners tested positive for HIV. The patient has had intermittent headaches, malaise, nausea, and blurry vision over the last several weeks. He has had no fever, sore throat, skin rash, genital lesions, or weight loss. The patient has no prior history of sexually transmitted infections or chronic medical problems. He smokes a pack of cigarettes daily, consumes alcohol occasionally, and does not use illicit drugs. The patient has had multiple sexual partners over the last several years and does not use condoms consistently. Temperature is 37.1 C (98.8 F), blood pressure is 122/74 mm Hg, and pulse is 72/min. There is no scleral icterus, oropharyngeal lesions, or skin rash. Mild, generalized lymphadenopathy is present. Cardiopulmonary and abdominal examinations are normal. Cranial nerves, deep tendon reflexes, and sensation are normal. No nuchal rigidity is present. Ophthalmologic examination reveals no abnormalities. Screening HIV immunoassay is positive. Other laboratory studies are as follows:  A subsequent fluorescent treponemal antibody absorption test is positive. Contrast-enhanced CT scan of the head reveals no space-occupying lesions. Which of the following is the most appropriate next step in management of this patient's treponemal infection?
 (Multiple Choice)
4.8/5 (84)
(84) A previously healthy 5-year-old boy is brought to the physician with 2 days of sore throat. He has some pain with swallowing but is drinking fluids normally. He also has fever but no rhinorrhea, cough, or congestion. The boy has no known allergies and his immunizations are up-to-date. He recently started kindergarten, and other children at the school have been ill. His temperature is 38.9 C (102 F), blood pressure is 110/60 mm Hg, pulse is 98/min, and respirations are 20/min. Physical examination shows purulent exudates on the tonsils and posterior pharynx. Anterior cervical nodes are enlarged and tender. Lungs are clear to auscultation. A rapid streptococcal antigen test result is positive. What is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (82)
(82) A newborn girl is evaluated in the nursery for respiratory distress. Approximately 30 minutes after the patient was born, she developed sudden-onset tachypnea and hypoxia for which she is receiving supplemental oxygen by nasal cannula. The infant was born to a 35-year-old woman at 39 weeks gestation via a scheduled cesarean delivery for breech presentation. Membranes ruptured at delivery, revealing clear amniotic fluid. The mother had insulin-controlled gestational diabetes mellitus and tested positive for Group B Streptococcus at 36 weeks gestation. Apgar scores were 7 and 8 at 1 and 5 minutes, respectively. Temperature is 36.7 C (98 F). Examination shows tachypnea, grunting, nasal flaring, and subcostal and intercostal retractions. Cardiac examination reveals tachycardia without murmurs. Femoral pulses are 2+. Chest x-ray reveals a flattened diaphragm, mild cardiomegaly, and a prominent horizontal fissure on the right side. Which of the following is the most likely outcome of this patient?
(Multiple Choice)
4.8/5 (71)
(71) A 7-month-old girl is brought to the office due to a rash. The mother states, "The rash began 3 days ago on her buttocks and has spread to her genitalia. I have been changing her diapers constantly and tried different brands of baby wipes, but the rash is getting worse." She reports that the child has been tugging at her diaper and has been "a little fussier than normal" but otherwise playful. The patient has been drinking her usual 4 bottles of formula daily, and her sleep pattern has not changed. A week ago, the child had a mild diarrheal illness that has since resolved. She has had no fever, runny nose, or cough. The patient was born full term without complications and has no chronic medical conditions. Family history is significant for allergic rhinitis in her mother and asthma in her 4-year-old sister. All vaccinations are up to date. Temperature is 36.7 C (98.1 F), and all other vital signs are normal. Physical examination reveals an active child in no distress. The rash is shown in the image below. A similar rash is present over the labia but not over the inguinal folds or thigh creases. 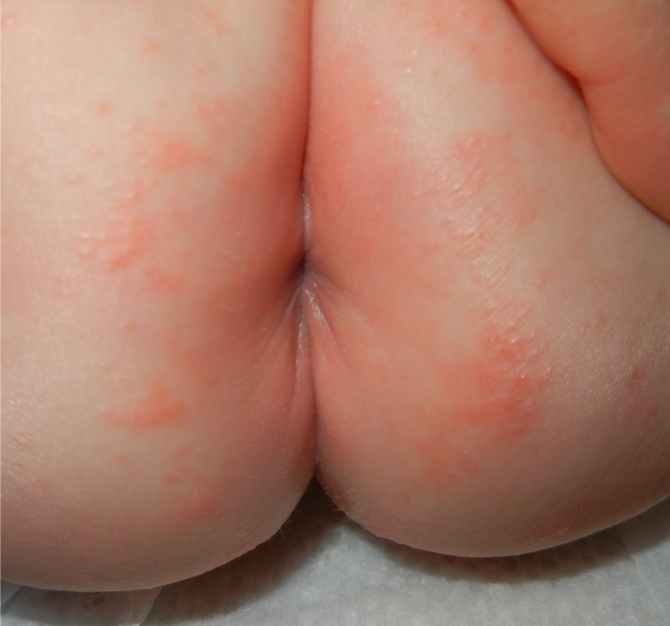 Which of the following is the best treatment for this patient?
 (Multiple Choice)
4.9/5 (87)
(87) A previously healthy 4-year-old boy is brought to the physician in July with fever, productive cough, and left-sided chest pain that began yesterday. He attends a preschool where other children have had a cough and runny nose. Past medical history is negative for asthma or other respiratory illnesses. The child's immunizations are up-to-date and he takes no medications. He lives with his parents and has not traveled outside the country. His temperature is 39.5 C (103.1 F), blood pressure is 98/64 mm Hg, pulse is 104/min, and respirations are 25/min. Oxygen saturation by pulse oximetry is 97%. Examination shows a cooperative boy with intermittent coughing. The left lower lung lobe has decreased breath sounds. A 2-view chest radiograph shows mild alveolar consolidation with air bronchograms in the left lower lobe. What is the most appropriate pharmacotherapy for this patient's condition?
(Multiple Choice)
4.7/5 (84)
(84) A 76-year-old man is admitted to the hospital with nausea, vomiting, and generalized abdominal distension. He has a long-standing history of type 2 diabetes mellitus. His medical follow-up has been poor. Physical examination and diagnostic workup are consistent with a complicated small-bowel obstruction. He undergoes exploratory laparotomy with no operative complications and is extubated postoperatively in the surgical intensive care unit. A few hours after extubation, the patient experiences sudden onset of chest discomfort, nausea, and marked diaphoresis. Temperature is 36.1 C (97 F), blood pressure is 84/50 mm Hg, pulse is 32/min, and respirations are 26/min. Examination shows minimal crackles at both bases. There are no murmurs on cardiac examination. Fingerstick glucose level is 150 mg/dL. ECG shows sinus bradycardia with 3-mm ST-segment elevations in leads II, III, and aVF. Immediate chest x-ray shows increased interstitial markings bilaterally. Intravenous normal saline infusion is started and intravenous atropine is administered without significant improvement. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.7/5 (83)
(83) A 26-year-old woman comes to the office due to fever, sweating, heat intolerance, and shortness of breath. Her symptoms began a week ago and have become progressively worse. The patient has also had severe pain in the anterior neck, which radiates to the angle of the jaw and ears and is worse when she turns her head. She adds that she has "been under a lot of stress lately since I was laid off from my job. I have been babysitting to make some extra money, but I think one of the kids gave me 'the flu.' I had a runny nose, cough, and fever a few weeks ago." Medical history is unremarkable, and the patient takes no medications. She has smoked a pack of cigarettes a day for the last 7 years, and smoked marijuana for a few months as a teenager. The patient is not sexually active and has never been pregnant. Her last menstrual period was 2 weeks ago. She is adopted, and her family history is unknown. Temperature is 38.3 C (100.9 F), blood pressure is 156/60 mm Hg, pulse is 110/min, and respirations are 22/min. The thyroid gland is diffusely enlarged, firm, and very tender. The extremities are warm and moist. Eye examination shows lid lag but no proptosis. The remainder of the examination is unremarkable. Laboratory results are as follows:
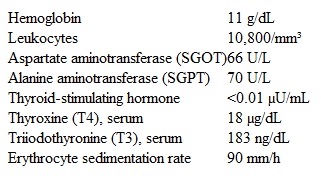 A radioactive iodine uptake with scintigraphy in this patient is mostly likely to show which of the following?
 (Multiple Choice)
4.8/5 (83)
(83) Showing 421 - 440 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)