



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


A 60-year-old man with a history of chronic obstructive pulmonary disease comes to the office due to hemoptysis. For the past several days, he has had increasing cough with greenish-yellow sputum. He also had 2 episodes of blood-streaked sputum, which prompted the clinic visit. The patient has mild dyspnea but no fever or chest pain. His other medical problems are peripheral vascular disease and osteoarthritis. His current medications include aspirin, inhaled fluticasone and salmeterol, and ipratropium. He continues to smoke 1/2 pack of cigarettes daily and drinks alcohol occasionally. The patient had a screening CT scan 2 years ago that was negative for lung mass. His father died of lung cancer. Blood pressure is 140/95 mm Hg and heart rate is 100/min. The patient's pulse oximetry shows 95% on room air. Lung auscultation reveals bilateral expiratory wheezing. Soon after the patient leaves the office, his wife calls and requests information about her husband's condition. She is also the treating physician's patient. Which of the following is the most appropriate response to her request?
(Multiple Choice)
4.8/5  (73)
(73) A 60-year-old man with a history of chronic obstructive pulmonary disease comes to the office due to hemoptysis. For the past several days, he has had increasing cough with greenish-yellow sputum. He also had 2 episodes of blood-streaked sputum, which prompted the clinic visit. The patient has mild dyspnea but no fever or chest pain. His other medical problems are peripheral vascular disease and osteoarthritis. His current medications include aspirin, inhaled fluticasone and salmeterol, and ipratropium. He continues to smoke 1/2 pack of cigarettes daily and drinks alcohol occasionally. The patient had a screening CT scan 2 years ago that was negative for lung mass. His father died of lung cancer. Blood pressure is 140/95 mm Hg and heart rate is 100/min. The patient's pulse oximetry shows 95% on room air. Lung auscultation reveals bilateral expiratory wheezing.
Which of the following is the best initial step in management of this patient?
(Multiple Choice)
5.0/5 (89)
(89) An 18-month-old boy is brought to the emergency department by his adoptive mother due to increasing irritability. The patient has been tiring easily for the past 3-4 days; now he is irritable, constantly crying, and inconsolable. The mother tried to comfort him by playing with his toys, but he refuses to pick them up and cries more when he attempts to walk. The patient has had no recent trauma, fever, cough, or runny nose. He was adopted 6 months ago from Nigeria and has been healthy. Immunizations are up to date. Family history is unknown. Temperature is 37.8 C (100 F) and pulse is 120/min. The patient is alert and appears uncomfortable. Pupils are equal and reactive. Scleral icterus is present and the conjunctivae are pale. Cardiopulmonary examination is normal. The hands and feet are mildly swollen and tender to palpation. Hemoglobin is 9 g/dL. Which of the following tests would establish the underlying diagnosis in this patient?
(Multiple Choice)
4.9/5 (84)
(84) A 46-year-old man is brought to the emergency department by the police after being found unresponsive on a nearby park bench. Previously, the patient was brought to the hospital on several occasions due to acute alcohol intoxication. No other history can be obtained. The patient appears disheveled and has a strong smell of alcohol. Temperature is 36.1 C (97 F), blood pressure is 110/76 mm Hg, and pulse is 84/min. Pulse oximetry shows 98% on ambient air. The patient does not follow instructions and withdraws all extremities to painful stimuli. The mucous membranes are dry, and he has several spider angiomata and bilateral gynecomastia. The lungs are clear to auscultation and heart sounds are normal with no murmur. There is moderate abdominal distension with shifting dullness. The liver edge cannot be palpated. While being evaluated in the emergency department, the patient vomits a large amount of bright red blood. Repeat vital signs show that blood pressure is 100/50 mm Hg and pulse is 110/min. Two large-bore peripheral lines are placed and intravenous fluid is administered.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (80)
(80) A 22-year-old woman comes to the physician with her husband for intermittent dizziness, weakness, and unsteady gait for the last several weeks. She has also had visual loss and pain in the right eye that worsens with eye movement for the past 2 days. A year ago, the patient had tingling and numbness of her right hand accompanied by unsteadiness, which improved spontaneously after 3-4 days. She has no other medical problems and does not take any medications. The patient has no significant social or family history. Her temperature is 37.2 C (99 F), blood pressure is 122/80 mm Hg, pulse is 82/min, and respirations are 16/min. On neurologic examination, her right eye has diminished visual acuity and an afferent pupillary defect. She also has a right arm intention tremor. Both lower extremities have spastic paresis, hyperreflexia, and positive Babinski sign. Appropriate investigation has confirmed the most likely diagnosis. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (81)
(81) A 28-year-old nulligravid woman comes to the office after noticing a lump in her left breast last week. The size of the mass has not changed. The patient has no associated nipple discharge or skin discoloration. She has no chronic medical conditions or previous surgery. Her last menstrual period was 5 days ago. The patient's maternal aunt was diagnosed with breast cancer at age 56 and is doing well after surgery and chemotherapy. The patient uses a progestin-containing subdermal implant for contraception. She smokes half a pack of cigarettes a day and drinks alcohol socially but does not use illicit drugs. The patient has no known drug allergies. Blood pressure is 110/70 mm Hg and pulse is 70/min. BMI is 25 kg/m2. Physical examination reveals a 1.5-cm, round, mobile, tender mass in the lateral superior quadrant of the left breast, 4 cm from the nipple. There is no fluctuance or erythema. No nipple discharge is expressed. Supraclavicular and axillary lymph nodes are not palpable. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (90)
(90) A 68-year-old man is brought to the emergency department by his daughter due to confusion and lethargy. The patient's daughter reports that he lives alone and has type 2 diabetes mellitus and hypertension. He takes aspirin, enalapril, and glipizide. He is afebrile. Blood pressure is 99/59 mm Hg, pulse is 132/min, and respirations are 22/min. The patient appears drowsy and is barely communicative. Examination shows dry mucous membranes, absent jugular venous distention, clear lung fields, and normal heart sounds. The abdomen is soft, nontender, and nondistended. Neurologic examination shows disorientation to time and place. The patient moves all extremities and examination shows no meningeal signs. Laboratory results are as follows:  An ECG shows atrial fibrillation with a rapid ventricular response. Nonspecific T wave changes are present. Which of the following is the best initial approach to managing this patient?
 (Multiple Choice)
4.7/5 (78)
(78) A 62-year-old man comes to the office due to shortness of breath for the past 6 months. The patient, who describes his symptoms as progressive, has difficulty walking a block without becoming out of breath. He experiences chest tightness and midline "squeezing" that is relieved after 5 minutes of rest. He also has fatigue and poor sleep but no palpitations, orthopnea, cough, or syncope. His other medical problems include hypertension and gastroesophageal reflux disease. His medications are hydrochlorothiazide and ranitidine. The patient has smoked a pack of cigarettes daily for 35 years and drinks 1 or 2 beers daily. His father has high blood pressure and had a stroke in his 60s, and his mother died of breast cancer. On physical examination, the patient appears comfortable at rest. Blood pressure is 136/78 mm Hg and pulse is 84/min and regular. BMI is 41 kg/m2. No cardiac murmurs are heard. The lungs are clear on auscultation. There is trace edema of the lower extremities bilaterally. Resting ECG shows normal sinus rhythm with no ST-segment or T-wave abnormalities. Exercise stress testing is performed and reveals a 1-mm ST depression in ECG leads I, aVL, V5, and V6 at minimal exertion. The patient is started on aspirin, atorvastatin, and metoprolol and counseled on smoking cessation. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
5.0/5 (80)
(80) A 60-year-old Caucasian male complains of difficulty swallowing which has rapidly worsened within the last two weeks. The patient noticed a swelling on the front of his neck that started growing for the past month. He was otherwise in his normal state of health. He also complains of fevers, night sweats, and weight loss. He denies cough, dyspnea, chest pain, headache, abdominal pain, skin rashes, and urinary symptoms. His past medical history is significant for mild hypertension treated with hydrochlorothiazide, as well as a small goiter for the past 10 years. He states that his blood tests for thyroid hormone levels were normal, and he has never taken thyroid hormone preparations in the past. His family history is positive for a mother and several other family members with hypothyroidism. He has a smoking history of 15-pack-years but quit 25 years ago. He does not drink alcohol. Physical examination reveals a large, irregular, non-tender swelling over the inferior aspect of his neck. The lower margin of this swelling can not be palpated. He develops facial plethora and venous engorgement of the neck veins after raising his arms above the shoulder for 20 seconds. CBC and basic chemistries are normal. TSH is 26.0 μU/ml (normal 0.35-5.0 μU/ml) and free T4 is 0.2 μg/dl (normal 0.8 to 1.8 μg/dl). Antithyroid peroxidase antibodies are detected in very high titers. What is the most likely diagnosis in this patient?
(Multiple Choice)
4.9/5 (78)
(78) A 46-year-old man comes to the office due to dysuria and a dull, aching pain in the penis and perineal region. The symptoms began 6 months ago and prompted the patient to visit an urgent care center twice. Both times, he received a short course of antibiotics, which improved symptoms temporarily, but they returned within days. The patient has also had pain during ejaculation but no urethral discharge, back pain, abdominal pain, weakness, or incomplete voiding. He is married and monogamous with his wife and has 2 children. He does not use tobacco or illicit drugs but occasionally drinks 1 or 2 beers on weekends. He has no medication allergies and no family history of cancer. Temperature is 37.1 C (98.8 F), blood pressure is 126/84 mm Hg, pulse is 72/min, and respirations are 14/min. Physical examination shows no abdominal or costovertebral angle tenderness. Digital rectal examination reveals a mildly tender prostate that is symmetric and not enlarged. The external genitalia are normal in size and appearance and are nontender to palpation. Urine microscopy after prostate massage reveals 30 leukocytes/hpf, and subsequent culture is negative. What is the most likely diagnosis?
(Multiple Choice)
4.8/5 (84)
(84) A 63-year-old woman is brought to the emergency department with left-sided weakness that started an hour ago. According to family members, the patient dropped her fork while having dinner and subsequently was unable to walk. Medical history includes hypertension, hyperlipidemia, and type 2 diabetes mellitus. Examination shows normal S1 and S2 and no carotid bruits. Neurologic examination shows dense, left-sided hemiplegia. After initial evaluation, including a noncontrast CT scan of the head that is negative for hemorrhage, tissue plasminogen activator is administered. The patient is not a candidate for mechanical thrombectomy. Five hours later, the left-sided weakness is improved. The patient has no headache, blurred vision, or nausea. Blood pressure is 198/110 mm Hg and pulse is 87/min and regular. Finger-stick glucose level is 143 mg/dL. Which of the following is the most appropriate immediate next step in management?
(Multiple Choice)
4.9/5 (73)
(73) A 1-year-old child is diagnosed with severe microcytic/hypochromic anemia. His past medical history is insignificant. His family history is significant for an early death of his uncle from 'a blood disease'. Physical examination reveals hepatomegaly and splenomegaly. Subicteric discoloration of the sclerae is present. If this child survives several years after the diagnosis, severe organ damage due to iron overload is best explained by which of the following?
(Multiple Choice)
4.7/5 (85)
(85) A 45-year-old male returns to clinic for follow-up examination. He has no current complaints and has been feeling well recently. Past medical history is significant for hypertension and gastroesophageal reflux disease. He also had a left knee operation eight months ago that was complicated by a postoperative deep vein thrombosis (DVT) of the left leg. He has no other personal history of blood clots, and there is no family history of clotting disorders. Currently, his vital signs are stable and his physical examination is within normal limits. Specifically, there is no swelling or calf tenderness of the left leg. He took warfarin on a daily basis for a total of six months after the DVT was diagnosed and then stopped taking it because he no longer wanted to deal with monitoring his INR. This is his first visit to clinic since being discharged after his knee operation. Which of the following is the next best step in treating this patient's prior DVT?
(Multiple Choice)
5.0/5 (87)
(87) A 38-year-old woman comes to the office due to worsening asthma symptoms for 2-3 days. She has shortness of breath, wheezing, and productive cough. The patient describes thick sputum that was blood-tinged yesterday. She was diagnosed with asthma 12 years ago but says that it had not been this bad until last year. For the past year the patient has had 2 hospitalizations for asthma exacerbations but has never been intubated. She completed a course of oral prednisone and azithromycin 2 months ago. Current medications include a daily fluticasone inhaler and as-needed albuterol inhaler. The patient reports no decrease in appetite or weight loss and has not travelled outside of her home state of New Jersey in the past 2 years. She works as a school teacher and does not use tobacco, alcohol, or illicit drugs. The patient has no second-hand tobacco exposure and no known allergies. Her grandmother also has asthma. Temperature is 37 C (98.6 F), blood pressure is 123/80 mm Hg, pulse is 94/min, and respirations are 16/min. Pulse oximetry shows 95% on room air. Pulmonary examination reveals scattered wheezes. Heart sounds are normal. There is no clubbing, peripheral edema, or skin rashes. Complete blood count shows the following:  Further laboratory evaluation of the patient shows a serum total IgE level of >1,000 ng/mL. High-resolution CT scan of the lungs confirms the presence of bilateral upper lobe infiltrates and central bronchiectasis. Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (75)
(75) A 65-year-old man is brought to the emergency department by his wife due to severe upper-abdominal pain. The pain began suddenly 4 hours ago while he was watching television; it radiates to the back and is exacerbated by any movement. The patient has had gastroesophageal reflux disease for many years and has been taking over-the-counter antacids for symptom control. He also has hypertension, which is controlled with a thiazide diuretic. He walks 5 miles daily. The patient has been consuming large amounts of milk and other dairy products to relieve "burning" symptoms in his stomach. His temperature is 37.8 C (100 F), blood pressure is 110/62 mm Hg, pulse is 110/min, and respirations are 22/min. He lies flat and motionless on the bed. His mucous membranes are dry. Abdominal examination shows marked tenderness on superficial palpation. The patient does not allow any further palpation of the abdomen. Electrocardiogram shows sinus tachycardia. Further evaluation shows pneumoperitoneum on the upright chest x-ray. The patient's white blood cell count is 11,300/μL, creatinine is 1.1 mg/dL, and lactic acid level is 2.1 mg/dL. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (93)
(93) A 26-year-old woman comes to the office due to fever, sweating, heat intolerance, and shortness of breath. Her symptoms began a week ago and have become progressively worse. The patient has also had severe pain in the anterior neck, which radiates to the angle of the jaw and ears and is worse when she turns her head. She adds that she has "been under a lot of stress lately since I was laid off from my job. I have been babysitting to make some extra money, but I think one of the kids gave me 'the flu.' I had a runny nose, cough, and fever a few weeks ago." Medical history is unremarkable, and the patient takes no medications. She has smoked a pack of cigarettes a day for the last 7 years, and smoked marijuana for a few months as a teenager. The patient is not sexually active and has never been pregnant. Her last menstrual period was 2 weeks ago. She is adopted, and her family history is unknown. Temperature is 38.3 C (100.9 F), blood pressure is 156/60 mm Hg, pulse is 110/min, and respirations are 22/min. The thyroid gland is diffusely enlarged, firm, and very tender. The extremities are warm and moist. Eye examination shows lid lag but no proptosis. The remainder of the examination is unremarkable. Laboratory results are as follows:
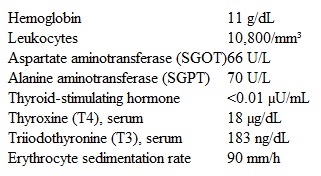 Which of the following is the best treatment for this patient?
 (Multiple Choice)
4.8/5 (81)
(81) A 76-year-old woman is hospitalized due to a fracture of her right proximal femur from an accidental nonsyncopal fall. Medical history is notable for breast cancer treated with a radical mastectomy 10 years ago, hypertension, and hyperlipidemia. She drinks a pint of vodka daily, but does not use tobacco or illicit drugs. The patient is started on thiamine and folic acid, and the next morning she undergoes orthopedic surgery for internal fixation of the right femur. She experiences mild agitation postoperatively, which is managed with as-needed, low-dose benzodiazepines. In addition, she is treated with low-molecular-weight heparin, opiates, and continued vitamin supplementation. On her third postoperative day, the nurse finds her agitated and in significant distress. The patient has an episode of nonbloody vomiting. On initial evaluation, she appears restless and confused but follows commands. Temperature is 36.7 C (98 F), blood pressure is 92/58 mm Hg, pulse is 122/min and regular, and respirations are 31/min. Pulse oximetry is 75% on room air and improves to 82% with supplemental oxygen by non-rebreather mask. Chest auscultation reveals no crackles or wheezes. Cardiac examination demonstrates tachycardia with a regular rhythm and normal S1 and S2. The abdomen is soft. Her pupils are equal and reactive to light, and she is moving all extremities.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (90)
(90) A 54-year-old woman comes to the emergency department with palpitations. She has experienced paroxysmal atrial fibrillation for the past 6 months. She has had extensive investigations for an underlying cause, including echocardiography and thyroid function testing, which were normal. The patient was started on amiodarone 6 weeks ago by her cardiologist and did well in the interim. She has had no change in her weight or intolerance to hot or cold temperatures. Her other medications include atenolol and low-dose aspirin. On physical examination, the patient appears comfortable. Her blood pressure is 132/82 mm Hg and heart rate is 112/min and irregular. Laboratory studies show a normal complete blood count and basic metabolic panel. ECG shows atrial fibrillation with rapid ventricular response. Thyroid function markers are as follows: 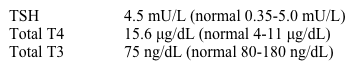 What is the most likely explanation for this patient's thyroid function tests?
 (Multiple Choice)
4.8/5 (91)
(91) A 67-year-old man undergoes coronary angiography due to stable angina and a positive stress test. Medical history is notable for type 2 diabetes mellitus, hypertension, and peripheral arterial disease. Access is obtained through the right femoral artery, and a high-grade lesion is diagnosed in the mid left anterior descending artery. A drug-eluting stent is successfully placed. After the procedure, the femoral arterial sheath is removed and manual compression is applied. The patient is discharged the next morning. Two days later, he comes to the office for follow-up due to right groin pain and discomfort that he thought would be gone by now. He has no chest pain, dyspnea, lightheadedness, or abdominal pain. The patient has been taking dual antiplatelet therapy prescribed on discharge. Blood pressure is 118/74 mm Hg and pulse is 82/min. Physical examination shows mild swelling and bruising of the right groin with accentuated pulsation. Skin color and perfusion are normal over both lower extremities. Popliteal and dorsalis pedis pulses are symmetric. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (73)
(73) A 70-year-old African-American male is brought to the emergency department with a low-trauma hip fracture. His past medical history is significant for long-term hypertension and myocardial infarction experienced two years ago. His current medications include metoprolol, enalapril, hydrochlorothiazide, and aspirin. He smokes two packs of cigarettes daily, and consumes alcohol occasionally. His mother had a vertebral fracture "when she was old." His serum calcium, phosphate, and alkaline phosphatase levels are normal. An x-ray of the hip shows osteopenia and a hip fracture. Which of the following is the single most important risk factor for this patient's condition?
(Multiple Choice)
4.9/5 (73)
(73) Showing 341 - 360 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)