



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


A 54-year-old man comes to the emergency department with a 2-week history of exertional dyspnea and nonproductive cough. He has no known medical problems and does not use any medications. The patient has a long history of alcohol abuse and currently consumes a half-pint of vodka a day, although he is "trying to cut down." He smokes a pack of cigarettes a day and does not use illicit drugs. Temperature is 36.8 C (98.2 F), blood pressure is 123/78 mm Hg, heart rate is 114/min and regular, and oxygen saturation is 96% on room air. Lung examination shows decreased breath sounds on the right with dullness to percussion. The patient's abdomen is distended with flank dullness and a positive fluid shift sign. There is 1+ bilateral pitting lower-extremity edema. His hands are flushed over the palmar aspects, and small dilated blood vessels are visible over his upper chest. Laboratory results are as follows: 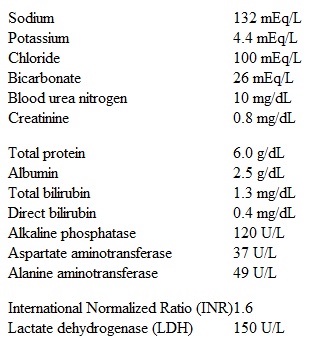 Chest x-ray demonstrates a large right-sided pleural effusion. A thoracentesis is performed, and 1.2 L of straw-colored fluid is removed. The fluid shows a protein concentration of 1.2 g/dL and lactate dehydrogenase concentration of 60 U/L. Gram stain and cultures are negative. The patient's symptoms improve after the procedure, and counseling regarding cessation of alcohol and tobacco use is provided. Which of the following is the best next step in management of this patient's pleural effusion?
 (Multiple Choice)
4.9/5  (77)
(77) An 8-year-old boy is brought to the office due to a 2-month history of excessive urination. The parents report that the boy is sometimes irritable and restless and has been drinking excessive amounts of water. He has had normal growth with achievement of all expected milestones and takes no medications. The patient's maternal grandfather tends to drink excess amounts of water. Vital signs reveal tachycardia. On physical examination, mucous membranes are dry. Neurologic examination shows no focal deficits. Laboratory results on a random blood sample are as follows:  Urine osmolality is 120 mOsm/kg H2O. Which of the following is the most appropriate next step in management?
 (Multiple Choice)
4.9/5 (86)
(86) A 50-year-old woman comes to the office for an annual preventive visit. She says, "I want to be tested for colon cancer because my 83-year-old mother was diagnosed with stage IV colon cancer a month ago." The patient has had no abdominal pain, nausea, vomiting, anorexia, weight loss, melena, hematochezia, or changes in bowel habits. She had a normal screening colonoscopy at age 45. Medical history is notable for hyperlipidemia and type 2 diabetes mellitus. Except for her mother, the patient has no family history of cancer. Temperature is 36.7 C (98 F), blood pressure is 120/70 mm Hg, and pulse is 80/min. The abdomen is nondistended, soft, and nontender with no hepatosplenomegaly. Bowel sounds are normal. Which of the following is the best recommendation regarding colorectal cancer screening in this patient?
(Multiple Choice)
4.9/5 (84)
(84) A 35-year-old man comes to the office due to painful bumps on his neck. For the last 6 months, he has had a progressive rash on his anterior neck that has not improved with over-the-counter emollients. Medical history is unremarkable. Vital signs are within normal limits. Skin examination findings are as shown: 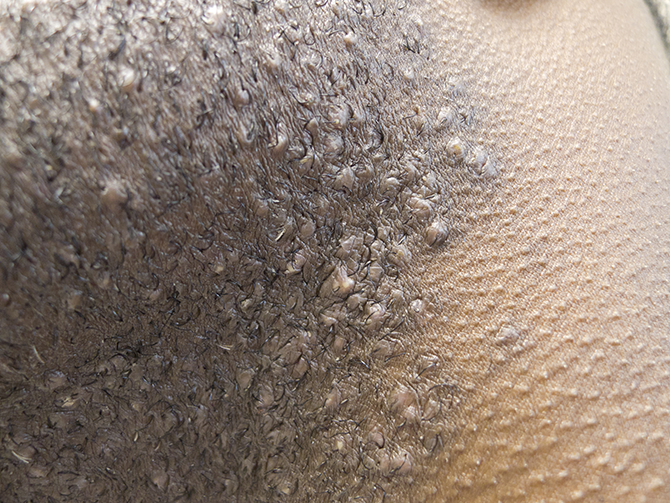 The remainder of the examination is normal. Which of the following is the most appropriate management for this patient's skin condition?
 (Multiple Choice)
4.8/5 (82)
(82) A 55-year-old man is brought to the emergency department due to an episode of hematemesis. He has a history of alcoholic cirrhosis with ascites for the last 2 years. In the emergency department, he is appropriately treated, and has no new episodes of bleeding. He is admitted to the hospital for observation and further work-up. His upper gastrointestinal endoscopy reveals esophageal varices with stigmata of recent bleeding. Which of the following is the most likely complication that he is at risk of developing during his hospitalization?
(Multiple Choice)
4.8/5 (75)
(75) An 81-year-old woman is brought to the office for assessment of behavioral changes over the past 10 months. The patient moved to a nursing home a year ago, and initially enjoyed playing simple card games there with other residents. Now she either seems uninterested in playing or quickly becomes upset during games, repeating, "I can't, I can't, I can't." She also becomes easily irritable and pushes staff away when they try to help her dress or comb her hair. The patient has had increasing difficulty recalling recent events and has started accusing staff of stealing her jewelry. Sleep and appetite are unchanged. The patient has a history of hypertension and noninsulin-dependent diabetes mellitus, as well as postpartum depression in her 20s. Temperature is 37 C (98.6 F), blood pressure is 140/90 mm Hg, and pulse is 86/min. Physical examination is unremarkable. She is oriented to person and place but not to time or day. Short-term recall is very poor. Her mood is "OK." Laboratory results, including electrolytes, complete blood count, thyroid function tests, and vitamin B12, are normal. Rapid plasma reagin is negative; fluorescent treponemal antibody absorption test is nonreactive. MRI of the brain reveals mild generalized cortical atrophy and slightly reduced hippocampal volume. Which of the following is the most appropriate statement regarding this patient's prognosis?
(Multiple Choice)
4.9/5 (84)
(84) A 72-year-old woman is found to be severely short of breath at her skilled nursing facility. The patient was recently hospitalized for vertebral osteomyelitis and discharged 2 weeks ago to complete a 6-week course of piperacillin-tazobactam via a peripherally inserted central venous catheter. Her dyspnea began only with exertion but is now also present at rest. Medical history includes coronary artery disease with ischemic cardiomyopathy, chronic obstructive pulmonary disease, and chronic kidney disease. She has had 2 hospitalizations for heart failure over the last year; noninvasive positive-pressure ventilation was required. Paramedics observe the patient to be obtunded with agonal respirations and rales throughout the bilateral lung fields. Oxygen saturation is 72% on room air. She is intubated and transferred to the emergency department. On arrival, the patient is minimally responsive to stimuli. Temperature is 36.7 C (98 F), blood pressure is 115/65 mm Hg, and pulse is 110/min and regular. The patient's oxygen saturation is 88% on 100% inspired oxygen. BMI is 19 kg/m2. The trachea is midline. On physical examination, rales are heard on the right side and markedly decreased breath sounds on the left side of the chest. S3 is heard. There is 2+ bilateral peripheral edema. A chest x-ray reveals the following: 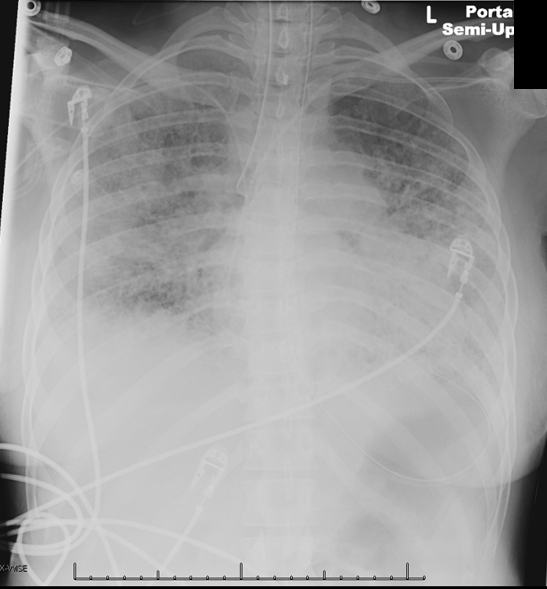 After the intervention is performed, the patient's oxygenation improves. She is transferred to the medical intensive care unit and treated with diuretics and bronchodilators. Two days later, her ventilation requirements have improved to 50% inspired oxygen and 5 cm of positive end-expiratory pressure. The patient's respirations suddenly become dys-synchronous with the ventilator, and her oxygen saturation drops to 85%. Tidal volume spontaneously decreases from 350 to 200 mL. Temperature is 37.2 C (99 F), blood pressure is 125/60 mm Hg, pulse is 110/min, and respirations are 25/min. Physical examination shows that the trachea is midline and the endotracheal tube is in place. No jugular venous distension is present. Breath sounds are markedly decreased on the right side. A portable chest x-ray reveals the following:
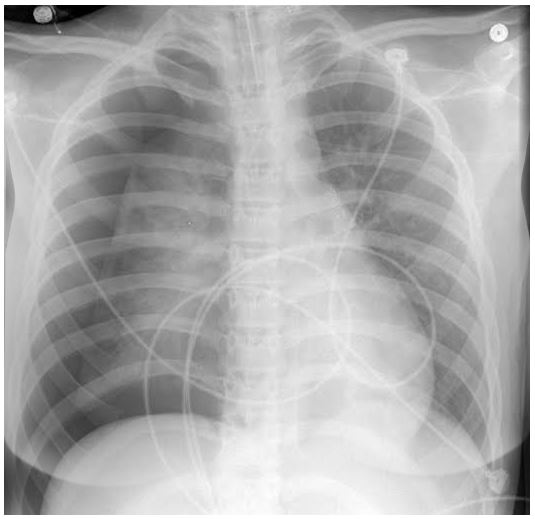 Which of the following is the best next step in management of this patient?
After the intervention is performed, the patient's oxygenation improves. She is transferred to the medical intensive care unit and treated with diuretics and bronchodilators. Two days later, her ventilation requirements have improved to 50% inspired oxygen and 5 cm of positive end-expiratory pressure. The patient's respirations suddenly become dys-synchronous with the ventilator, and her oxygen saturation drops to 85%. Tidal volume spontaneously decreases from 350 to 200 mL. Temperature is 37.2 C (99 F), blood pressure is 125/60 mm Hg, pulse is 110/min, and respirations are 25/min. Physical examination shows that the trachea is midline and the endotracheal tube is in place. No jugular venous distension is present. Breath sounds are markedly decreased on the right side. A portable chest x-ray reveals the following:
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.7/5 (92)
(92) A 52-year-old male presents with enlargement of his hands and feet which began one year ago. His jaw is also getting bigger. Acromegaly is suspected on clinical examination, and later confirmed by non-suppression of GH following a glucose load and increased serum IGF1 levels. The rest of his hormonal profile is within normal limits. MRI shows a 9 mm pituitary adenoma. The patient is advised to undergo surgery; however, he refuses adamantly because he says that he feels fine. If this patient does not get any treatment for his acromegaly, which of the following will most likely increase his mortality risk?
(Multiple Choice)
4.9/5 (75)
(75) A 72-year-old woman comes to the emergency department due to right ear pain and drainage for the past 2 days. She saw her primary care physician approximately a week ago for decreased hearing in the right ear and underwent aural irrigation to remove impacted cerumen. The patient's medical history is notable for hypertension, diabetes mellitus, and rheumatoid arthritis. Current medications include hydrochlorothiazide, enalapril, metformin, and methotrexate. She does not use tobacco, alcohol, or illicit drugs. Temperature is 37.2 C (99 F), blood pressure is 146/74 mm Hg, pulse is 100/min, and respirations are 16/min. There is marked tenderness with motion of the right earlobe. Purulent discharge and granulation tissue are noted on the floor of the right external auditory canal at the osseocartilaginous junction. The tympanic membrane appears intact.
Which of the following is the most likely cause of this patient's acute findings?
(Multiple Choice)
4.9/5 (81)
(81) A 32-year-old woman comes to the emergency department due to 7 days of fever and dry cough. She has also had progressive shortness of breath with minimal walking and climbing stairs. The patient was diagnosed with HIV infection a year ago and is not currently on antiretroviral treatment. She does not use tobacco, alcohol, or illicit drugs. Temperature is 38.4 C (101.1 F), blood pressure is 110/64 mm Hg, pulse is 106/min, and respiratory rate is 26/min. Pulse oxymetry is 87% on room air and decreases to 82% with minimal walking. Oropharyngeal thrush is present. Lung auscultation reveals scattered bilateral crackles and rhonchi. The abdomen is soft and nontender without organomegaly. No cyanosis, clubbing, or edema is present. Chest x-ray reveals diffuse interstitial opacities bilaterally. CD4 count is 85/mm3. The patient is admitted and started on empiric therapy. Twenty-four hours after admission, the induced sputum analysis is negative for Pneumocystis. Which of the following is the most appropriate indication for the use of corticosteroids in this patient?
(Multiple Choice)
4.8/5 (79)
(79) A 4-year-old boy is brought to the office with right leg pain. The pain began about a week ago when the patient bumped his leg into a coffee table. At the time, his parents were not concerned as he "cried for only a few minutes" and was able to walk normally afterward. However, the pain has worsened over the past few days and the patient is now limping. He also developed a persistent fever 4 days ago that is not improving despite ibuprofen and acetaminophen. The patient has had no cough, vomiting, diarrhea, or rash. Medical history is notable for sickle cell disease, and he has been hospitalized several times for vaso-occlusive pain crises. He has no history of splenic sequestration or acute chest syndrome. The patient takes no medications other than the antipyretics. Immunizations are up to date. Temperature is 39.4 C (103 F), blood pressure is 95/60 mm Hg, pulse is 158/min, and respirations are 30/min. Physical examination shows warmth and swelling of the right distal thigh with decreased spontaneous movements, although the patient has full range of motion in his hips and knees. The lungs are clear to auscultation with no increased work of breathing, and the abdomen is soft and nontender with no organomegaly. Laboratory results are as follows: 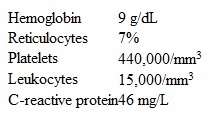 Additional diagnostic testing is pending. Which of the following is the most appropriate empiric antibiotic therapy for this patient?
 (Multiple Choice)
4.9/5 (95)
(95) A 13-year-old boy is brought to clinic by his parents due to copious, purulent discharge from his right eye. The patient's eye was crusted shut this morning. His father was able to open the eye by wiping it with a damp washcloth. The patient went to school but was sent home by the school nurse. He has not had ocular pain, visual changes, or fever. He lives at home with his parents and older sister, none of whom have similar symptoms. The patient has mild myopia and wears contact lenses. He takes loratadine daily for seasonal allergies. Vital signs are within normal limits. Examination shows conjunctival erythema and yellow exudate in the right eye. The conjunctiva of the left eye is also erythematous, but there are no secretions. Visual acuity testing with the patient's contacts removed shows 20/80 vision in both eyes, consistent with his well-child examination at age 12. The mother is very concerned about possible complications of the disease. Which of the following complications is most likely to occur with this patient's condition?
(Multiple Choice)
4.8/5 (102)
(102) A 22-year-old college student comes to the office due to a 1-week history of right lower leg pain. She has mild dull pain at rest that becomes sharp and "bothersome" with exercise. She is an avid runner and has been preparing for an upcoming marathon event for the past 2 months. Her shoe has recently been bothering her, especially on the lateral side of the right foot. The patient has no other medical problems or history of recent trauma. Physical examination shows point tenderness and localized swelling over the right lower tibial border. The diagnostic study performed on the right lower extremity reveals a nondisplaced, distal tibial stress fracture. Which of the following is the most appropriate next step in the management of this patient?
(Multiple Choice)
5.0/5 (79)
(79) A 16-year-old girl is brought to the physician for a routine well-child examination. She recently moved to a new high school in southern California and engages in outdoor sports throughout the year. The girl is on the varsity soccer team and participates in local surfing competitions. Her grandfather died of melanoma recently. The physical examination shows light blonde hair and a fair complexion. She has several freckles on the nose and malar area of the face but no concerning nevi on her body. The girl says that several of her friends use tanning beds prior to spending the weekend at the beach. Her parents request guidance in preventing malignant melanoma. Which of the following is the most appropriate response to the parents' concerns?
(Multiple Choice)
5.0/5 (62)
(62) A 28-year-old woman comes to the office due to exertional shortness of breath for the last 2 weeks. She and her husband recently immigrated to the United States from Cambodia. She has a history of rheumatic mitral stenosis with an estimated mitral valve area of 1.5 cm2, which was documented on her most recent transthoracic echocardiogram 4 months ago. The patient's exercise tolerance is about 5 blocks of brisk walking at baseline but is currently about 1 block. She has had no recent upper respiratory infection, sore throat, cough, orthopnea, lower extremity swelling, palpitations, syncope, or chest pain. Blood pressure is 108/67 mm Hg, and pulse is 92/min and regular. A diastolic rumble is heard at the apex in the left decubitus position. The lungs are clear on auscultation. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (85)
(85) A 55-year-old man comes to the emergency department after coughing up blood earlier this morning. The patient estimates that he coughed up 100 mL of blood at home and another 50 mL in the emergency department. He reports 4 hospital admissions for pneumonia in the past 18 months, but this is the first episode of hemoptysis. He has a chronic cough with yellow-green sputum production that is sometimes foul-smelling. The patient gets winded after climbing 2 flights of stairs or walking uphill. He is an ex-smoker with a 10-pack-year history. Physical examination is notable for crackles at the right lung base and scattered bilateral wheezes. There is no jugular venous distension or lower-extremity edema. What is the most likely mechanism of hemoptysis in this patient?
(Multiple Choice)
4.8/5 (75)
(75) A 6-year-old boy is brought to the clinic for influenza vaccination in September. He has been healthy and has no nasal congestion, rhinorrhea, or other symptoms. The patient had 2 episodes of otitis media during infancy and has mild intermittent asthma treated with inhaled albuterol as needed. He has no other respiratory problems and takes no other medications. His older brother had cystic fibrosis and recently died at age 10 from a severe influenza infection; the patient's sweat test was negative. The patient has no medication allergies but has developed a splotchy, itchy red rash to egg-containing products in the past. Eggs have since been excluded from his diet. He has no history of other reactions to egg or to immunizations. Vital signs and physical examination are normal. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (76)
(76) A 28-year-old woman, gravida 2 para 1, at 16 weeks gestation comes to the office for prenatal follow-up. The patient reports increased fatigue, intermittent headache, myalgia, and arthralgia for the past several days. She attributes her symptoms to physical exhaustion after her recent travel to Connecticut, where she visited her family and enjoyed outdoor activities. The patient does not recall a specific insect or tick bite during the trip. She has no significant medical history and takes prenatal vitamins daily. She does not use tobacco or illicit drugs and stopped drinking alcohol after conceiving. The patient lives with her husband and 4-year-old son. Temperature is 37.7 C (99.8 F), blood pressure is 120/70 mm Hg, and pulse is 84/min. Cardiopulmonary examination is normal. The abdomen is soft and nontender with the uterine fundus palpable halfway between the symphysis pubis and the umbilicus. Skin examination reveals a 5-cm, circular, erythematous rash with central clearing in the left popliteal area. Empiric treatment with amoxicillin is administered. The patient is concerned about risk to the fetus and her family. Which of the following is most accurate regarding this patient's current condition?
(Multiple Choice)
4.7/5 (66)
(66) A 16-year-old boy is brought to the office due to a rash on his chin. The boy sustained a minor cut while shaving with his father's razor 4 days ago. The patient was also using a new shaving cream at the time. The bleeding stopped with minimal pressure. The surrounding skin appeared red the next day. Since then, the affected area has increased in size, become tender, and appeared "wet." This morning, the rash is "dry and crusty." The patient has a history of acne vulgaris and uses a topical retinoid and benzoyl peroxide on his forehead and cheeks. He also periodically develops "cold sores" when experiencing stress, such as before tests at school. He takes no other medications and has no known allergies. Temperature is 37 C (98.6 F). Physical examination shows a well-appearing adolescent in no distress. Skin examination reveals inflammatory acne on the cheeks and forehead. The rash on the chin is shown in the exhibit. 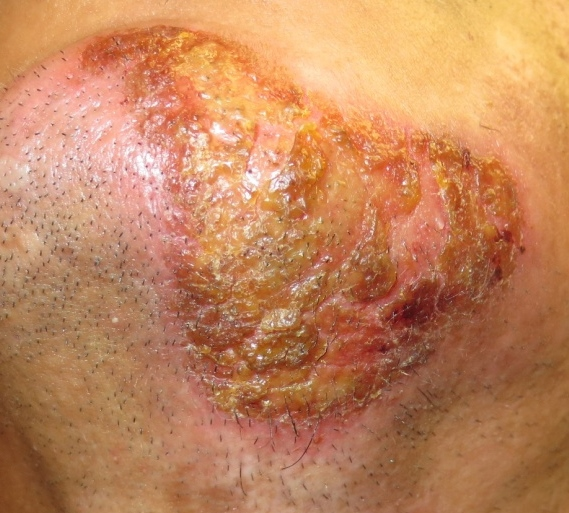 Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.8/5 (79)
(79) A 48-year-old Hispanic woman with no past medical history is brought to the emergency department by an ambulance after being rescued from a burning apartment building. The woman was trapped in a smoke-filled back bedroom of the apartment. On physical exam, her vital signs are stable, and while there is some singeing of her facial hair, there is no visible evidence of burns. An arterial blood gas is obtained, and the values are as follows:  What potential development is of most concern in this woman over the next 24 hours?
 (Multiple Choice)
4.7/5 (91)
(91) Showing 361 - 380 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)