



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


A 66-year-old hospitalized man is evaluated after an episode of generalized tonic-clonic seizure. The patient has no previous history of seizure. He underwent right hemicolectomy for cecal adenocarcinoma the previous day. Postoperatively, the patient had hypotensive episodes, which responded to fluid resuscitation. He has been receiving intravenous infusion of 5% dextrose with 0.45% saline. He is also receiving morphine via a patient-controlled device. On physical examination, he is postictal. Temperature is 36.7 C (98 F), blood pressure is 112/60 mm Hg, pulse is 68/min, and respirations are 12/min. Pulse oximetry shows 96% on room air. Laboratory results are as follows: 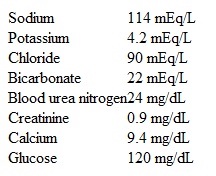 Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.9/5  (78)
(78) A 34-year-old woman comes to the office due to malaise and jaundice. The patient was in good health until about 4 weeks ago, when she developed joint pain, fatigue, and a pruritic rash over her trunk and extremities. The joint pain and rash resolved about a week ago, but the fatigue has persisted. Two days ago, the patient noticed some yellowish discoloration of the whites of her eyes and began to experience decreased appetite. However, she has been able to eat and drink without difficulty. Medical history includes irritable bowel syndrome and allergic rhinitis. Medications include docusate and intranasal fluticasone. She does not use any other over-the-counter medications. Immunization history is unknown. She is sexually active with 2 male partners and uses condoms inconsistently. The patient drinks on social occasions and does not use tobacco or illicit drugs. Temperature is 36.7 C (98 F), blood pressure is 110/64 mm Hg, and pulse is 68/min. BMI is 25 kg/m2. Physical examination is notable for moist mucous membranes, scleral icterus, and normal jugular venous pressure. Heart and lung sounds are normal. Abdominal examination reveals a palpable liver edge approximately 2 cm below the costal margin without tenderness. Bowel sounds are normoactive. The extremities are warm and without edema. The joints are nontender and without erythema. Neurologic examination is normal with no asterixis. The remainder of the physical examination is unremarkable. Laboratory results are as follows:
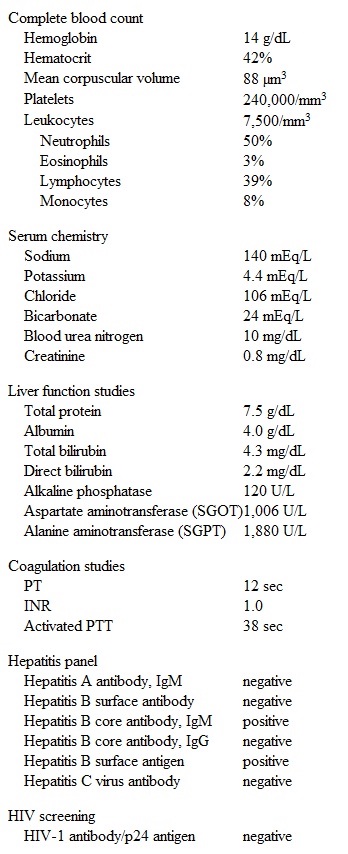 Shortly after the initial visit, the patient's hepatitis B viral DNA level is found to be 300,000 IU/mL. She has returned to the clinic multiple times over the past several weeks since her initial illness. Today's visit is 6 weeks after her initial presentation. The patient's anorexia, fatigue, and jaundice have resolved. Laboratory results are as follows:
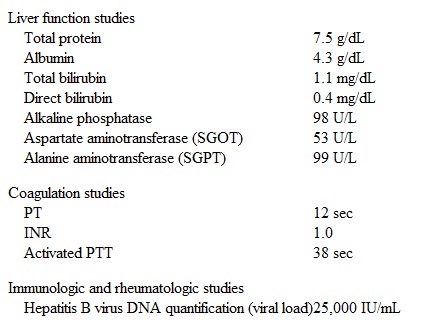 What is the most appropriate means of treating this patient's condition?
Shortly after the initial visit, the patient's hepatitis B viral DNA level is found to be 300,000 IU/mL. She has returned to the clinic multiple times over the past several weeks since her initial illness. Today's visit is 6 weeks after her initial presentation. The patient's anorexia, fatigue, and jaundice have resolved. Laboratory results are as follows:
What is the most appropriate means of treating this patient's condition? (Multiple Choice)
4.9/5 (85)
(85) A 50-year-old male comes in to the emergency department complaining of unremitting pain in an area of his right buttock near the anus. Although he is uncertain when the discomfort first began, he notes that the pain has increased significantly over the past 24 hours. He finds he is unable to pass stool because of the pain. He has not experienced symptoms like this before. Ten years ago, he was diagnosed with diabetes mellitus. He is currently on insulin. He smokes half a pack of cigarettes per day but would like to quit. He denies drinking alcohol or using recreational drugs. His temperature is 38.1C (100.6F), blood pressure is 128/86 mm Hg, and pulse is 90/min. There is a hot, tender, mass located between the anus and the left ischial tuberosity. The mass fluctuates upon palpation.
What is the most appropriate next step in the management of this patient?
(Multiple Choice)
4.8/5 (84)
(84) A 36-year-old man comes to the emergency department due to acute pain in his left foot. He was previously feeling well but suddenly woke from sleep with severe pain at the base of his great toe. The patient has type 1 diabetes mellitus complicated by peripheral sensory neuropathy and proliferative retinopathy. He also has end-stage renal disease due to diabetic nephropathy, for which he underwent cadaveric renal transplant 18 months ago. The patient's diabetes is controlled by an insulin pump. His other medications include lisinopril, amlodipine, cyclosporine, mycophenolate, and prednisone (5 mg/day). Temperature is 37.3 C (99.1 F), blood pressure is 126/84 mm Hg, and pulse is 88/min. Physical examination shows an erythematous, swollen, warm, and tender left first metatarsophalangeal joint. Range of motion testing is limited by severe pain. There is a moderate hammertoe deformity at the third toe but no abnormal calluses. Posterior tibial and dorsalis pedis pulses are easily palpable. Bedside capillary glucose is 184 mg/dL.
Aspiration of the affected joint is likely to reveal which of the following in this patient?
(Multiple Choice)
4.7/5 (99)
(99) A 72-year-old man comes to a rural health clinic due to intermittent leg pain. The patient reports a dull discomfort in his left lower calf with activity, causing him to stop and rest on the way to his mailbox, which is approximately 150 m (492 ft) from his house. The pain improves with rest and does not occur at night when he is lying in bed. Medical history is significant for hypertension and gout. Current medications include lisinopril and allopurinol. The patient has a 40-pack-year smoking history, but quit 5 years ago. Family history is significant for a stroke in his father and breast cancer in his mother. Blood pressure is 130/78 mm Hg and pulse is 75/min. The patient's left foot is shiny and devoid of hair, but there are no lower extremity ulcerations. Strength and sensory examination of the left lower extremity is normal. The ankle-brachial index is 0.76 on the left and 1.05 on the right (normal: 1.0-1.4). Laboratory results are as follows:
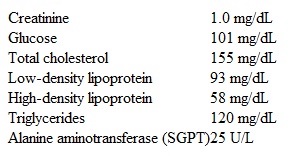 In addition to aspirin, which of the following medications is the most appropriate to add to this patient's pharmacologic regimen?
 (Multiple Choice)
4.8/5 (77)
(77) A 36-year-old woman is brought to the outpatient psychiatry clinic by her husband. He says that his wife was fine and working as a store clerk until about 8 months ago, when they relocated to another state for his new job. Soon after, the patient's behavior abruptly changed. She became suspicious of her neighbors and has remained convinced that they are secretly monitoring her with hidden cameras planted outside the couple's new apartment. She claims that she hears the neighbors whispering about her every night, and her husband has seen her shout at other people when no one is in the room. The patient has stopped cleaning and cooking and is fearful of going outside. For the past month, she has refused to pick up their daughter at school as she believes the child has been replaced by an imposter. She hears voices warning her that "this is not your child." The patient has no history of similar signs or symptoms, and there is no family history of psychiatric illness. Physical examination is unremarkable. Recent results of blood work, urine toxicology, and a brain CT scan were also normal. The husband asks if his wife will be okay. Which of the following is the most appropriate statement regarding this patient's prognosis?
(Multiple Choice)
4.9/5 (70)
(70) An 8-year-old boy is brought to the emergency room by paramedics with a reported ingestion about four hours ago. The patient had an accidental ingestion of "antifreeze" after mistaking it for a beverage in the garage.
Which of the following is the most appropriate treatment of early ethylene glycol ingestion?
(Multiple Choice)
4.9/5 (91)
(91) A 64-year-old man comes to the emergency department with a 3-day history of fever, shortness of breath, and worsening productive cough. The patient also reports sharp, intermittent, right-sided chest pain. He has a history of hypertension and type 2 diabetes mellitus. The patient has smoked a pack of cigarettes daily for 20 years. Temperature is 38.9 C (102 F), blood pressure is 110/60 mm Hg, pulse is 114/min, and respirations are 32/min. The patient's pulse oximetry shows 86% on room air. Examination reveals diffuse crackles over the lung fields. Heart sounds are regular with no murmurs or gallops. Chest x-ray reveals bilateral consolidation and infiltrates. He is started on empiric intravenous antibiotics after obtaining cultures but requires endotracheal intubation due to respiratory failure. Which of the following is most reliable for confirming tracheal (rather than esophageal) endotracheal tube placement in this patient?
(Multiple Choice)
4.8/5 (67)
(67) A 55-year-old Caucasian male is receiving doxorubicin-based chemotherapy, opioids and anti-emetics for stage IV Hodgkin's lymphoma. He complains of an unstable gait and slowing of movements. Physical examination reveals a bilateral increase in the muscular tone without lateralizing neurologic signs. Which of the following is the best next step in the management of this patient's condition?
(Multiple Choice)
4.8/5 (71)
(71) A 41-year-old man is brought to the emergency department by ambulance after a motor vehicle accident. He was driving a car with his 6-year-old daughter in the back seat when they were broadsided by a large truck traveling at high speed. The patient is conscious during transit to the emergency department. He appears oriented to date and time, and informs paramedics that he is a Jehovah's Witness and does not want blood transfusions for himself or his daughter. Soon after, he begins moaning and writhing and is clearly in distress. He complains of feeling nauseated and thirsty. A facemask is placed to administer 100% oxygen. Initial assessment indicates his temperature is 37 C (98.6 F), blood pressure is 100/58 mm Hg, pulse is 132/min and thready, and respirations are 34/min. There are numerous lacerations on his scalp, trunk, abdomen, and extremities. The patient's skin is cool and clammy. Chest auscultation shows tachypnea and tachycardia but is otherwise normal. His abdomen is diffusely tender to palpation and guarding is present. Rectal examination is normal. The patient's blood pressure begins to drop rapidly and approaches 60/15 mm Hg. The trauma surgeon advises that an immediate exploratory laparotomy is warranted to ascertain the source of the internal bleeding. Hemoglobin is 5.5 g/dL.
Given the circumstances, which of the following is the most appropriate next step?
(Multiple Choice)
4.9/5 (73)
(73) A 16-year-old-girl comes to the clinic for follow-up after sustaining a head injury 7 days ago. The patient was playing soccer and her head collided with another player. She was seen in the office that day and diagnosed clinically with a concussion. The patient was instructed to rest for 2 days before beginning a gradual return-to-play program. She participated in light aerobic activity yesterday and began moderate aerobic activity exercises today. During training today, she developed nausea and felt dizzy. The patient has no chronic medical conditions. Blood pressure is 112/76 mm Hg, pulse is 90/min, and respirations are 16/min. The patient is alert and oriented. Cardiopulmonary examination is normal. Cranial nerves are intact. Strength is normal. Sensations and reflexes are equal bilaterally. Cerebellar examination and gait are normal. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (75)
(75) A 45-year-old woman comes to the office due to progressive stiffness, pain, and swelling of the joints in the hands and wrists for the past 3 months. The symptoms are worse when she wakes up and gradually improve after several hours. The patient also feels fatigued but has had no skin rashes, oral lesions, or fever. She recently began taking chlorthalidone for hypertension and takes no other medications. She works in a daycare center. The patient drinks alcohol occasionally and does not use tobacco or illicit drugs. Her mother had "arthritis" in her older age, and her sister has systemic lupus erythematosus. Temperature and other vital signs are within normal limits. Physical examination shows warmth, swelling, and tenderness of the second and third proximal interphalangeal joints, the metacarpophalangeal joints, and the wrists of both hands. The remainder of the examination shows no abnormalities. A week later, the patient returns to the office and says that her symptoms have improved with the prescribed treatment. Laboratory results are as follows:
 Hand x-rays reveal mild periarticular osteopenia and early erosions of the proximal interphalangeal and metacarpophalangeal joints. Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
5.0/5 (88)
(88) A 62-year-old female is being evaluated for vague epigastric discomfort which she has had for the past two months. She denies having nausea, vomiting, diarrhea, flank pain or urinary symptoms, but says she might have lost 2-3 pounds during this time. Her past medical history is significant for hypertension. Her daily medications are hydrochlorothiazide and lisinopril. She does not use tobacco or alcohol. Her family history is significant for breast cancer in her mother at age 72. On physical examination, the patient's blood pressure is 133/87 mmHg and heart rate is 73/min. Her BMI is 22 kg/m2. The remainder of the examination is unremarkable. Her laboratory test results are as follows:
 CT scan of the abdomen shows a 3.6 cm loculated cystic lesion in the head of the pancreas with some wall calcifications. What is the best next step in the management of this patient?
 (Multiple Choice)
4.7/5 (84)
(84) A 24-year-old man is brought to the emergency department by his girlfriend due to progressive weakness. They have been on a cross-country road trip for the past month. While traveling through the midwestern United States 2 weeks ago, the patient developed diarrhea, nausea, and vomiting. He rested, drank fluids, and improved spontaneously after 2-3 days. However, the patient had persistent fatigue, and 4 days ago they had to stop traveling as his legs became too weak to press down the brake pedal. He is now unable to get out of bed. The patient has also had tingling of the hands and feet as well as shortness of breath. He has had no fever, chills, abdominal pain, or recurrent diarrhea. The patient has no prior medical problems and takes no medications. He does not use tobacco, alcohol, or illicit drugs. Temperature is 37.7 C (99.8 F), blood pressure is 120/70 mm Hg, pulse is 90/min, and respirations are 20/min. Pulse oximetry shows 98% on ambient air. The patient is awake, alert, and speaking in full sentences but develops a weak cough after taking a sip of water. The lungs are clear to auscultation and heart sounds are normal. The abdomen is soft and nontender. Neurologic examination shows symmetric bilateral lower extremity weakness. Deep tendon reflexes are absent at the knees and ankles, and 1+ in the biceps and triceps. Cranial nerve examination and sensation are normal, and he has no neck rigidity. There is no skin rash or lymphadenopathy. Which of the following is the best treatment modality for this patient?
(Multiple Choice)
4.7/5 (81)
(81) A 6-year-old girl is brought to the office by her parents due to swelling on the right side of her neck. Two weeks ago, the patient's mother first noticed a mass on her daughter's neck; although the mass size remains unchanged, it has become more painful. Initially, her parents tried to treat the pain with ibuprofen and warm compresses, but with minimal relief. A 7-day course of oral clindamycin resulted in no improvement. The mass has become so painful that the patient is unable to fall asleep and tries not to turn her head. Today, she reports a foreign body sensation in her eyes and increased tearing. She has had increased fatigue and decreased appetite but no fever, weight loss, or difficulty swallowing. The patient has environmental allergies and seborrhea. She has a kitten and 2 hamsters. Temperature is 37.2 C (99 F). Examination of the right eye shows injected conjunctivae and scant clear discharge. The left eye is unaffected. Tympanic membranes are clear bilaterally. The posterior oropharynx is clear and without erythema or exudates. There is a 3-cm (1.2-in), tender, indurated, mobile cervical lymph node and a smaller 1-cm, tender, preauricular lymph node, both on the right side of the neck. Which of the following complications is most likely to develop in this patient?
(Multiple Choice)
4.8/5 (89)
(89) A 5-year-old boy is brought to the office for his annual well-child visit. The boy was briefly hospitalized a month ago for an asthma exacerbation, which was treated with albuterol and oral corticosteroids. He has been well since then except for a runny nose and cough for the past 2 days. He takes an inhaled corticosteroid daily and albuterol as needed, most recently 3 weeks ago. The patient lives at home with his mother, who is 38 weeks pregnant, and his father and 2-year-old sister. He recently started kindergarten and is doing well. Temperature is 36.7 C (98 F). The patient is tracking along the 40th and 60th percentiles for weight and height, respectively. Physical examination shows a well-appearing boy who speaks clearly in full sentences, counts to 12, and can hop on one foot. The lungs are clear to auscultation, and the remainder of the examination is unremarkable. He is scheduled to receive the second dose of measles-mumps-rubella (MMR) vaccine today. The parents say, "After his first MMR shot a few years ago, he had a fever up to 39.4 C (103 F), and we almost took him to the emergency department." Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (81)
(81) A 38-year-old woman in the intensive care unit is evaluated for worsening hypoxia. The patient was admitted a week ago due to dyspnea and nonproductive cough. At that time, diffuse crackles were found on lung examination, and chest x-ray revealed bilateral infiltrates. The patient smoked crack cocaine and used intravenous heroin prior to symptom onset. She required endotracheal intubation due to hypoxic respiratory failure and has been mechanically ventilated. Her respiratory condition has gradually improved over the past week, but in the last 2 days she has required a higher fraction of inspired oxygen. The patient has also had increased tracheobronchial secretions. Temperature is 38.9 C (102 F), blood pressure is 112/71 mm Hg, pulse is 114/min, and respirations are 22/min. Central venous pressure is 8 cm H2O. Lung auscultation reveals bilateral crackles. Heart sounds are normal with no murmur or gallop. The abdomen is soft and nondistended with normoactive bowel sounds. She has no dependent edema or skin rash. Ventilator settings, arterial blood gases, and laboratory results are as follows:  Repeat chest x-ray reveals asymmetric worsening of the lung infiltrate. Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (84)
(84) A 22-year-old man comes to the clinic for routine follow-up of his mild asthma. He has a history of keeping his appointments but has missed the last three. Today he seems distracted and uninterested, answering various questions with very brief replies. At one point, the patient says that he would like to hurry the visit along so he can get home sooner. Following inquiries about his social life, he becomes more animated and describes spending time with new friends who "really know how to party." On further questioning, he says, "I have been snorting cocaine sometimes but it's not a big deal. I haven't used any this past week. I quit school because it was just stupid and I was wasting my money. I'm working as a waiter now and enjoying it. At least I can make my own money and not be dependent on my parents." The patient says that he has been living with his new friends since his parents asked him to move out 2 weeks ago, but he would "rather not talk about that." He denies any symptoms of depression, mania, or psychosis. Temperature is 37.7 C (99.9 F), blood pressure is 120/82 mm Hg, pulse is 86/min, and respirations are 15/min. Physical examination shows perforations of the nasal septum. After discussion, the patient agrees to curtail his cocaine use and says that it will not be a problem. He is receptive to a back-up plan of referrals to 12-step group programs and outpatient substance abuse programs. The physician asks for permission to speak with his parents, and the patient says he will think about it. However, he fails to attend his 1-month follow-up appointment. Six months later, the patient makes an appointment to renew his asthma medications. When the physician notes multiple track marks on his arms, the patient admits he has been injecting cocaine. He has lost his job as a waiter and is currently unemployed. He has not spoken to his parents and is temporarily staying with a friend who also uses drugs. The patient says he tried a few Narcotics Anonymous meetings but did not attend regularly and has been unable to stop using. He admits to feeling depressed and has lost 4.5 kg (10 lb). He has no suicidal ideation. Which of the following is the most appropriate step in managing the patient's substance use problem?
(Multiple Choice)
4.7/5 (81)
(81) A 3-year-old girl is brought to the emergency department due to pain and fever. Two days ago, she developed mild abdominal and back pain. Her fever began yesterday morning and reached a maximum of 40.1 C (104.2 F) last night. Over the last 8 hours, she had 6 episodes of emesis but has since tolerated a few sips of water. The girl has a history of constipation since the start of toilet training at age 2 and has "pellet-like" stools once a week. She has frequent urinary accidents during the day and night. She takes no medications and has no other medical problems. Immunizations are up to date. Temperature is 40 C (104 F), blood pressure is 90/60 mm Hg, pulse is 110/min, and respirations are 20/min. Physical examination shows a tired-appearing girl with dry mucous membranes. She has right costovertebral tenderness. The abdomen is soft, nontender, and nondistended. The remainder of the examination is unremarkable. Laboratory results are as follows:  A 20-mL/kg normal saline bolus is administered. The patient has another episode of emesis and an additional void in the emergency department. The patient is admitted to the hospital, and intravenous antibiotics are started. Urine culture is positive for pansensitive Escherichia coli. Blood culture is negative. After 48 hours, the patient is tolerating oral fluids and is afebrile. The patient is discharged from the hospital on oral antibiotics. Which of the following should be recommended to prevent recurrence of this patient's infection?
 (Multiple Choice)
4.8/5 (77)
(77) A 32-year-old Caucasian man comes to the office for a routine follow-up visit. He was diagnosed with epilepsy three years ago, and has been taking carbamazepine 800 mg/day ever since. He does not use tobacco, alcohol or illicit drugs. His family history is not significant. Physical examination shows no abnormalities. The patient is concerned about the potential side effects of his medication. Which of the following complications is this patient at greatest risk for?
(Multiple Choice)
4.9/5 (82)
(82) Showing 181 - 200 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)