



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


A 9-year-old boy is brought to the emergency department by his aunt with right arm pain and swelling after falling in his backyard. The aunt says that the boy fell off the monkey bars and landed on his right hand. There was no head injury or vomiting. On physical examination, the child screams in pain and feels tingling in his right fifth digit. The right elbow is swollen and deformed. The right radial pulse is 1+ and sensation is intact. Radiographs are obtained. The boy's aunt is not his legal guardian but would like him to be treated for this injury. His parents are currently out of town and cannot be reached by phone. The aunt mentions that the boy was treated at this hospital 3 months ago and his mother gave consent for treatment at that time. Which of the following is the most appropriate next step in the management of this patient?
(Multiple Choice)
4.8/5  (64)
(64) A 55-year-old man is brought to the emergency department with severe abdominal pain and vomiting for the last 24 hours. The patient's abdominal pain began abruptly, and he describes it as a stabbing sensation radiating to his back. He then developed malaise, chills, nausea, and several episodes of vomiting. The patient's medical history includes hypertension, hyperlipidemia, and gout. Medications include chlorthalidone, atorvastatin, and allopurinol. Family history is unremarkable. The patient occasionally uses alcohol and has smoked a half a pack of cigarettes a day for 20 years. He does not use illicit drugs. Temperature is 39.4 C (102.9 F), blood pressure is 105/58 mm Hg, pulse is 110/min, and respirations are 18/min. BMI is 27 kg/m2. Physical examination shows a middle-age man in moderate distress. The patient has scleral icterus, normal jugular venous pressure, clear lung fields, and distinct S1 and S2. The abdomen is soft and tender to palpation over the midepigastrium and right upper quadrant. There is no rebound tenderness, rigidity, hepatomegaly, or splenomegaly. The remainder of the examination is normal. Laboratory test results are as follows: 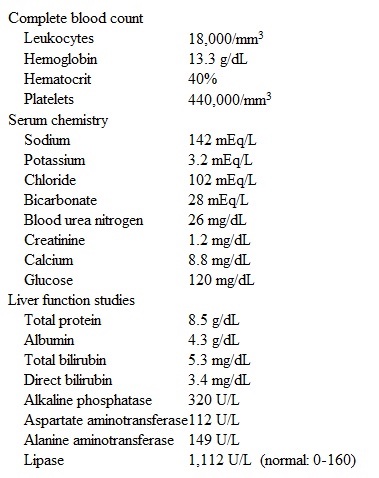 Abdominal ultrasound demonstrates multiple small gallbladder stones and common bile duct dilation. No stones are visualized in the biliary tree. The pancreas is not well visualized due to gastric shadow. Blood cultures are drawn. The patient is admitted and treated with intravenous fluids and antibiotics. Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.8/5 (75)
(75) A 71-year-old man is brought to the emergency department by his daughter for evaluation of an episode of slurred speech and right upper extremity weakness. The symptoms began approximately 3 hours ago and lasted an hour. He had no associated headache, chest pain, palpitations, shortness of breath, or syncope. The patient has had no similar episodes in the past. He now feels well. Medical history is significant for hypertension. He has a 60-pack-year smoking history but quit 8 years ago. The patient's mother had atrial fibrillation. Blood pressure is 162/96 mm Hg and pulse is 92/min. BMI is 33 kg/m2. Auscultation of the upper anterior cervical triangle on the left side of the neck reveals a bruit. Neurologic examination is normal. No lower extremity edema is present. Low-density lipoprotein cholesterol is 110 mg/dL. ECG shows normal sinus rhythm and nonspecific ST-segment and T-wave changes. MRI of the brain shows mild age-related changes but no areas of restricted diffusion. MR angiogram reveals 75% stenosis of the proximal left internal carotid artery and normal intracerebral vessels. Echocardiography shows left ventricular hypertrophy, normal left ventricular function, and mild left atrial enlargement. A patent foramen ovale is detected via agitated saline study. Lower extremity ultrasound is negative for deep vein thrombosis. He is started on aspirin and rosuvastatin. Which of the following is the best management strategy for this patient?
(Multiple Choice)
4.9/5 (96)
(96) A 26-year-old Italian-American man comes to your office for the evaluation of low back pain. He has had this pain for the last eight months, and it is progressively getting worse. The pain is worse in the morning and gets better as the day progresses. He denies any history of trauma in the past. He works as a chef at a local restaurant. His father and uncles also have "back problems." His physical examination reveals a limited range of motion of his lumbosacral spine and markedly reduced chest expansion. The rest of his physical and musculoskeletal examination is unremarkable. Which of the following is the most appropriate statement regarding the prognosis of this condition?
(Multiple Choice)
4.8/5 (81)
(81) A 46-year-old African American man comes to the physician with a "funny feeling" in his face that started yesterday. He has difficulty smiling and chewing on the right side of his mouth. Cigarette smoking has also been difficult because he is unable to "puff." He has "cold sores" every few months that correlate with stressful deadlines at his computer programming job. He smokes 1 pack of cigarettes daily. He lives in Arizona and has not traveled outside of the state in at least 3 years. Physical examination shows wrinkling of the left forehead with ipsilateral eyebrow elevation. He is unable to raise his right eyebrow, and his right forehead remains smooth. When the patient is asked to close his eyes, his right eye remains partially open. The right side of his mouth appears droopy. The remainder of his examination is normal. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (74)
(74) A 26-year-old man comes to the office after learning that one of his sexual partners tested positive for HIV. The patient has had intermittent headaches, malaise, nausea, and blurry vision over the last several weeks. He has had no fever, sore throat, skin rash, genital lesions, or weight loss. The patient has no prior history of sexually transmitted infections or chronic medical problems. He smokes a pack of cigarettes daily, consumes alcohol occasionally, and does not use illicit drugs. The patient has had multiple sexual partners over the last several years and does not use condoms consistently. Temperature is 37.1 C (98.8 F), blood pressure is 122/74 mm Hg, and pulse is 72/min. There is no scleral icterus, oropharyngeal lesions, or skin rash. Mild, generalized lymphadenopathy is present. Cardiopulmonary and abdominal examinations are normal. Cranial nerves, deep tendon reflexes, and sensation are normal. No nuchal rigidity is present. Ophthalmologic examination reveals no abnormalities. Screening HIV immunoassay is positive. Other laboratory studies are as follows:  A subsequent fluorescent treponemal antibody absorption test is positive. Contrast-enhanced CT scan of the head reveals no space-occupying lesions. Additional tests are performed and are normal. Which of the following is the best treatment option?
 (Multiple Choice)
4.9/5 (74)
(74) A previously healthy 28-year-old Caucasian woman comes to the physician because of fatigue, arthralgias, and chest pain over the past 6 months. She has had a 2.3-kg (5-lb) weight loss during this period. She denies any recent travel or sick contacts. Her past medical history is insignificant. She takes no medications and has no known drug allergies. She is sexually active and uses condoms for contraception. She has never been pregnant. She does not use tobacco, alcohol, or drugs. Her mother has rheumatoid arthritis. Her temperature is 37.2 C (99 F), blood pressure is 122/77 mm Hg, and pulse is 78/min. Physical examination shows a faint facial rash. The lungs are clear to auscultation with mildly decreased breath sounds at the left lung base. The abdomen is soft and non-tender. There is no organomegaly. There is no peripheral edema. Neurologic examination is unremarkable. Further evaluation reveals a positive antinuclear antibody (ANA) screen in high titers. Other lab studies show: 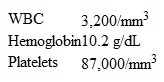 Which of the following antibody titers is most likely to correlate with the disease activity in this patient?
 (Multiple Choice)
4.9/5 (88)
(88) A 32-year-old woman comes to the office due to heavy vaginal bleeding. For the past 6 months, the patient has had regular menses every 30 days, with 7 days of painful cramping, heavy vaginal bleeding, and passage of large clots. She uses both a tampon and a sanitary napkin simultaneously to prevent blood from staining her underwear and soaking through her clothes. The patient has had no intermenstrual bleeding or abnormal vaginal discharge. Her last menstrual period ended a week ago. Her menses previously consisted of 5 days of mild cramping with moderate bleeding. Past medical history is significant for recurrent migraines with aura, for which she takes daily prophylaxis. The patient is sexually active and uses condoms and spermicide for contraception. She would like to attempt to conceive in the next few years. Blood pressure is 100/70 mm Hg and pulse is 84/min. BMI is 23 kg/m2. Pelvic examination reveals a 14-week-sized, irregularly shaped uterus with no cervical motion tenderness or adnexal masses. Hemoglobin is 9.8 g/dL. A urine pregnancy test is negative. Pelvic ultrasound shows a large uterus with several intramural leiomyomas and a normal endometrial stripe. The patient asks what can be done to treat her condition. Which of the following is the most appropriate management at this time?
(Multiple Choice)
4.8/5 (83)
(83) A 26-year-old woman comes to the physician to monitor her thyroid medication. She has a history of papillary thyroid cancer that was treated with a subtotal thyroidectomy and ablative radioiodine 3 years ago. The tumor was 2.1 cm in greatest dimension without lymph node involvement or distant metastasis. She currently takes 125 mcg of levothyroxine on an empty stomach every morning and has no current symptoms. Laboratory tests show undetectable thyroglobulin, undetectable anti-thyroglobulin antibodies, TSH of 4.8 μU/mL, and free T4 of 1.3 ng/dL (normal 0.8-1.8 ng/dL). One year ago, her total body radioactive iodine scan and neck ultrasound were unremarkable. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (73)
(73) A 46-year-old woman comes to the office for follow-up of rheumatoid arthritis. The patient was diagnosed 2 years ago and started on treatment with prednisone and methotrexate; she had a good initial response to treatment, and the oral glucocorticoid was gradually tapered. However, her symptoms have progressively worsened over the last several months, despite increases in the methotrexate dose. The patient continues to have hand stiffness and pain lasting 2-3 hours every morning and increasing knee and ankle pain. She takes frequent doses of acetaminophen and ibuprofen but her symptoms still significantly restrict her daily activities. Medical history is otherwise unremarkable. The patient does not use tobacco, alcohol, or illicit drugs. Physical examination shows symmetric swelling and tenderness of the proximal small hand joints, wrists, and knees. Blood cell count shows mild normochromic, normocytic anemia with normal leukocyte and platelet counts. Erythrocyte sedimentation rate is 55 mm/hr. Hand x-ray reveals periarticular osteopenia and mild joint erosions.
After discussion of treatment options, tumor necrosis factor inhibitor therapy is planned. Which of the following tests is most appropriate prior to beginning the treatment?
(Multiple Choice)
4.8/5 (86)
(86) A 32-year-old woman comes to the office due to abnormal liver imaging. The patient went to the emergency department a week ago for severe right flank pain radiating to the groin. A CT scan revealed a small ureter calculus, which she passed spontaneously the following day. The scan also found a solitary liver lesion, and the patient was advised to follow up with her primary care physician. She reports no right upper quadrant pain, nausea, jaundice, or clay-colored stool. She has no chronic medical problems and has no history of surgery or blood product transfusions. There is no history of cancer or liver disease in her family. She has taken combined oral contraceptives for the past 8 years. The patient does not use tobacco, alcohol, or illicit drugs. She works in a bank, is in a monogamous relationship with her husband, and recently traveled to Europe for her honeymoon. Vital signs are within normal limits. There is no scleral icterus, mucosal lesions, lymphadenopathy, or skin rash. Cardiopulmonary examination shows no abnormalities. Bowel sounds are active in all quadrants. The abdomen is nondistended, soft, and nontender. Liver is not enlarged, and spleen is not palpable. Laboratory results are as follows: 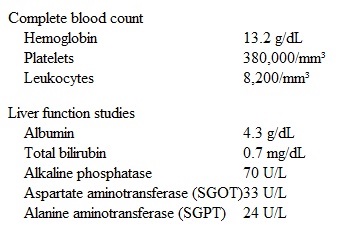 A CT scan of the abdomen reveals a 3-cm, well-demarcated lesion in the right lobe of the liver that shows peripheral enhancement with intravenous contrast administration. There are no areas of hemorrhage, necrosis, or scarring. The remainder of the liver is normal. Which of the following is the most appropriate response to this patient regarding her liver lesion?
 (Multiple Choice)
4.8/5 (87)
(87) A 32-year-old woman returns to the office due to acne. For the past 3 months, the patient has been applying topical clindamycin, benzoyl peroxide, and tretinoin on the face and neck, with only partial improvement. In addition, she has been using a salicylic acid-containing gel cleanser morning and evening. The acne tends to worsen before menses, which occur every 28-30 days and last 5-7 days. During menses, the patient also craves chocolate, sometimes eating multiple bars a day. Medical history includes recurrent vaginal candidiasis and a bilateral tubal ligation. Examination reveals comedones, papules, and pustules on the lower cheeks, chin, and neck but no scarring. Facial and body hair distribution is normal. Which of the following is the most appropriate next step in management of this patient's acne?
(Multiple Choice)
4.9/5 (81)
(81) A 54-year-old man with new-onset type 2 diabetes mellitus comes to the physician for his first screening ophthalmologic examination. He has no eye symptoms and describes his vision as excellent. He does not smoke. His family history is significant for obesity and diabetes but negative for cancer. Funduscopic examination shows a small, densely pigmented lesion with irregular borders in the peripheral right choroid. The lesion is about 8 mm in diameter and is minimally raised (1 mm). Comprehensive skin examination is unremarkable. The patient is lost to follow-up. He returns 2 years later due to intermittent blurry vision. His HbA1c is 8.2%. Repeat funduscopic examination shows that the pigmented lesion now measures 18 mm in diameter and its height is estimated at 4 mm. Comprehensive skin examination is unremarkable. Further evaluation shows no lesions beyond the right eye. Which of the following is the best next step in the management of this patient?
(Multiple Choice)
4.8/5 (78)
(78) A 37-year-old woman, gravida 4 para 3, comes to the emergency department due to contractions and vaginal bleeding. She has no leakage of fluid and has had normal fetal movement. The patient did not receive prenatal care, and her last menstrual period was 10 months ago. Her 3 prior pregnancies ended in uncomplicated, term vaginal deliveries. The patient has no chronic medical conditions and takes no medications. Blood pressure is 130/82 mm Hg and pulse is 78/min. The fetal heart rate shows moderate variability, no accelerations, and occasional late decelerations. The tocodynamometer shows contractions every 3 minutes. The cervix is dilated 8 cm and 100% effaced, and the fetal head is at +1 station. The patient is admitted and precipitously delivers a small-for-gestational-age (2.8-kg [6.2-lb]) male infant. Apgar scores are 8 and 9 at 1 and 5 minutes, respectively. The infant has green, wrinkled, peeling skin; thin fingers; and long fingernails. Loose skin and prominent skin creases are noted over the thighs and buttocks. The placental membranes are stained green. The remainder of the examination is unremarkable. Which of the following is the most likely cause of this infant's examination findings?
(Multiple Choice)
4.7/5 (92)
(92) A 13-year-old girl is brought to the emergency department by paramedics due to difficulty breathing that started 30 minutes ago. She was at an amusement park with her family when she was stung by a bee on her left ear. The patient experienced shortness of breath; itching; and a raised, red rash on her face and neck minutes after the sting. Medical history includes asthma that is well controlled on budesonide. Blood pressure is 80/40 mm Hg, pulse is 144/min, and respirations are 28/min. Pulse oximetry shows 92% on a nonrebreather mask. The patient is in obvious distress. The oropharynx is patent and without swelling. On auscultation of the lungs, severe bilateral wheezing is present. Heart sounds are rapid without murmurs. There are multiple raised erythematous papules on her face, neck, and upper chest. The patient's vital signs normalize, and symptoms resolve completely an hour after a single dose of epinephrine and nebulized albuterol. What is the appropriate disposition for this patient?
(Multiple Choice)
4.9/5 (76)
(76) A 62-year-old Caucasian man comes to the physician because of progressive weight loss and right lower extremity weakness for the last two months. On further questioning, he tells you that he has been having frequent leg cramps in the right leg. These cramps are most prominent in the morning, after he wakes up. He also has difficulty with swallowing and chewing. He denies any problems with bowel or bladder function. His other medical problems include hypertension and hypercholesterolemia. He does not use tobacco. His family history is not significant. His vital signs are within normal limits. The physical examination reveals weakness in his right lower leg, atrophy and fasciculation of the thigh and calf muscles, a hyperactive knee jerk, and tongue fasciculations. The rest of his neurological examination, including the sensory examination, is normal. Item 1 of 2
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (79)
(79) A 46-year-old truck driver comes to the office due to fatigue. He has consumed energy drinks during the past 3 months to complete his driving routes. He sleeps most of the day on weekends and avoids his wife and kids. The patient says, "I even slept through my son's baseball game. I felt really bad about that." He has a history of chronic back and knee pain due to a motorcycle accident. The patient's medications include naproxen. He drinks a few beers with friends but has not socialized much lately. The patient's wife says that he is never there for her and they fight constantly. He has no history of manic symptoms or other psychiatric history. Physical examination and routine laboratory studies are unremarkable. Mental status examination shows depressed mood and sad affect. The patient says he has had thoughts of suicide but would never do anything because of his children. He is diagnosed with depression and started on sertraline. He returns for a 3-week follow-up, reporting little change. The patient says, "Some days I think I'm feeling a little better, but other days are really bad. I don't know about these pills. I've been taking them and don't have any side effects, but I still feel pretty bad."
Which of the following is the most appropriate response?
(Multiple Choice)
4.7/5 (75)
(75) A 65-year-old man is brought to the emergency department after a syncopal episode. He was sitting at the kitchen table when his wife saw him suddenly slump over. She estimates he was unresponsive for 30 seconds. He felt "completely fine" after the incident and was not confused. The patient sustained no trauma and does not remember any symptoms prior to the event. He has a history of benign prostate hyperplasia, hypertension, and a myocardial infarction requiring stent placement 3 years ago. He takes aspirin, carvedilol, atorvastatin, ramipril, and tamsulosin. Temperature is 36.7 C (98 F), blood pressure is 130/80 mm Hg, pulse is 60/min, and respirations are 14/min. Pulse oximetry shows 96% on room air. Physical examination reveals moist mucous membranes, normal jugular venous pressure, clear lung fields, and normal first and second heart sounds. There is trace edema of the lower extremities bilaterally. Neurologic examination is within normal limits. Complete blood count, basic metabolic panel, troponin, and chest x-ray are normal. ECG reveals normal sinus rhythm, Q waves in leads V2 to V4, normal QRS complex duration, and normal QTc interval. Transthoracic echocardiogram shows an apical wall motion abnormality with ejection fraction of 40%. Which of the following is the most likely cause of this patient's syncope?
(Multiple Choice)
4.9/5 (71)
(71) A 2-hour-old boy is evaluated in the newborn nursery due to an asymmetric Moro reflex. The infant was born via vaginal delivery to a 32-year-old woman, gravida 3 para 3. Labor was induced at 39 weeks gestation due to oligohydramnios noted on prenatal ultrasound. The mother received 5 doses of penicillin during labor for a positive test for group B Streptococcus. Labor was prolonged and required vacuum assistance due to difficult extraction. The pregnancy was complicated by gestational diabetes mellitus, which was not well controlled. The fetal lie was breech at 18 and 27 weeks gestation but was cephalic starting at 30 weeks. The infant weighs 4.6 kg (10 lb 3 oz, 99th percentile). Finger-stick glucose was 39 mg/dL at birth and increased to 54 mg/dL after formula. The infant is sleeping but wakes during examination and cries. A large cephalohematoma is noted at the vacuum site. Cardiopulmonary examination is normal. The right arm is adducted and internally rotated and the forearm is pronated at rest. When the Moro reflex is elicited, the right arm has decreased movement. The palmar grasp reflex is present in both hands. Which of the following risk factors likely contributed to this patient's abnormal neurologic findings?
(Multiple Choice)
4.8/5 (83)
(83) A 16-year-old boy is brought to the emergency department via ambulance. The school nurse who accompanied him informs the physician that he has had 2 days of headache and generalized body aches that did not respond to acetaminophen. He felt well enough to attend school and to work his part-time job at a local hardware store. However, this morning his headache worsened and he was extremely drowsy. The paramedics administered intravenous normal saline; no other interventions were required during transport. In the emergency department, he becomes lethargic, has a seizure, and is immediately intubated by the resident physician. Subsequent evaluation reveals that the patient is suffering from acute meningococcal meningitis. The individuals requiring antibiotic prophylaxis are identified and contacted. Which of the following is the most appropriate therapy for chemoprophylaxis against meningococcal meningitis?
(Multiple Choice)
4.9/5 (89)
(89) Showing 761 - 780 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)