



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


A 17-year-old girl is brought to an urgent care center for sunburn. She was jogging outside for an hour today and subsequently developed redness and pain on the exposed portion of her arms and face. The patient says, "It wasn't even that sunny today. I've been outside for a lot longer than this and have never had a sunburn this bad." Her medical history includes acne vulgaris for which she was prescribed a topical and an oral medication, neither of which she can remember by name. She does not take any other medications and has no allergies. The patient is a long-distance runner for her high school track team. She lives with her father, who has dyslipidemia. Physical examination shows numerous comedones, papules, and pustules on her face and chest. Confluent areas of erythema, warmth, and edema are present on the patient's face and upper extremities. Her left arm is shown in the image below. 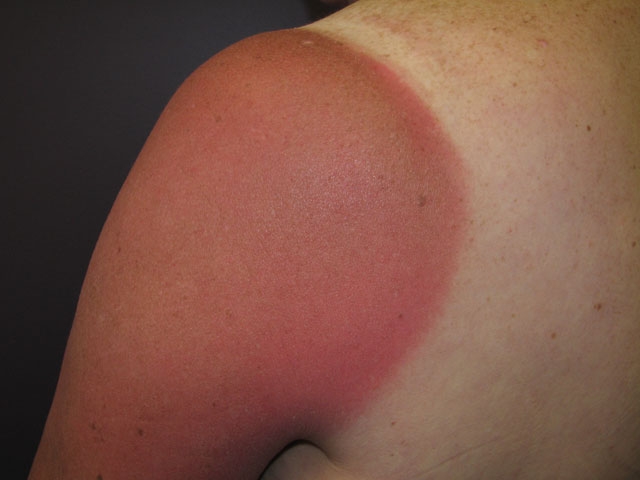 Which of the following medications most likely influenced the severity of this patient's sunburn?
 (Multiple Choice)
4.8/5  (97)
(97) A 25-year-old man comes to the employee health center for a physical examination prior to starting work as a patient care technician in a community hospital. The patient's family immigrated to the United States from Eastern Europe when he was a toddler. He received a medical evaluation prior to immigrating, but the records are not available. The patient has had no fevers, chills, night sweats, weight loss, cough, or fatigue. He has no chronic medical problems and takes no medications. He consumes alcohol occasionally but does not use tobacco or illicit drugs. The patient went on a 2-month backpacking trip through Central and South America a year ago. His immunization records are up to date. He has a small scar in the right deltoid area and notes that he received a bacillus Calmette-Guérin vaccination as an infant. The patient has no other abnormalities on physical examination. Item 1 of 2
Regarding pre-employment evaluation for tuberculosis, which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (70)
(70) A 30-year-old woman comes to the office due to tingling and numbness in both of her distal lower extremities for the last 3 months. Her symptoms are gradually worsening. She also has had intense fatigue. She has not had any weight change, constipation, skin dryness, headaches, or visual changes. The patient was diagnosed with primary hypothyroidism secondary to Hashimoto thyroiditis when she was 10 years old. She is currently on 100 mcg per day of levothyroxine orally. Her mother also has hypothyroidism. The patient does not use tobacco, alcohol, or recreational drugs. Her menstrual cycles have been irregular for the last 6 months. Her last menstrual period was 2 months ago. She is sexually active with one partner. Blood pressure is 114/78 mm Hg and pulse is 72/min. She weighs 69 kg (152 lbs) and is 163 cm (5'4") tall. Her thyroid is nonpalpable. Her mucous membranes are moist and pale. Her tongue appears to be bald. She does not have any scleral icterus. Vibration and proprioception are decreased in both of her lower extremities distally. Pain and temperature sensations appear normal. Her ankle jerks are absent, but other reflexes are brisk. Babinski is present, and Romberg signs is positive. The rest of the physical examination is unremarkable. Stool obtained from the rectal examination is negative for occult blood. Laboratory results reveal a hemoglobin of 8 g/dL and hematocrit of 24%. Her total leukocyte count is 3,200/mm3. Her platelet count is 300,000/mm3. Basic serum chemistries are within normal limits. Her total T4 level is 8.2 mcg/dL (normal 4-12 mcg/dL) and TSH level is 2.4 micro IU/mL.
What is the next best step in the management of this patient?
(Multiple Choice)
4.8/5 (77)
(77) A 29-year-old woman comes to the office due to 3 months of worsening exertional dyspnea and nonproductive cough. The patient says, "I thought the symptoms were from a cold or allergies, but they have not gone away and have gotten worse. None of the over-the-counter congestion medicines from the pharmacy have helped." She has also had occasional joint pain and has felt too tired to keep up with her exercise routine of running 5 miles 3 times a week. She has had no chest pain, palpitations, syncope, or leg edema. The patient has no chronic medical problems and does not use tobacco, alcohol, or illicit drugs. Her brother has asthma. Laboratory results are as follows:  Chest radiography is shown in the exhibit.
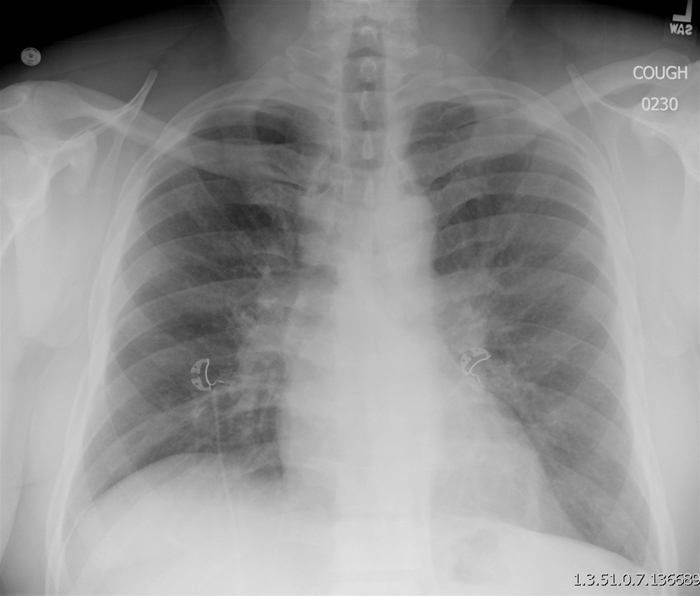 Pulmonary function testing reveals that FEV1 is 60% of the predicted value, FEV1/FVC is 80%, and diffusion capacity for carbon monoxide is 60% of predicted. After discussion of a likely diagnosis and possible therapy, the patient asks about long-term prognosis. Which of the following is the most appropriate response to this patient?
Chest radiography is shown in the exhibit. Pulmonary function testing reveals that FEV1 is 60% of the predicted value, FEV1/FVC is 80%, and diffusion capacity for carbon monoxide is 60% of predicted. After discussion of a likely diagnosis and possible therapy, the patient asks about long-term prognosis. Which of the following is the most appropriate response to this patient? (Multiple Choice)
4.8/5 (77)
(77) An 18-year-old woman comes to the emergency department with heavy vaginal bleeding for the past 3 days. The patient has soaked 6 thick sanitary pads today and has had several large blood clots. She has bled through her clothing for the past 2 nights. The patient has no syncope, palpitations, or dyspnea on exertion. There is no history of recurrent epistaxis, easy bleeding, or bruising. Menarche was at age 14; her menstrual periods have been irregular since the onset of menses. She has never been sexually active. The patient has no chronic medical conditions and has had no surgeries. Family history is noncontributory. She has no known drug allergies. The patient does not use tobacco, alcohol, or illicit drugs. Temperature is 37 C (98.6 F), blood pressure is 120/70 mm Hg, and pulse is 95/min. BMI is 28 kg/m2. Mucous membranes are moist and capillary refill is normal. Cardiac examination shows a normal rate and regular rhythm. Pelvic examination reveals bleeding from the cervix after several large clots are evacuated from the vaginal vault. On bimanual examination, the uterus is small and mobile; there are no adnexal masses. Urine pregnancy test is negative. Pelvic ultrasound shows a small uterus with a thickened endometrium and normal ovaries bilaterally. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (65)
(65) A 32-year-old man with type 1 diabetes comes to the emergency department with malaise, fatigue, and abdominal pain. His wife says that over the past 24 hours he has consumed large amounts of water and urinated frequently. On physical examination, the patient has dry mucous membranes. Laboratory testing confirms diabetic ketoacidosis. Shortly after admission, the patient suffers a seizure after accidentally receiving a bolus of insulin 10 times the amount indicated. He is transferred to the intensive care unit, where he experiences a ventricular arrhythmia and dies despite resuscitative measures. His wife is inconsolable and says that she plans to sue the hospital for her husband's death. The hospital administration enlists a team to perform a root cause analysis. Which of the following is the first step in performing this analysis?
(Multiple Choice)
4.9/5 (82)
(82) A 17-year-old girl comes to the office for increasing malodorous vaginal discharge over the past week. The patient has had no fevers, chills, nausea, dysuria, hematuria, vulvar pruritus, or postcoital bleeding. Her last menstrual period was 2 weeks ago. The patient's menses have become irregular since a progestin-containing intrauterine device was placed 8 months ago. She has no chronic medical conditions or previous surgeries. The patient is sexually active with a male partner and has had 2 lifetime partners. She does not use tobacco, alcohol, or illicit drugs. The patient has no known drug allergies. She is currently a senior in high school and will be going to a local university in the fall. Temperature is 37.2 C (99 F), blood pressure is 110/70 mm Hg, and pulse is 76/min. BMI is 20 kg/m2. Pelvic examination shows normal external genitalia with no lesions, erythema, or inguinal lymphadenopathy. Bimanual examination reveals no cervical motion tenderness, a mobile uterus, and no adnexal masses. On speculum examination, there is purulent discharge from the cervical os, and the ectocervix bleeds easily when touched with a cotton swab. The intrauterine device strings are visible in the cervix. A urine pregnancy test is negative. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (85)
(85) A 34-year-old woman comes to the office due to malaise and jaundice. The patient was in good health until about 4 weeks ago, when she developed joint pain, fatigue, and a pruritic rash over her trunk and extremities. The joint pain and rash resolved about a week ago, but the fatigue has persisted. Two days ago, the patient noticed some yellowish discoloration of the whites of her eyes and began to experience decreased appetite. However, she has been able to eat and drink without difficulty. Medical history includes irritable bowel syndrome and allergic rhinitis. Medications include docusate and intranasal fluticasone. She does not use any other over-the-counter medications. Immunization history is unknown. She is sexually active with 2 male partners and uses condoms inconsistently. The patient drinks on social occasions and does not use tobacco or illicit drugs. Temperature is 36.7 C (98 F), blood pressure is 110/64 mm Hg, and pulse is 68/min. BMI is 25 kg/m2. Physical examination is notable for moist mucous membranes, scleral icterus, and normal jugular venous pressure. Heart and lung sounds are normal. Abdominal examination reveals a palpable liver edge approximately 2 cm below the costal margin without tenderness. Bowel sounds are normoactive. The extremities are warm and without edema. The joints are nontender and without erythema. Neurologic examination is normal with no asterixis. The remainder of the physical examination is unremarkable. Laboratory results are as follows:
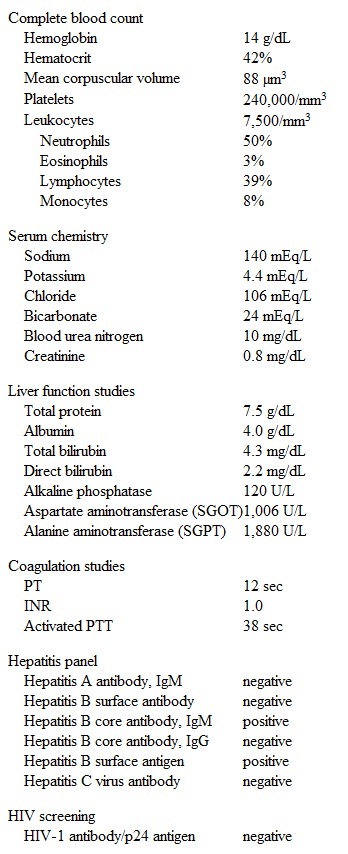 Urine pregnancy test is negative. Abdominal ultrasound reveals mild hepatic enlargement but no cirrhosis, gallstones, biliary ductal dilation, or ascites. Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.9/5 (76)
(76) A 30-year-old woman, gravida 3 para 0 aborta 3, comes to the office due to a history of recurrent spontaneous abortions. The patient has had 3 first trimester spontaneous abortions in the past 2 years that did not require medical or surgical management. Her menses occur every 30 days and consist of 4-5 days of moderate bleeding and mild cramping. Her Pap tests have been normal, and she has never had a sexually transmitted infection. The patient has no chronic medical conditions and takes no medications. She had a laparoscopic right ovarian cystectomy at age 18 for a large, benign cyst. She drinks alcohol on special occasions, but does not use tobacco or illicit drugs. She practices yoga 4-5 times a week. Blood pressure is 120/70 mm Hg and pulse is 74/min. BMI is 26 kg/m2. Bimanual examination reveals a smooth, normal-sized, nontender uterus and no adnexal masses or tenderness. Speculum examination shows minimal physiologic cervical discharge and a cervix with no visible lesions. Laboratory evaluation is normal. A hysterosalpingogram shows a filling defect in the middle of the uterine cavity and bilaterally patent fallopian tubes. Her husband has a healthy daughter from a prior relationship and recently had a semen analysis that was normal. The patient asks what can be done to prevent another miscarriage. Which of the following is the most appropriate response?
(Multiple Choice)
4.8/5 (68)
(68) A 66-year-old man comes to the clinic for a routine physical examination. He has chronic kidney disease, diabetes mellitus, hypercholesterolemia, and hypertension. His medications include aspirin, atorvastatin, hydrochlorothiazide, and metformin. The patient has smoked 2 packs of cigarettes daily for the past 22 years. His temperature is 37.2 C (99 F), blood pressure is 140/90 mm Hg, pulse is 80/min, and respirations are 12/min. Physical examination shows a palpable abdominal mass, and auscultation shows a bruit below his umbilicus. A CT angiogram with intravenous iodinated contrast is performed. His creatinine level on the day of the scan was 1.8 mg/dL and 2 days later was 2.6 mg/dL. Which of the following would most likely have prevented this complication in the patient?
(Multiple Choice)
4.9/5 (80)
(80) A 62-year-old Caucasian woman presents to her primary care physician complaining about her facial appearance. She says she dislikes "looking so much worse than all my friends." Specifically, she mentions that the deep wrinkles and brown spots on her face are what she finds most disturbing. Her past medical history is significant for breast cancer, hypothyroidism, and diverticulosis. Her only medications are levothyroxine, tamoxifen, and a multivitamin. She is a divorced mother of two and has recently retired from working as the supervising gardener of a large estate. She has a forty-year history of smoking one pack of tobacco per day and consumes one or two glasses of wine each night. She admits to occasional marijuana usage when she was a younger adult. Examination of her facial skin is remarkable for a general leathery appearance with many deep furrows and wrinkles. The wrinkles are especially prominent on the forehead and at the lateral corners of the eyes. The skin is sallow and has variable pigmentation. The surface texture is rough in areas. There are scattered flesh-colored scaly patches with slightly irregular margins and occasional clusters of what appear to be dilated superficial capillaries and venules.
The diagnosis is made. Which of the following factors is most likely to be responsible for worsening this woman's condition?
(Multiple Choice)
4.8/5 (95)
(95) An 18-year-old female presents to your office with dysuria and urinary frequency. She denies any fever, chills, or flank pain. She has a history of recurrent urinary tract infections, including two episodes over the last six months. She is otherwise healthy. She had no urinary problems in childhood. She has been sexually active with one partner during the last year. She takes oral contraceptives. Urine dipstick is positive for leukocyte esterase and nitrites. Urine cultures are sent. Polymerase chain reaction (PCR) is negative for gonorrhea and chlamydia. Pregnancy test is negative. Which of the following is the best management step for this patient?
(Multiple Choice)
4.9/5 (84)
(84) A 45-year-old Caucasian female presents to your office with abdominal discomfort and distention that is especially bothersome after meals. She has noticed recently that she gets tired more easily. She feels "down", but denies any sleep difficulty, crying spells and suicidal ideation. She visited a doctor approximately one year ago due to similar complaints, and was told that the problem was psychological. She underwent myomectomy for a large uterine fibroid 8 years ago. She is not sexually active. Her family history is significant for pancreatic cancer in her father and a thyroid disease in her mother. The physical examination is significant for mild pallor of the conjunctivae. The abdomen is somewhat distended with no palpable masses. The laboratory values are:  What is the best next step in the management of this patient?
 (Multiple Choice)
4.8/5 (68)
(68) A 28-year-old primigravid woman comes to the office for her first prenatal visit. She is 9 weeks pregnant by date of her last menstrual period. The patient reports excessive tiredness, intermittent nausea, and anorexia. She has also had subjective fever, night sweats, and dry cough. The patient has no prior medical problems and takes a prenatal multivitamin daily. She does not use tobacco, alcohol, or illicit drugs. The patient's mother recently came to visit her from Southeast Asia but had to return back early after becoming sick. Temperature is 38 C (100.4 F), blood pressure is 120/80 mm Hg, and pulse is 76/min. Sclerae are anicteric and mucous membranes are pink and moist. Heart sounds are normal with no murmurs. Fine crackles are present over the right posterior thorax. The abdomen is soft and nontender with no hepatosplenomegaly. Pelvic examination reveals an appropriately enlarged uterus. Chest radiograph reveals a right upper lobe infiltrate with a small cavity. Two of three sputum samples are positive for acid-fast bacilli. Liver function studies are within normal limits and testing for HIV, hepatitis B virus, and hepatitis C virus are negative. Which of the following is the most appropriate next step in management of this patient's pulmonary infection?
(Multiple Choice)
4.9/5 (75)
(75) A 62-year-old woman comes to the office for a preoperative evaluation 3 days before undergoing elective cholecystectomy. Over the past few months, she has had transient episodes of postprandial abdominal pain after large meals. Abdominal ultrasound confirms multiple gallstones. The patient feels well overall but has had 3 days of cough productive of green sputum and worsened dyspnea. She has a history of chronic obstructive pulmonary disease, myocardial infarction with stenting of the right coronary artery, hypertension, and obesity. She currently takes aspirin, lisinopril, rosuvastatin, amlodipine, albuterol, and ipratropium. She has had no previous surgeries. The patient has smoked a pack of cigarettes daily for 35 years but does not use alcohol or illicit drugs. Vital signs are within normal limits. Physical examination reveals moist mucous membranes and normal jugular venous pressure. Pulmonary auscultation indicates wheezing over the bilateral lung fields and prolonged expiration. There are no heart murmurs. No edema is present, and the remainder of the examination is normal. Which of the following interventions is most likely to reduce the incidence of postoperative pulmonary complications in this patient?
(Multiple Choice)
4.8/5 (71)
(71) A 48-year-old woman comes to the office due to a recurrent rash. Six months ago, a rash developed on her legs that she describes as "red patches with raised areas." The rash worsened that night with intense itching that disrupted her sleep. It spontaneously resolved over the next day. Since then, she has had repeated episodes of similar symptoms on her arms, legs, and back, each lasting 8-12 hours and occurring nearly every 2-3 weeks. She reports no trauma, insect bites, travel history, sick contacts, or changes in weight. Medical history is notable for hypertension treated with lisinopril. She does not use tobacco, alcohol, or illicit drugs. Temperature is 36.1 C (97 F), blood pressure is 138/77 mm Hg, and pulse is 78/min. Physical examination is within normal limits. The patient brings a photo of the rash, shown in the image below, from her most recent episode 2 days ago. Complete blood count, urinalysis, erythrocyte sedimentation rate, and liver function studies are within normal limits.
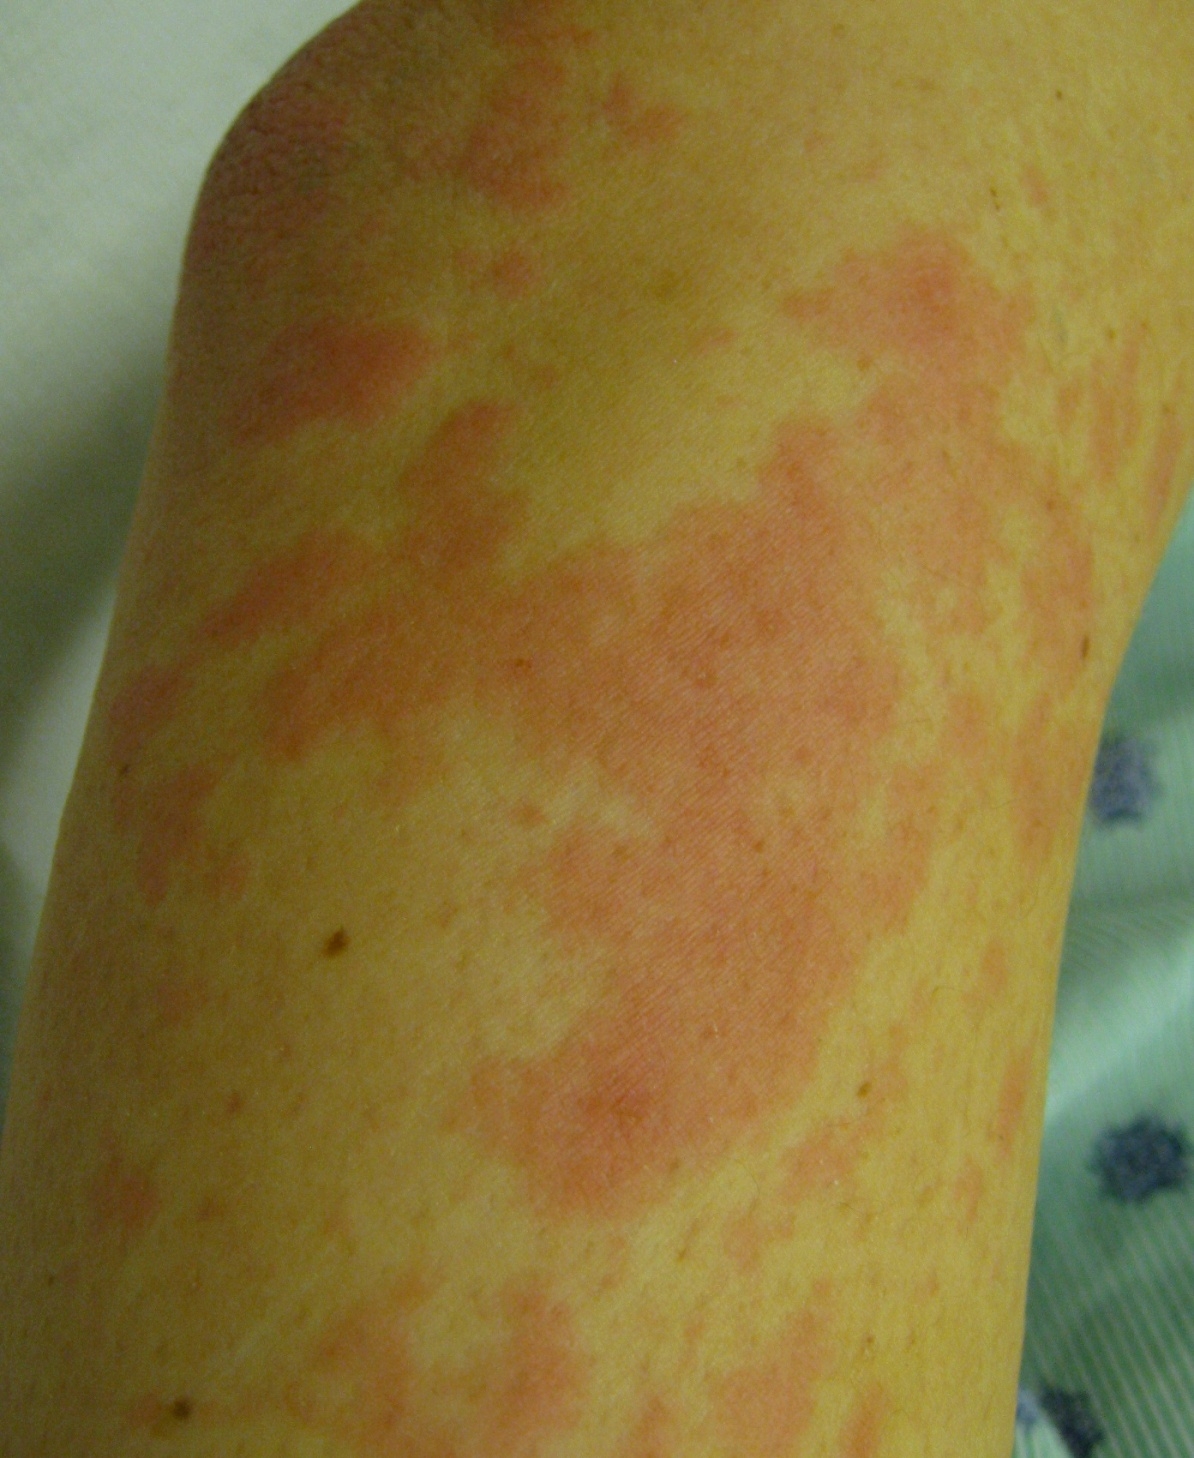 The patient currently has no rash but would like treatment recommendations for possible future episodes. Which of the following is the most appropriate treatment for this patient?
 (Multiple Choice)
4.8/5 (89)
(89) A 29-year-old woman, gravida 2 para 0 aborta 1, at 34 weeks gestation comes to the office for a routine prenatal visit. She reports no abdominal pain, leakage of fluid, or vaginal bleeding. There is normal fetal movement. Since her last visit 2 weeks ago, she has developed severe pruritus on her abdomen, which has not responded to over-the-counter moisturizers. The patient has had no recent contact with anyone who has had a fever, rash, or pruritus. She was diagnosed with gestational diabetes mellitus that is well controlled with an insulin regimen. Earlier in the pregnancy, she had an episode of vulvar candidiasis that was treated with a topical antifungal. The patient has no chronic medical problems or previous surgeries. She takes prenatal vitamins daily and has no allergies. The patient does not use tobacco, alcohol, or illicit drugs. Temperature is 36.7 C (98 F) and blood pressure is 100/70 mm Hg. BMI is 31 kg/m2. Fetal heart rate is 145/min and fundal height is 35 cm. Physical examination shows prominent abdominal striae and several red linear excoriations on the abdominal wall unrelated to the striae. Laboratory results are as follows:  The patient is prescribed treatment for her symptoms. She returns a week later for follow-up and reports good fetal movement and no contractions, vaginal bleeding, or leakage of fluid. Her pruritus has worsened, and blisters have appeared near her umbilicus and are spread out over her abdomen. Temperature is 36.7 C (98 F) and blood pressure is 100/70 mm Hg. Fetal heart rate is 145/min and fundal height is unchanged at 35 cm. Physical examination reveals the following:
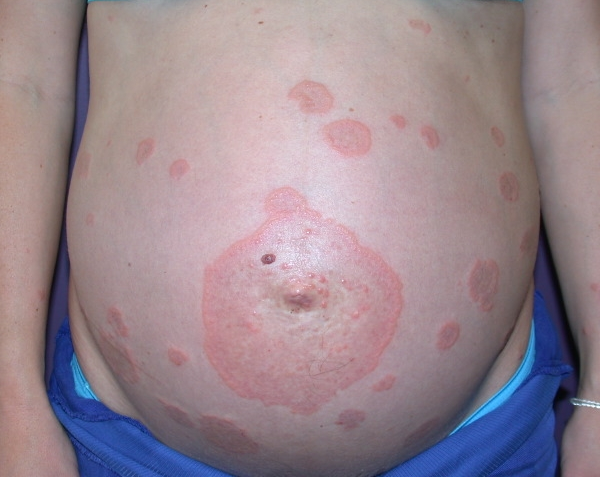 Which of the following is the most likely diagnosis?
The patient is prescribed treatment for her symptoms. She returns a week later for follow-up and reports good fetal movement and no contractions, vaginal bleeding, or leakage of fluid. Her pruritus has worsened, and blisters have appeared near her umbilicus and are spread out over her abdomen. Temperature is 36.7 C (98 F) and blood pressure is 100/70 mm Hg. Fetal heart rate is 145/min and fundal height is unchanged at 35 cm. Physical examination reveals the following: Which of the following is the most likely diagnosis? (Multiple Choice)
4.9/5 (88)
(88) A 36-year-old man comes to the emergency department with severe pain in his left leg. He is a carpenter and recalls that he had a small puncture wound from a wood splinter yesterday in his workshop. The patient washed the wound and applied a small adhesive bandage. This morning, he experienced severe pain in his left thigh and calf, and the pain has worsened since. He has no other medical problems and takes no medications regularly. His temperature is 39.4 C (103 F), blood pressure is 90/60 mm Hg, heart rate is 96/min, and respirations are 16/min. Physical examination of his left lower extremity shows slight erythema and swelling of the thigh and calf with severe tenderness to palpation. Two blisters are present on the posterior aspect of his proximal calf.
Which of the following is the most likely organism responsible for this patient's condition?
(Multiple Choice)
4.7/5 (79)
(79) A 70-year-old woman is brought to the emergency department by her son for evaluation of shortness of breath. She has had a sensation of choking since last night. According to her son, for the past several weeks she has had a dry cough at night and has been taking over-the-counter cough drops. The patient has had no chest pain, palpitations, back pain, abdominal symptoms, or lightheadedness. She has a history of hypertension, hyperlipidemia, and type 2 diabetes mellitus. She has been refusing statin therapy, as she heard statins cause multiple side effects. The patient has also refused flu vaccinations over the last several years. Her only hospital admission occurred 6 years ago when she underwent a spinal fusion for lower back pain. She does not use tobacco, alcohol, or illicit drugs. Family history is not significant. Temperature is 36.1 C (97 F), blood pressure is 171/102 mm Hg, pulse is 92/min, and respirations are 34/min. Pulse oximetry is 85% on room air. BMI is 29 kg/m2. Bilateral crackles are heard on lung examination. There are no heart murmurs. ECG shows normal sinus rhythm, increased voltage in the precordial leads, and T-wave inversion in leads V5 and V6. Chest x-ray is shown in the exhibit. 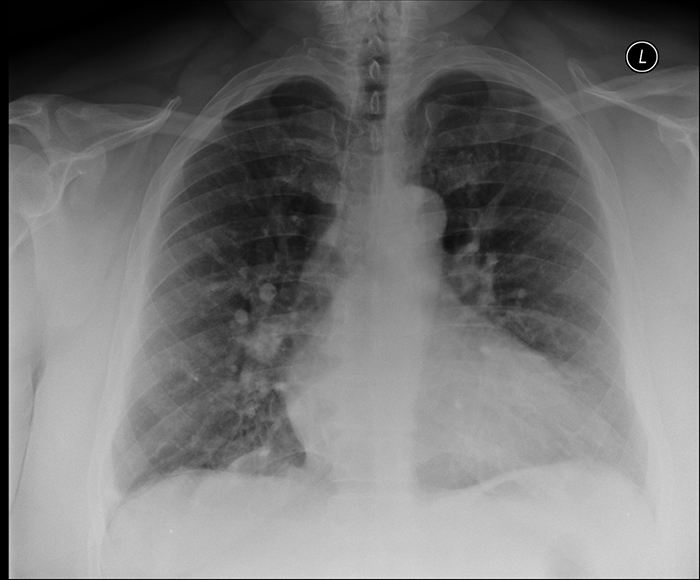 Oxygen is administered via 100% nonrebreather facemask.
Which of the following is the most appropriate next step in management of this patient?
Oxygen is administered via 100% nonrebreather facemask.
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.9/5 (71)
(71) A 23-year-old woman, gravida 3 para 2, at 35 weeks gestation comes to the emergency department due to vaginal bleeding that started after intercourse, 2 hours prior to arrival, and has soaked through 3 perineal pads. The patient reports normal fetal movement and mild intermittent cramping but no leakage of amniotic fluid. Her only prenatal visit was at 7 weeks gestation, when an ultrasound was normal. The patient has a history of 2 prior cesarean deliveries at term. The first delivery was performed for a category III fetal heart rate tracing; the second was an elective repeat. The patient has a history of intravenous drug use and smokes a pack of cigarettes a day. She has no known drug allergies. Blood pressure is 130/70 mm Hg and pulse is 98/min. The fetal heart rate tracing is 140/min with moderate variability, accelerations, and no decelerations. The tocometer shows contractions every 5 minutes. On examination, the patient is in no distress. The abdomen is gravid, soft, and nontender. There is frank blood on the patient's perineal pad. A bedside ultrasound reveals a low, posterior placenta that extends over the internal cervical os. The patient continues to have heavy vaginal bleeding, and a cesarean delivery is performed under spinal anesthesia. The infant and placenta are delivered without difficulty. However, prior to repair of the uterine incision, the patient reports increasing shortness of breath and becomes unresponsive. Blood pressure is 70/40 mm Hg, pulse is 124/min, and respirations are 34/min. Pulse oximetry is 86% on room air. A lung examination reveals decreased breath sounds bilaterally. Endotracheal intubation is performed and the airway is secured. Profuse bleeding is noted from the uterine incision and placental bed. Examination of the Foley catheter reveals frank blood in the collection bag. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
5.0/5 (77)
(77) Showing 521 - 540 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)