



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


A 78-year-old woman is brought to the emergency department after her neighbor found her slumped over on her front porch bench, unable to speak or walk. The neighbor reports that, 2 hours prior, he had seen the patient walking to her mailbox. He spoke with her for a few minutes, and she seemed normal at that time. The patient lives alone but has an adult daughter in another town. Vital signs are normal. Neurologic examination demonstrates right-sided hemiparesis and aphasia. The patient is a candidate for thrombolysis but does not appear to understand when the risks and benefits of thrombolysis are discussed. The daughter could not be reached by phone on the initial attempt. Which of the following is the most appropriate next step regarding consent for thrombolysis in this patient?
(Multiple Choice)
4.8/5  (94)
(94) A 48-year-old Caucasian woman comes to the physician because of a 1 week history of a lump in her neck. She has muscle pains and body aches. Upon further questioning, she adds that she often experiences a "gritty, burning sensation in both of my eyes, and sometimes they get red and inflamed." She does not wear contact lenses. She has not had fever, chills, weight loss, dysphagia, cough, hemoptysis, muscle weakness, or joint swelling. She has fibromyalgia, depression, and cholelithiasis. She has extensive caries of her teeth and has been visiting a dentist regularly. She does not use tobacco, alcohol, or drugs. Her only medication is fluoxetine. Her temperature is 37.0 C (98.6 F), blood pressure is 122/80 mm Hg, pulse is 76/min, and respirations are 14/min. Her BMI is 27 kg/m2. Examination shows a mobile, non-tender 2x2 cm right-sided submandibular mass. Item 1 of 2
Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.8/5 (74)
(74) A 56-year-old man comes to the emergency department due to chest pain that occurred at home. He was watching television when he developed left-sided chest pain described as dull and pressure-like. The pain progressively worsened and radiated to the throat but spontaneously resolved within 20 minutes. During the past week, the patient had 2 similar episodes with exertion at his job as a construction worker. He has had no palpitations, syncope, shortness of breath, or diaphoresis. He has a history of hypertension treated with lisinopril and is a lifetime nonsmoker. Family history is significant for stroke at a young age in a paternal uncle. The patient is currently free of chest pain and comfortable. Blood pressure is 150/80 mm Hg and pulse is 78/min. Physical examination is otherwise unremarkable. ECG shows sinus rhythm with T-wave inversion in leads V5 and V6. Chest x-ray is normal. Cardiac troponin I level is normal (<0.012 ng/dL). Aspirin, metoprolol, atorvastatin, clopidogrel, and subcutaneous enoxaparin are initiated. Eight hours later, he is still without chest pain. ECG is unchanged and repeat troponin I level is normal. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (79)
(79) A 12-year-old boy is brought to the emergency department due to brown urine for the past 2 days. In addition, the patient has had decreased urine output and a mild headache. He has no chronic medical conditions but was treated with oral amoxicillin 18 days ago for pharyngitis. The patient's family history is unremarkable. Temperature is 36.8 C (98.2 F), blood pressure is 150/92 mm Hg, pulse is 89/min, and respirations are 15/min. Physical examination shows a tired-appearing boy with edema in the scrotum and bilateral lower extremities. Laboratory results are as follows:  Complement component C3 levels are low. Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (79)
(79) A 54-year-old Indian female comes to your office because of dysphagia. She emigrated from India two years ago. She is the mother of a computer engineer, and lived her whole life in an iodine-deficient area in India. She denies any past medical problems, and is currently on no medications. For the past five months, she has been having some difficulty in swallowing large chunks of food, which seems to be progressively getting worse. She has no difficulty in breathing or swallowing liquids. Her weight is constant. She denies fever, cough, chest pain, abdominal pain, heat intolerance, sweating, or tremors. She is a vegetarian, and does not smoke or drink. She has never undergone any mammography or Pap smear screening. Her last menstrual period was four years ago. She has minimal hot flashes, and was never on hormone replacement therapy. Her family history is significant for a father with type-2 diabetes mellitus. Examination of her neck reveals a short neck with a very low lying thyroid; its lower margin could not be felt. The upper one-third of the sternum is dull on percussion. Her face becomes plethoric after raising her arms for one minute. There is no lymphadenopathy. The rest of the physical examination is normal. TSH is 0.78 μU/mL (normal 0.35-5.0 μU/ml), free T4 is 1.3 μU/ml (normal 0.8-1.8 μU/dl), and antithyroid peroxidase antibody is negative. Chest x-rays reveal a large upper mediastinal mass that is shifting the trachea to the left side. A CT scan of the chest reveals that the upper retrosternal mass is consistent with a large multinodular retrosternal thyroid gland. A barium swallow shows mild compression of the esophagus by the goiter. What is the best option for the management of this patient?
(Multiple Choice)
4.8/5 (71)
(71) A 60-year-old woman comes to the office due to new-onset pelvic pressure. The patient reports increasing pelvic pressure over the last 3 months, now with associated urinary frequency. She has no abdominal pain, dysuria, or hematuria. The patient reports some dyspnea on exertion; review of systems is otherwise negative. The patient has a history of breast cancer at age 45; it was treated with radical mastectomy, chemotherapy, and adjuvant tamoxifen therapy. The cancer has since been in remission and she had a normal mammogram last year. The patient has no other chronic medical conditions. She underwent menopause 8 years ago and has had no episodes of postmenopausal vaginal bleeding. The patient has had no abnormal Pap tests, the last of which was 3 years ago. She does not use tobacco, alcohol, or illicit drugs. Blood pressure is 130/80 mm Hg, pulse is 80/min, and respirations are 18/min. BMI is 26 kg/m2. Decreased breath sounds are noted over the lower base of the right lung. Abdominal examination reveals normoactive bowel sounds and mild distension but no tenderness. On bimanual examination, a 12-week-sized, irregularly shaped uterus is noted, but there are no adnexal masses. Urinalysis is within normal limits. Pelvic ultrasound shows a dense focal mass measuring 9 cm in the anterior fundus of the uterus, normal ovaries bilaterally, and a moderate amount of free fluid in the posterior cul-de-sac. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (89)
(89) A 31-year-old woman, gravida 3 para 0, comes to the office for contraception management. The patient has a history of 3 first-trimester spontaneous abortions and a left lower extremity deep vein thrombosis that occurred during the last pregnancy. During evaluation after the most recent spontaneous abortion, she was diagnosed with antiphospholipid antibody syndrome based on positive lupus anticoagulant and anticardiolipin antibody tests and was placed on chronic anticoagulation. The patient's menses occur every 30 days and consist of 5 days of heavy vaginal bleeding and 2 days of moderate cramping that is relieved by nonsteroidal anti-inflammatory medications. She has no other chronic medical conditions or previous surgeries. The patient does not use tobacco, alcohol, or illicit drugs. Her maternal grandmother was diagnosed with metastatic ovarian cancer at age 65; family history is otherwise noncontributory. Blood pressure is 110/70 mm Hg and pulse is 70/min. BMI is 23 kg/m2. Cardiopulmonary examination is normal. Pelvic examination reveals a normal-sized, nontender uterus and no adnexal masses or tenderness. Urine pregnancy test is negative. Which of the following is the best contraception option for this patient?
(Multiple Choice)
4.8/5 (59)
(59) A 72-year-old woman is brought to the emergency department by her husband with confusion and slurred speech. She was diagnosed with type 2 diabetes mellitus a year ago, and her medication regimen has been changed multiple times due to medication intolerance. Three weeks ago, the patient was started on a single-drug diabetes regimen. Her husband reports that since that time, her home glucose readings have been "all over the place," and she has "stopped eating junk food to try to smooth them out." Medical history is notable for hypertension and hyperlipidemia, for which she takes lisinopril, chlorthalidone, and atorvastatin. The patient also has osteoarthritis of the knees and has been intermittently taking an over-the-counter medication for pain. She does not use tobacco or alcohol. Blood pressure is 142/70 mm Hg and pulse is 101/min and regular. Mucous membranes are moist. Bedside capillary blood glucose is 35 mg/dL. An intravenous glucose solution is administered, with rapid improvement in her mental state. A basic metabolic panel shows serum potassium of 3.8 mEq/L and serum creatinine of 1.7 mg/dL, with an estimated glomerular filtration rate of 50 mL/minute/1.73 m2; serum creatinine 2 weeks earlier was 1.3 mg/dL. Which of the following medications is most likely to have caused this patient's condition?
(Multiple Choice)
4.8/5 (78)
(78) A 32-year-old woman, gravida 2 para 1, comes to the office for a routine prenatal visit. The patient had a postpartum hemorrhage (PPH) after her first pregnancy and is worried about the possibility of PPH after her scheduled repeat cesarean delivery. She read about the effectiveness of prophylactic tranexamic acid in reducing the risk of hemorrhage after scheduled cesarean delivery and wants to discuss the results. The outcomes of the study were PPH, clinical and laboratory (blood samples at day 2) measurements of postpartum blood loss, and several adverse events after scheduled cesarean delivery at ≥34 weeks gestation. Patients received intravenous infusion of a uterotonic agent and either tranexamic acid or saline placebo within 3 minutes after cesarean delivery. A summary of the results is shown in the table below. 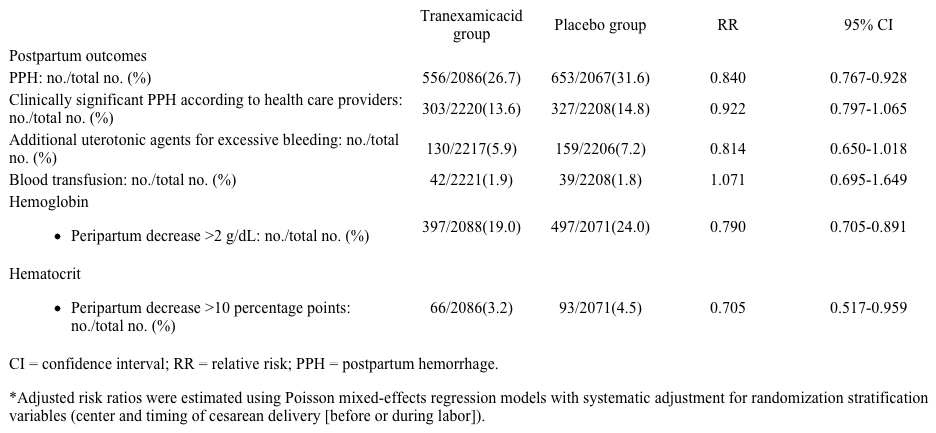 Based on the study results, which of the following conclusions is strongly justified?
 (Multiple Choice)
4.8/5 (65)
(65) What is the most appropriate means of correcting this patient's hyponatremia?
(Multiple Choice)
4.8/5 (70)
(70) A 35-year-old man comes to the emergency department due to 2 days of fever and dysuria. He has a history of paraplegia as the result of a gunshot wound 5 years ago that required surgical intervention. He takes narcotics for chronic pain that has developed since the surgery. The patient is bedbound and practices intermittent urinary self-catheterization. He has had multiple admissions for recurrent urinary tract infections; urine cultures have grown multidrug-resistant organisms requiring intravenous antibiotic therapy in the past. He most recently completed a course of antibiotics a week ago. The patient says, "It feels like my urinary tract infection is coming back-I was just done with antibiotics and was hoping I would get a break!" He reports that every 5 years of life in his current state of health are equivalent to 1 year of life in full health. Which of the following measures is best described by this value?
(Multiple Choice)
4.9/5 (86)
(86) A 55-year-old Caucasian male is brought to the emergency department by an ambulance after collapsing at a local golf course on a hot summer day. The man had been golfing with friends for several hours, when he reported feeling dizzy and seemed confused. His temperature is 41.2C (106.2F), blood pressure is 110/68 mm Hg, pulse is 104/min, and respirations are 25/min. The man is now unconscious. His skin is hot, dry, and flushed. Which of the following should be undertaken first in managing this condition?
(Multiple Choice)
4.9/5 (87)
(87) A 10-month-old boy is brought to the clinic due to abnormal feet and gait. The patient was recently adopted from overseas, and the adoptive parents state that he just began pulling himself up to stand a few weeks ago. However, he appears clumsy when trying to take steps. Height and weight are at the 25th percentile. Head circumference is at the 50th percentile. Vital signs are normal. The patient is alert while sitting in the parent's lap. The head appears normal, and the anterior fontanelle is open and flat. Examination of the chest is unremarkable, and the abdomen is soft and nontender. The back appears normal. Examination of the feet shows bilateral plantar flexion with adduction and inversion. The feet resist range-of-motion assessment. The knees and hips have normal range of motion. After pulling himself up to stand, the patient puts weight on the lateral sides of both feet. As he attempts to take a step, he falls. The parents ask about the prognosis of his condition. Which of the following is the most appropriate response?
(Multiple Choice)
4.9/5 (90)
(90) A 22-year-old woman comes to the office with right lower quadrant pain for the past 3 weeks. The pain is exacerbated with bowel movements, but there is no associated nausea, vomiting, diarrhea, constipation, or melena. She has no chronic medical conditions and has never had surgery. Family history is noncontributory. The patient has regular menstrual periods every 28-30 days. She is sexually active and uses condoms for contraception. She does not use tobacco, alcohol, or illicit drugs. Temperature is 37.2 C (99 F), blood pressure is 110/70 mm Hg, and pulse is 80/min. BMI is 24 kg/m2. Physical examination shows a well-appearing woman in no apparent distress. The abdomen is soft with normal bowel sounds. There is tenderness to deep palpation in the right lower quadrant without rebound or guarding. The uterus is small, nontender, and anteverted; there is no cervical discharge or cervical motion tenderness. The right adnexa is enlarged and tender. There is nodularity and tenderness on rectovaginal examination. This patient is at increased risk for which of the following conditions?
(Multiple Choice)
4.9/5 (83)
(83) A 3-week-old male infant with Down's syndrome is brought by his parents to your office due to feeding difficulties. According to the mother, the infant becomes short of breath and his face turns blue during feeding, and when he cries. On chest auscultation, there is a harsh holosystolic murmur heard best over the lower left sternal border. There are no rales or wheezing over the lung fields. In the long run, this infant is at increased risk of developing which of the following?
(Multiple Choice)
4.8/5 (82)
(82) A 74-year-old woman is brought to the emergency department with fever, chills, and shortness of breath. Two days ago, she choked while having tea and doughnuts and almost lost consciousness. Her son performed the Heimlich maneuver. The patient has advanced Alzheimer dementia, and her son is her health care proxy and primary caregiver; her 73-year-old husband also participates in her care. Her other medical problems include hypertension, hyperlipidemia, coronary heart disease, ischemic stroke with mild residual right hemiparesis, history of heme-positive stools, and urine incontinence. She is allergic to penicillin (anaphylaxis). Her temperature is 38.9 C (102 F), blood pressure is 120/80 mm Hg, pulse is 92/min, and respirations are 24/min. Pulse oxymetry shows 89% on room air and 94% on 40% facemask oxygen. Auscultation of the chest shows crackles at the right lung base. The heart sounds are regular. There is no jugular venous distension. The abdomen is soft, nontender, and nondistended. There is no peripheral edema. Laboratory results are as follows:  A portable chest x-ray shows a right lower-lobe infiltrate.
Item 1 of 4
Which of the following is the most appropriate next step in management of this patient?
A portable chest x-ray shows a right lower-lobe infiltrate.
Item 1 of 4
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.8/5 (87)
(87) A 72-year-old man comes to the emergency department due to progressive shortness of breath and cough productive of yellowish sputum. The patient says, "I have been feeling breathless for the past several months while mowing the lawn or walking around the house, but it has been worse over the last 3 days." He has had no chest pain or leg swelling but notes that his heart "has been racing." The patient has a history of hypertension, peptic ulcer disease, and osteoarthritis. He was hospitalized for pneumonia a year ago and required intravenous antibiotics. Six months ago, the patient underwent a cardiac stress test for chest discomfort, which was unremarkable. The patient has smoked a pack of cigarettes daily for 45 years. Blood pressure is 160/90 mm Hg, pulse is 148/min, and respirations are 26/min. He is speaking in partial sentences and using accessory muscles of respiration but is alert and cooperative. There is no jugular venous distension or heart murmurs, rub, or gallops, but the heart sounds are irregular. Lung auscultation reveals bilateral rhonchi and expiratory wheezes. Arterial blood gases while breathing 2 L of oxygen via nasal cannula reveal PO2 of 66 mm Hg, PCO2 of 52 mm Hg, and pH 7.33. ECG shows narrow QRS complexes with distinct P waves of different morphologies and variable PR segments and R-R intervals. Chest x-ray reveals no pulmonary infiltrates or consolidation. Inhaled bronchodilators and systemic glucocorticoids are administered.
Which of the following is the most appropriate additional step in management of this patient's arrhythmia?
(Multiple Choice)
4.8/5 (81)
(81) A 52-year-old Caucasian woman presents to the office for the evaluation of a constant left groin pain. The pain started spontaneously about a week ago and is gradually progressive. It is worse with walking and weight bearing. She has a past medical history of systemic lupus erythematosus, chronic renal insufficiency, and hypertension. She has been maintained on 20 mg/day of prednisone for eight months. Attempts to decrease the dose of prednisone in the past have caused a flare of lupus activity. She does not smoke or drink alcohol. On physical examination, she walks with a limp. There is marked discomfort and limitation of the range of motion on the left side. The radiologic imaging reveals that the patient has stage 4 osteonecrosis of the femoral head. She has considerable pain on weight bearing, and this is affecting her daily activities. Which of the following is the most appropriate next step in the management of this patient?
(Multiple Choice)
4.9/5 (85)
(85) A 27-year-old woman comes to the office for an annual physical examination. She currently works as a medical interpreter in a regional hospital. The patient feels well and has no medical problems. Her only medication is a daily oral contraceptive pill. She does not use tobacco, alcohol, or illicit drugs. The patient is up to date with recommended vaccinations and has had no known contact with a person infected with tuberculosis. Vital signs are within normal limits. Mucous membranes are moist and without lesions. Lung fields are clear to auscultation and heart sounds are normal. The abdomen is soft and nontender with no organomegaly. No skin rash is present. A tuberculin skin test is performed and produces a 12-mm induration at 48 hours. Chest radiography is normal, and urine pregnancy testing is negative. The patient receives counseling and initiation on anti-tuberculosis therapy. Which of the following is the most appropriate employment-related recommendation for this patient?
(Multiple Choice)
4.8/5 (90)
(90) A 44-year-old man with a medical history of food allergy to peanuts is brought to the emergency department for an allergic reaction. The patient developed the acute onset of dyspnea and wheezing shortly after ingesting a cookie. His symptoms progressed to difficulty swallowing and swelling of the face and tongue. On arrival, temperature is 36.9 C (98.4 F), pulse is 115/min, blood pressure is 85/74 mm Hg, and respirations are 28/min. Oxygen saturation is 93% on a nonrebreather face mask. He is anxious and pale with swollen lips, swollen tongue, and inspiratory stridor. On lung auscultation, bilateral wheezing is present. Intramuscular epinephrine, intravenous fluids, and racemic epinephrine via nebulizer are administered without improvement. The patient's distress is increasing, and he is becoming more agitated. The decision to intubate using awake fiberoptic nasotracheal intubation is made. Which of the following medications would be the best choice to aid in awake fiberoptic nasotracheal intubation in this patient?
(Multiple Choice)
4.8/5 (80)
(80) Showing 961 - 980 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)