



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


A 55-year-old woman comes to the office due to exertional dyspnea for 3 months. The patient has had no chest pain. Medical history is significant for hypertension and chronic kidney disease. Medications include furosemide, amlodipine, and lisinopril. The patient has never smoked cigarettes. Temperature is 37 C (98.6 F), blood pressure is 128/80 mm Hg, and pulse is 80/min. Oxygen saturation is 98% on room air. BMI is 27 kg/m2. There is no jugular venous distension. Cardiopulmonary examination is normal. Trace bilateral pedal edema is present. Laboratory studies are as follow:  ECG is unremarkable. Chest x-ray reveals clear lung fields. Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.8/5  (82)
(82) A 58-year-old obese woman comes to the physician with a 6-month history of intermittent, postprandial, colicky right-upper quadrant abdominal pain. Each bout of pain lasts about 15 minutes. The patient has a 10-pack-year smoking history (she quit 20 years ago) and drinks alcohol socially. Both her parents died of heart attacks. Her older brother is in good health. The patient's temperature is 36.7 C (98 F), blood pressure is 130/90 mm Hg, pulse is 62/min, and respirations are 14/min. Palpation of the abdomen shows tenderness in the right upper quadrant. Murphy's sign is present. Abdominal ultrasound reveals several gallstones and biliary sludge. The patient undergoes an uncomplicated laparoscopic cholecystectomy and is discharged the following day. On a follow-up visit 2 months later, she complains of daily diarrhea (4-5 watery bowel movements per day). She has tried dietary changes with no improvement. What is the most appropriate next step in management of this patient?
(Multiple Choice)
4.7/5 (66)
(66) A 67-year-old woman comes to the emergency department due to sudden-onset, severe low back pain that began when she was lifting her grandson. The pain does not radiate to the lower extremities; she has had no weakness or sensory loss in her legs or urinary incontinence. The patient has had back pain in the past but not of this severity. She has a history of hypertension, hyperlipidemia, and hypothyroidism, for which she takes lisinopril, atorvastatin, and levothyroxine. The patient was also found to have low bone mineral density during a screening test 2 years ago. She has been feeling more tired lately and has not been able to exercise as recommended but does take daily calcium and vitamin D supplements and weekly alendronate as prescribed. She also has not consumed dairy products regularly as in the past due to her poor appetite; she has lost about 4.5 kg (10 lb) over the past several months. The patient is a lifelong nonsmoker and drinks alcohol occasionally. Blood pressure is 148/86 mm Hg and pulse is 96/min. BMI is 21 kg/m2. Physical examination shows tenderness to percussion over the lower thoracic spine. Bilateral lower extremity muscle strength, sensation, and deep tendon reflexes are normal. Laboratory results are as follows: 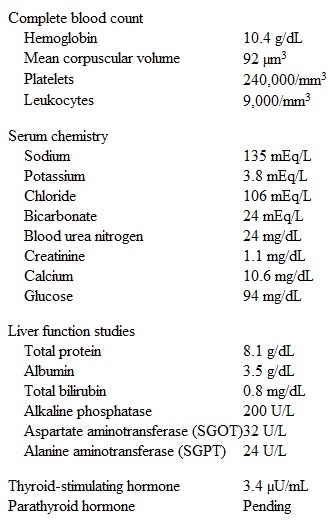 Spine radiography shows a T12 vertebral compression fracture. In addition to analgesics, which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.9/5 (79)
(79) A 69-year-old man comes to the office due to a skin lesion near the medial left eye. The lesion does not itch or hurt. There have been no visual changes or eye discharge. Medical history is notable for hypothyroidism treated with levothyroxine. Examination of the lesion is shown in the exhibit. 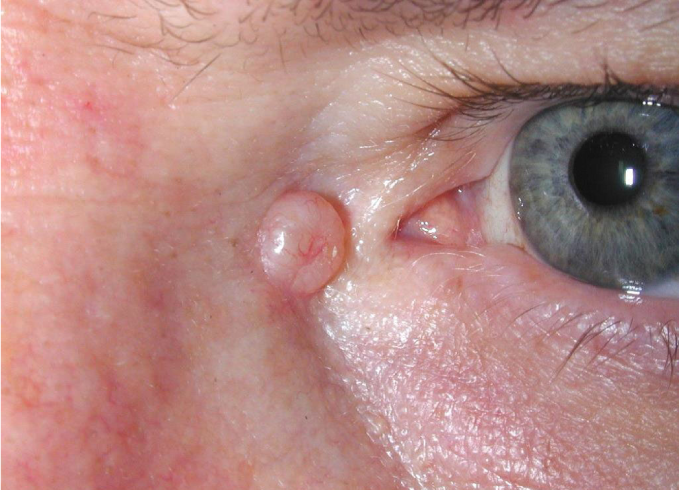 Extraocular movements are intact. Visual acuity is 20/20 bilaterally. Conjunctivae are clear. If left untreated, what is the most likely prognosis of this lesion?
 (Multiple Choice)
4.9/5 (88)
(88) A previously healthy 20-year-old man is brought to the emergency department for fever, dysphagia, drooling, and poor coordination. The symptoms started last week with mild fever, throat pain, and malaise. He was able to eat some food but is afraid to drink any fluids as he feels his "throat closing up." The patient, an anthropology student, went on a school trip 2 months ago during which he explored several caves. He took several over-the-counter analgesic medications without relief. He does not recall any bites, scratches, or animal exposures. The patient has received all standard immunizations and takes no medications. He is febrile and tachycardic. Examination shows dehydration, lethargy, and ataxia. Drool is pooling in his mouth. No pharyngeal erythema or exudates are seen.
Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (62)
(62) A 31-year-old woman, gravida 1 para 0, at 28 weeks gestation comes to the office for a routine prenatal visit. The patient has had good fetal movement. She has no abdominal pain or vaginal bleeding but reports a thin, malodorous vaginal discharge that is increasing and now requires her to use a panty liner. The patient's pregnancy has been complicated by gestational diabetes mellitus diagnosed at 26 weeks gestation. Due to uncontrolled glucose levels last week, an oral antihyperglycemic medication was prescribed; glucose level today shows improvement. The patient has no other chronic medical conditions. She exercises 3 days a week in a water aerobics class. The patient does not use tobacco, alcohol, or illicit drugs. She has no drug allergies. Temperature is 37.1 C (98.8 F), blood pressure is 120/76 mm Hg, and pulse is 74/min. Fundal height is 28 cm. Fetal heart rate is 150/min by Doppler ultrasonography. Pelvic examination reveals a nontender, closed cervix without cervical discharge and a nontender gravid uterus. A thin, gray vaginal discharge is present, but no vesicles, ulcers, or other lesions are seen. There is no leakage of fluid through the cervix during the Valsalva maneuver. Microscopy of the vaginal fluid shows epithelial cells that have a stippled appearance but no ferning. Urine dipstick test is negative for protein and glucose. The appropriate action is taken. The patient asks for the rationale of the management plan. Which of the following is the most appropriate response?
(Multiple Choice)
4.9/5 (59)
(59) An 83-year-old woman with mild cognitive impairment comes to the office due to a feeling of "not being myself." The patient has lived in an assisted living facility since her husband died 2 years ago. She is accompanied by a caregiver, who notes that the patient has developed progressive changes in behavior and personality over the last several months. The patient has often refused meals and snacks and has had decreased participation in group activities that she previously enjoyed. She also gets agitated very easily and often "wants to be left alone." Medical history is notable for hypertension, heart failure with preserved ejection fraction, and osteoporosis. The patient was also diagnosed with atrial fibrillation 6 months ago, and apixaban and escalating doses of metoprolol succinate were prescribed. She has never used tobacco, alcohol, or illicit drugs. Temperature is 37.4 C (99.3 F), blood pressure is 150/60 mm Hg, pulse is 92/min, and respirations are 22/min. Oxygen saturation is 97% on room air. Weight is 68.7 kg (151.5 lb); a month ago, it was 72.3 kg (159.4 lb). Ocular examination is normal. There is no nuchal rigidity or thyroid enlargement. The heart has an irregularly irregular rhythm, and the chest is clear to auscultation. No focal neurologic deficits are present and the patient's gait appears stable. Laboratory tests show normal complete blood count, serum chemistry panel, and urinalysis. ECG shows atrial fibrillation with nonspecific T-wave abnormalities. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (79)
(79) A 26-year-old student comes to the emergency department 10 hours after his right arm was scratched by a bat. He says, "I frequently explore caves, and bats do not always seem to like me." He had a similar scratch 1 year ago and completed his anti-rabies vaccination series. All his vaccinations are up-to-date. His past medical history is otherwise insignificant. He does not use tobacco, alcohol, or illicit drugs. He is currently not taking any medications and has no known allergies. What is the best management strategy for this patient?
(Multiple Choice)
4.9/5 (92)
(92) A 24-year-old man is carried into the emergency department by friends after a fight in the street. During the fight, the patient was struck in the head with a knife, which became firmly implanted in his skull. His blood pressure is 106/72 mm Hg, pulse is 118/min, and respirations are 14/min. Pulse oximetry shows 93% on room air. His Glasgow Coma Scale score is 8. He opens his eyes to pain, and his speech is incomprehensible. Compressing the fingernail bed causes him to withdraw his hand. The estimated length of the knife is 14 cm, 3 cm of which have penetrated his skull. There is no other evidence of injury on his body. Which of the following is the most important next step in management of this patient?
(Multiple Choice)
4.8/5 (76)
(76) An open-label randomized trial is conducted to compare a new nonsteroidal anti-inflammatory agent (AG) and low-dose colchicine for the treatment of gout flares in primary care. A total of 400 adults with gout flares were randomized 1:1 to AG for 7 days or low-dose colchicine three times per day for 4 days. The primary outcome was change in pain intensity from baseline measured over the first 7 days. At Day 7 follow-up, about 25% of participants in the low-dose colchicine group had switched treatment to AG, and about 15% of participants in the low-dose colchicine group had stopped treatment altogether. The primary investigator decided to preserve the original randomization for the data analysis. Which of the following describes the data analysis approach adopted by the primary investigator?
(Multiple Choice)
4.7/5 (96)
(96) A 74-year-old woman is brought to the emergency department from a skilled nursing facility due to a positive stool PCR test for Clostridioides difficile. The patient was discharged from the hospital to the nursing facility 10 days ago after treatment for urinary tract infection and septic shock. She developed C difficile-associated diarrhea during the hospitalization and completed a course of oral fidaxomicin therapy 3 days ago. This treatment resolved the diarrhea, nausea, and abdominal pain; yesterday, the patient had an episode of bloating, nausea, and loose stool after a meal at the nursing facility, prompting repeat stool testing. Since then, she has had no additional abdominal pain, nausea, vomiting, or diarrhea. Other medical conditions include hypertension, hyperlipidemia, ischemic stroke with residual left hemiparesis, and gastroesophageal reflux. Temperature is 37 C (98.6 F), blood pressure is 130/68 mm Hg, and pulse is 84/min. The abdomen is soft, nondistended, and nontender, with normoactive bowel sounds in all quadrants. Rectal examination shows soft, brown stool negative for occult blood. Leukocyte count is 7,100/mm3.
Which of the following is the most appropriate course of action in management of this patient's symptoms?
(Multiple Choice)
4.8/5 (71)
(71) A 67-year-old woman comes to the office due to 4 weeks of upper abdominal pain. She also has epigastric fullness and mild nausea that occur mostly after eating and sometimes at night. The patient has had no vomiting, weight loss, dysphagia, acid reflux, or black or bloody stools. Medical history includes hypertension, hyperlipidemia, migraines, and mild intermittent asthma. Medications include lisinopril and atorvastatin. The patient's father died of colon cancer at age 75. On physical examination, the abdomen is soft and nontender. There is no jaundice or palpable masses. Hemoglobin is 13.2 g/dL. Colonoscopy 3 years ago was normal. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.7/5 (75)
(75) A 53-year-old woman of white ethnicity comes to the office to discuss the results of her bone density test. She feels well but is very concerned about osteoporotic fractures as her mother passed away at age 81 after sustaining a hip fracture. The patient had menopause at age 50 and currently has no hot flashes or vaginal dryness. She eats a healthy diet and exercises at least 5 days a week with a combination of strength training and aerobic conditioning exercises. Medical history is unremarkable and her only medication is a daily over-the-counter vitamin D3 supplement (800 IU). She has never been married and has no history of pregnancy. The patient drinks a glass of wine every night and does not use tobacco or illicit drugs. In addition to osteoporosis, family history is positive for breast cancer in a maternal aunt. Vital signs are normal. BMI is 25 kg/m2. Physical examination is unremarkable. Fasting laboratory and bone mineral density results are as follows:  The 10-year probability of fracture calculated using the fracture assessment tool (FRAX) is 12% and 0.6% for a major osteoporotic fracture and a hip fracture, respectively. Mammogram a year ago was normal. Which of the following is the most appropriate next step in management of this patient's low bone density?
 (Multiple Choice)
4.8/5 (65)
(65) A 24-year-old primigravid woman at 35 weeks gestation comes to the office for a routine prenatal visit. The patient reports no leakage of fluid or vaginal bleeding but has noticed occasional painless uterine contractions over the past week. Fetal movement is normal. Her pregnancy has been uncomplicated. The patient has no chronic medical conditions and has had no surgeries. She takes a daily prenatal vitamin and has not used tobacco, alcohol, or illicit drugs during the pregnancy. The patient takes a prenatal yoga class 3 times a week. Blood pressure is 130/80 mm Hg and pulse is 68/min. BMI is 28 kg/m2. The fetal heart rate is 142/min by Doppler ultrasound. Fundal height is 32 cm. Pelvic examination shows the cervix to be closed and long with the fetal presenting part at 0 station. Ultrasound reveals a fetus in footling breech presentation with an estimated fetal weight at the 25th percentile for gestational age, a fundal placenta, and a normal amniotic fluid level. The diagnosis of breech presentation is reviewed with the patient, who responds by saying "I am really hoping for a vaginal delivery." Which of the following is the most appropriate response to this patient?
(Multiple Choice)
4.8/5 (96)
(96) A 48-year-old man comes to the emergency department with several days of headache, photophobia, nausea, and vomiting. He has also had decreased hearing in the left ear and occasional vision floaters for the past week. The patient has no earache, tinnitus, or vertigo. He was treated for gonorrhea 6 months ago with a single antibiotic injection. He uses intravenous drugs and reports having unprotected sex with multiple partners. The patient does not use tobacco or alcohol and has not traveled recently. His temperature is 37.2 C (99 F), blood pressure is 122/68 mm Hg, and pulse is 92/min. He has bilateral eye irritation and a generalized maculopapular rash, as shown in the exhibit. 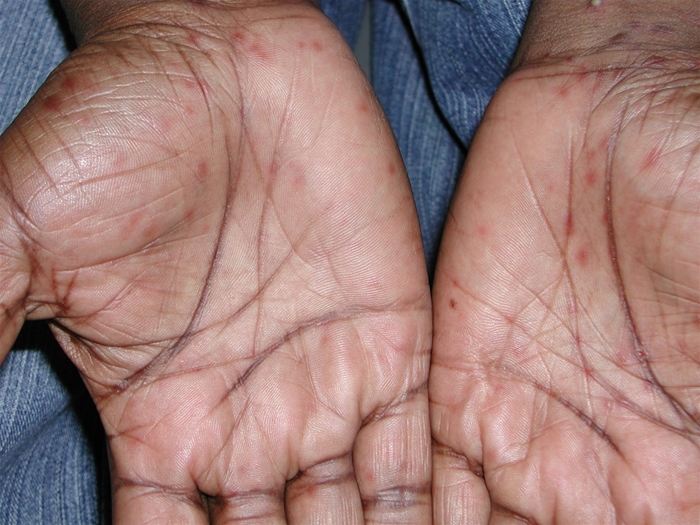 Multiple, nontender cervical and inguinal lymph nodes are palpable. There is sensorineural hearing loss in the left ear and neck stiffness. Cardiopulmonary examination is normal. The abdomen is soft and nontender. The motor examination is symmetric, and reflexes are 2+ bilaterally throughout the upper and lower extremities. Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (68)
(68) A 65-year-old man is brought to the emergency department by his wife due to severe upper-abdominal pain. The pain began suddenly 4 hours ago while he was watching television; it radiates to the back and is exacerbated by any movement. The patient has had gastroesophageal reflux disease for many years and has been taking over-the-counter antacids for symptom control. He also has hypertension, which is controlled with a thiazide diuretic. He walks 5 miles daily. The patient has been consuming large amounts of milk and other dairy products to relieve "burning" symptoms in his stomach. His temperature is 37.8 C (100 F), blood pressure is 110/62 mm Hg, pulse is 110/min, and respirations are 22/min. He lies flat and motionless on the bed. His mucous membranes are dry. Abdominal examination shows marked tenderness on superficial palpation. The patient does not allow any further palpation of the abdomen. Electrocardiogram shows sinus tachycardia. The patient was managed operatively, and he recovers well. Three years later, he comes to the emergency department with a 1-day history of nausea, vomiting, upper-abdominal pain, and distension. An abdominal radiograph reveals the presence of multiple air-fluid levels in the small intestine consistent with intestinal obstruction. Which of the following is the most likely mechanism of his intestinal obstruction?
(Multiple Choice)
4.9/5 (78)
(78) A 32-year-old woman comes to the emergency department due to 7 days of fever and dry cough. She has also had progressive shortness of breath with minimal walking and climbing stairs. The patient was diagnosed with HIV infection a year ago and is not currently on antiretroviral treatment. She does not use tobacco, alcohol, or illicit drugs. Temperature is 38.4 C (101.1 F), blood pressure is 110/64 mm Hg, pulse is 106/min, and respiratory rate is 26/min. Pulse oxymetry is 87% on room air and decreases to 82% with minimal walking. Oropharyngeal thrush is present. Lung auscultation reveals scattered bilateral crackles and rhonchi. The abdomen is soft and nontender without organomegaly. No cyanosis, clubbing, or edema is present. Chest x-ray reveals diffuse interstitial opacities bilaterally. CD4 count is 85/mm3. The patient is admitted and started on empiric therapy. Twenty-four hours after admission, the induced sputum analysis is negative for Pneumocystis.
Which of the following is the likely cause of this patient's pneumonia?
(Multiple Choice)
4.8/5 (89)
(89) A 56-year-old Caucasian male presents to your office for a routine check-up. He complains of chronic cough, fatigue, and occasional headaches. He has longstanding hypertension, which is controlled with amlodipine and lisinopril. Three months ago, he was diagnosed with acute bronchitis and treated with a short course of antibiotics. He smokes one pack of cigarettes daily and consumes alcohol occasionally. He denies any recreational drug use. His family history is significant for prostate cancer in his father and renal cell carcinoma in his uncle. His blood pressure is 147/82 mmHg, pulse is 93/min, temperature is 36.7 C (98 F), and respirations are 14/min. His oxygen saturation is 94% on room air. His BMI is 42 kg/m2. Physical examination is unremarkable. His chest X-ray is normal. 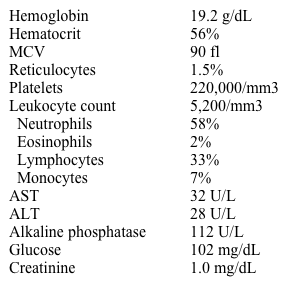 Item 1 of 2
Which of the following is the best next step in managing this patient?
Item 1 of 2
Which of the following is the best next step in managing this patient? (Multiple Choice)
4.8/5 (80)
(80) A 42-year-old Caucasian woman comes to the emergency department because of right-sided neck pain, persistent cough, and dyspnea for the past three days. Her past medical problems include hypertension and obesity. She takes enalapril and hydrochlorothiazide. She has smoked one pack of cigarettes daily for the past 25 years. She does not drink alcohol. She works as an executive secretary. Her temperature is 37.8C (100 F), blood pressure is 130/80 mm Hg, pulse is 92/min and respirations are 18/min. Examination shows decreased breath sounds in the upper part of the right lung. There is moderate swelling and erythema of the neck, moderate right jugular vein dilatation, and increased venous marks in the right arm. Her serum creatinine level is 0.8 mg/dL. A chest x-ray reveals a right-sided opacity. Which of the following is the most appropriate immediate step in the management of this patient?
(Multiple Choice)
4.9/5 (62)
(62) A 62-year-old Hispanic woman comes to the office with complaints of a sense of heaviness and discomfort in her right groin. Her discomfort is worse with standing and coughing, and is relieved by lying flat. She also noticed a painful bulging mass at the same site two days ago, which resolved spontaneously after two hours. She has a past medical history of breast cancer and chronic bronchitis. She had a left mastectomy at age 48 and two cesarean sections at 28 and 33 years of age. She smokes a pack of cigarettes daily. On examination and Valsalva maneuver, you find a right-sided femoral hernia that is easily reducible. There is no evidence of incarceration or strangulation. Which of the following is the most appropriate next step?
(Multiple Choice)
4.8/5 (89)
(89) Showing 461 - 480 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)