



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


A 30-year-old Caucasian female presents to your office for a routine check-up. Her past medical history is insignificant. She does not smoke, and consumes 1-2 bottles of beer on weekends. She is sexually active with her boyfriend and takes oral contraceptives. She also takes one multivitamin tablet daily. The physical examination reveals several 3-4 mm warty projections on the posterior wall of her vagina that turn white on acetic acid application. The patient denies ever having any sexually transmitted disease, but she describes having scant vaginal discharge, which she did not pay much attention to. She wants to know what the most probable cause of her problem is.
Which of the following is the best response to this patient's concern?
(Multiple Choice)
5.0/5  (87)
(87) A 25-year-old woman comes to the office due to 4 days of burning with urination, increased urinary frequency, and blood in her urine. The patient has not had fevers, chills, or abnormal vaginal discharge. She has tried to treat her symptoms with cranberry juice and increased fluid intake but has had no improvement. The patient has been in a monogamous relationship for the last 8 months. She and her partner have intercourse 3 or 4 times a week; they use a progestin subdermal implant and condoms with spermicide for contraception. The patient voids immediately after intercourse but has had 3 urinary tract infections in the last 7 months. She has no chronic medical conditions but had a laparoscopic ovarian cystectomy for a mature teratoma at age 20. The patient takes a multivitamin daily. She drinks wine on special occasions but does not use tobacco or illicit drugs. Temperature is 36.7 C (98 F), blood pressure is 110/60 mm Hg, and pulse is 58/min. BMI is 22 kg/m2. Abdominal examination shows suprapubic tenderness but no costovertebral angle tenderness. Pelvic examination reveals a small, nontender uterus with no adnexal masses. Speculum examination reveals a normal cervix with no abnormal discharge. Urinalysis results are as follows:  A 1-week course of antibiotics is prescribed. In addition to the course of antibiotics, which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (85)
(85) A 46-year-old man is brought to the emergency department by the police after being found unresponsive on a nearby park bench. Previously, the patient was brought to the hospital on several occasions due to acute alcohol intoxication. No other history can be obtained. The patient appears disheveled and has a strong smell of alcohol. Temperature is 36.1 C (97 F), blood pressure is 110/76 mm Hg, and pulse is 84/min. Pulse oximetry shows 98% on ambient air. The patient does not follow instructions and withdraws all extremities to painful stimuli. The mucous membranes are dry, and he has several spider angiomata and bilateral gynecomastia. The lungs are clear to auscultation and heart sounds are normal with no murmur. There is moderate abdominal distension with shifting dullness. The liver edge cannot be palpated. While being evaluated in the emergency department, the patient vomits a large amount of bright red blood. Repeat vital signs show that blood pressure is 100/50 mm Hg and pulse is 110/min. Two large-bore peripheral lines are placed and intravenous fluid is administered. The initial appropriate steps are taken for this patient, and an upper gastrointestinal endoscopy is planned. Laboratory results are as follows:
 Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
5.0/5 (72)
(72) A 45-year-old man comes to the clinic for follow-up 8 weeks after an episode of acute pancreatitis due to alcohol abuse. The patient initially presented with abdominal pain radiating to his back, nausea, and vomiting. His condition improved with supportive care, and the hospital course was uncomplicated. Since discharge, he reports occasional mild abdominal discomfort but otherwise feels well. His abdominal discomfort is not associated with food. He has no vomiting, diarrhea, or early satiety. The patient has stopped drinking since his last admission, but continues to smoke a pack of cigarettes a day and has done so for the last 30 years. Temperature is 36.7 C (98.2 F), blood pressure is 125/70 mm Hg, pulse is 72/min, and respirations are 16/min. On physical examination, oropharynx is without lesions, lungs are clear, and there are normal S1 and S2 without murmurs. Abdominal examination reveals fullness and mild tenderness over the epigastric area. Bowel sounds are present. There is no hepatomegaly, splenomegaly, guarding, or rebound tenderness. The remainder of the examination is normal. Laboratory results are as follows:  Which of the following is the most likely cause of this patient's persistent abdominal pain?
 (Multiple Choice)
4.7/5 (93)
(93) A 62-year-old woman comes to the office due to episodic tightness over her anterior chest for the past 6 months. It sometimes occurs while the patient is walking or climbing stairs, but several episodes have occurred while sitting at her desk at work, which she attributes to stress. The discomfort usually lasts 5-10 minutes and feels like muscle cramps. She has had no shortness of breath, palpitations, lightheadedness, syncope, or lower-extremity swelling. The patient has a history of diet-controlled diabetes mellitus diagnosed 20 years ago and anxiety disorder. She takes low-dose aspirin, lisinopril, and atorvastatin. She is a lifetime nonsmoker and drinks 1 or 2 glasses of wine during social gatherings. The patient has no known drug allergies. Her father was diagnosed with a myocardial infarction at age 60, and her mother died from a hemorrhagic stroke. Blood pressure is 125/80 mm Hg and pulse is 72/min. BMI is 29 kg/m2. Physical examination shows no abnormalities. ECG shows normal sinus rhythm with no abnormal repolarization changes. Serum creatinine is 1.1 mg/dL and hemoglobin A1c is 6.5%. Lipid panel shows LDL of 134 mg/dL and HDL of 45 mg/dL. The patient undergoes exercise stress testing. She exercises for 8 minutes without chest discomfort, and exercise ECG shows no abnormal ST-segment changes. Which of the following should be communicated to the patient regarding her stress testing results?
(Multiple Choice)
5.0/5 (76)
(76) A 55-year-old man comes to the emergency department due to sudden onset of retrosternal chest pain. The pain began 10 hours ago and has been mostly constant, although he describes it as "being bad and then getting a little better." The patient has had no lightheadedness, syncope, or shortness of breath. ECG shows normal sinus rhythm with 2-mm ST-segment elevation in leads V2 to V5. He is taken emergently for cardiac catheterization and undergoes percutaneous coronary intervention with stent placement to the left anterior descending artery. After the procedure, the ST-segment changes improve and he has complete resolution of the chest pain. On the third night, just prior to discharge, he calls for the nurse due to the sudden onset of sharp, retrosternal chest pain. The patient first noticed the pain while turning around in bed; it worsens with deep breathing. Temperature is 37.8 C (100 F), blood pressure is 134/80 mm Hg, heart rate is 108/min, and respirations are 22/min. Physical examination reveals regular heart sounds and clear lung fields. There is a scratchy sound heard during ventricular systole along the left sternal border. Abdominal palpation reveals no localized tenderness. ECG shows sinus tachycardia with Q waves and T-wave inversion in leads V2 to V5. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (79)
(79) A 61-year-old man comes to the office for follow-up after a screening colonoscopy. During the procedure, a 1-cm pedunculated polyp in the sigmoid colon and 2 small pedunculated polyps in the descending colon were removed. Histopathologic evaluation of the sigmoid lesion revealed an adenomatous polyp with an area of well-differentiated adenocarcinoma invading the muscularis mucosa in the head of the polyp. The stalk and the polyp margins are free of cancerous tissue. No lymphatic or vascular involvement is seen in the tissue sample. The two descending colon polyps are hyperplastic. The patient previously had a normal screening colonoscopy at age 50 and has no family history of colon cancer. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (77)
(77) A 21-year-old woman comes to the office due to poor sleep and depression. She has been feeling progressively depressed and unmotivated over the past month, and also describes decreased appetite, a 2.2-kg (5-lb) weight loss, poor concentration, and low energy. The patient has no suicidal ideation or manic or psychotic symptoms. She drinks 1 or 2 beers twice a week but does not use illicit drugs. She has never felt like this before and is worried as her symptoms have worsened to the point that she has trouble getting out of bed and attending college. Major depressive disorder is diagnosed, and the patient is started on citalopram 20 mg. One month later, she returns for a follow-up visit. She now reports feeling much better, has improved energy and sleep, and has returned to school. The patient has no side effects from the medication and wonders how long she should continue it. Which of the following is the most appropriate recommendation?
(Multiple Choice)
4.8/5 (83)
(83) A 21-year-old woman comes to the office due to weakness and fever for 9 days. She has also developed headaches, myalgia, and a sore throat. The patient's symptoms have worsened since their onset, causing her to be unable to go to work. Despite remaining in bed for most of the day, she feels "exhausted." She has lost 2 kg (4.4 lb) over the past week. The patient has no significant medical history and takes no medications. She drinks alcohol occasionally and has smoked a pack of cigarettes a day for the past 7 years. She is sexually active and uses condoms "most of the time." Temperature is 38.3 C (100.9 F), blood pressure is 120/70 mm Hg, pulse is 82/min, and respirations are 16/min. Physical examination shows an awake but tired woman. There is no rhinorrhea or erythema of tympanic membranes; she has enlarged tonsils with white exudates. Large cervical and axillary lymph nodes are palpable bilaterally. S1 and S2 are normal without murmurs. Lungs are clear to auscultation bilaterally. The abdomen is soft and nontender with normal bowel sounds; the liver edge extends 2 cm below the right costal margin and there is palpable splenomegaly. There are no rashes or lesions.
What is the most appropriate next step in this patient's workup?
(Multiple Choice)
4.8/5 (74)
(74) A 55-year-old man comes to the emergency department due to sudden onset of retrosternal chest pain. The pain began 10 hours ago and has been mostly constant, although he describes it as "being bad and then getting a little better." The patient has had no lightheadedness, syncope, or shortness of breath. ECG shows normal sinus rhythm with 2-mm ST-segment elevation in leads V2 to V5. He is taken emergently for cardiac catheterization and undergoes percutaneous coronary intervention with stent placement to the left anterior descending artery. After the procedure, the ST-segment changes improve and he has complete resolution of the chest pain. On the third night, just prior to discharge, he calls for the nurse due to the sudden onset of sharp, retrosternal chest pain. The patient first noticed the pain while turning around in bed; it worsens with deep breathing. Temperature is 37.8 C (100 F), blood pressure is 134/80 mm Hg, heart rate is 108/min, and respirations are 22/min. Physical examination reveals regular heart sounds and clear lung fields. There is a scratchy sound heard during ventricular systole along the left sternal border. Abdominal palpation reveals no localized tenderness. ECG shows sinus tachycardia with Q waves and T-wave inversion in leads V2 to V5.
Which of the following is the most likely cause of this patient's recurrent symptoms?
(Multiple Choice)
4.8/5 (69)
(69) A 36-year-old woman comes to the physician for a rash on her lower abdomen. The rash first appeared 3 months ago and has been slowly expanding in the same area. It is mildly pruritic but otherwise asymptomatic. Treatment with topical emollients has not been beneficial. The patient has a history of depression for which she takes citalopram but is otherwise healthy. Skin examination findings are shown in the image below.  Which of the following is the most likely explanation for this patient's symptoms?
 (Multiple Choice)
4.8/5 (72)
(72) A 21-year-old woman comes to the office due to weakness and fever for 9 days. She has also developed headaches, myalgia, and a sore throat. The patient's symptoms have worsened since their onset, causing her to be unable to go to work. Despite remaining in bed for most of the day, she feels "exhausted." She has lost 2 kg (4.4 lb) over the past week. The patient has no significant medical history and takes no medications. She drinks alcohol occasionally and has smoked a pack of cigarettes a day for the past 7 years. She is sexually active and uses condoms "most of the time." Temperature is 38.3 C (100.9 F), blood pressure is 120/70 mm Hg, pulse is 82/min, and respirations are 16/min. Physical examination shows an awake but tired woman. There is no rhinorrhea or erythema of tympanic membranes; she has enlarged tonsils with white exudates. Large cervical and axillary lymph nodes are palpable bilaterally. S1 and S2 are normal without murmurs. Lungs are clear to auscultation bilaterally. The abdomen is soft and nontender with normal bowel sounds; the liver edge extends 2 cm below the right costal margin and there is palpable splenomegaly. There are no rashes or lesions. The appropriate workup is completed and the correct diagnosis is made. Which of the following is the most appropriate management?
(Multiple Choice)
4.8/5 (71)
(71) A healthy 12-month-old boy is brought to the physician for a routine examination. He started walking last week and can say "mama," "dada," "night-night," and "go." He eats a well-rounded diet and drinks whole milk twice a day. The patient lives with his mother, who is 17 weeks pregnant. His growth parameters and physical examination are normal. He is scheduled to receive measles-mumps-rubella, varicella, inactivated poliovirus, and pneumococcal conjugate vaccinations today. Which of the following is the best next step in management of this patient?
(Multiple Choice)
5.0/5 (72)
(72) A 66-year-old man comes to the emergency department with progressive lower back pain, urinary incontinence, and decreased appetite for the past 2 days. He was recently diagnosed with L4-L5 disc herniation and received an epidural injection for radicular pain 2 weeks ago. His other medical problems include type 2 diabetes mellitus and hypertension. Temperature is 38.3 C (100.9 F), blood pressure is 136/88 mm Hg, pulse is 96/min, and respirations are 14/min. The patient is alert and oriented. Physical examination shows poor dentition, tenderness on palpation of the lumbar spine, and absent deep-tendon reflexes in both lower extremities. Rectal examination shows decreased rectal sphincter tone and an enlarged, smooth prostate. Laboratory results are as follows:  Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.9/5 (72)
(72) An 80-year-old Caucasian female is being discharged from the hospital after surgical repair of the right hip fracture. She fractured her right hip after falling down the steps in her home. She has a past history of osteoporosis, hypertension controlled with thiazide diuretics and metoprolol, diabetes mellitus treated with metformin, and hypercholesterolemia controlled with simvastatin. She suffered from an acute myocardial infarction six years ago, but she has not had any complications or recurrence of symptoms. She has a 50-year-old daughter who lives near her house. You advise the patient to consider an alternate living arrangement; however, she clearly expresses her desire to live by herself in her own home. She does not want to live in her daughter's house or in a nursing home. Which of the following is the most appropriate next step?
(Multiple Choice)
4.9/5 (64)
(64) A 42-year-old woman, gravida 6 para 6, is evaluated in the postpartum unit on postoperative day 2 after a cesarean delivery. The patient has had increasing vaginal bleeding, abdominal pain, and fever. She is breastfeeding exclusively with a good latch. The patient was initially admitted to the hospital for prelabor rupture of membranes at 40 weeks gestation. A primary cesarean delivery was performed for arrest of descent of a 5-kg (11-lb) infant after 3 hours of pushing. The pregnancy was complicated by recurrent vaginal candidiasis. Prior pregnancies were uncomplicated; the patient's last delivery was 12 years ago. Temperature is 38.7 C (101.7 F), blood pressure is 110/70 mm Hg, pulse is 114/min, and respirations are 18/min. On physical examination, the patient appears pale and tired. The lungs are clear to auscultation bilaterally; the breasts are full but without erythema. The uterine fundus is tender to palpation. Speculum examination shows heavy lochia but no active bleeding. The transverse incision across the lower abdomen is intact and without erythema or drainage.
Which of the following is this patient's most important risk factor for her current postpartum infection?
(Multiple Choice)
4.8/5 (86)
(86) A 45-year-old woman comes to the office due to progressive stiffness, pain, and swelling of the joints in the hands and wrists for the past 3 months. The symptoms are worse when she wakes up and gradually improve after several hours. The patient also feels fatigued but has had no skin rashes, oral lesions, or fever. She recently began taking chlorthalidone for hypertension and takes no other medications. She works in a daycare center. The patient drinks alcohol occasionally and does not use tobacco or illicit drugs. Her mother had "arthritis" in her older age, and her sister has systemic lupus erythematosus. Temperature and other vital signs are within normal limits. Physical examination shows warmth, swelling, and tenderness of the second and third proximal interphalangeal joints, the metacarpophalangeal joints, and the wrists of both hands. The remainder of the examination shows no abnormalities. Additional laboratory results show normal hepatic aminotransferase levels. The patient is advised to avoid alcohol consumption. She receives appropriate immunizations, and methotrexate therapy is begun. Which of the following additional interventions is the most appropriate in this patient?
(Multiple Choice)
4.9/5 (83)
(83) A 74-year-old man with a history of hypertension comes to the clinic asking advice about his recent memory problems. He is accompanied by his wife. The patient says, "I have always been very sharp but over the last year I have had difficulty remembering things. I missed a number of appointments and sometimes I feel embarrassed because I forget names of the people I meet." His wife says he has been moody and irritable and that he complains of headaches; "He doesn't sleep well at nights and we rarely have sex now. I don't know if it's old age or what." The patient reports no nausea, vomiting, falls, weakness, weight loss, fevers, chills, vision changes, or incontinence. Other issues include obesity, diet-controlled type 2 diabetes mellitus, and coronary artery disease. Current medications include lisinopril, atorvastatin, aspirin, and carvedilol. He does not use alcohol, tobacco, or recreational drugs. Family history is unremarkable. Temperature is 36.7 C (98 F), blood pressure is 155/95 mm Hg, pulse is 62/min, and respirations are 14/min. BMI is 34 kg/m2 and neck circumference is 45.7 cm (18 in). Examination shows normal jugular venous pressure and no lymphadenopathy. Lung fields are clear, and S1 and S2 are normal. The abdomen is soft and nontender. Examination shows no edema. Mental status examination shows poor concentration and 3-object recall, while other aspects are normal. Cranial nerves are within normal limits. Muscle strength is 5/5 in both upper and lower extremities, and upper and lower limb deep tendon reflexes are 2+. Gait is normal. The patient's complete blood count and metabolic panel are normal. Other laboratory results are as follows: 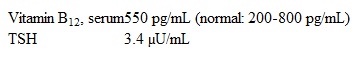 Which of the following is the best response to this patient's concerns?
 (Multiple Choice)
4.9/5 (79)
(79) A 25-year-old woman, gravida 1 para 1, comes to the office for evaluation of fever and right breast pain. The patient is 2 weeks postpartum after an uncomplicated pregnancy and vaginal delivery. She has been breastfeeding every 2-3 hours; however, the infant has had difficulty with latching due to the mother's inverted nipples. Yesterday, the patient developed constant sharp pain in the side of her right breast as well as fever, chills, nausea, and body aches. The pain is worsening, especially during breastfeeding. She has been taking acetaminophen and ibuprofen with minimal relief. The patient has no chronic medical conditions. She is on maternity leave from her engineering job. The patient has no drug allergies and is taking a daily prenatal vitamin. Temperature is 38.9 C (102 F), blood pressure is 110/70 mm Hg, and pulse is 100/min. Examination reveals the upper outer quadrant of the right breast to be erythematous, tender, and swollen but without fluctuance. The left breast has no erythema or tenderness.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (85)
(85) A 9-month-old boy is brought to the emergency department by his parents as he is not "acting like himself." The parents report that he has always been a fussy baby and often awakens multiple times a night. However, yesterday he cried the entire night and seemed more tired than usual this morning. The infant typically eats yogurt and formula for breakfast but refused to eat this morning and vomited 3 times. His mother says, "He may have hit his head on the floor after climbing onto and then rolling off the couch 2 days ago. He recently started crawling and often bumps into furniture around the house." The infant was born at term via an uncomplicated vaginal delivery. He was evaluated several times in the emergency department between ages 3 and 5 months for fussiness and was diagnosed with colic. His mother is currently taking antibiotics for bacterial pharyngitis; otherwise, there are no sick contacts or contributory family history. Temperature is 37 C (98.6 F) and pulse is 125/min. Height and weight are at the 75th and 50th percentiles, respectively. On examination, the infant is lethargic. The lungs are clear to auscultation and there are no murmurs. The abdomen is soft and nondistended. A small bruise is present on the buttocks; there are no additional rashes, lesions, or bruises. The infant's airway is secured, and his condition is stabilized. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (65)
(65) Showing 441 - 460 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)