



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


A 66-year-old woman comes to the office to have a lipoma removed from her elbow. The lipoma does not cause her pain, but she does not like the way it looks when she wears sleeveless dresses. Her other medical problems include hypertension and gastroesophageal reflux. Review of systems is positive for 8 months of general malaise and fatigue, which the patient attributes to having started a more difficult Pilates routine. Temperature is 37.2 C (98.6 F), blood pressure is 108/72 mm Hg, and pulse is 66/min. Physical examination shows mild pallor and mobile, firm lymphadenopathy in her cervical and supraclavicular chains. The jugular veins are not distended. Cardiopulmonary and abdominal examinations are normal. Her preoperative blood count is as follows: 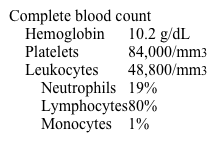 Flow cytometry confirms the diagnosis. Which of the following is correct about this patient?
 (Multiple Choice)
4.9/5  (75)
(75) A 24-year-old man is brought to the emergency department by his friend due to disorientation and restlessness. His friend says, "He's gone crazy. I had a tough time bringing him in. He kept moving from side to side in the car, banging his body against the door. Then he started pushing me while I was driving. I almost ran off the road." The patient is well known from past emergency department admissions for similar behavior of agitation; he often becomes coherent in 7-8 hours. He is homeless and has a history of using multiple illicit substances. He was also hospitalized a month ago for opioid overdose with subsequent aspiration pneumonia. The patient has no other active medical illnesses except for injuries due to trauma while intoxicated. He does not have any other psychiatric disorders. Temperature is 37.2 C (99 F), blood pressure is 160/100 mm Hg, and heart rate is 120/min. He is not oriented to time and place but recalls his name and date of birth. Examination shows prominent nystagmus as well as multiple cuts and abrasions of the shoulders and extremities. The patient is restless and paces in his room. He then stops, sits down, stands up again, bangs his body against the wall, and yells, "They're pushing a rock on me." Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (74)
(74) A 45-year-old man is brought to the emergency department by his wife due to progressive lethargy, confusion, and abdominal pain. He has had no hematemesis, melena, or hematochezia. The patient has a history of alcoholic cirrhosis. He had a variceal hemorrhage 2 months ago and has been treated previously for hepatic encephalopathy. The patient takes nadolol, furosemide, spironolactone, and lactulose at home. There have been no changes in his dietary intake, and he has not used any over-the-counter medicines or herbal supplements. He still occasionally drinks alcohol but does not use tobacco or illicit drugs. Temperature is 38 C (100.4 F), blood pressure is 104/60 mm Hg, and pulse is 96/min. The patient is cachectic and somnolent, and he wakes up with painful stimuli. He has a flapping tremor of both hands, and the speech is slurred and incomprehensible. Mucous membranes are dry, and he has scleral icterus. Several spider angiomata are present on the upper torso. The lungs are clear to auscultation, and heart sounds are normal with no murmur. The abdomen is distended and tense with large abdominal wall collaterals. There is a fluid wave and diffuse tenderness but no rebound tenderness. Bowel sounds are decreased. Stool occult blood is negative. Laboratory results are as follows:
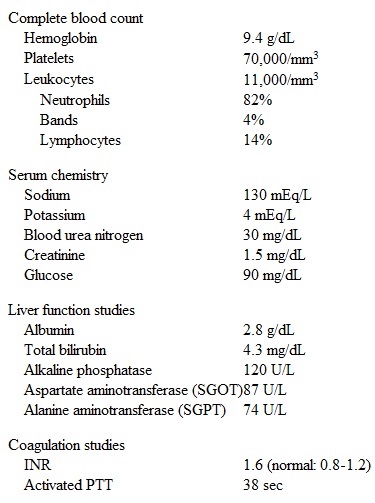 A diagnostic paracentesis is performed, and the ascitic fluid results are as follows:
 Which of the following is the best next step in management of this patient?
A diagnostic paracentesis is performed, and the ascitic fluid results are as follows:
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.7/5 (81)
(81) A 60-year-old man comes to the office for an annual preventive visit. The patient feels healthy and has no symptoms. He has a history of hypertension that is well controlled with lisinopril. The patient does not use tobacco or alcohol; he has a balanced diet and exercises regularly. He had a normal screening colonoscopy 10 years ago but says, "I had an awful experience during the bowel preparation, and I would rather not go through that again." He has no family history of colorectal cancer. Vital signs are normal, and physical examination shows no abnormalities. The patient agrees to undergo flexible sigmoidoscopy, which reveals 2 pedunculated polyps of 1-1.5 cm in the descending colon; the polyps are removed, and histopathology findings are consistent with villous adenoma in both polyps. Which of the following is the best recommendation for this patient regarding colorectal cancer screening?
(Multiple Choice)
4.9/5 (86)
(86) A 19-year-old man comes to the student health center due to 2 days of burning pain during urination. He has also had itching of the urethral meatus but no urinary discharge, fever, chills, or rash. The patient has no chronic medical conditions and takes no medications. He had unprotected sexual intercourse with a new female partner a week ago. The patient has smoked a pack of cigarettes daily since age 14. He drinks alcohol on weekends and does not use illicit drugs. Vital signs are within normal limits. There is scant, watery urethral discharge at the urethral meatus. There are no genital ulcers, rashes, erythema, or inguinal lymphadenopathy. Urethral swab is performed, and Gram stain of the urethral fluid reveals many neutrophils but no organisms. Nucleic acid amplification tests of the urine are sent for Chlamydia trachomatis and Neisseria gonorrhoeae. The patient received treatment with a single dose of azithromycin but returns to the office 2 weeks later due to continued burning with urination. Since his previous visit, he has had no urethral discharge, fever, chills, scrotal pain, rash, or additional sexual encounters. Nucleic acid amplification testing from his prior visit was negative for Neisseria gonorrhoeae and Chlamydia trachomatis. Screening for syphilis with rapid plasma reagin and for HIV with fourth-generation HIV testing was also negative. No urethral discharge is present, and the remainder of the physical examination is normal. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (87)
(87) A 35-year-old man is brought to the emergency department after cutting his finger with a rusty knife while doing yard work. It is a deep cut, and his wife had immediately applied a pressure dressing to stop the bleeding. His immunization status is unknown. The patient last saw his doctor about 10 years ago, and cannot recall if he received all of his childhood vaccinations. He has a deep laceration on the palmar aspect of his right middle finger. Cleaning of the wound and other wound-care measures are initiated. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (68)
(68) A 19-year-old man is brought to the emergency department by his mother. She says that he has been acting strangely for the past 2 months, spending significantly less time with his friends and more time on the computer. Over the past few nights the mother has observed the patient shouting at the computer screen. She became alarmed when he suddenly disconnected all electronic devices in the house and warned his family that encrypted messages were being sent over the internet to control his brain. The patient's grades at the local community college have recently declined, and he stopped attending classes after he became convinced that other students were laughing at him behind his back. He has no medical history. Psychiatric history is significant for mild anxiety in high school that was never treated. The patient does not use tobacco or alcohol but smokes marijuana daily. He also has used cocaine on several occasions. There is a family history of schizophrenia in a maternal uncle. Vital signs are within normal limits and physical examination shows no abnormalities. The patient is cooperative, guarded, and anxious during the interview. Blood work and a CT scan of his brain are normal. Urine toxicology is positive for tetrahydrocannabinol. The mother asks if her son is going to be okay. After obtaining consent from the patient to speak with his mother, which of the following is the most appropriate response to her at this time?
(Multiple Choice)
4.9/5 (81)
(81) A 59-year-old man comes to the office for a routine wellness examination. The patient's medical history includes chronic bronchitis, hypertension, hypertriglyceridemia, and basal cell carcinoma. He smokes a pack of cigarettes per day, with a total 40-pack-year history. The patient typically consumes 1 or 2 cans of beer each night. Family medical history is remarkable for heart disease and diabetes mellitus. The patient had a normal screening colonoscopy 5 years ago. A chest x-ray from a year ago shows changes consistent with chronic bronchitis.
The patient asks if he is at increased risk for lung cancer because of his smoking history. What is the most appropriate response by the physician?
(Multiple Choice)
4.8/5 (66)
(66) A 35-year-old woman, gravida 2 para 1, at 20 weeks gestation comes to the office due to cholelithiasis found incidentally during a prenatal ultrasound. She has no prior history of gallstones and has no abdominal pain, jaundice, or clay-colored stool. She has no chronic medical problems, and her only medication is a daily prenatal vitamin. The patient stopped drinking alcohol after learning that she was pregnant and does not use tobacco or illicit drugs. Her mother underwent cholecystectomy for acute cholecystitis at age 40. Vital signs are within normal limits. The patient is anicteric and mucous membranes are moist and pink. Examination reveals a gravid abdomen but no tenderness. Laboratory results are as follows:  Ultrasonography of the right upper quadrant reveals a 1-cm gallstone without gallbladder distension, wall thickening, or pericholecystic fluid. The intrahepatic biliary ducts and common bile duct are normal in size. Which of the following is the most appropriate intervention for this patient's gallstone?
 (Multiple Choice)
5.0/5 (80)
(80) A 34-year-old woman comes to the physician after several months of amenorrhea. Several home pregnancy tests have been negative. Her past medical history is insignificant. She is married with 2 children and has no plans to have more. Her body mass index is 23 kg/m2. Physical examination is unremarkable. Serum prolactin level is 500 ng/mL (normal 5-20 ng/mL). Magnetic resonance imaging of the head shows a 5-mm pituitary mass. This patient is at high risk of developing which of the following if left untreated?
(Multiple Choice)
4.9/5 (73)
(73) A 27-year-old woman, gravida 3 para 3, comes to the office for an annual examination. She has no intermenstrual or postcoital bleeding or abnormal vaginal discharge. Her last menstrual period was 2 weeks ago. The patient has no chronic medical conditions and takes a multivitamin daily. She has had 3 uncomplicated vaginal deliveries and no surgeries. The patient has had 2 sexual partners in the past 3 years and uses oral contraceptive pills. Her last Pap test 3 years ago demonstrated atypical squamous cells of undetermined significance (ASCUS), and reflex human papillomavirus (HPV) testing at that time was negative. The patient has no history of sexually transmitted infections. Vital signs are normal. BMI is 22 kg/m2. The cervix appears parous and without visible lesions. The uterus is small, anteverted, and mobile, with notable descent of the cervix to the introitus during the Valsalva maneuver; the adnexa are not enlarged. Pap testing indicates a high-grade squamous intraepithelial lesion (HSIL). Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (78)
(78) A 73-year-old woman is brought to the office by her daughter due to worsening memory. The patient began having difficulty with her memory 2 years ago but was mostly independent until recently. Over the past 2 months, she has gotten lost several times while driving locally. She can no longer be allowed to cook for herself because she has frequently forgotten to turn off the stove. The patient has hypertension, gastroesophageal reflux disease, and alcohol use disorder. Her medications include lisinopril and ranitidine. Family history is negative for dementia. Vital signs and physical examination are within normal limits. TSH and vitamin B12 levels are normal. Montreal Cognitive Assessment is 22 out of 30 (normal: ≥26). Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (64)
(64) A 22-year-old primigravida comes to the office at 12 weeks gestation for her first prenatal visit. The patient was unaware that she was pregnant until last week, when she went to the emergency department for persistent vomiting; an ultrasound confirmed an intrauterine pregnancy. The patient has irregular menstrual cycles due to polycystic ovary syndrome. Nine months ago, she stopped taking oral contraceptives due to intolerable side effects; she did not inform her provider. The patient also has a history of idiopathic seizures beginning in childhood and receives valproate monotherapy. She states, "I just read in one of those maternity books that seizure medications can be bad for my baby. Should I stop now? I have not had a seizure in a long time." Her last seizure occurred a year ago after an attempt to change her medication regimen; she was hospitalized for aspiration pneumonia afterward. The patient does not use tobacco, alcohol, or illicit drugs. There is no family history of congenital abnormalities. Item 1 of 2
Which of the following is the best strategy for management of this patient?
(Multiple Choice)
4.8/5 (81)
(81) A 47-year-old Caucasian man comes to the office for a follow-up visit. He was recently diagnosed with diabetes mellitus type 2, and was started on a low-carbohydrate diet six months ago. He also has obesity, hypertension and hyperlipidemia. He is a financial advisor. He does not use tobacco or illicit drugs, but drinks alcohol occasionally. His medications include enalapril, simvastatin and hydrochlorothiazide. Examination shows no abnormalities. His laboratory test results show the following:
Serum Chemistry
 LFT
 Lipid Profile
 Which of the following is the most appropriate pharmacotherapy for this patient?
LFT
Lipid Profile
Which of the following is the most appropriate pharmacotherapy for this patient? (Multiple Choice)
4.9/5 (88)
(88) A 21-year-old woman comes to the office due to weakness and fever for 9 days. She has also developed headaches, myalgia, and a sore throat. The patient's symptoms have worsened since their onset, causing her to be unable to go to work. Despite remaining in bed for most of the day, she feels "exhausted." She has lost 2 kg (4.4 lb) over the past week. The patient has no significant medical history and takes no medications. She drinks alcohol occasionally and has smoked a pack of cigarettes a day for the past 7 years. She is sexually active and uses condoms "most of the time." Temperature is 38.3 C (100.9 F), blood pressure is 120/70 mm Hg, pulse is 82/min, and respirations are 16/min. Physical examination shows an awake but tired woman. There is no rhinorrhea or erythema of tympanic membranes; she has enlarged tonsils with white exudates. Large cervical and axillary lymph nodes are palpable bilaterally. S1 and S2 are normal without murmurs. Lungs are clear to auscultation bilaterally. The abdomen is soft and nontender with normal bowel sounds; the liver edge extends 2 cm below the right costal margin and there is palpable splenomegaly. There are no rashes or lesions. The appropriate treatment was started and the patient was discharged and scheduled for follow-up. Two days later, she comes to the emergency department due to difficulty breathing. The patient states that she has developed shortness of breath when lying down. She has also had increased difficulty swallowing. On examination, she appears agitated. Her tonsils have increased erythema and swelling and now meet at the midline; there is copious white exudate. Multiple enlarged anterior and posterior cervical lymph nodes are present. What is the most appropriate next step in management of this patient's condition?
(Multiple Choice)
4.8/5 (86)
(86) A 45-year-old Caucasian man comes to see you in the office. He is accompanied by his wife. They have noticed that he has shakiness of both hands for the past six months. The shakiness is limited only to his hands and has not progressed over time. It becomes much more pronounced when he tries to pick up things or attempts to eat or drink. On physical examination, you notice a constant tremor in both his hands, which becomes much more pronounced when his arms are outstretched. There is also a very subtle head tremor present. There is no rigidity or slowing of voluntary movements in the upper or lower extremities. His father had a similar problem in his 50s or 60s, but he is not sure what treatment he received at that time. His wife is extremely anxious and wants to know his prognosis.
Item 1 of 2
Which of the following is the most appropriate response?
(Multiple Choice)
4.7/5 (85)
(85) A 68 year old male presents to the emergency room with his wife complaining of falling at his home. The patient is currently hemodynamically stable and has no other complaints. The patient takes hydrochlorothiazide and metoprolol for high blood pressure and atorvastatin for hypercholesterolemia. A head CT reveals no intracranial bleeding or skull fractures and the patient is free of any noticeable injuries. The patient says he feels fine and wonders if it is okay to go home. What is the next best step in the management of this patient?
(Multiple Choice)
5.0/5 (92)
(92) A 6-year-old boy is brought to the emergency department due to difficulty breathing. His mother states that he had a mild sore throat yesterday but seemed to respond to over-the-counter analgesics. She adds, "I noticed that my son felt warm, and his voice sounded raspy and hoarse. However, he was sleeping comfortably until an hour ago when he woke up suddenly with rapid, labored breathing." The patient has no cough, runny nose, emesis, or diarrhea. He recently attended a family wedding where several guests were ill. Medical history is significant only for multiple episodes of otitis media and occasional upper respiratory infections. Other than analgesics for this illness, he takes no medications and has not been vaccinated. Temperature is 40 C (104 F), blood pressure is 105/70 mm Hg, pulse is 128/min, and respirations are 46/min. Examination shows an agitated-appearing boy who is leaning forward with his neck extended and mouth open wide. His tongue is protruding, and he is drooling heavily. There is mild inspiratory stridor with no wheezing or crackles, and subcostal and intercostal retractions are present. Heart sounds are normal without murmurs. There are no rashes or skin lesions. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (69)
(69) A 17-year-old girl, gravida 0 para 0, comes to the office for routine examination and an oral contraception prescription. Her menses occur every 28 days and her last menstrual period was 3 weeks ago. She is feeling well and is preparing to leave for college in 5 months. The patient has no chronic medical conditions or previous surgeries. She has no history of migraine headaches or thromboembolism. The patient is up to date on all vaccinations. Her maternal grandmother has hepatitis B; family history is otherwise noncontributory. The patient currently takes no medications and does not use tobacco, alcohol, or illicit drugs. She has no known drug allergies. She has been sexually active with one partner for the past 2 years and uses condoms for contraception. Temperature is 37.2 C (99 F), blood pressure is 110/70 mm Hg, and pulse is 72/min. Weight is 60 kg (132.3 lb) and height is 162.5 cm (5 ft 4 in). Cardiopulmonary examination is normal. The abdomen is soft and nontender with no hepatosplenomegaly. On pelvic examination, no vulvar or cervical lesions and no cervical discharge are present. On bimanual examination, the uterus is small and without cervical motion tenderness. Bilateral adnexa are small, mobile, and nontender. In addition to an oral contraception prescription, which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (74)
(74) A 46-year-old man comes to the office due to a 3-day history of cough, wheezing, and shortness of breath. Symptoms started a week ago with nasal congestion, sore throat, and body aches. The cough is productive of thin, whitish sputum. The patient has no fever, chills, chest pain, or abdominal pain. He has asthma managed with budesonide-formoterol as needed. Since yesterday, he has used the inhaler multiple times without significant symptom relief. His other medical condition is hypertension. He does not use tobacco, alcohol, or illicit drugs. Temperature is 36.7 C (98.1 F), blood pressure is 138/74 mm Hg, pulse is 86/min, and respirations are 20/min. Pulse oximetry is 96% on room air. The patient speaks in full sentences. He appears mildly uncomfortable but does not use accessory respiratory muscles. Jugular venous pressure is normal. There is no nasal sinus tenderness. The pharyngeal mucosa is without exudates. Bilateral expiratory wheezing with prolonged expiration is noted. Inspiratory breath sounds are normal. Heart sounds are normal. Peak expiratory flow is 30% lower than his prior baseline. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (87)
(87) Showing 641 - 660 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)