



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


An 82-year-old man is admitted to the hospital after an out-of-hospital cardiac arrest. He was successfully resuscitated and intubated in the field by paramedics and transferred to the hospital's intensive care unit. On day 3 of hospitalization, he remains minimally responsive to most stimuli. The hospital has the patient's advance directive on file, which clearly states that the patient does not want life-sustaining treatment, including mechanical ventilation. The patient's wife agrees with the advance directive and wants to withdraw life support. The rest of the family, including a son and 2 daughters from a previous marriage, become very upset with her decision and strongly oppose the withdrawal of life support. They claim that their father's wife "never really cared for him and married him only for his money." They would like to continue mechanical ventilation to see if their father's condition improves. Despite multiple meetings with all family members in an attempt to reach a mutual decision, the patient's children and wife continue to disagree about management. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
5.0/5  (91)
(91) A 38-year-old man was brought to the emergency department after nearly being hit by a car that swerved to avoid hitting him as he walked down the middle of a busy city street. On arrival, the patient was ataxic and his speech was slurred. He had evidence of polysubstance abuse on toxicology testing. He received intravenous fluids and was monitored for several hours in the emergency department. The patient's vital signs are now stable. He is oriented to time, place, and person, and he feels badly about his behavior. As the patient is about to be discharged, his wife arrives. He informs the staff that he does not wish to see her. Before the staff can intervene, she bursts into his room and they begin a heated argument about his substance use, recent job loss, and neglect of family responsibilities. The nurse asks the patient's wife to leave, but she says, "I'm not leaving. He is going to hear everything I have to say!" The patient becomes increasingly agitated and starts shouting. His fists are clenched and his loud voice and offensive language disrupt nearby staff and patients. Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.9/5 (87)
(87) A 4-month-old boy is brought to the office by his parents for a well-child visit. Their only concern is that the infant spits up a few times a day after breastfeeding. These episodes are occurring less frequently than before, and the emesis is not bilious or projectile. He is sometimes fussy after spitting up but is easily consolable. The patient was born at 37 weeks gestation by spontaneous vaginal delivery and has no chronic medical conditions. Vaccinations are up to date. His weight and length growth charts are shown in image 1, and the head circumference growth chart is shown in image 2. On physical examination, the patient is alert and smiling. The anterior fontanelle is soft and flat, and there are no craniofacial anomalies. Cardiac examination is normal. The abdomen is soft and nontender. He is able to roll from his stomach to his back and hold his head steady without support. Which of the following is the best next step in the management of this patient?
(Multiple Choice)
4.8/5 (76)
(76) A 67-year-old man comes to the emergency department due to 3 days of fever and cough productive of yellowish sputum. He has had no hemoptysis, weight loss, night sweats, or anorexia. He has not traveled recently and has not had exposure to anyone with similar symptoms. The patient was discharged from the hospital 3 weeks ago after an episode of community-acquired pneumonia involving the left lower lobe. He is a chronic smoker with a 45-pack-year smoking history. He drinks alcohol occasionally. Temperature is 38.1 C (100.6 F), blood pressure is 112/52 mm Hg, pulse is 98/min, and respirations are 22/min. Oxygen saturation is 90% on room air. Physical examination reveals decreased breath sounds and crackles over the left lower lobe. Chest x-ray is consistent with consolidation of the left lower lung zone. What is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (68)
(68) A 49-year-old woman with a history of multiple sclerosis and epilepsy is hospitalized due to recurrent seizures. Her multiple sclerosis is complicated by spastic paraplegia and urinary incontinence. The patient lives with her family, but as her disease has progressed it has become difficult for them to physically assist her and help in her care. As a result, she has missed several doses of medications, including her antiepileptics. The patient does not use alcohol, tobacco, or illicit drugs. Temperature is 36.6 C (97.9 F), blood pressure is 136/80 mm Hg, pulse is 75/min, and respirations are 16/min. BMI is 19.5 kg/m2. Physical examination shows severe extensor spasticity in both lower extremities. Skin examination shows a 4×6 cm ulcerated area overlying the left ischial tuberosity. Devitalized tissue is present around the wound edges, but the base is clearly visible. The wound extends into the subcutaneous tissue, but no muscle, tendon, bone, or fascia is visible; there are no undermined areas or sinus tracts. The wound surface has no foul odor or exudate. The need for frequent turning is discussed with the nursing staff, and an air-fluidized bed is ordered. Which of the following additional measures is most appropriate for treatment of this patient's wound?
(Multiple Choice)
4.9/5 (65)
(65) A 36-year-old man comes to the emergency department with severe pain in his left leg. He is a carpenter and recalls that he had a small puncture wound from a wood splinter yesterday in his workshop. The patient washed the wound and applied a small adhesive bandage. This morning, he experienced severe pain in his left thigh and calf, and the pain has worsened since. He has no other medical problems and takes no medications regularly. His temperature is 39.4 C (103 F), blood pressure is 90/60 mm Hg, heart rate is 96/min, and respirations are 16/min. Physical examination of his left lower extremity shows slight erythema and swelling of the thigh and calf with severe tenderness to palpation. Two blisters are present on the posterior aspect of his proximal calf. While in the emergency department, the patient complains of increasing pain despite intravenous narcotic administration. His blood pressure decreases to 70/50 mm Hg despite 2 L intravenous fluids. Vasopressors are initiated. His creatine phosphokinase level is 7,400 IU/L (normal 60-174 IU/L) and lactic acid level is 3.2 mmol/L (normal 0.7-1.8 mmol/L). Blood cultures are pending. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.7/5 (80)
(80) A study of patients with metastatic renal cell carcinoma (RCC) compared the effectiveness of standard chemotherapy to a novel tyrosine kinase inhibitor (TKI) with activity against vascular endothelial growth factor in progression-free survival (primary end point) as first-line treatment. Tumor response was significant in both groups at final follow-up (p < 0.05). The Kaplan-Meier survival curve for overall survival is shown below. 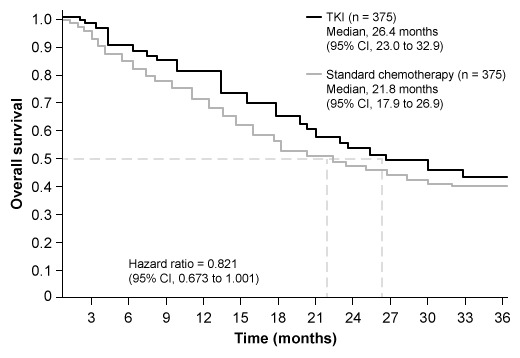 Treatment-related adverse events such as diarrhea, nausea, vomiting, hypertension, hand-foot syndrome, asthenia, leukopenia, neutropenia, thrombocytopenia, lymphopenia, and increased lipase and uric acid occurred more frequently in the TKI group than in the standard chemotherapy group (p < 0.05). Based on the findings of this study, which of the following conclusions is justified?
 (Multiple Choice)
4.9/5 (87)
(87) A previously healthy 28-year-old Caucasian woman comes to the physician because of fatigue, arthralgias, and chest pain over the past 6 months. She has had a 2.3-kg (5-lb) weight loss during this period. She denies any recent travel or sick contacts. Her past medical history is insignificant. She takes no medications and has no known drug allergies. She is sexually active and uses condoms for contraception. She has never been pregnant. She does not use tobacco, alcohol, or drugs. Her mother has rheumatoid arthritis. Her temperature is 37.2 C (99 F), blood pressure is 122/77 mm Hg, and pulse is 78/min. Physical examination shows a faint facial rash. The lungs are clear to auscultation with mildly decreased breath sounds at the left lung base. The abdomen is soft and non-tender. There is no organomegaly. There is no peripheral edema. Neurologic examination is unremarkable.
The patient returns one week after the initial visit. Her laboratory work-up shows the following additional findings:
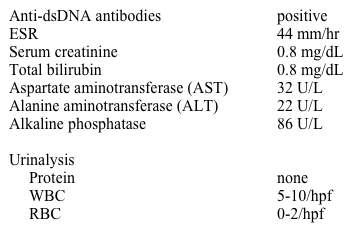 An x-ray film of the chest shows a mild, left-sided pleural effusion. Which of the following is the most appropriate next step in management?
 (Multiple Choice)
4.8/5 (70)
(70) A 76-year-old woman is hospitalized due to a fracture of her right proximal femur from an accidental nonsyncopal fall. Medical history is notable for breast cancer treated with a radical mastectomy 10 years ago, hypertension, and hyperlipidemia. She drinks a pint of vodka daily, but does not use tobacco or illicit drugs. The patient is started on thiamine and folic acid, and the next morning she undergoes orthopedic surgery for internal fixation of the right femur. She experiences mild agitation postoperatively, which is managed with as-needed, low-dose benzodiazepines. In addition, she is treated with low-molecular-weight heparin, opiates, and continued vitamin supplementation. On her third postoperative day, the nurse finds her agitated and in significant distress. The patient has an episode of nonbloody vomiting. On initial evaluation, she appears restless and confused but follows commands. Temperature is 36.7 C (98 F), blood pressure is 92/58 mm Hg, pulse is 122/min and regular, and respirations are 31/min. Pulse oximetry is 75% on room air and improves to 82% with supplemental oxygen by non-rebreather mask. Chest auscultation reveals no crackles or wheezes. Cardiac examination demonstrates tachycardia with a regular rhythm and normal S1 and S2. The abdomen is soft. Her pupils are equal and reactive to light, and she is moving all extremities. The patient is successfully intubated and put on mechanical ventilation. Initial settings include fraction of inspired oxygen set to 100% and positive end-expiratory pressure of 5 cm H2O. Pulse oximetry shows 96%. Her blood pressure drops to 78/42 mm Hg and pulse is 120/min. ECG shows sinus tachycardia and a new right bundle branch block with no ST-segment or T-wave changes. Chest x-ray reveals a normal cardiac silhouette and no infiltrates. Which of the following is most likely to show on emergent bedside echocardiogram?
(Multiple Choice)
4.7/5 (94)
(94) A 20-year-old female is referred to your office by her pediatrician. The patient has been followed by her pediatrician for idiopathic hypoparathyroidism for the past four years. She takes vitamin D 50,000 units with 1.5 g of elemental calcium every day. She denies any symptoms. The physical examination is unremarkable, including a negative Chvostek's sign. Her calcium level is 7.8 mg/dL, and phosphorus level is of 5.2 mg/dL. Her 24-hour urinary calcium is 680 mg. What is the next best step in the management of this patient?
(Multiple Choice)
4.9/5 (73)
(73) A 58-year-old man comes to the physician for follow-up of type 2 diabetes mellitus. He has had diabetes for 14 years. Other medical problems include hypertension and hyperlipidemia. His current medications include glipizide, metformin, lisinopril, atorvastatin, and daily low-dose aspirin. The patient's hemoglobin A1c has progressively increased over the last few years; however, he has repeatedly refused to add additional medication to improve glycemic control. He does not use tobacco or alcohol. The patient's father also had type 2 diabetes and died of a myocardial infarction at age 55. Blood pressure is 134/78 mm Hg and pulse is 78/min. BMI is 33 kg/m2. Physical examination, including lower extremity vascular and sensory examination, is normal. Laboratory evaluation shows a fasting blood glucose level of 178 mg/dL, serum creatinine of 1.1 mg/dL, and hemoglobin A1c of 8.8%. While discussing additional medication to improve his glycemic control, the patient says, "Doc, I feel fine. I don't understand why you keep trying to give me more pills." Which of the following is the most appropriate response to this patient?
(Multiple Choice)
4.7/5 (69)
(69) A 36-year-old man comes to the emergency department due to loss of consciousness. He was standing in a crowded subway station when he felt lightheaded, had a pounding sensation in his chest, and passed out. On awakening, he felt short of breath for a little while and then was "completely fine." He has had no similar episodes, nor chest pain, confusion, tongue biting, or urinary incontinence. The night before, he was at a party with friends and consumed alcohol. Later he was nauseated and had 3 episodes of vomiting and one episode of diarrhea. In the emergency department, blood pressure is 124/68 mm Hg and pulse is 80/min. There is a small laceration above his right eyebrow. Cardiac examination shows normal heart sounds with regular rhythm. The lungs are clear to auscultation. Neurologic examination shows no abnormalities. ECG is shown in the exhibit.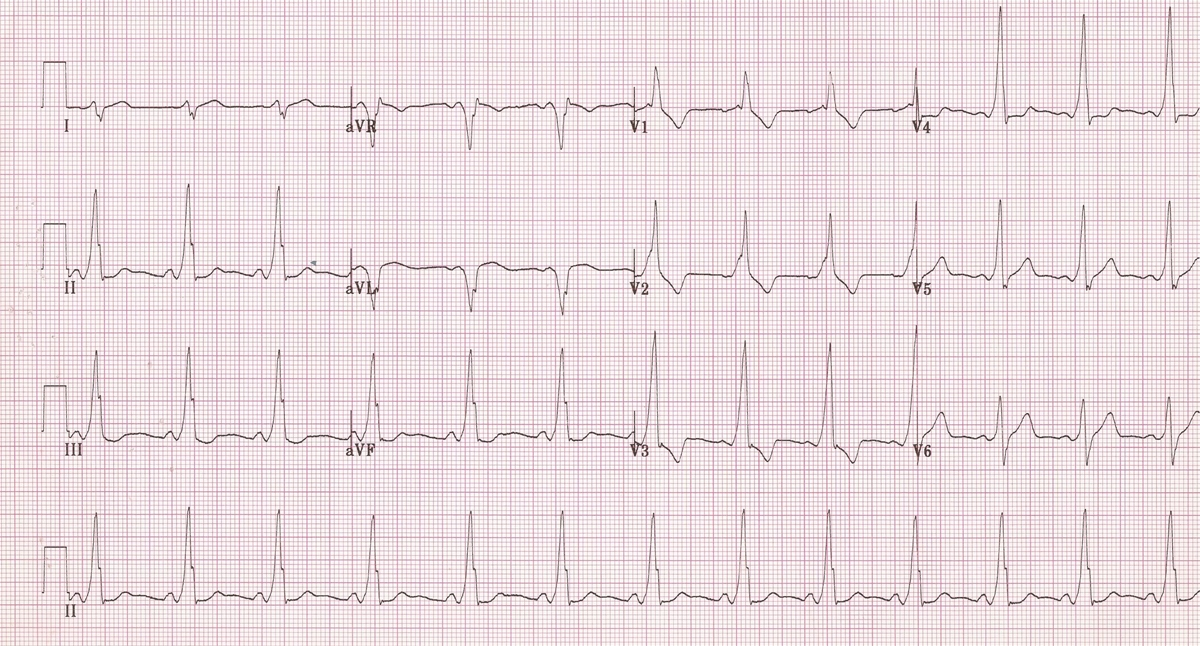 The patient is hospitalized for observation. His serum electrolytes are within normal limits. Echocardiogram shows normal left ventricular size and function and no significant valvular abnormalities. During the hospital stay, he has another episode of lightheadedness when the telemetry revealed brief supraventricular tachycardia that resolved spontaneously. Which of the following is the most appropriate next step in management?
 (Multiple Choice)
4.9/5 (78)
(78) A 16-year-old boy comes to the office for follow-up after having been seen in the emergency department 5 days ago due to an acute asthma exacerbation. Two weeks ago, he developed a cough and rhinorrhea. The rhinorrhea resolved after a few days, but the cough worsened and he began wheezing, prompting his visit to the emergency department. In the emergency department, his temperature was 36.7 C (98 F), respirations were 24/min, pulse oximetry was 94% on room air, and pulmonary examination revealed scattered expiratory wheezes with slightly diminished breath sounds in all fields. The patient received 2 doses of nebulized albuterol and 60 mg of oral prednisone, after which he felt considerably better and had a normal lung examination; he was then discharged home on an additional 60 mg of prednisone daily for the next 4 days. Today he feels well and his cardiopulmonary examination is normal. Prior to this illness, he had been treated at home for the last several years with intermittent albuterol. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (83)
(83) A 42-year-old man comes to the emergency department due to a week of eye pain and blurry vision. Initially, he developed mild red eye and irritation, which he attempted to manage with artificial tear drops. The patient works as a commercial fisherman and had assumed his symptoms were due to frequent sun and water exposure. However, over the past few days, his eye pain has worsened, and he can "barely see" out of his left eye. He has no medical history but has a family history of hypertension and diabetes. Temperature is 37.2 C (99.1 F). Blood pressure is 128/82 mm Hg, pulse is 70/min, and respirations are 11/min. There is copious clear drainage from the left eye, and a large ulceration is overlying the cornea; the right eye appears unremarkable. Minimal sensation of the left cornea is noted during esthesiometry testing. With fluorescein application, additional shallow linear, branched ulcerations are visualized along the margins of the central defect of the affected eye. Routine Gram stain of the bacterial culture shows numerous white blood cells but no organisms. Which of the following should be started immediately in this patient?
(Multiple Choice)
4.7/5 (91)
(91) A 16-year-old boy is brought to the emergency department via ambulance. The school nurse who accompanied him informs the physician that he has had 2 days of headache and generalized body aches that did not respond to acetaminophen. He felt well enough to attend school and to work his part-time job at a local hardware store. However, this morning his headache worsened and he was extremely drowsy. The paramedics administered intravenous normal saline; no other interventions were required during transport. In the emergency department, he becomes lethargic, has a seizure, and is immediately intubated by the resident physician. Subsequent evaluation reveals that the patient is suffering from acute meningococcal meningitis.
In addition to the patient's family members, which of the following contacts requires antibiotic prophylaxis to prevent the development of meningococcal meningitis?
(Multiple Choice)
4.9/5 (85)
(85) A 9-month-old boy is brought to the office by his mother due to fever for 3 days. The patient has been irritable for the past 2 days. He normally drinks 6-oz bottles of expressed breast milk but has been taking <3 oz per feed and voiding less frequently than usual. He has had no rash, cough, congestion, vomiting, or diarrhea. The patient takes no medications and has no known allergies. Temperature is 38.9 C (102 F). He is irritable but easily consoled by his mother. Mucous membranes are moist, and tears are present with crying. Tympanic membranes are gray and translucent bilaterally, and the oropharynx is normal. Cardiopulmonary examination is normal. The abdomen is soft, nontender, and nondistended. The penis is uncircumcised. Urine catheterization is performed and urine dipstick analysis reveals the following:  Oral antibiotics are started, and the patient is afebrile within 36 hours. Urine culture yields >50,000 colony-forming units of Escherichia coli. After completion of the therapeutic antibiotic course, which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.7/5 (84)
(84) A 49-year-old woman comes to the physician requesting treatment for "this unattractive redness of my skin." In the past 3 months, she developed blemishes on her nose, cheeks, and chin. She now flushes intensely in response to hot or cold temperatures, emotion, and the consumption of spicy foods or alcohol. She has no history of dermatological problems. Physical examination shows a reddening of the central face, erythematous papules on the nose, and sporadic telangiectasias on the nose and cheeks as shown below. 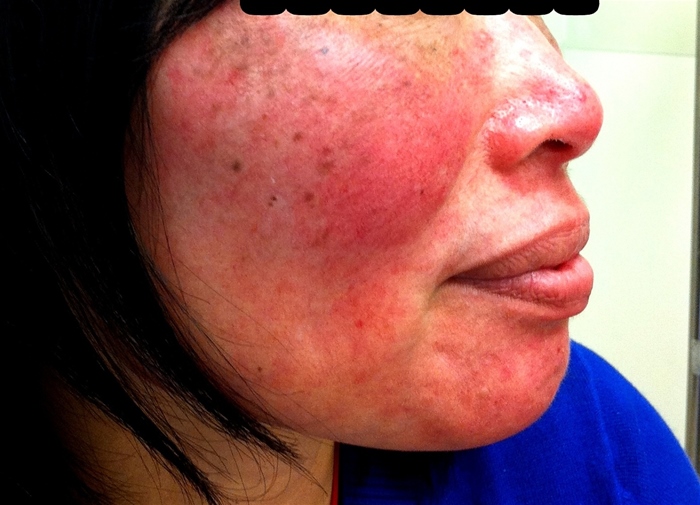 Which of the following is the most appropriate treatment for this condition?
 (Multiple Choice)
4.8/5 (73)
(73) A 26-year-old Italian-American man comes to your office for the evaluation of low back pain. He has had this pain for the last eight months, and it is progressively getting worse. The pain is worse in the morning and gets better as the day progresses. He denies any history of trauma in the past. He works as a chef at a local restaurant. His father and uncles also have "back problems." His physical examination reveals a limited range of motion of his lumbosacral spine and markedly reduced chest expansion. The rest of his physical and musculoskeletal examination is unremarkable. The patient is given a prescription for non-steroidal anti-inflammatory agents. He returns for a follow-up visit after two weeks, and says that he feels a lot better. His pain and stiffness have almost resolved with daily intake of medications. He used to swim and exercise regularly before his symptoms developed a few months ago, and he wants to resume these activities, but he is concerned that his disease may get worse if he does so. Which of the following is the most appropriate response?
(Multiple Choice)
4.8/5 (77)
(77) A 46-year-old woman comes to the clinic for follow-up treatment of hypertension. The patient was diagnosed with hypertension 2 years ago and nonpharmacological management was initially advised. A year ago, she was started on valsartan and amlodipine after her blood pressure was measured at 144/86 mm Hg. A month after treatment initiation, she reported no adverse effect from the medication and blood pressure was 130/80 mm Hg. Since then, the patient has missed several follow-up appointments, which she attributes to being busy at work. She currently has no concerns and overall feels "great." She has had no chest pain, headaches, lightheadedness, or syncope. The patient has no other medical issues and does not use tobacco or alcohol. She works as a salesperson and eats fast food a few times a month. Her mother died of a stroke at age 67. Today, blood pressure is 152/88 mm Hg in the right arm and 148/86 mm Hg in the left arm; pulse is 76/min and regular. Repeat blood pressure measurements after 15 minutes of rest are similar. BMI is 28 kg/m2. Estimated jugular venous pressure is normal. There are no carotid bruits. Heart sounds are normal with no murmurs. Lung examination is unremarkable. Peripheral pulses are full and symmetric. There is no peripheral edema. Laboratory results are as follows:  ECG shows normal sinus rhythm with nonspecific T-wave changes. Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (76)
(76) A 59-year-old man comes to the office for follow-up. He has a history of hypertension for which he takes 2 antihypertensive agents. The patient has no other cardiovascular problems and does not smoke. On examination, his blood pressure is 145/90 mm Hg and BMI is 25.4 kg/m2. The remainder of the examination is unremarkable. Laboratory studies show elevated fasting lipid levels, including LDL cholesterol. His 10-year risk of cardiovascular events is calculated as 10%, and a discussion regarding moderate or intensive statin therapy is initiated. The patient has read that statins may cause diabetes and asks if there is an even more increased risk with intensive compared to moderate statin therapy. Based on the abstract, what was the pooled odds ratio of major cardiovascular events among participants on intensive compared to moderate statin therapy?
(Multiple Choice)
4.9/5 (81)
(81) Showing 881 - 900 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)