



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


A 32-year-old female comes to the physician's office for a follow-up visit. She was recently brought to the emergency department due to head trauma, and the head CT scan performed at that time revealed an abnormal sella. She does not have any significant medical problems. She is currently not on any medications. Her menstrual cycles are regular. She is sexually active with one partner. She does not have any children. Her family history is insignificant. She does not smoke cigarettes or drink alcohol. Her physical examination is unremarkable. Prolactin, IGF-1, LH, FSH, TSH, and free T4 are within normal limits. Her plasma cortisol is normally suppressed after the administration of 1 mg of dexamethasone. MRI of the pituitary region shows a 5-mm hypo-intense lesion within the pituitary gland, whose architecture is not distorted. The rest of the brain appears normal. What is the next best step in the management of this patient?
(Multiple Choice)
4.8/5  (79)
(79) A 30-year-old Caucasian man with no significant past medical history presents to his primary care physician complaining of nausea, vomiting, diarrhea, abdominal cramping, and fever to 38.3C (100.9F). The symptoms started 12 hours after the man consumed a beverage that contained pureed fruit, powdered protein, and three raw eggs. Physical examination of the man is unremarkable. Salmonella enteritidis is subsequently isolated from his stool culture. What is the best means of managing this patient's care?
(Multiple Choice)
4.9/5 (75)
(75) An 82-year-old woman with dementia and insulin-dependent diabetes mellitus is evaluated at her nursing home due to a urine culture result showing Escherichia coli. Two days ago, the patient was taken to the emergency department due to increased confusion from her baseline that was noted shortly following breakfast. Evaluation revealed mild hypoglycemia and dehydration but normal blood cell counts, serum chemistry studies, chest x-ray, and brain imaging. Urinalysis showed 10-15 leukocytes/hpf and occasional bacteria; a clean catch urine culture specimen was obtained. The patient's confusion resolved with intravenous hydration and normalization of her glucose levels; her medication regimen was reviewed, and she was sent back to the nursing home. A staff member from the emergency department contacts the nursing home as the urine culture grew >100,000 cfu/mL of Escherichia coli sensitive to trimethoprim-sulfamethoxazole and ciprofloxacin. The patient has had no fever, abdominal pain, dysuria, hematuria, or hypoglycemia. Her other medical issues include hypertension, hyperlipidemia, and osteoarthritis. Vital signs are within normal limits. The patient is at her baseline neurocognitive function with orientation to place and person only. Lungs are clear to auscultation and heart sounds are normal. Abdominal examination reveals no suprapubic or flank tenderness. Which of the following is the most appropriate next step in management of this patient's urinary abnormalities?
(Multiple Choice)
4.8/5 (81)
(81) A 23-year-old male with type 1 diabetes presents to your office with blurry vision in both eyes. He states that he is having problems with reading television captions and things written on the classroom board. He denies any redness, discharge or pain in his eyes. He also complains of increased urination, increased thirst and weight loss. He has had diabetes for the past year, and is presently on a multiple dose injection regimen of NPH and regular insulin. Lately, he has not been compliant with his insulin regimen, and his blood sugars have been ranging from 200-300 mg/dl during the past months. His HBA1c, performed 7 days ago, is 9.0 % (normal 4-6%). Six weeks ago, he was seen by an ophthalmologist who did not note any changes of diabetic retinopathy on fundus examination. What is the next best step in managing this patient's problem?
(Multiple Choice)
4.8/5 (95)
(95) A 4-year-old boy is brought to the emergency department by his mother for vomiting and diarrhea. His mother says, "He started complaining of a stomachache after playing at the neighbor's farm, but I thought he was just hungry after playing outside all afternoon." The child subsequently had several episodes of emesis and diarrhea. His mother has also noticed that he seems to be sweating excessively and drooling. He has no medical conditions and takes no daily medications. The patient lives with his parents and uncle. His uncle has sickle cell disease, for which he takes ibuprofen and oxycodone as needed for pain crises. Temperature is 37.2 C (99 F), blood pressure is 90/60 mm Hg, pulse is 50/min, and respirations are 36/min. Pulse oximetry is 94% on room air. Physical examination shows an ill-appearing child moaning on the stretcher and clutching his abdomen. Significant diaphoresis and bilateral tearing are noted, and his pupils are constricted. Cardiac examination reveals a regular rhythm with bradycardia and no murmurs, and respiratory exam is notable for tachypnea, bilateral wheezing, and mild subcostal retractions. Oxygen via facemask is administered. Which of the following medications should also be administered?
(Multiple Choice)
4.8/5 (69)
(69) You are the current "on call physician" for your group, when you receive a call regarding one of your nursing home patients. The nurse reports that one patient has been acting strangely for the last few hours and is agitated at times. This patient is an 82-year-old female who has been in the nursing home for the last two years, and has always been very pleasant. You know her very well from your recent nursing home visit. She has a past medical history of hypertension, diabetes mellitus, osteoporosis, and Alzheimer's dementia. Her daily medications are amlodipine, metformin, calcium - vitamin D, and donepezil. You are concerned that something is not right with the patient.
The nurse calls you back in twenty minutes. She states that she gave a dose of prn (as needed) medication which was ordered by a physician before. She arranged an ambulance to transfer the patient to a nearby hospital. Her temperature is 36.7 C (98 F), blood pressure is 116/78 mmHg, pulse rate is 76/min, and respiratory rate is 18/min. She is still agitated, and she is now disoriented to place and person. She gets easily distracted, and she is having auditory hallucinations. In the hospital, her physical examination is unremarkable. What is the most appropriate next step in the management of her condition?
(Multiple Choice)
4.9/5 (77)
(77) A 67-year-old woman comes to the emergency department because of severe weakness, fatigue, and non-bloody diarrhea. She has well-controlled diabetes mellitus type 2 and bronchial asthma. The patient used to smoke 1 pack of cigarettes daily for 25 years but quit 10 years ago. She does not use alcohol or illicit drugs. Her medications include glyburide, metformin, albuterol, and fluticasone metered dose inhalers. Her temperature is 37.8 C (100 F), blood pressure is 92/61 mm Hg, pulse is 106/min, and respirations are 32/min. Examination shows no pulmonary or cardiac abnormalities on auscultation. The patient's laboratory tests show the following:  The patient's serum creatinine was 1.7 mg/dL 3 months ago. Which of the following is the most appropriate immediate next step?
 (Multiple Choice)
4.9/5 (84)
(84) A 54-year-old woman comes to the emergency department due to 12 hours of constant upper abdominal discomfort, nausea, and vomiting. The patient had a large dinner, went to bed feeling well, and was awakened by severe pain. In the past year, she has had brief similar episodes, but the pain was never this persistent. She has had no diarrhea or dysuria. Medical history includes gastroesophageal reflux, hyperlipidemia, and type 2 diabetes mellitus. The patient does not use alcohol, tobacco, or illicit drugs. Temperature is 38.3 C (100.9 F), blood pressure is 140/90 mm Hg, pulse is 110/min, and respirations are 20/min. BMI is 33.2 kg/m2. The lungs are clear to auscultation and heart sounds are normal. Abdominal examination reveals moderate tenderness in the right upper quadrant with voluntary guarding. There is no rebound tenderness. Laboratory results are as follows: 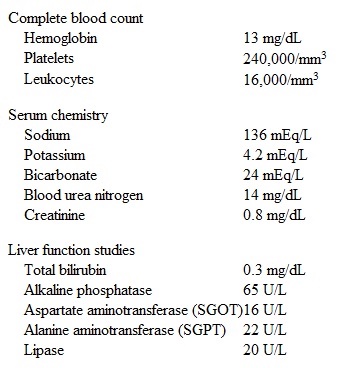 Ultrasound of the abdomen reveals several small gallstones without gallbladder wall edema or sonographic Murphy sign. The common bile duct is not enlarged. Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (70)
(70) A 27-year-old man comes to the physician with pain in his left knee, ankle, and lower back over the last week. His back feels stiff in the morning and improves with activity. Three months ago, he was treated for chlamydia proctitis with azithromycin and ceftriaxone. He also had painless sores on his glans penis, but tests for syphilis were negative at that time. On examination, he still has multiple shallow ulcers on the glans penis. The patient reports no change in appearance of the ulcers over the 3-month period. There is no urethral discharge or inguinal lymphadenopathy. The left knee and ankle joints are swollen and nontender. No redness or warmth is noted. Laboratory results are as follows:  Synovial fluid aspirated from the knee shows a white blood cell count of 4,000/mm3 with 80% neutrophils. Gram stain is negative and no pathogen is isolated on fluid culture.
The suspected pathogen is detected in this patient. Which of the following is the most appropriate therapeutic regimen?
Synovial fluid aspirated from the knee shows a white blood cell count of 4,000/mm3 with 80% neutrophils. Gram stain is negative and no pathogen is isolated on fluid culture.
The suspected pathogen is detected in this patient. Which of the following is the most appropriate therapeutic regimen? (Multiple Choice)
4.9/5 (72)
(72) A 25-year-old college student comes to the office for evaluation of a rash. His symptoms began 2 months ago on his face and progressed over time to involve his upper chest, upper back, and axillary areas. The rash is associated with mild pruritus and erythema but no pain, fever, or exudate. The patient has a history of acne during adolescence and increasing "dandruff" over the last year; his medical history is otherwise unremarkable. He takes no regular medications. The patient does not use tobacco but drinks alcohol heavily on weekends and occasionally smokes marijuana. Temperature is 36.8 C (98.2 F), blood pressure is 118/70 mm Hg, and pulse is 64/min. BMI is 26 kg/m2. Physical examination shows erythematous plaques on the eyebrows, nasal bridge, nasolabial folds, upper lip, upper chest, and back. The plaques have an indistinct margin and are covered by fine, greasy scales. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (79)
(79) A 12-year-old boy with Down syndrome is brought to the emergency department by ambulance after being in a motor vehicle collision. The patient was a restrained, rear seat passenger who required extrication from the vehicle. Temperature is 36.1 C (97 F), blood pressure is 89/60 mm Hg, pulse is 128/min, and respirations are 24/min. The patient is unconscious and has a cervical neck collar in place. Multiple lacerations to his face, arms, and abdomen are noted. A large hematoma is noted across the upper pelvis. His 17-year-old sister, who was driving the boy to music class, is present. The sister has several contusions from the airbag but is otherwise alert and oriented. She is distressed about her brother and says that he has severe impairment in intellectual functioning and requires constant supervision. The sister states that their parents are on a flight, but they are due to land in the next 30 minutes and can then be contacted by phone. The grandparents, who also live with them, do not have mobile phones but are expected to arrive in the emergency department within the next 5-10 minutes. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (72)
(72) A 32-year-old man comes to the office due to right-sided facial weakness for 3 days. He has had no fever, headache, vision disturbances, or extremity weakness or numbness but has been extremely fatigued over the past several months. The patient has no prior medical conditions and takes no medications. He drinks alcohol occasionally and does not use tobacco or illicit drugs. The patient lives in coastal California and has not traveled recently. Vital signs are within normal limits. Physical examination reveals right-sided facial droop with flattening of the nasolabial fold. He is unable to elevate the right eyebrow or close the right eye completely. Upper and lower extremity muscle strength, deep tendon reflexes, and sensation are normal on both sides. There is no neck rigidity. The lungs are clear on auscultation, and heart sounds are normal. Hepatosplenomegaly is present. The cervical, axillary, and inguinal lymph nodes are multiple, firm, and nontender. No skin rash or extremity edema is present. The joints are not swollen or tender. A week later, the patient returns to the office for follow-up. His facial weakness is improving with oral glucocorticoids, and he has had no new symptoms. Laboratory results from the previous visit are as follows: 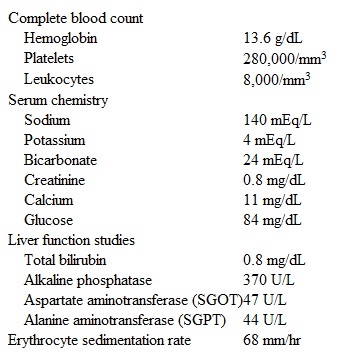 Chest x-ray reveals bilateral hilar adenopathy and interstitial infiltrates. Which of the following is most appropriate to confirm the diagnosis?
 (Multiple Choice)
4.9/5 (68)
(68) A 20-month-old girl is brought to the emergency department due to cough and fever. She had nasal congestion and a dry cough yesterday, but the symptoms are worse today. The patient developed a fever overnight and the cough is now more forceful. Her father says, "She was coughing so hard that it sounded like she couldn't breathe." Her appetite is mildly decreased, but she has been drinking water and juice frequently throughout the day. The patient's immunizations are up to date, and she takes no medications. Temperature is 38.1 C (100.6 F), pulse is 100/min, and respirations are 28/min. Physical examination demonstrates an awake, alert patient playing with a toy on her father's lap. When the examiner approaches her, she cries and has an episode of harsh, brassy coughing followed by mild inspiratory stridor. The nares are patent with clear rhinorrhea, the pharynx has no erythema or exudate, and the tympanic membranes are clear. S1 and S2 are present without murmurs. The lungs are clear to auscultation, but there are mild intercostal retractions. The abdomen is soft and nontender without organomegaly. There are no rashes or lesions. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (77)
(77) A 55-year-old man with type 2 diabetes mellitus and hypertension comes to the physician with exertional chest pain over the last 3 months that has worsened recently. He reports chest pain, occasionally accompanied by diaphoresis, after walking one block. His medications include low-dose aspirin, metoprolol, rosuvastatin, insulin detemir, and nitroglycerin as needed. Cardiac catheterization shows proximal left anterior descending artery stenosis of 90%, right coronary artery stenosis of 85%, and left circumflex artery stenosis of 75%. His left ventricular ejection fraction is 45%. His hemoglobin A1C is 7.8% and LDL cholesterol is 110 mg/dL. What is the most appropriate management for this patient?
(Multiple Choice)
5.0/5 (94)
(94) A 25-year-old woman is brought to the emergency department by her parents for evaluation of agitated and bizarre behavior over the past week. The patient abruptly stopped attending college classes a week ago. She has gotten into several loud arguments with strangers on the street. She has not slept for several days but has "tons of energy." The patient demands to leave the hospital, explaining that she must work on her novel, which "will be the greatest book of the century." The patient experienced depression at age 17 and 20 but was never treated. Physical examination is unremarkable, and a urine drug screen is negative. In the emergency department, the patient starts to pace and becomes increasingly agitated when told she cannot leave. She shouts, pounds her fists, and refuses medication. Administration of which of the following medications is the most appropriate next step in management?
(Multiple Choice)
4.9/5 (71)
(71) A 77-year-old man calls the office on a Sunday evening due to fever and cough. The patient has had a "cold" for several days but noticed worsened productive cough, fever, and chills over the last 24 hours. He says "I know it's just a cold and will get better, but my wife worries too much and made me call." The patient has a history of hypertension, chronic kidney disease, chronic obstructive pulmonary disease, and osteoarthritis. He has had to use his albuterol inhaler more frequently during the last few days due to shortness of breath. He has also been taking over-the-counter cough syrup without improvement. The patient is up to date with influenza and pneumococcal vaccines. He is a former smoker and does not use alcohol or illicit drugs. He lives with his wife, who has early-stage dementia. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (86)
(86) A 25-year-old man comes to the emergency department with pain in his right hand and wrist. A few hours earlier, he fell forward and landed on his outstretched right hand while playing football. He could not continue playing due to intolerable pain. The patient has no other medical problems and does not use tobacco, alcohol, or illicit drugs. Examination shows mild swelling in the dorsum of the right hand with preserved range of motion. Right hand grip strength is reduced. There is severe tenderness on palpation of the radial dorsal aspect of the wrist.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5 (71)
(71) A 55-year-old man comes to the office for a medical evaluation for life insurance. The patient feels well and has no chronic health issues. He takes no prescription medications but recently began taking over-the-counter supplements, which have improved his energy level. The patient has smoked a pack of cigarettes a day for 30 years but is trying to cut down. He drinks alcohol occasionally and does not use illicit drugs. Family history is notable for non-Hodgkin lymphoma in his brother. Temperature is 37 C (98.6 F), blood pressure is 140/90 mm Hg, pulse is 80/min, and oxygen saturation is 99% on ambient air. The patient's complexion is ruddy. There are no skin rashes or mucosal lesions. The lungs are clear to auscultation and heart sounds are normal. The abdomen is soft and nontender with no hepatosplenomegaly. Laboratory results are as follows:
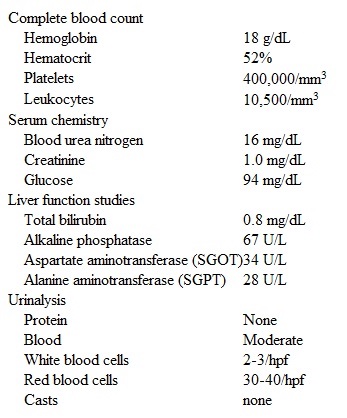 Imaging studies reveal a complex cystic mass with enhancing soft-tissue components and thick, irregular septa in the right kidney. Which of the following is the best intervention for this patient's current renal condition?
 (Multiple Choice)
4.9/5 (87)
(87) A 16-year-old girl comes to the office for an annual checkup, accompanied by her mother. The patient is a junior in high school and lives with her parents and 2 younger siblings. During the visit, she discloses that she has had sexual intercourse several times with a boy in her class. The patient believes she may be in love and says that the sex is consensual. Her partner is using condoms. When the physician inquires if her parents are aware that she is sexually active, the patient says, "I would never tell them. They are totally against premarital sex. They don't even allow me to date. They would be furious if they knew." Physical examination is normal and urine pregnancy test is negative. Routine laboratory screening for common sexually transmitted diseases is performed, and the patient is educated about safe sex and contraceptive options. The patient asks the physician to say nothing to her parents.
Which of the following is the most appropriate response to the patient?
(Multiple Choice)
4.8/5 (81)
(81) As part of a study on treatment of uncomplicated cellulitis, outpatients age >12 seeking care at the emergency department with cellulitis and no wound, purulent drainage, or abscess were randomly assigned to either cephalexin plus trimethoprim-sulfamethoxazole for 7 days (n = 85) or cephalexin plus placebo for 7 days (n = 87). The primary outcome was clinical cure, defined as absence of fever and more than minimal erythema, swelling, or tenderness (days 14-21). A total of 24 patients in the cephalexin plus trimethoprim-sulfamethoxazole group and 18 patients in the cephalexin plus placebo group did not complete treatment as prescribed or failed to complete the test-of-clinical-cure visit; they were categorized as noncompliant patients. The principal investigator of the study wanted to conduct a per-protocol analysis of the data. Which of the following describes how the data pertaining to noncompliance should be treated to conduct such an analysis?
(Multiple Choice)
4.8/5 (81)
(81) Showing 701 - 720 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)