



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


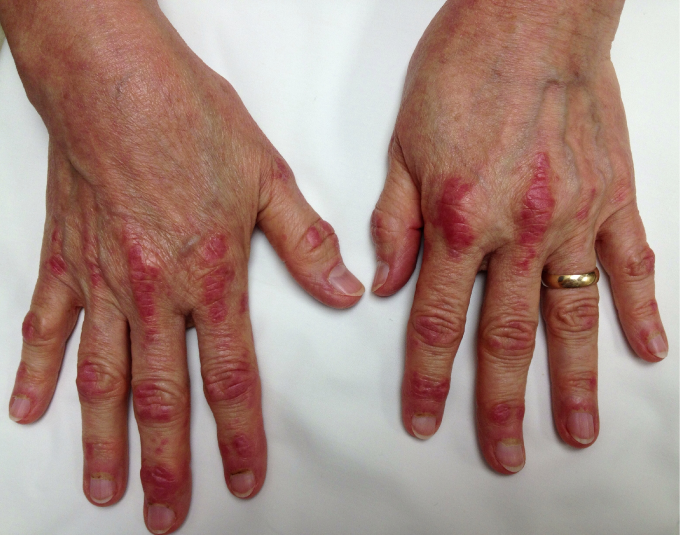
A 55-year-old woman comes to the physician due to a 2-month history of malaise, mild fever, and difficulty climbing stairs and rising from a chair. She has unintentionally lost 9.1 kg (20.1 lb) over this period. The patient has hypertension and asthma. Medications include amlodipine, as-needed albuterol, and inhaled glucocorticoids during winter. The patient does not smoke or use illicit drugs. She worked for 20 years supervising cotton processing in a textile factory but has been working as a secretary for the past 10 years. Temperature is 37.8 C (100 F), blood pressure is 120/70 mm Hg, pulse is 82/min, and respirations are 12/min. Chest examination reveals clear lung fields and normal S1 and S2. The patient has bilateral proximal upper and lower extremity weakness with normal reflexes. Plantar reflexes are down-going bilaterally. Violaceous papules and plaques are seen on the dorsum of both hands, as shown in the image below:
 Kidney and liver function are within normal limits. Creatine kinase level is 1,200 IU/L.
Which of the following conditions is most likely associated with this patient's disease?
Kidney and liver function are within normal limits. Creatine kinase level is 1,200 IU/L.
Which of the following conditions is most likely associated with this patient's disease? (Multiple Choice)
4.9/5  (84)
(84) A 38-year-old woman with a history of bipolar I disorder comes to the office due to low energy. The patient felt well until 4 months ago when she noticed she was reacting slowly at work and was reluctant to meet with friends on weekends due to fatigue. She is afraid she is becoming depressed again. The patient says, "I am so discouraged. I really felt so much better on my medication, and now I feel like I'm slipping." She has a history of multiple hospitalizations for manic and depressive episodes since late adolescence. She attempted suicide at age 20 by taking an overdose of aspirin. The patient was previously treated with valproate and olanzapine and has been taking lithium for the past year. Her other medical issues include hypertension and allergic rhinitis, for which she takes hydrochlorothiazide and loratadine, respectively. On review of systems, the patient reports fatigue and difficulty concentrating over the past few weeks. Mental status examination shows a tired appearance and sad affect. She has no suicidal ideation. Physical examination shows no abnormalities. The patient's blood lithium level is 0.9 mEq/L (range: 0.6-1.2 mmol/L). Other laboratory results are as follows: 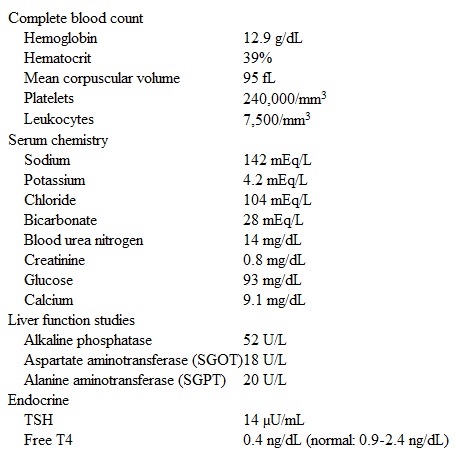 Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (73)
(73) A 9-year-old boy is brought to the emergency department by his babysitter after "passing out" at home. The babysitter says, "He was playing video games and I noticed his eyes started blinking a lot. He did not respond when I called his name and then he slumped to the floor. He has been very sleepy since waking up." The boy had been well, with no fevers, upper respiratory symptoms, or vomiting. He takes carbamazepine for epilepsy and has not had a seizure in years. He also takes loratadine as needed for allergic rhinitis. The patient has no known drug allergies and his immunizations are up to date. It has been a stressful time for him as his parents are going through a divorce and he has been splitting time between 2 homes. The boy also just returned from a week-long stay at his grandparents' house. Vital signs are normal. On physical examination, the patient is drowsy but able to answer questions and follow directions. Pupils are 4 mm bilaterally and equally reactive to light. Cardiopulmonary examination is normal. The abdomen is soft and nontender without hepatosplenomegaly. Muscle tone and strength are normal in all extremities. Plantar reflexes are downgoing. There are no skin rashes or lesions. Which of the following is the best next step in evaluation of this patient?
(Multiple Choice)
4.9/5 (74)
(74) A 17-year-old girl is brought to an urgent care center for sunburn. She was jogging outside for an hour today and subsequently developed redness and pain on the exposed portion of her arms and face. The patient says, "It wasn't even that sunny today. I've been outside for a lot longer than this and have never had a sunburn this bad." Her medical history includes acne vulgaris for which she was prescribed a topical and an oral medication, neither of which she can remember by name. She does not take any other medications and has no allergies. The patient is a long-distance runner for her high school track team. She lives with her father, who has dyslipidemia. Physical examination shows numerous comedones, papules, and pustules on her face and chest. Confluent areas of erythema, warmth, and edema are present on the patient's face and upper extremities. Her left arm is shown in the image below. 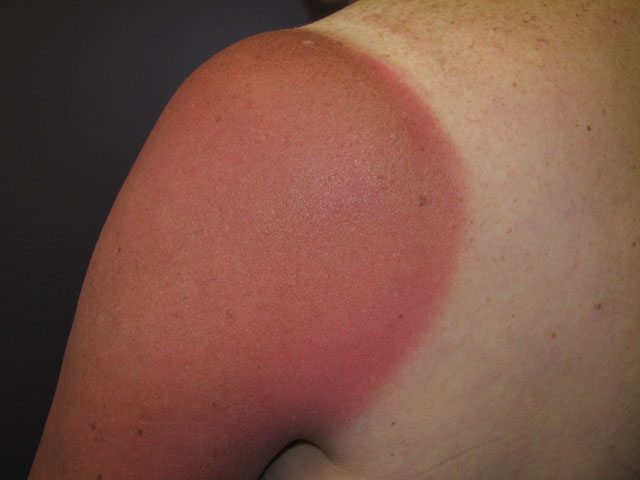 Over the next several months, the patient consistently uses a topical retinoid, a topical antibiotic, and an oral antibiotic. She is also prescribed a daily oral contraceptive as adjunctive therapy for acne. Six months later, the patient returns to the office for a follow-up appointment. She says she is not sexually active, and review of systems is positive for occasional feelings of anxiety with school workload. Current BMI is 19 kg/m2. Blood pressure is 90/60 mm Hg, and pulse is 68/min. Examination shows oily skin on the forehead, nose, and cheeks. Inflammatory and nodular acne is present on the face, back, and upper arms. There is also scarring on the forehead. The patient has no hirsutism or acanthosis nigricans. Urine β-hCG is negative. The patient desires the most effective treatment, and appropriate pharmacotherapy is discussed. Which of the following should also be discussed prior to prescribing the new medication?
 (Multiple Choice)
4.9/5 (91)
(91) A 62 year-old Caucasian man is brought to the emergency department (ED) with complaints of nausea, vomiting, crampy lower abdominal pain and distension over the past two days. His last bowel movement was four days ago. His wife tells you that he has been unable to eat anything for the past 24 hours due to repeated episodes of vomiting. His past medical history includes hypertension, hyperlipidemia, and peptic ulcer disease. His current medications include thiazide diuretics, atorvastatin, and pantoprazole. He had an appendectomy at the age of 36 years, and surgical repair of a perforated peptic ulcer 8 years ago. His temperature is 36.7C (98F), blood pressure is 124/62 mmHg, respiratory rate is 22/min and heart rate is 96/min. His mucous membranes are dry. Abdominal examination reveals a distended abdomen with increased bowel sounds, a tympanic note throughout the abdomen, and tenderness on deep palpation over the lower abdomen. The rest of the examination is unremarkable. His initial blood work reveals marked electrolyte abnormalities. An obstruction series done in the ED reveals multiple air fluid levels in the small intestine consistent with a diagnosis of small bowel obstruction. There is some air seen in the distal colon. What is the most appropriate next step in the management of this patient?
(Multiple Choice)
4.8/5 (86)
(86) A 22-year-old woman comes to the office to discuss initiating oral contraception. She has been sexually active with the same partner for the last year and has been using condoms but would like a more reliable method of contraception. The patient has a 4-year history of primary hypothyroidism, which has been well controlled on 125 µg/day of levothyroxine. Her most recent serum TSH was within normal limits. She has no other chronic medical conditions and no previous surgeries. The patient does not use tobacco, alcohol, or illicit drugs. Family history is significant for breast cancer in her mother diagnosed at age 52 and a sister who has type 1 diabetes mellitus. Blood pressure is 110/76 mm Hg and pulse is 78/min. BMI is 24 kg/m2. There is no thyromegaly, and the remainder of the physical examination is normal. The patient states that her best friend noted an improvement in her acne after starting an oral contraceptive, and she would like to take the same type of pill. Which of the following is the most accurate statement regarding contraception in this patient?
(Multiple Choice)
5.0/5 (78)
(78) A 36-year-old man comes to the office due to frequent "loose stools" for the past 10 months. The patient describes stools that are large in volume, liquid to semisolid, occurring up to 3-4 times a day, and often foul-smelling. He also reports excessive flatulence and occasional nausea and abdominal cramping. The patient says he may have lost some weight because his clothes are much looser than before. He has no prior medical problems and takes no medications. Family history is notable for hypertension and coronary artery disease in his father. The patient immigrated to the United States from Italy with his family when he was 2 years old and has not traveled out of the country since then. He does not use tobacco or illicit drugs and drinks alcohol occasionally. The patient works in a family-owned restaurant and has had no sick contacts. He consumes a balanced diet and notes no specific association of diarrhea to food. The patient has been in a monogamous relationship with his wife for the past 10 years. Temperature is 36.6 C (97.9 F), blood pressure is 130/86 mm Hg, and pulse is 72/min. Weight is 63.5 kg (140 lb). The sclerae are anicteric, and mucous membranes are moist without any lesions. Cardiopulmonary examination is unremarkable. The abdomen is soft, nondistended, and nontender, with no organomegaly. Bowel sounds are increased. Rectal examination shows no masses or tenderness and an empty rectal vault. Stool occult blood testing is negative. Samples for blood count, erythrocyte sedimentation rate, TSH, and serum electrolytes are obtained.
Which of the following additional interventions is most appropriate in management of this patient's diarrhea?
(Multiple Choice)
4.9/5 (64)
(64) A Schirmer test confirms inadequate tear production in this patient and anti-Ro/SSA antibodies are positive. Which of the following is the most likely explanation for this patient's neck mass?
(Multiple Choice)
4.7/5 (72)
(72) An 8-year-old girl is brought to the emergency department by her mother for evaluation of blurry vision. The patient reports that she woke up this morning with a sudden onset of blurry vision. Her mother states, "She has worn thick glasses since age 2, but this morning she said that everything was blurry in her left eye, even with her glasses on." There is no associated erythema or discharge. The patient does not recall any trauma. The girl has no chronic medical conditions and has had no surgeries. She is an honor roll student in the 3rd grade. The patient lives with her mother, and her father left when she was an infant. The mother's medical history is unremarkable but she says, "I think her father had a similar problem when he was younger and had a weak heart." The patient is at the 50th and >95th percentiles for weight and height, respectively. She is alert and in no distress. The right pupil is 4 mm and briskly reactive; the left pupil is 1 mm. Bilateral globes appear intact with no conjunctival injection. Extraocular eye movements are intact bilaterally and visual fields are full to confrontation bilaterally. A dilated direct ophthalmoscopic examination followed by a slit-lamp examination of the left eye reveals the following: 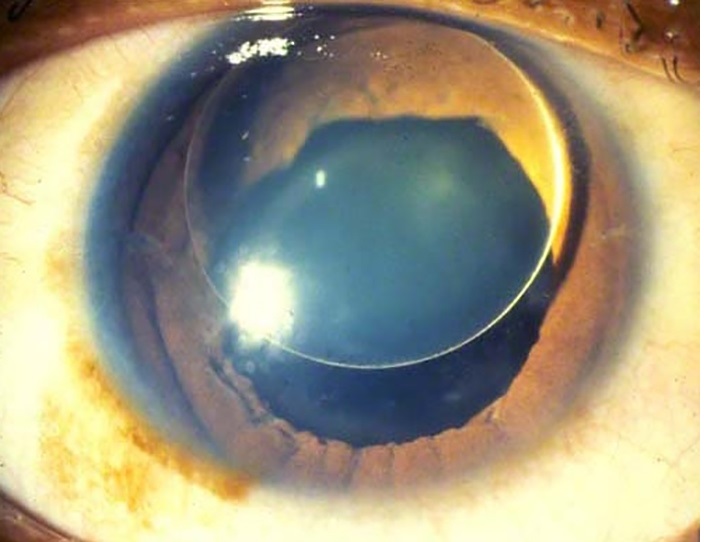 Which of the following conditions is this patient at greatest risk of developing?
 (Multiple Choice)
4.9/5 (88)
(88) A randomized, parallel-group, controlled clinical trial evaluates the effectiveness of an anti-inflammatory intervention as treatment for neuropathic pain following spinal cord injury. Participants with varying levels and severities of spinal cord injury are randomly assigned to either a 24-week, anti-inflammatory diet treatment group or a control group. Primary outcomes consist of changes in pain scores and markers of inflammation at 6 months. Preliminary analyses reveal a significant reduction in pain scores in the treatment group from baseline to 6 months (p = 0.03). There was a significant reduction in pain scores among nonobese subjects (p = 0.01) and a nonsignificant increase in pain scores among obese subjects (p = 0.06). Which of the following is the best explanation for these differences in findings between obese and nonobese subjects?
(Multiple Choice)
4.7/5 (84)
(84) A 19-year-old woman comes to the student health center after a sexual assault 2 days ago. She has no fevers, chills, abdominal pain, or abnormal vaginal discharge. The patient was sexually assaulted by a man she has seen multiple times, who also attends the university. Menses are regular and occur every 29 days; her last menstrual period was 2 weeks ago. She has no known medical conditions and has had no surgeries. The patient takes no medications and has no drug allergies. She smokes cigarettes and drinks alcohol socially. There is no family history of any illness. She is sexually active with a long-term male partner, and they use condoms for contraception. The patient has no history of sexually transmitted infections. Temperature is 36.7 C (98 F), blood pressure is 110/70 mm Hg, and pulse is 65/min. BMI is 20 kg/m2. The abdomen is soft and nontender, with no palpable masses. Bruises and abrasions are present over the inner thighs, perineum, and vulva. Pelvic examination reveals a friable cervix that bleeds easily on contact. The vaginal mucosa is erythematous with no evidence of hematoma. The uterus is small and nontender on bimanual examination; no adnexal masses are palpated. Microscopy shows an abundance of polymorphonuclear leukocytes. Urine pregnancy test is negative. The patient undergoes a sexually transmitted infection workup, including viral hepatitis, HIV, syphilis, chlamydia, and gonorrhea. She completed a hepatitis B vaccination series prior to college, and all other vaccines are up to date. Based on her history and examination, which of the following medications should be administered?
(Multiple Choice)
5.0/5 (81)
(81) A 70-year-old man comes to the hospital due to fever, lethargy, productive cough, and shortness of breath. He has type 2 diabetes mellitus, hypertension, paroxysmal atrial fibrillation, and peripheral vascular disease. His medications include warfarin, sotalol, insulin detemir, and lisinopril. Chest x-ray shows infiltrates in the left lung base. He is admitted and treated with azithromycin, ceftriaxone, and oxygen therapy.
On the second day of hospitalization, he has 2 episodes of loss of consciousness associated with seizure-like activity. The telemetry strips during one of these episodes is shown in the exhibit. 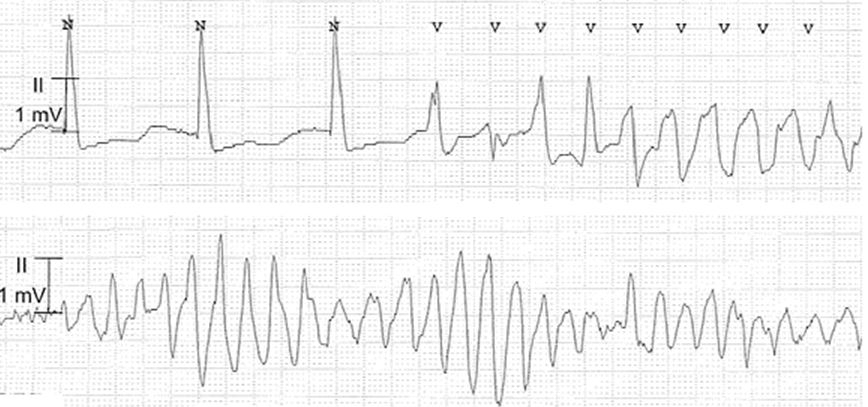 Which of the following is most likely to provoke a recurrent event in this patient?
 (Multiple Choice)
4.8/5 (85)
(85) A 22-year-old woman comes to the office for an annual physical examination. The patient, who has no concerns at the visit, has regular, monthly menses with 3-4 days of light bleeding, and no palpable breast masses, abnormal vaginal discharge, dysuria, or changes in bowel function. She has no chronic medical conditions or previous surgeries. The patient has engaged in sexual activities only with women and has had 3 lifetime partners. Sexually transmitted infection testing a year ago was negative. She has not received a human papillomavirus vaccination. The patient does not use tobacco, alcohol, or illicit drugs. She is finishing her last year of college and plans to attend graduate school. Vitals signs are stable. BMI is 26 kg/m2. Physical examination is unremarkable. She asks for counseling for herself and her partner regarding the health risks of their sexual orientation. Which of the following is the most appropriate statement regarding general health-related issues for this patient?
(Multiple Choice)
4.8/5 (68)
(68) A 5-year-old boy is brought to the emergency department with severe leg pain that started 6 hours earlier. His mother says that their heating system broke last night so she "tried to keep him warm with lots of blankets." The patient was given ibuprofen and oxycodone at home without relief of pain. He played outside with his brother yesterday but did not experience any trauma or injury. He has not had fever, cough, vomiting, or rash. Medical history includes mild persistent asthma and sickle cell disease, and he has been hospitalized once for a vaso-occlusive pain episode. Temperature is 37.2 C (99 F), blood pressure is 100/62 mm Hg, pulse is 150/min, and respirations are 20/min. Physical examination shows a young child lying in bed in significant discomfort, crying and holding his left leg. Mucous membranes are moist and capillary refill is <2 seconds. The lungs are clear to auscultation, and the abdomen is soft, nontender, and nondistended without organomegaly. The left anterior calf is markedly tender to palpation but does not have erythema, warmth, or swelling. A peripheral intravenous line is inserted, and a complete blood count is drawn.
What is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (83)
(83) A 52-year-old woman is brought to the emergency department due to a day of fever, lethargy, and skin lesions. She is currently undergoing combination chemotherapy for diffuse large B-cell lymphoma, and her last treatment was 10 days ago. Yesterday, the patient developed a red rash on her right thigh. Within a few hours, a pustule formed in the center of the lesion, rapidly evolved into a dark bulla, and then ruptured and formed an ulcer. A second, similar skin lesion arose shortly thereafter. The patient has also had fever and chills and progressive weakness and lethargy. Temperature is 38.9 C (102 F), blood pressure is 110/60 mm Hg, and pulse is 106/min. She has an implanted central venous catheter with a subcutaneous port; the overlying skin is not erythematous or tender. Cardiopulmonary auscultation reveals clear lung fields and no cardiac murmurs. The abdomen is soft and nontender. Skin examination shows a nontender, necrotic ulcer with an erythematous rim and yellow-green, purulent exudate on the right thigh. There is another lesion with a hemorrhagic dark-bluish bulla and surrounding erythematous, indurated skin. Leukocyte count is 800/mm3 with 10% neutrophils.
Which of the following is the most likely cause of this patient's skin lesions?
(Multiple Choice)
4.9/5 (90)
(90) A 79-year-old man is brought to the office by his daughter. The patient has been having increasing difficulty caring for himself over the last 2 years. He is now dependent on his daughter for meal preparation, shopping, and cleaning. He will frequently go a week without bathing and often has difficulty dressing himself appropriately. The patient sometimes grows frustrated and shouts at his daughter but has never been physically violent. On direct questioning, he states that he feels fine, does not see any reason for coming to the office, and is quite suspicious of his daughter's motives. The patient has lived alone since his wife died 5 years ago. He has hypertension, osteoarthritis, and a history of remitted major depressive disorder. Medications include hydrochlorothiazide and acetaminophen as needed. Neurologic examination is nonfocal. The patient scores 20 out of 30 on the Montreal Cognitive Assessment. Neuroimaging studies reveal diffuse cortical atrophy. The laboratory workup is unremarkable. Which of the following is the most appropriate next step in pharmacotherapy?
(Multiple Choice)
4.8/5 (89)
(89) A 74-year-old woman comes to the emergency department because of an episode of syncope. She has generalized weakness, fever, nausea, dysuria, and urinary frequency. She has a 3-day history of decreased oral intake. She lives alone at home. She does not use tobacco, alcohol, or drugs. Her medications include aspirin, lisinopril, and ibuprofen. Her blood pressure is 102/45 mm Hg and pulse is 48/min. Examination shows dry mucus membranes. The abdomen is mildly tender, soft, and non-distended. Cardiac and lung exam show no abnormalities. The lab studies show:  An ECG shows a rate of 48/min, a regular rhythm, wide QRS complexes, and absent P waves. Which of the following is the most appropriate next step in management?
 (Multiple Choice)
4.8/5 (84)
(84) A 44-year-old man comes to the urgent care clinic due to palpitations. The current episode started 2 hours ago and feels like "fluttering in the chest." He has no chest pain, orthopnea, dizziness, syncope, or shortness of breath. The patient has had similar episodes in the past 6 months, but they usually last less than an hour and resolve spontaneously. He cannot identify any clear-cut precipitating factor for these episodes. He has a history of migraines and kidney stones. The patient does not use tobacco, alcohol, or illicit drugs. His family history is significant for liver cancer and renal failure. He works in an office and his lifestyle is mainly sedentary. On initial evaluation, he appears comfortable. Blood pressure is 124/82 mm Hg and pulse is 122/min. Oxygen saturation is 99% on room air. BMI is 31 kg/m2. Cardiac auscultation reveals no murmurs. The patient's lungs are clear to auscultation and there is no peripheral edema. ECG shows atrial fibrillation with a rapid ventricular response. Complete blood count, basic metabolic panel, TSH level, and chest x-ray are normal. A transthoracic echocardiogram shows normal left ventricular size and function, mild enlargement of the left atrium, and no valvular abnormalities. The patient is given oral metoprolol and reports improvement of his symptoms after 2 hours. Repeat ECG shows normal sinus rhythm with a ventricular rate of 77/min at rest. There are no repolarization abnormalities and his QTc interval is 410 msec. In addition to oral metoprolol, which of the following is the most appropriate therapy for this patient?
(Multiple Choice)
4.8/5 (78)
(78) A 48-year-old woman comes to the office due to a recurrent rash. Six months ago, a rash developed on her legs that she describes as "red patches with raised areas." The rash worsened that night with intense itching that disrupted her sleep. It spontaneously resolved over the next day. Since then, she has had repeated episodes of similar symptoms on her arms, legs, and back, each lasting 8-12 hours and occurring nearly every 2-3 weeks. She reports no trauma, insect bites, travel history, sick contacts, or changes in weight. Medical history is notable for hypertension treated with lisinopril. She does not use tobacco, alcohol, or illicit drugs. Temperature is 36.1 C (97 F), blood pressure is 138/77 mm Hg, and pulse is 78/min. Physical examination is within normal limits. The patient brings a photo of the rash, shown in the image below, from her most recent episode 2 days ago. Complete blood count, urinalysis, erythrocyte sedimentation rate, and liver function studies are within normal limits. 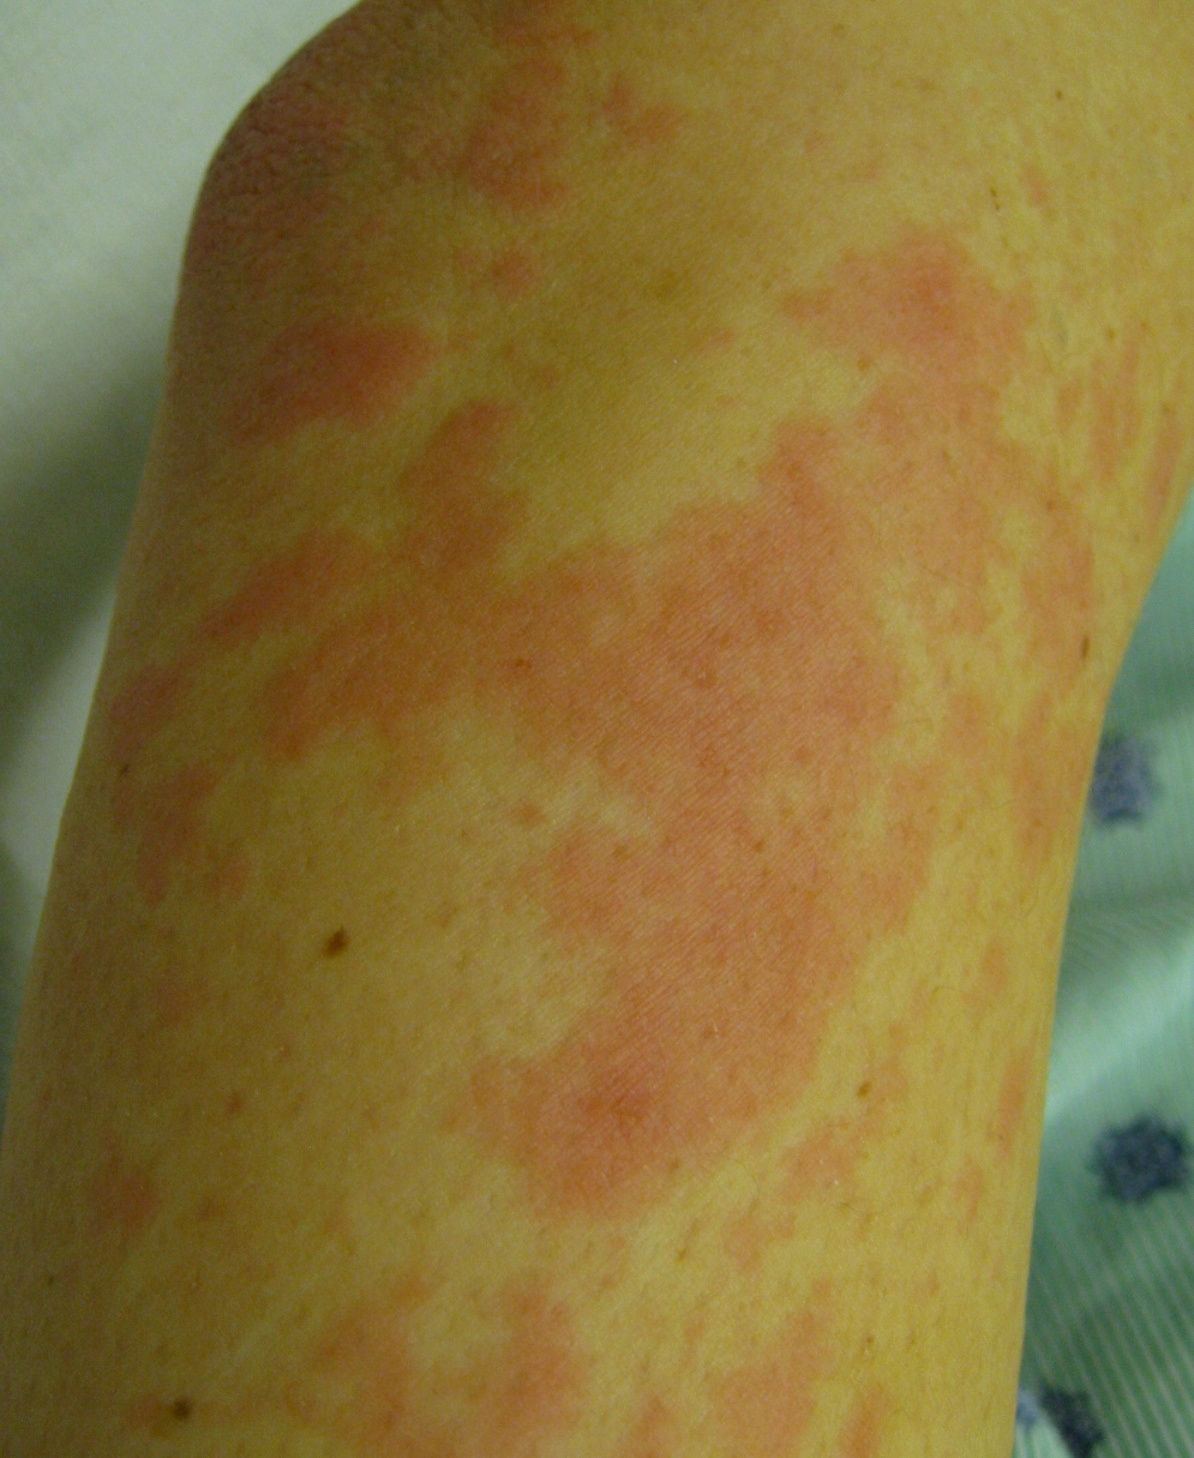 Which of the following is the best next step in management of this patient's condition?
 (Multiple Choice)
4.8/5 (80)
(80) A 68-year-old woman comes to the emergency department due to a month-long history of increasing palpitations. She has had no associated chest pain or shortness of breath but has experienced unusual fatigability. The patient has also noted a 4-kg (8.8-lb) weight loss on her home scale and has been waking with increasing frequency at night to urinate. She was diagnosed with osteopenia on bone densitometry at age 65; she increased her intake of "milk, yogurt, cheese, and other foods with lots of calcium" and started a vitamin D supplement, but repeat DXA 2 months ago revealed a significant interval decline in bone density. The patient's medical history is otherwise unremarkable, and she does not use tobacco, alcohol, or illicit drugs. Her mother died of breast cancer at age 62 and her father died in a motor vehicle collision at age 40. Temperature is 36.7 C (98 F), blood pressure is 151/68 mm Hg, pulse is 122/min, and respirations are 16/min. The thyroid gland is diffusely enlarged and nontender. Lid lag is noted on eye examination. The lungs are clear to auscultation. The heart has an irregularly irregular tachycardia with a variable intensity of S1. Laboratory results are as follows:  Which of the following should be addressed next in treatment of this patient's condition?
 (Multiple Choice)
4.9/5 (68)
(68) Showing 741 - 760 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)