



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


A 28-year-old man comes to the office for a health maintenance visit. He has no history of serious illness but reports periodic headaches over the last several years that often respond to acetaminophen. Occasionally the headaches are severe enough to necessitate taking a sick day from work. He cannot recall specific triggers but notes that the headaches are usually unilateral. The patient does not use tobacco or illicit drugs. He drinks alcohol socially and 2-3 cups of coffee daily. He is a software engineer and often works at a computer 10-12 hours a day. His sister has a history of migraines. Vital signs are within normal limits. Physical examination, including neurological examination, is normal. The patient comes to the emergency department at 1 AM later that night due to unrelenting headache. He was awakened 2 hours prior by severe, sharp, periorbital pain on the left side of his head. He also has had nausea and watering from the left eye. The patient took ibuprofen and acetaminophen but experienced no relief. Temperature is 37 C (98.6 F), blood pressure is 140/90 mm Hg, pulse is 92/min, and respirations are 16/min. Pulse oximetry shows 98% while breathing ambient air. He appears in pain and is restless. Physical examination shows mild ptosis and miosis of the left eye. There is clear discharge from the left nostril. He has no other focal neurological deficits, and the remainder of the physical examination is normal. Which of the following is the most appropriate intervention at this time?
(Multiple Choice)
4.8/5  (95)
(95) A 1-month-old boy is brought to clinic by his mother due to concerns about his breathing. The mother states that over the past week she has noticed several episodes in which "he just stops breathing and then takes a lot of quick breaths." She adds, "He does it many times within a minute and then seems to breathe normally again. It really scares me." The infant has had no cyanosis, coughing, choking, fevers, or abnormal eye or limb movements. He is exclusively breastfed and is given vitamin D daily. The infant was born at 36 weeks gestation via normal spontaneous vaginal delivery after preterm premature rupture of membranes. He spent a week in the neonatal intensive care unit for temperature instability and feeding difficulties, and was discharged with no remaining medical issues. Family history is notable for a maternal cousin with epilepsy. Temperature is 36.7 C (98 F), blood pressure is 80/50 mm Hg, pulse is 132/min, and respirations are 44/min. Pulse oximetry is 99% on room air. The patient is tracking along the 30th percentiles for weight, length, and head circumference. Physical examination shows a well-nourished infant sleeping in his mother's arms. The heart has a regular rate and rhythm without murmurs, and the lungs are clear to auscultation without apnea, tachypnea, or increased work of breathing. He has appropriate tone and intact suck, grasp, and Moro reflexes. Plantar reflexes show upgoing toes bilaterally. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.7/5 (75)
(75) A 15-month-old boy is brought to the office for a well-child visit. His parents are concerned that he is not yet walking. He can pull himself up to stand and take steps while holding on to furniture but has not yet taken any steps unassisted. The patient says 5 words and can follow simple commands, such as "Clap your hands!" or "Wave bye-bye!" He is also able to pick up small items and food with his thumb and pointer finger and tries to use a spoon when feeding. The boy is up to date with all vaccinations. He has no known allergies and takes no medications. He was born via uncomplicated vaginal delivery at 37 weeks gestation. The patient was breastfed exclusively, with vitamin D supplementation, until age 6 months and has since had a varied diet. Gross motor milestones include rolling over at age 6 months and sitting unassisted at age 8 months. Height and weight are at the 40th percentile. Physical examination shows a nondysmorphic and active boy. He pulls himself up to stand and cruises around the examination room while holding on to chairs or his mother. During the examination, he cries and clings to his mother. The remainder of the examination is unremarkable. What is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (69)
(69) A 48-year-old man comes to the office due to progressive weakness for the past 2 months. The patient has experienced difficulty climbing stairs, especially when carrying heavy items such as groceries, and his symptoms have become progressively worse. He also reports occasional fevers, but no significant pain in the muscles or joints. The patient has had no diplopia, dyspnea, dysphagia, abdominal pain, or heat or cold intolerance. He has a history of hypertension and hyperlipidemia, for which he has taken losartan and atorvastatin, respectively, for the last 4 years. The patient does not use tobacco, alcohol, or illicit drugs. Temperature is 37.1 C (98.8 F), blood pressure is 132/84 mm Hg, pulse is 72/min, and respirations are 14/min. He has no scleral icterus. Cardiopulmonary examination is normal. The abdomen is soft and nontender with no hepatosplenomegaly. Muscle strength is 3/5 in the deltoids and hip flexors but is otherwise normal. Deep tendon reflexes are normal and symmetric, and sensations to pain and light touch are intact. There is mild muscle tenderness and some of the small joints of both hands are tender to palpation without any swelling or erythema. He has no skin rash. Laboratory results are as follows:
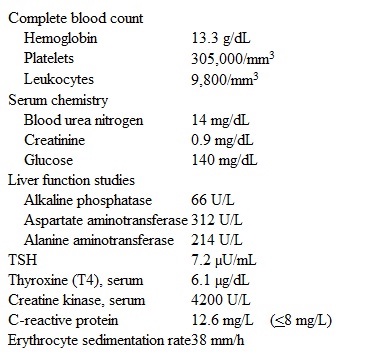 Which of the following is the most likely cause of this patient's current symptoms?
 (Multiple Choice)
4.8/5 (86)
(86) A 9-month-old boy is brought to the office for a well-child visit. His parents are concerned that he has not been meeting milestones as quickly as his older brother. The patient has not started crawling and requires support from his parents to sit up. His mother states, "I think his lack of crawling is because he cannot roll over from his back to his stomach." The parents say that he sleeps well through the night and is a happy infant overall. The patient spits up occasionally after bottle feedings but less so than when he was a newborn. His diet is still primarily infant formula, but he has been self-feeding solid foods since age 6 months with no gagging or coughing. The patient was born at 35 weeks gestation via an uncomplicated delivery. Due to gestational age, the infant was observed in the neonatal intensive care unit; however, his stay was uneventful, and he was discharged from the hospital a week after delivery. Family history is negative for developmental delays or metabolic disorders; his 3-year-old brother is healthy with no chronic medical conditions. Height, weight, and head circumference are at the 75th percentile. The infant is alert and smiling and has no dysmorphic facial features. The anterior fontanelle is open and flat, and gaze is conjugate with no nystagmus. He reaches for small toys and laughs when they rattle. Musculoskeletal examination reveals increased tone in the bilateral lower extremities. When the infant is suspended by the axillae, his legs maintain a scissoring posture. Patellar reflexes are 3+. Sustained clonus is also noted in the ankles bilaterally. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (82)
(82) A 20-year-old woman, gravida 1 para 0, comes to the emergency department due to severe headache and right-sided weakness. She has had a constant, dull headache for the past week. The pain is greatest when she awakens in the morning. Coughing or straining worsens the pain and causes transient blurry vision. When the patient awoke this morning she was unable to stand due to right leg weakness, and she had difficulty calling for help because she could not pick up the phone with her right hand. She has no prior medical issues. The patient is at 24 weeks gestation and had nausea and vomiting during the first trimester, but she has had no other pregnancy-related complications. Her only medication is a daily prenatal multivitamin. She stopped smoking cigarettes and drinking alcohol once she learned she was pregnant, and she has no history of illicit drug use. Her sister has a history of pulmonary embolism. Temperature is 36.7 C (98 F), blood pressure is 120/76 mm Hg, pulse is 80/min and regular, and respirations are 16/min. Bilateral pupils are equal, round, and reactive. Funduscopy shows bilateral papilledema. Neurologic examination is notable for right-sided motor weakness with pronator drift and Babinski sign on the right. Sensation is intact, and she has normal mentation. Meningeal signs are absent. Neuroimaging reveals intraluminal thrombus in the sagittal sinus and a small area of intraparenchymal hemorrhage. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (77)
(77) An 86-year-old woman comes to the office due to a vaginal bulge and difficulty urinating. The patient first noticed the bulge several years ago but did not seek care. Over the last few months, as the bulge has enlarged, she has experienced increasing pelvic pressure. In addition, she now has to manually elevate the bulge to urinate. The patient has no vaginal bleeding or difficulty with defecation. She has chronic obstructive pulmonary disease managed with an inhaled combined long-acting beta agonist and corticosteroid. She had 2 vaginal deliveries in her early 20s; the second was complicated by a fourth-degree perineal laceration. The patient has a 50-pack-year smoking history, but quit 15 years ago; she does not use alcohol or illicit drugs. Blood pressure is 150/90 mm Hg, pulse is 78/min, respirations are 20/min, and pulse oximetry is 91% on room air. BMI is 34 kg/m2. Auscultation of the lungs reveals decreased breath sounds bilaterally. Pelvic examination reveals anterior vaginal wall prolapse and protrusion of the cervix through the vaginal introitus. During the examination, the uterus is elevated and the prolapse is reduced; the patient is asked to cough and no leakage of urine is observed. Post-void residual urine volume is 40 mL. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (81)
(81) A 70-year-old woman comes to the office due to back pain, fatigue, and inability to carry out her daily work. The pain began 6 months ago and has slowly intensified. The patient had a hip fracture 3 months ago but has no other medical conditions. She is a lifetime nonsmoker and drinks alcohol on social occasions. She currently takes no medications. The patient has no extremity weakness or paresthesia. She has mild constipation; urination is normal. Initial laboratory results are as follows:  Dipstick urinalysis is normal. The patient undergoes a bone marrow biopsy, which shows 20% plasma cells. While discussing the options for further investigation and treatment, the patient says that, since her initial visit, she has had pain in her left shoulder and right flank after a minor fall. Which of the following is the best next step in management?
 (Multiple Choice)
4.9/5 (72)
(72) A 25-year-old man is brought to the emergency department by ambulance after ingesting toilet bowl cleaner an hour ago. The patient has a history of schizoaffective disorder and stopped taking his medication a week ago. His family suspected deterioration of his condition when he stopped returning their calls. They came to his house with emergency medical personnel to bring him to the hospital, but he said he "had to maintain order in the solar system" and would rather die than leave. The patient then consumed toilet bowl cleaner for a few moments before he started coughing and was subsequently restrained. He has no other medical conditions. The patient currently reports burning sensation in his throat, chest, and upper abdomen. His voice is hoarse and saliva runs out of his mouth while speaking. Temperature is 36.8 C (98.2 F), blood pressure is 148/75, pulse is 104/min, and respirations are 28/min. Pulse oximetry shows 93% on room air. The oropharynx is erythematous and edematous with gray exudates. Lung and heart sounds are normal. The abdomen is soft, nondistended, and tender in the epigastric region. There is no guarding or rebound tenderness. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
5.0/5 (75)
(75) A 34-year-old, obese, Caucasian male presents to your office with an abnormal sensation over his right thigh. He says, "It gets numb, and sometimes I feel burning over my thigh." He denies any back pain, muscle weakness, or abnormal sensation below the knee. His past medical history is insignificant. He smokes two packs of cigarettes and consumes 1-2 bottles of beer daily. He is a construction worker. He frequently works in a squatting position. Physical examination reveals an area of decreased sensation over the right anterolateral thigh. There is no muscle weakness. Deep tendon reflexes are symmetrical.
Which of the following is the most appropriate next step in the management of this patient?
(Multiple Choice)
4.7/5 (85)
(85) A randomized controlled study of chronically sleep-deprived (<6.5 hr per night), morbidly obese subjects examined whether sleep extension is associated with weight loss and metabolic and endocrinal improvements. The intervention consisted of education regarding sleep hygiene and a gradual change to subjects' bedtimes to earlier in the evening. Participants underwent general screening at visit 1 with collection of baseline parameters; then, 2 months later, at visit 2, subjects were randomized into either an intervention group or a comparison group. Researchers evaluated several parameters, including sleep duration, sleepiness, and sleep quality. The following results were reported: Note: Data is reported as mean ± standard deviation.
*p < 0.05.
1 ESS (Epworth Sleepiness Scale [daytime sleepiness]) >10 = sleepy.
2 PSQI (Pittsburgh Sleep Quality Index [subjective sleep quality]) >5 = abnormal.
There were statistically significant differences in all 3 parameters between visit 1 and visit 2. Which of the following is the best explanation for the difference between findings at the screening and randomization visits?
(Multiple Choice)
4.9/5 (68)
(68) A 61-year-old Caucasian female presents to her primary care physician complaining, "I feel terrible lately, coughing much worse than normal. Just very nauseated and tired. My head is pounding and my husband says I'm especially irritable." She also attests to a gradual increase in thirst and a generalized weakness. She has a history of mitral valve prolapse and well-controlled hypertension. Her only medications at this time are atenolol and a multivitamin. From the age of 19, she has smoked one pack of cigarettes per day. She drinks socially on the weekends. Physical examination reveals a thin, pale woman who is mildly wheezing but otherwise appears normal. Chest x-ray shows a four centimeter perihilar mass and increased hilar opacity.  What is the most likely diagnosis?
 (Multiple Choice)
4.8/5 (85)
(85) A 34-year-old woman comes to the office due to intermittent palpitations for 2 weeks. The patient has no chest pain or shortness of breath. She was diagnosed with hypertrophic cardiomyopathy 10 years ago and hypothyroidism 5 years ago. The patient takes metoprolol and levothyroxine. Temperature is 37.1 C (98.8 F), blood pressure is 120/80 mm Hg, pulse is 65/min and regular, and respirations are 15/min. BMI is 27 kg/m2. Oxygen saturation is 98% on room air. Mucous membranes are moist. Jugular venous pressure is normal. The thyroid gland is symmetrically enlarged and nontender. The lungs are clear to auscultation. A grade 2/6 systolic murmur is heard best at the left sternal border. Complete blood count and serum chemistries are normal. Serum TSH concentration is 1.4 μU/mL. ECG shows normal sinus rhythm with T-wave inversions in the anterior leads, unchanged from 6 months ago. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (95)
(95) A 14-year-old girl with a history of juvenile myoclonic epilepsy is brought to the emergency department after 2 generalized tonic-clonic seizures that started approximately 1 hour ago. She has not returned to baseline between seizures. The patient was prescribed daily levetiracetam, but her parents suspect that she has not taken it for the past week. On arrival, her airway is patent and she has good respiratory effort. Her blood pressure is 123/82 mm Hg, pulse is 130/min, respirations are 16/min, and pulse oximetry is 99% on 2 L oxygen via nasal cannula. The patient's eyes are open, but she is not responding to commands. Neurologic examination shows pupils that are equal but minimally responsive to light. Rhythmic non-suppressible twitching of the mouth, both arms, and both legs has persisted for 10 minutes. Fingerstick glucose is 115 mg/dL. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (86)
(86) A 68-year-old man undergoing hemodialysis is being evaluated due to "difficulty breathing and chest tightness." He has not had any chest pain. The patient was feeling well when he arrived at his hemodialysis appointment. He was started on hemodialysis 15 minutes ago after a heparin flush; an intravenous iron infusion was started 5 minutes ago for iron deficiency anemia. Medical history is significant for end-stage renal disease due to uncontrolled hypertension, a small pericardial effusion, and small, bilateral pleural effusions. He has been on hemodialysis treatment for the past year. Temperature is 35.6 C (96.1 F), blood pressure is 90/60 mm Hg, pulse is 112/min, and respirations are 24/min. Pulse oximetry is 93% on room air. The patient is alert but in mild distress. Conjunctivae are pale. Lungs sounds are decreased at both bases. Bilateral wheezing is noted on auscultation of the lungs. Heart sounds are slightly muffled and rapid but without murmurs or rubs. Abdomen is soft and nontender. Skin is flushed. Mild, bilateral pitting pedal edema is present. What is the most likely cause of this patient's symptoms?
(Multiple Choice)
5.0/5 (76)
(76) A 22-year-old hospitalized man is evaluated for new-onset fever. The patient has a history of type 1 diabetes mellitus and came to the hospital 4 days ago due to abdominal pain, nausea, and vomiting. Admission laboratory studies showed blood glucose of 450 mg/dL, positive urine ketones, and metabolic acidosis on arterial blood gas analysis. He was treated with intravenous fluids and insulin infusion with improvement in his condition, and was transitioned to subcutaneous insulin. Over the past 24 hours, he has had high fever, worsening headache, and nasal congestion. Temperature is 38.9 C (102 F), blood pressure is 130/80 mm Hg, and pulse is 110/min. Mild periorbital swelling is present. There is right-sided, bloody, purulent nasal discharge and a black eschar on the inferior nasal turbinate. Percussion reveals a tender right-sided maxillary sinus. Neurological examination is normal. Which of the following is the best pharmacological treatment for this patient's current condition?
(Multiple Choice)
4.9/5 (84)
(84) A 3-day-old girl is brought to the emergency department due to profuse eye discharge. The infant's right eye began to have clear drainage and redness yesterday evening. The parents wiped the drainage away with a moist cloth. This morning, both eyes were involved and the discharge was heavy and purulent. The patient is breastfeeding well and voiding and stooling normally. She was born at term via vaginal delivery to a 24-year-old primigravida. The parents elected for an all-natural birth process and declined routine prenatal laboratory testing. The mother opted for unmedicated labor and delivery at a birthing center, and the infant received no medications postpartum. The mother and infant were discharged approximately 4 hours after delivery. Temperature is 36.9 C (98.4 F). On physical examination, bilateral eyelid swelling is seen. When the eyelids are opened, thick, purulent discharge is expressed. The remainder of the examination is unremarkable. Which of the following peripartum interventions would most likely have prevented this patient's condition?
(Multiple Choice)
5.0/5 (85)
(85) A 79-year-old man is brought to the office by his daughter. The patient has been having increasing difficulty caring for himself over the last 2 years. He is now dependent on his daughter for meal preparation, shopping, and cleaning. He will frequently go a week without bathing and often has difficulty dressing himself appropriately. The patient sometimes grows frustrated and shouts at his daughter but has never been physically violent. On direct questioning, he states that he feels fine, does not see any reason for coming to the office, and is quite suspicious of his daughter's motives. The patient has lived alone since his wife died 5 years ago. He has hypertension, osteoarthritis, and a history of remitted major depressive disorder. Medications include hydrochlorothiazide and acetaminophen as needed. Neurologic examination is nonfocal. Item 1 of 2
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (87)
(87) A 74-year-old woman is brought to the emergency department with fever, chills, and shortness of breath. Two days ago, she choked while having tea and doughnuts and almost lost consciousness. Her son performed the Heimlich maneuver. The patient has advanced Alzheimer dementia, and her son is her health care proxy and primary caregiver; her 73-year-old husband also participates in her care. Her other medical problems include hypertension, hyperlipidemia, coronary heart disease, ischemic stroke with mild residual right hemiparesis, history of heme-positive stools, and urine incontinence. She is allergic to penicillin (anaphylaxis). Her temperature is 38.9 C (102 F), blood pressure is 120/80 mm Hg, pulse is 92/min, and respirations are 24/min. Pulse oxymetry shows 89% on room air and 94% on 40% facemask oxygen. Auscultation of the chest shows crackles at the right lung base. The heart sounds are regular. There is no jugular venous distension. The abdomen is soft, nontender, and nondistended. There is no peripheral edema. Laboratory results are as follows:  A portable chest x-ray shows a right lower-lobe infiltrate.
During the last 4 days of hospitalization, the patient has received 6 L of 0.9% saline. Her urine output has been 400 mL in the last 24 hours. She has been afebrile for the past 2 days. Her blood cultures are negative, and her urine culture grew budding yeast. The patient is currently receiving 150 mL/hr of 0.9% saline, nasogastric tube feedings, and antibiotics. Her temperature is 36.7 C (98 F), blood pressure is 140/70 mm Hg, pulse is 82/min, respirations are 18/min, and oxygen saturation is 96% on 2 L O2 by nasal cannula. Her mucous membranes are moist. The lungs still have crackles at the right base. There is no pericardial rub, peripheral edema, or asterixis. The results of her recent basic metabolic panel are as follows:
 An ECG shows no abnormal intervals and no peaked T waves.
What is the most appropriate course of action at this time?
A portable chest x-ray shows a right lower-lobe infiltrate.
During the last 4 days of hospitalization, the patient has received 6 L of 0.9% saline. Her urine output has been 400 mL in the last 24 hours. She has been afebrile for the past 2 days. Her blood cultures are negative, and her urine culture grew budding yeast. The patient is currently receiving 150 mL/hr of 0.9% saline, nasogastric tube feedings, and antibiotics. Her temperature is 36.7 C (98 F), blood pressure is 140/70 mm Hg, pulse is 82/min, respirations are 18/min, and oxygen saturation is 96% on 2 L O2 by nasal cannula. Her mucous membranes are moist. The lungs still have crackles at the right base. There is no pericardial rub, peripheral edema, or asterixis. The results of her recent basic metabolic panel are as follows:
An ECG shows no abnormal intervals and no peaked T waves.
What is the most appropriate course of action at this time? (Multiple Choice)
4.8/5 (107)
(107) A 33-year-old man comes to the office due to fever, malaise, and worsened cough. Six weeks ago, the patient visited the emergency room due to 2 weeks of anorexia, cough, fever, weight loss, and dyspnea. He was hospitalized and found to have a right upper lobe lung infiltrate, acid-fast bacilli in the sputum, a CD4 count of 55/mm3, and an HIV RNA viral load of 125,000 copies/mL. The patient was diagnosed with active pulmonary tuberculosis and HIV infection, and was initiated on antiretroviral therapy and 4-drug tuberculosis treatment. His symptoms steadily improved until 3 days ago when his fever and cough returned. He lives alone but a visiting nurse helps him with his medications; he has taken all medications as prescribed. He has no known drug allergies. The patient has a history of multiple incarcerations and used cocaine heavily in the past. Temperature is 39.6 C (103.2 F), blood pressure is 126/82 mm Hg, pulse is 92/min, and respirations are 20/min. There are no mucosal lesions or skin rash. Lung auscultation reveals right-sided crackles. Heart sounds are normal with no murmur. The abdomen is soft and nontender with no hepatosplenomegaly. Chest x-ray is performed and reveals a larger-sized lung opacity and worsened hilar lymphadenopathy. Laboratory studies show a CD4 count of 220/mm3 and HIV RNA viral load of <10,000 copies/mL. Sputum culture results from his previous hospitalization show acid-fast bacilli sensitive to all tested drugs. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (54)
(54) Showing 921 - 940 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)