



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


A 68-year-old man comes to the emergency department due to 12 hours of worsening abdominal pain, nausea, and vomiting. The patient has had intermittent abdominal discomfort and nausea over the past several months but not to this severity. He has had no diarrhea, and his most recent bowel movement was 1 day ago. The patient has no known medical conditions and takes no medications. He has smoked a pack of cigarettes daily for 30 years and drinks 1 or 2 alcoholic beverages daily. Temperature is 38.5 C (101.3 F), blood pressure is 106/64 mm Hg, pulse is 112/min, and respirations are 18/min. On physical examination, the patient appears to be in discomfort and is diaphoretic. The abdomen is tender and rigid throughout. Bowel sounds are absent. Abdominal imaging shows free air under the diaphragm. Intravenous fluids and empiric antibiotics are started, and surgical consultation is obtained. While being prepared for laparotomy, the patient develops new-onset atrial fibrillation with a ventricular rate of 118/min. The patient reports no palpitations, chest pain, or dyspnea. Blood pressure is 110/70 mm Hg. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5  (61)
(61) A 52-year-old man comes to the emergency department an hour after the onset of severe substernal chest pressure that lasted 30 minutes. The symptoms started when he was helping his brother move into his new house and were associated with mild dizziness and shortness of breath. His brother has coronary artery disease with stable angina and the patient took 3 of his brother's nitroglycerin tablets sublingually before his pain eventually subsided. He is currently pain free. Medical history includes hypertension and hyperlipidemia. The patient's daily medications include losartan, atorvastatin, and low-dose aspirin. Blood pressure is 152/93 mm Hg and pulse is 105/min. BMI is 32 kg/m2. The lungs are clear to auscultation bilaterally. Cardiac examination indicates a prominent point of maximal impulse that is displaced downward and to the left. Auscultation reveals regular, normal heart sounds with an audible S4. There are no murmurs. The rest of the physical examination is within normal limits. ECG shows sinus tachycardia and voltage criteria for left ventricular hypertrophy, similar to the patient's ECG 6 months ago. His troponin level is normal. He says, "I feel fine! I just want to go home and I will see my primary care doctor." Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (94)
(94) A 13-year-old boy is brought to clinic by his parents due to copious, purulent discharge from his right eye. The patient's eye was crusted shut this morning. His father was able to open the eye by wiping it with a damp washcloth. The patient went to school but was sent home by the school nurse. He has not had ocular pain, visual changes, or fever. He lives at home with his parents and older sister, none of whom have similar symptoms. The patient has mild myopia and wears contact lenses. He takes loratadine daily for seasonal allergies. Vital signs are within normal limits. Examination shows conjunctival erythema and yellow exudate in the right eye. The conjunctiva of the left eye is also erythematous, but there are no secretions. Visual acuity testing with the patient's contacts removed shows 20/80 vision in both eyes, consistent with his well-child examination at age 12. Item 1 of 3
Which of the following is the most appropriate pharmacotherapy?
(Multiple Choice)
4.8/5 (79)
(79) A 36-year-old woman, gravida 3 para 2, at 13 weeks gestation comes to the office for a prenatal visit. The patient had painless vaginal spotting a few weeks ago that has since resolved. An ultrasound was performed several days ago as a part of the first-trimester integrated screening. The patient's previous 2 pregnancies ended in uncomplicated term vaginal deliveries. She has no chronic medical conditions. Her only surgery was a laparoscopic cholecystectomy. She is the vice principal at a local elementary school and volunteers as a basketball coach. The patient takes a prenatal vitamin and an iron supplement daily. She does not use tobacco, alcohol, or illicit drugs. The patient attends a yoga class 3 times a week. Blood pressure is 110/70 mm Hg and pulse is 68/min. BMI is 26 kg/m2. Fetal heart rate is 150/min. The ultrasound reveals a 13-week fetus with a normal nuchal translucency measurement and a 1.8-cm (0.71-in), crescent, hypoechoic area between the gestational sac and the uterus, which is consistent with a hematoma. The patient's blood type is B, Rh positive. The other results from the first-trimester integrated screening are normal. Appropriate action was taken. Given the ultrasound findings, this patient is at increased risk for which of the following complications?
(Multiple Choice)
4.9/5 (76)
(76) A 15-year-old girl is brought to the office after falling in the shower. Her mother was outside of the bathroom when she heard a thud, and went in and found her daughter trying to get back up. The patient insists, "I just slipped. It's no big deal. I am fine." She reports that she had no loss of consciousness, tongue biting, incontinence, or confusion. Her parents are concerned that she lost her balance because she is thin and eats poorly. They also note that she seems depressed and has not been interested in seeing any friends. The patient admits, "I have been a little down since my boyfriend broke up with me, but I don't blame him because I am so fat." She takes no medications, has no allergies, and does not use tobacco, alcohol, or illicit drugs. Temperature is 35.6 C (96 F), blood pressure is 100/60 mm Hg sitting and 80/48 mm Hg standing, pulse is 50/min, and respirations are 14/min. BMI is 16 kg/m2. Examination shows an alert and cooperative girl with dry mucous membranes and emaciation. Calluses are present over the knuckles. The abdomen is soft, nontender, and nondistended. Urine hCG is negative. Laboratory results are as follows:
 The patient is admitted to the hospital. Thiamine is administered prior to initiation of a supervised diet. On the third day of hospitalization, the patient develops progressive dyspnea and orthopnea. Temperature is 35.6 C (96 F), blood pressure is 100/60 mm Hg sitting and standing, pulse is 78/min, and respirations are 24/min. Examination reveals an anxious girl with bibasilar crackles, dullness to percussion of the lung bases, and pretibial pitting edema. Laboratory results are as follows:
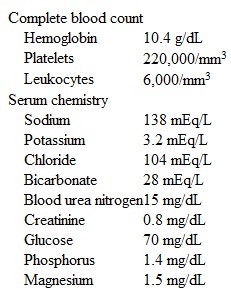 Which of the following therapies should be administered immediately?
The patient is admitted to the hospital. Thiamine is administered prior to initiation of a supervised diet. On the third day of hospitalization, the patient develops progressive dyspnea and orthopnea. Temperature is 35.6 C (96 F), blood pressure is 100/60 mm Hg sitting and standing, pulse is 78/min, and respirations are 24/min. Examination reveals an anxious girl with bibasilar crackles, dullness to percussion of the lung bases, and pretibial pitting edema. Laboratory results are as follows:
Which of the following therapies should be administered immediately? (Multiple Choice)
4.9/5 (70)
(70) A 41-year-old woman comes to the physician with an 8-month history of amenorrhea. Multiple home pregnancy tests during this time have been consistently negative. She has mild dyspareunia and blurred vision but no headaches, galactorrhea, hot flashes, or weight change. The patient's past medical and family histories are unremarkable. She takes no medications, including over-the-counter drugs. She does not use alcohol, tobacco, or intravenous drugs. Physical examination is unremarkable. Basic metabolic panel and complete blood count are within normal limits. Her hormone profile shows a prolactin level of 50 ng/mL (normal 5-20 ng/mL). Serum luteinizing hormone level is undetectable, follicle-stimulating hormone is low normal, and the α-subunit is markedly increased. Serum thyroid-stimulating hormone, testosterone, and insulin-like growth factor 1 are normal. Magnetic resonance imaging of the pituitary shows a 2-cm pituitary tumor with suprasellar extension. What is the most appropriate next step in management of this patient?
(Multiple Choice)
4.7/5 (85)
(85) A 28-year-old man with a history of bipolar I disorder is brought to the emergency department after being pulled over by police for driving erratically. The police report indicates that the patient appeared alcohol-intoxicated and refused to cooperate with questions, stating, "I have the skills of a race car driver and a need for speed." He has been on lithium for years and says he has been adherent. The patient has a history of bilateral knee injuries sustained in an accident when he jumped from a high ledge. He has no other medical history. The emergency physician contacts the outpatient psychiatrist, who reports that the patient has been treated with lithium for the past 3 years. He had a therapeutic lithium level and appeared stable at his last visit 2 weeks ago. The patient is re-interviewed when he is sober. He felt upset after his girlfriend left him and was turned down for a job, and so decided to "get drunk." He is apologetic for driving recklessly and says he intends to follow up with his outpatient psychiatrist. Although the patient admits to a history of crack cocaine use, he currently uses no illicit substances other than marijuana on weekends. Temperature is 37.2 C (99 F), blood pressure is 140/80 mm Hg, and pulse is 88/min. Physical examination is normal. The patient is alert, and his speech is nonpressured. Urine toxicology screen is negative for illicit substances. The patient admits that he was, in fact, trying to get up the nerve to crash his car and kill himself. He started to swerve on purpose but then straightened out when he thought of how his suicide would devastate his mother. He explains, "When I am in a dark hole, it seems that nothing will ever get better for me; suicide seems like the only way out." His psychiatrist confirms that the patient has had suicidal thoughts in the past, nearly always when he is drinking. The patient agrees to hospitalization for further evaluation and treatment. Which of the following is the most appropriate next step to reduce the risk of suicide in this patient?
(Multiple Choice)
4.8/5 (75)
(75) A 55-year-old man comes to the emergency department due to a painful, persistent erection. Earlier in the evening, the patient used an intracavernosal injection of alprostadil to achieve an erection for sexual intercourse. His erection persisted afterward but he was able to fall asleep. He was then awakened 4 hours later due to pain in his penis. The patient placed an ice pack over the region, but the painful erection remained. He does not have a history of genitourinary trauma or similar episodes in the past. Medical history is notable for type 2 diabetes mellitus and peripheral vascular disease. Current medications include lisinopril, metformin, rosuvastatin, and low-dose aspirin. The patient does not use tobacco, alcohol, or illicit drugs. Temperature is 37 C (98.6 F), blood pressure is 120/78 mm Hg, pulse is 88/min, and respirations are 14/min. The corpora cavernosa of the penis are engorged and tender to palpation. The glans and the corpus spongiosum are softly distended without rigidity. There are no genital lesions, urethral discharge, or evidence of trauma. Cavernosal blood gas analysis shows pH of 7.2, pCO2 of 65 mm Hg, and pO2 of 30 mm Hg, consistent with ischemic priapism. Corporeal aspiration is attempted but fails to relieve the patient's symptoms. Which of the following is the best next step in the management of this patient's condition?
(Multiple Choice)
4.9/5 (74)
(74) A 54-year-old postmenopausal woman comes to the office to establish care. She feels well and describes her lifestyle as "overall healthy." The patient has a history of hypertension, osteopenia, and anxiety disorder. She went through menopause at age 49, during which time she experienced hot flashes, sleep disturbances, and mood swings. The symptoms have largely resolved except for occasional episodes of anxiety. The patient did not receive any therapy for her menopausal symptoms. Her current medications include valsartan, calcium/vitamin D, and paroxetine. She is married, works as a television news reporter, and does not smoke or consume alcohol. Family history is negative for coronary heart disease, stroke, cancer, and venous thromboembolism. Blood pressure is 128/76 mm Hg and pulse is 68/min. BMI is 29 kg/m2. Physical examination is normal. Laboratory results are as follows: 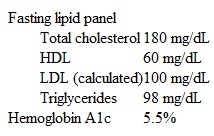 The patient says that her friends have been telling her about the "anti-aging" effects of hormone replacement therapy, and she would like to discuss initiating treatment. She asks for advice regarding the risks and benefits of combined estrogen/progesterone menopausal hormonal therapy (MHT). Which of the following is the most appropriate response regarding MHT in this patient?
 (Multiple Choice)
4.7/5 (71)
(71) A 54-year-old man comes to the office due to 3 months of urinary frequency and urgency. He has also had discomfort in the pelvic region and pain during ejaculation. The patient's symptoms temporarily improved during a week-long course of trimethoprim-sulfamethoxazole for urinary tract infection but recurred shortly after treatment concluded. He has a history of hypertension well controlled with lisinopril. He also had a single episode of gonorrhea 20 years ago that was treated with penicillin. The patient has a 20-pack-year smoking history but quit 4 years ago. He drinks alcohol on social occasions and does not use illicit drugs. He is monogamous with his wife. Temperature is 37 C (98.6 F), blood pressure is 120/70 mm Hg, and pulse is 80/min. The abdomen is soft and nontender with no organomegaly. Genital examination shows a circumcised penis with no urethral discharge. Testicular examination shows no abnormalities. The prostate is slightly enlarged with minimal tenderness and no nodules. Urinalysis shows 20-30 leukocytes/HPF and moderate bacteruria but no erythrocytes. Prostate-specific antigen level is within normal limits. Which of the following is the most appropriate management of this patient?
(Multiple Choice)
4.9/5 (71)
(71) A 62-year-old man comes to the office due to burning discomfort in his chest, which has been getting worse over the last year. The discomfort occurs 4 or 5 times a week, usually 30-40 minutes after meals. The patient has reduced his intake of coffee because he thinks it provokes the symptoms. Other issues include chronic back pain, dry cough, and constipation. The patient has good exercise tolerance and is not limited by chest pain or shortness of breath. He has had no abdominal pain, vomiting, black stools, or weight loss. Medications include daily aspirin and a multivitamin. His father died of pancreatic cancer at age 55. The patient has a 20-pack-year smoking history but quit 5 years ago. Blood pressure is 133/90 mm Hg and pulse is 76/min. BMI is 32 kg/m2. Waist circumference is 110 cm. Physical examination is otherwise unremarkable. Upper gastrointestinal endoscopy is indicated to evaluate for which of the following in this patient?
(Multiple Choice)
4.8/5 (83)
(83) A 14-year-old girl comes to the office accompanied by her mother for an annual examination. The patient's medical problems include acne, for which she takes clindamycin. When seen alone for examination, she is shy and quiet. The patient says everything is "going okay." She does not have a boyfriend and is not sexually active. When asked about drug and alcohol use, she says, "No, but I have tried alcohol and marijuana a few times at parties." Physical examination is normal other than mild acne, which has improved since her last visit. Following the examination, the physician informs the mother that everything is fine, renews the patient's clindamycin prescription, and asks if she has any questions. With the daughter present, the mother replies, "I remember what it's like to be a teenager, but she is really impossible to deal with now. I can't get her up on time in the morning because she stays up late on her computer. She no longer wants to spend time with the family. In the morning, she refuses to eat breakfast and then sleeps during the entire drive to school. I worry because her school friends use drugs. I think they are a bad influence and now her grades are falling. I don't know how she will get into a decent college. We warned her that she wouldn't be allowed to go on the family vacation if she doesn't improve her grades, but she doesn't seem to care." The physician speaks with the patient privately and begins by asking her more about school. She says, "I'm really upset about my grades and I feel guilty because my parents have been saving up to send me to college. I just space out when the teacher is lecturing. When it comes to tests, I can't remember anything I have read." When asked about her friends and substance use, she says, "Some of my friends smoke marijuana, but I don't even go out with them. I prefer to go straight home after school, stay in my room, and sleep or listen to music. The last time I tried marijuana was at a party 4 months ago." When asked about her sleep, the patient says, "It's hard to get up in the morning when I feel so tired. I quit the volleyball team because the coach was mean and I couldn't get up early for practice." She has not been dieting or vomiting and says, "I skip meals because I'm just not that interested in food." The patient avoids spending time with her family because "my mom just gets on my nerves and she is always critical. I really don't want to go on vacation with my family. I just want to be left alone." Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (83)
(83) A 26-year-old white woman who is a long distance runner comes to your office. She trains daily and participates frequently in marathons and other long-distance competitive events all around the country. She denies smoking or alcohol drinking, and says that she follows a healthy, low-fat diet. Her last menstrual period was three years ago, but this is not a problem for her as she does not want to get pregnant "at least in the next five years." After an extensive work-up, her amenorrhea was attributed to exercise. She is 168 cm (5'6'') tall and weighs 50 kg (110 lbs). Her blood pressure is 100/60 mmHg, pulse is 58/min, and respirations are 14/min. Physical examination shows no abnormality. You alert the patient that her amenorrhea poses the risk of another condition. Which of the following conditions are you referring to?
(Multiple Choice)
4.9/5 (84)
(84) A 64-year-old man comes to the emergency department after developing fever and chills during hemodialysis. He still feels feverish but has no sore throat, cough, abdominal pain, nausea, or diarrhea. Temperature was 38.9 C (102 F) at the dialysis center. The patient has a history of poorly controlled type 2 diabetes mellitus and hypertension, which led to end-stage renal disease. He was initiated on long-term intermittent hemodialysis 2 months ago. The patient has no known drug allergies. He does not use tobacco, alcohol, or illicit drugs. Temperature is 38 C (100.4 F), blood pressure is 120/62 mm Hg, pulse is 105/min, and respirations are 22/min. Oxygen saturation is 96% on room air. There is a tunneled central venous catheter in the right internal jugular vein, and the skin around the insertion site is not erythematous or tender. Cardiopulmonary auscultation reveals clear lung fields and normal heart sounds. The abdomen is soft and nontender. No skin rash or neck stiffness is present. Leukocyte count is 14,000/mm3 with 90% neutrophils. Chest-x ray reveals no infiltrate or consolidation. Two sets of blood cultures, one from a peripheral vein and the other from the central venous catheter, are obtained. Both sets of blood cultures grow methicillin-resistant Staphylococcus aureus. The patient's antibiotic regimen is narrowed to vancomycin alone, and the tunneled catheter is removed. On day 4 of hospitalization, he continues to have intermittent fevers. He has no cough, abdominal pain, or diarrhea but does note worsening back pain in his lumbar region, which he attributes to inactivity and the uncomfortable hospital bed. The pain is a dull ache and does not radiate. Examination reveals midline tenderness in the lower lumbar area. Neurological examination shows no abnormalities. Leukocyte count remains elevated at 16,000/mm3. Repeat blood cultures performed after venous catheter removal show no growth. Plain radiographs of the lumbosacral spine reveal no abnormalities. Echocardiography reveals no valvular vegetations. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (75)
(75) An 18-year-old man comes to the physician for daytime sleepiness lasting several months. The patient recently started college, has difficulty staying awake during classes, and often falls asleep suddenly even though he "gets a good night's sleep." He typically goes to bed at 2 am and sleeps until at least 9 am, usually later. The patient's sleep pattern at night is fragmented. He wakes frequently but is usually able to go back to sleep within a few minutes. He does not snore or wake up gasping. The patient feels like "someone is in the room with me when I'm just falling asleep and I sometimes hear my name being called." His past medical history is otherwise insignificant. The patient does not use tobacco or alcohol. Blood pressure is 120/70 mm Hg and heart rate is 70/min. His body mass index is 23 kg/m2. Item 1 of 3
Which of the following is the best next step in diagnosing the cause of this patient's symptoms?
(Multiple Choice)
4.7/5 (78)
(78) A 33-year-old Caucasian female presents to your office with a six-month history of cold intolerance. When the weather is cold, her third and fourth fingers on both hands get numb and turn blue. She says, 'I wear gloves to keep my hands warm, but it does not always work'. Her past medical history is significant for non-ulcer dyspepsia treated with omeprazole. She does not smoke or consume alcohol, and denies any recreational drug use. She has no known drug allergies. She works as a nurse at a local hospital and considers her job moderately stressful. She is sexually active with her husband and uses condoms for contraception. Physical examination findings are within normal limits.
Which of the following medications is the best initial treatment for this patient?
(Multiple Choice)
4.8/5 (78)
(78) A 34-year-old woman, gravida 2 para 1, at 38 weeks gestation comes to the emergency department for contractions and vaginal spotting. The contractions started 4 hours ago and are now occurring every 3 minutes. She reports normal fetal movement and no leakage of fluid. The patient had no prenatal care but was hospitalized at 18 weeks gestation for viral gastroenteritis. A fetal ultrasound performed during this hospitalization was normal. The patient's previous delivery, a year ago, was a term cesarean delivery for breech presentation. The patient has no chronic medical conditions and has had no other surgeries. She does not use tobacco, alcohol, or illicit drugs. Temperature is 36.7 C (98 F), blood pressure is 100/60 mm Hg, and pulse is 84/min. The fetal heart rate tracing is shown below: 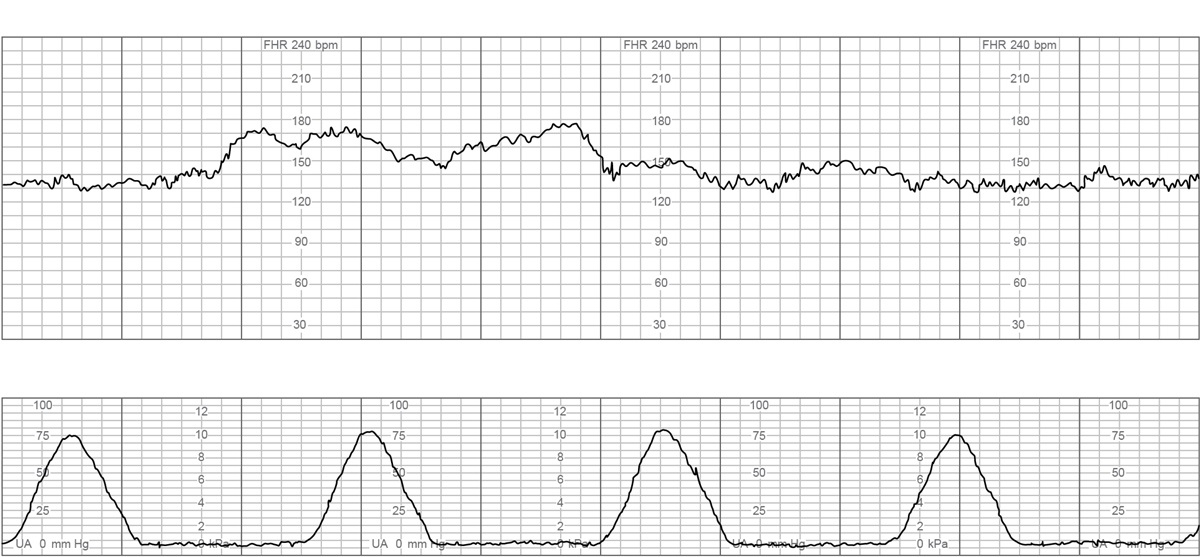 Examination shows the cervix to be 5 cm dilated and 80% effaced, with the fetal head at 0 station. Blood type is O, Rh negative. The patient is admitted and epidural anesthesia is administered. Two hours later, the patient has spontaneous rupture of membranes and becomes acutely uncomfortable. Blood pressure is 140/92 mm Hg and pulse is 100/min. The fetal heart rate tracing now is shown below:
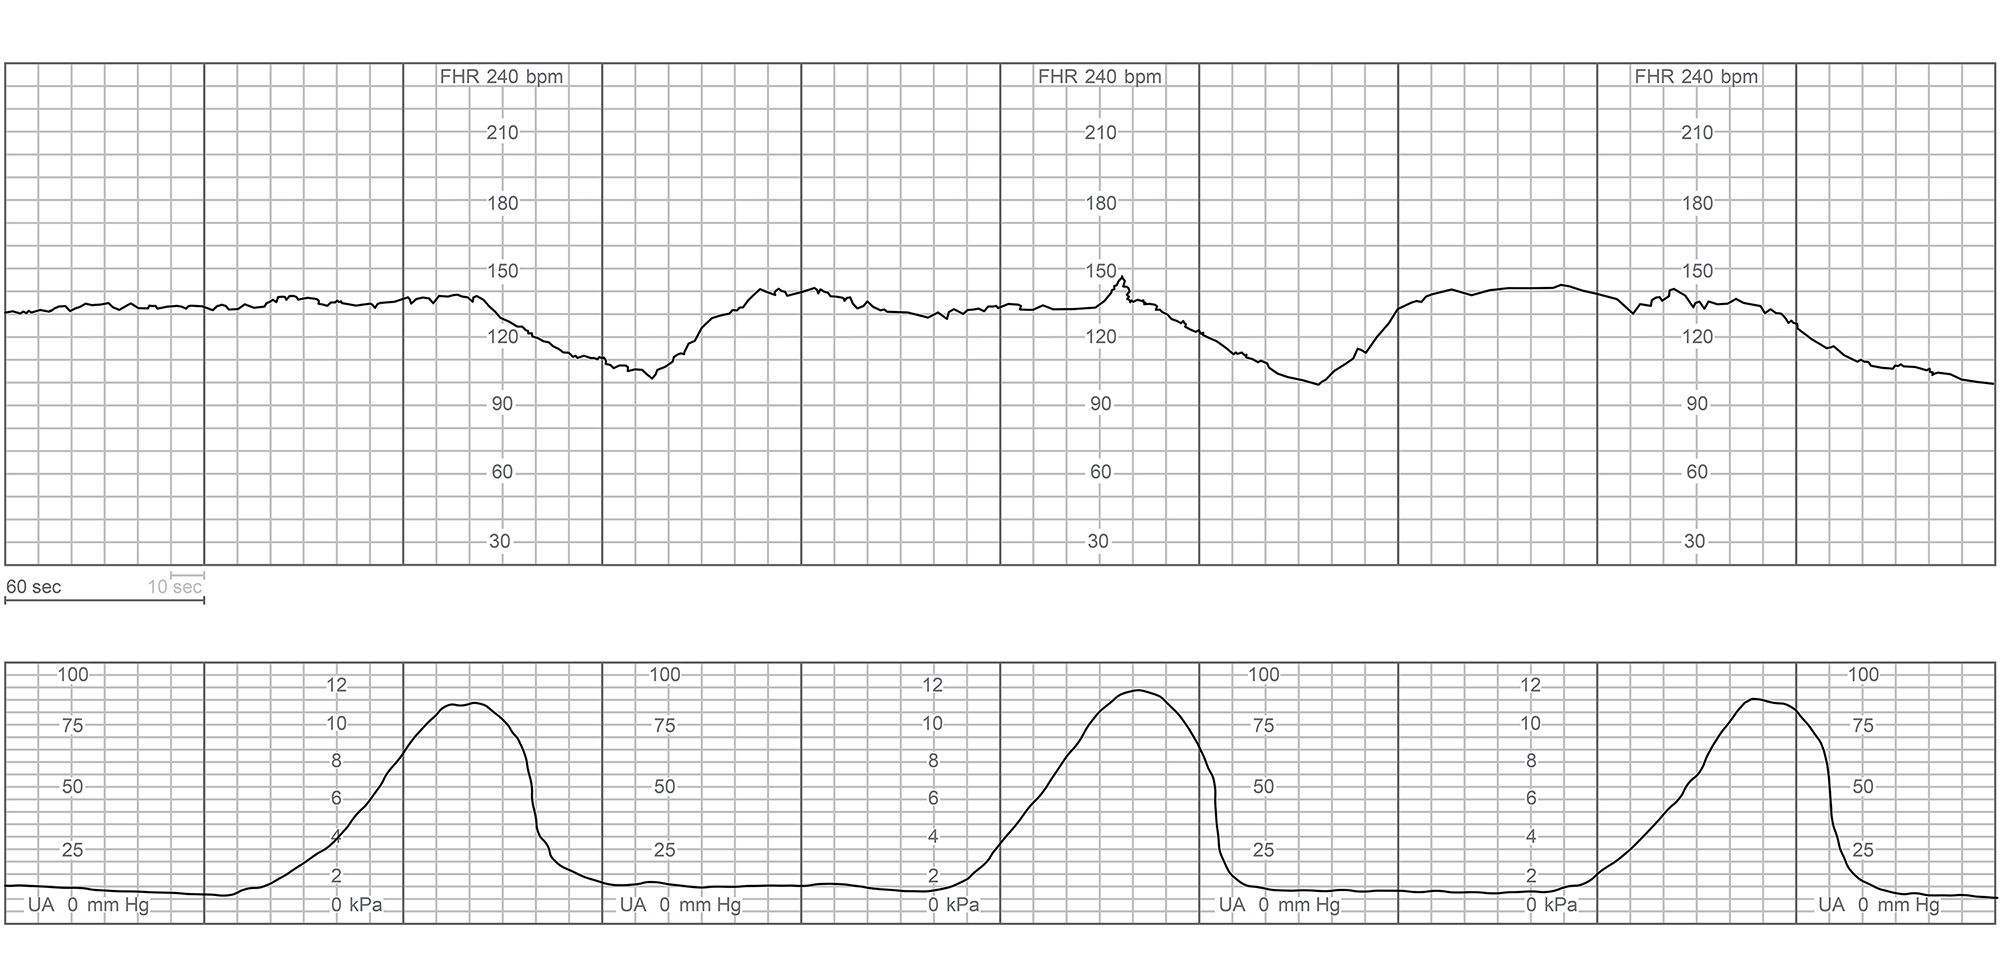 The patient begins to have heavy vaginal bleeding. The cervix is now 5 cm dilated and 80% effaced, with the fetal head at -3 station. Which of the following is the best next step in management of this patient?
Examination shows the cervix to be 5 cm dilated and 80% effaced, with the fetal head at 0 station. Blood type is O, Rh negative. The patient is admitted and epidural anesthesia is administered. Two hours later, the patient has spontaneous rupture of membranes and becomes acutely uncomfortable. Blood pressure is 140/92 mm Hg and pulse is 100/min. The fetal heart rate tracing now is shown below:
The patient begins to have heavy vaginal bleeding. The cervix is now 5 cm dilated and 80% effaced, with the fetal head at -3 station. Which of the following is the best next step in management of this patient? (Multiple Choice)
4.7/5 (79)
(79) A 52-year-old homeless man comes to the urgent care clinic due to itching and discomfort in both feet. He has had these symptoms for the past year but they intensified recently. His shoes are uncomfortable and cause irritation. Several shelter residents also have some "swelling of the feet." The patient was told that he has "borderline" diabetes and high blood pressure. He has no regular medical follow-up. Physical examination shows extensive erythema and scaling, especially between the toes, as well as multiple thickened and brittle toenails as shown in the image below. 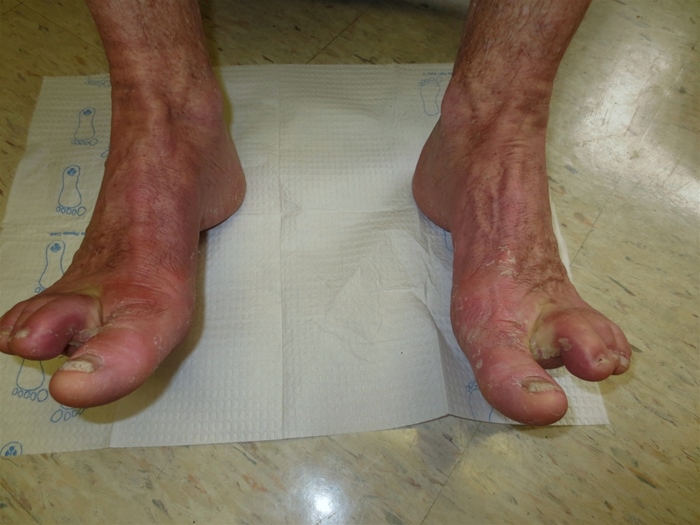 Which of the following is the best treatment for this patient?
 (Multiple Choice)
4.8/5 (76)
(76) A 24-year-old woman, gravida 1 para 0, at 11 weeks gestation comes to the office for a routine prenatal visit. The patient is doing well and has no vaginal bleeding or cramping. Earlier in the pregnancy, she had mild nausea that she managed by eating multiple small meals throughout the day. The patient has a history of cystitis that occurred prior to pregnancy, but currently has no dysuria or hematuria. She has no chronic medical conditions or previous surgeries. She takes a daily prenatal vitamin. The patient has no known drug allergies and does not use tobacco, alcohol, or illicit drugs. She runs on a treadmill for 45 minutes, 4 times a week. Temperature is 36.7 C (98 F), blood pressure is 124/74 mm Hg, and pulse is 78/min. Fetal heart rate is 140/min by Doppler ultrasound. Physical examination is otherwise unremarkable. Laboratory results from her initial prenatal visit are reviewed; a routine clean catch urine culture grew >100,000 colony-forming units/mL of Escherichia coli. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (81)
(81) A 65-year-old woman is brought to the emergency department by paramedics after falling on a snow-covered sidewalk. The patient fell backward onto her hands while trying to maintain her balance and immediately felt a sharp, excruciating pain in her right arm. She also notes mild tenderness and bruising on the right flank and right buttock. The patient has a history of osteoporosis and hypertension and takes valsartan, alendronate, and a vitamin D supplement. She does not use tobacco, alcohol, or illicit drugs. In the emergency department, radiograph reveals a displaced fracture of the right distal radius. The patient is admitted to the hospital and undergoes open reduction and internal fixation of the radius fracture. On postoperative day 2, she reports severe, constant, burning pain over her right flank. The postsurgical pain in the right arm is mild and well controlled with low-dose morphine as needed. Temperature is 37.8 C (100 F), blood pressure is 145/84 mm Hg, pulse is 97/min, and respirations are 16/min. Mucous membranes are moist and the oropharynx is without lesions. Cardiopulmonary auscultation reveals clear lungs and normal heart sounds. The abdomen is soft, nontender, and nondistended. The right flank is tender to light touch with a rash over the area, as shown in the exhibit. 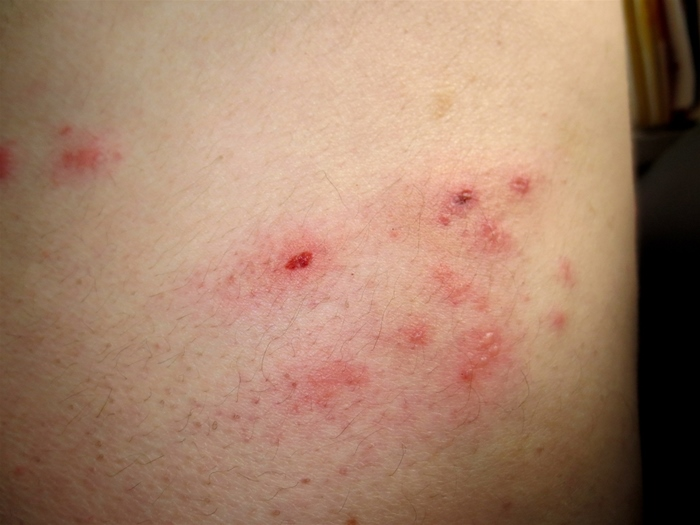 The surgical wound is healing normally without signs of infection. Four months later, the patient visits her primary care provider. She is going to physical therapy for her arm injury, and all the lesions on her right flank have resolved. However, the patient continues to have burning pain in the area where the rash occurred. In addition, she says that light touch of the area results in severe pain, and that the pain is making it difficult to sleep at night. Which of the following is the most appropriate treatment for this patient?
 (Multiple Choice)
4.8/5 (77)
(77) Showing 1061 - 1080 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)