



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


A 72-year-old man is referred for preoperative evaluation for abdominal aortic aneurysm repair. He has had no chest pain, palpitations, shortness of breath, or syncope. The aneurysm was initially identified on routine screening when the patient was age 65. Since then, he has undergone yearly surveillance ultrasounds. The most recent study demonstrated an aneurysm with a diameter of 5.5 cm, an increase of 4 mm from the measurement at the ultrasound performed a year prior. He is not a candidate for minimally invasive endovascular stent graft repair due to the juxtarenal location of the aneurysm and need for left renal artery reimplantation. The patient has a history of hypertension, hyperlipidemia, type 2 diabetes mellitus, and mild aortic stenosis. Medications include aspirin, valsartan, amlodipine, high-intensity atorvastatin, metformin, and long-acting insulin. He is a former smoker but quit 15 years ago when he was diagnosed with diabetes. He does not drink alcohol and has no history of illicit drug use. The patient reports no difficulty with managing his activities of daily living, including briskly climbing up and down stairs in his 2-story home. A younger brother recently underwent coronary artery bypass graft surgery. Temperature is 36.7 C (98 F), blood pressure is 142/80 mm Hg, pulse is 70/min, and respirations are 14/min. Pulse oximetry shows 99% on room air. Weight is 100 kg (220.5 lb) and height is 177.5 cm (5 ft 10 in). BMI is 30 kg/m2. Examination shows normal jugular venous pressure. Carotid pulses are 2+ and brisk bilaterally. The lungs are clear. On cardiac auscultation, S1 and S2 are normal and there is a soft midpeaking systolic murmur. A pulsatile mass is palpable on abdominal examination. There is trace pretibial edema bilaterally. On preoperative laboratory testing, the complete blood count is within normal limits. Glucose is 156 mg/dL and creatinine is 1.3 mg/dL. ECG shows normal sinus rhythm with nonspecific T-wave changes. Chest x-ray demonstrates a tortuous thoracic aorta but is otherwise normal. Which of the following is the most appropriate course of action?
(Multiple Choice)
4.7/5  (79)
(79) A 42-year-old woman comes to the office for evaluation of elevated blood pressure. She says, "I checked my blood pressure on a machine at the pharmacy, and it was 160/90 mm Hg. The pharmacist said I should see a doctor." The patient has no history of hypertension and has had no chest pain, headache, or focal weakness or numbness. She notes occasional episodes of pain in her flanks, which she ascribes to muscle tension. The patient has had several urinary tract infections over the course of her life but has no chronic medical problems and takes no medication regularly. She does not use tobacco, alcohol, or illicit drugs. The patient is married and has a son. Her mother has hypertension, her father died at an early age in a motor vehicle collision, and her uncle has renal failure and receives dialysis. Blood pressure is 156/94 mm Hg on the right arm and 152/96 mm Hg on the left arm. Pulse is 80/min and respirations are 16/min. Jugular venous pressure is within normal limits. Breath sounds are normal bilaterally with no crackles. Point of maximal impulse is displaced to the left and down. Heart sounds are normal with no murmur or gallops. The abdomen is soft with bilateral flank fullness. Bowel sounds are active. Laboratory results are as follows.  Urinalysis shows dysmorphic erythrocytes and mild proteinuria. ECG shows left ventricular hypertrophy with nonspecific ST-T wave changes.
Which of the following is the best next step in management of this patient?
Urinalysis shows dysmorphic erythrocytes and mild proteinuria. ECG shows left ventricular hypertrophy with nonspecific ST-T wave changes.
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.8/5 (85)
(85) A 17-year-old Caucasian boy is brought to the emergency department due to 3 days of worsening cough productive of green sputum. He has also had fever, fatigue, and chest pain with deep inspiration. For the past several years, the patient has had a cough on most days, but his current symptoms are worse than usual. He has had multiple hospitalizations for pneumonia, most recently 18 months ago. He also had a partial small bowel obstruction as a newborn. The patient takes several inhaled and oral medications daily. His sister has similar medical problems. Temperature is 102.3 F (39.1 C) and respirations are 22/min; oxygen saturation is 87% on room air. Examination shows a thin patient in moderate respiratory distress. Cardiac examination is normal. Auscultation of the lungs reveals crackles and scattered wheezes throughout, most prominent at the left base. Chest x-ray reveals hyperinflation, enlarged perihilar lymph nodes, and prominent bronchovascular markings. In addition to vancomycin, the most appropriate initial antimicrobial therapy for this patient should include which of the following?
(Multiple Choice)
5.0/5 (84)
(84) A 79-year-old woman is hospitalized after a fall that resulted in a left femoral neck fracture. She tripped over her dog while cleaning her home, hit her head on a bookshelf, and landed on her left side. Prior to this she had been in her usual state of health; her other medical issues include obesity, type 2 diabetes mellitus, hypertension, chronic kidney disease, and hypothyroidism. The patient lives at home by herself. She has smoked a pack of cigarettes daily for 38 years. She drinks alcohol every weekend. Results of the patient's initial workup in the emergency department demonstrated the left femoral neck fracture, creatinine of 2.0 mg/dL, and a negative noncontrast head CT. She was admitted to the hospital and the following day underwent surgical repair. The procedure was uncomplicated. However, on postoperative day 3 the patient is noted to be uncomfortable and mildly agitated. She is unable to coherently explain her symptoms. Current medications include prophylactic subcutaneous heparin, insulin glargine, omeprazole, hydrocodone, and levothyroxine. Temperature is 37.7 C (99.9 F), blood pressure is 104/68 mm Hg, pulse is 114/min, and respirations are 28/min. Pulse oximetry is 86% on room air. Examination shows equal round and reactive pupils. Lung examination demonstrates decreased breath sounds at the bilateral bases. Heart rhythm is regular with normal S1 and S2. The surgical incision shows no surrounding erythema or purulent drainage. The patient follows commands and moves all extremities except the left leg. Laboratory results are as follows:
 Troponin I is undetectable. Chest x-ray shows slight bibasilar atelectasis without focal consolidation, pleural effusion, or pulmonary edema. ECG shows sinus tachycardia but is otherwise unremarkable.
Ventilation-perfusion scan shows high probability for pulmonary embolism. The patient is started on intravenous heparin. The next day, the nurse reports that the patient has a fever. The patient still has some chest pain but her shortness of breath and mental status are improved. There is no cough, abdominal pain, nausea, vomiting, diarrhea, dysuria, urinary frequency, or headache. Temperature is 38.3 C (101 F), blood pressure is 121/73 mm Hg, pulse is 102/min, and respirations are 22/min. Oxygen saturation is 92% on 2 L of oxygen by nasal cannula. She does not appear ill. The lungs are clear to auscultation. The abdomen is soft and nontender. Neurologic examination is nonfocal. The operative site is healing well without erythema or purulence. The patient's 2 peripheral IV lines have no evidence of infection. Indwelling urinary catheter is draining clear yellow urine. Laboratory results are as follows:
 Chest x-ray shows no new abnormalities. Urinalysis is normal. Blood cultures are sent. Which of the following would be the most appropriate next step for this patient?
Troponin I is undetectable. Chest x-ray shows slight bibasilar atelectasis without focal consolidation, pleural effusion, or pulmonary edema. ECG shows sinus tachycardia but is otherwise unremarkable.
Ventilation-perfusion scan shows high probability for pulmonary embolism. The patient is started on intravenous heparin. The next day, the nurse reports that the patient has a fever. The patient still has some chest pain but her shortness of breath and mental status are improved. There is no cough, abdominal pain, nausea, vomiting, diarrhea, dysuria, urinary frequency, or headache. Temperature is 38.3 C (101 F), blood pressure is 121/73 mm Hg, pulse is 102/min, and respirations are 22/min. Oxygen saturation is 92% on 2 L of oxygen by nasal cannula. She does not appear ill. The lungs are clear to auscultation. The abdomen is soft and nontender. Neurologic examination is nonfocal. The operative site is healing well without erythema or purulence. The patient's 2 peripheral IV lines have no evidence of infection. Indwelling urinary catheter is draining clear yellow urine. Laboratory results are as follows:
Chest x-ray shows no new abnormalities. Urinalysis is normal. Blood cultures are sent. Which of the following would be the most appropriate next step for this patient? (Multiple Choice)
4.9/5 (68)
(68) A 28-year-old man comes to the office for a health maintenance visit. He has no history of serious illness but reports periodic headaches over the last several years that often respond to acetaminophen. Occasionally the headaches are severe enough to necessitate taking a sick day from work. He cannot recall specific triggers but notes that the headaches are usually unilateral. The patient does not use tobacco or illicit drugs. He drinks alcohol socially and 2-3 cups of coffee daily. He is a software engineer and often works at a computer 10-12 hours a day. His sister has a history of migraines. Vital signs are within normal limits. Physical examination, including neurological examination, is normal. The patient states that the prior headaches were of similar nature and recurred several days in a row before remitting. Recently, the periods of active headaches have increased in duration with no remission. Which of the following is the best pharmacotherapy for headache prevention in this patient?
(Multiple Choice)
4.9/5 (76)
(76) A 25-year-old woman, gravida 1 para 1, comes to the office for evaluation of fever and right breast pain. The patient is 2 weeks postpartum after an uncomplicated pregnancy and vaginal delivery. She has been breastfeeding every 2-3 hours; however, the infant has had difficulty with latching due to the mother's inverted nipples. Yesterday, the patient developed constant sharp pain in the side of her right breast as well as fever, chills, nausea, and body aches. The pain is worsening, especially during breastfeeding. She has been taking acetaminophen and ibuprofen with minimal relief. The patient has no chronic medical conditions. She is on maternity leave from her engineering job. The patient has no drug allergies and is taking a daily prenatal vitamin. Temperature is 38.9 C (102 F), blood pressure is 110/70 mm Hg, and pulse is 100/min. Examination reveals the upper outer quadrant of the right breast to be erythematous, tender, and swollen but without fluctuance. The left breast has no erythema or tenderness. The patient had planned to breastfeed her infant exclusively for the first year of life but is now discouraged by the infection and the discomfort that occurs during latching. Which of the following is the most appropriate advice for this patient?
(Multiple Choice)
4.9/5 (82)
(82) A 7-year-old boy is brought to the emergency department with nausea, vomiting, and abdominal pain. He has been increasingly tired for the past month and has experienced abdominal pain and nausea for the past 2 days. His temperature is 36.7 C (98 F), blood pressure is 92/56 mm Hg, pulse is 134/min, and respirations are 24/min. Physical examination shows a tired but cooperative patient with dry mucous membranes. His lungs are clear to auscultation. The abdomen is soft, nondistended, and mildly tender in all quadrants. Bowel sounds are normal. There is no rebound or guarding. Laboratory results are as follows:  Urinalysis shows a specific gravity of 1.030, ketonuria, and glucosuria. A 10-mL/kg bolus of normal saline is administered intravenously over an hour. An insulin drip is then started. Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.8/5 (74)
(74) A 56-year-old obese female comes to the emergency department (ED) for evaluation of sudden-onset left-sided lower chest pain and shortness of breath. Her past medical history includes cholelithiasis, hypertension, hypothyroidism, and hyperlipidemia. Her medications are hydrochlorothiazide, amlodipine, aspirin, and levothyroxine. She has a 35-pack-year smoking history and continues to smoke one pack of cigarettes daily. Initial work-up in the ED reveals a large left-sided pulmonary embolism, left lower lobe pulmonary infarction, and right popliteal vein thrombosis. She is admitted to the hospital and started on subcutaneous enoxaparin and warfarin. On the third hospital day, she develops weakness and dizziness and produces 500 ml of coffee grounds emesis. Physical examination reveals a temperature of 36.7 C (98 F), heart rate of 110/min, blood pressure of 98/54 mmHg, and respiratory rate of 26/min. Her hemoglobin level is 9.8 g/dL (12.6 g/dL on admission) and platelet count is 320,000/mm3 (210,000/mm3 on admission). Upper gastrointestinal endoscopy shows multiple stomach ulcers and erosions. She is started on high-dose pantoprazole. Which of the following is the most appropriate next step in the management of this patient?
(Multiple Choice)
4.9/5 (77)
(77) A 41-year-old woman comes to the physician because of pain and persistent morning stiffness in both hands. She has had these symptoms for the past six months. She has used ibuprofen and tapering steroids; however, as soon as she stops using the steroids, the stiffness and pain recur. She does not use tobacco, alcohol, or drugs. Examination reveals synovitis in both metacarpophalangeal and proximal interphalangeal joints, bilaterally. Further workup revealed systemic lupus erythematosus. She is started on chronic steroid therapy with prednisone 7.5 mg/day along with hydroxychloroquine. Which of the following is the most appropriate next step in managing this patient?
(Multiple Choice)
4.8/5 (72)
(72) A 47-year-old woman comes to a multidisciplinary community health center. She is uninsured, and the center's social worker counsels the patient regarding options for insurance enrollment. The patient reports high levels of stress due to financial constraints and the recent deaths of her sister and mother from breast cancer. She wishes to establish care with a primary care physician to be screened for breast cancer and discuss cancer prevention. The patient is eligible to enroll in a private health insurance plan through the Health Insurance Marketplace exchange. She states, "Every dollar counts right now. I'm scared the doctor will charge me a big fee to get a mammogram." Which of the following best describes this patient's expected out-of-pocket spending to obtain a mammogram?
(Multiple Choice)
4.8/5 (79)
(79) A 42-year-old woman, gravida 6 para 6, is evaluated in the postpartum unit on postoperative day 2 after a cesarean delivery. The patient has had increasing vaginal bleeding, abdominal pain, and fever. She is breastfeeding exclusively with a good latch. The patient was initially admitted to the hospital for prelabor rupture of membranes at 40 weeks gestation. A primary cesarean delivery was performed for arrest of descent of a 5-kg (11-lb) infant after 3 hours of pushing. The pregnancy was complicated by recurrent vaginal candidiasis. Prior pregnancies were uncomplicated; the patient's last delivery was 12 years ago. Temperature is 38.7 C (101.7 F), blood pressure is 110/70 mm Hg, pulse is 114/min, and respirations are 18/min. On physical examination, the patient appears pale and tired. The lungs are clear to auscultation bilaterally; the breasts are full but without erythema. The uterine fundus is tender to palpation. Speculum examination shows heavy lochia but no active bleeding. The transverse incision across the lower abdomen is intact and without erythema or drainage. Item 1 of 2
Which of the following is the most appropriate pharmacotherapy for this patient?
(Multiple Choice)
4.8/5 (75)
(75) A 45-year-old woman comes to the emergency department due to worsening fatigue. Today, she was so tired that she became short of breath doing household chores. She has also had "spots" on her extremities and seems to bruise very easily. The patient has had no fever, night sweats, cough, chest pain, palpitations, or abdominal pain. She has no chronic medical problems and has had no recent cold or flu symptoms. She does not take any medications and does not use tobacco, alcohol, or illicit drugs. Temperature is 38 C (100.4 F), blood pressure is 110/60 mm Hg, pulse is 92/min, and respirations are 16/min. Physical examination shows moist mucous membranes, clear lung fields, and normal heart sounds. The abdomen is soft and nontender with no hepatosplenomegaly. Neurologic examination is within normal limits. The extremities have no edema, but there are scattered petechiae and ecchymoses bilaterally. Laboratory results are as follows: 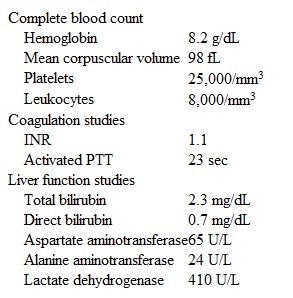 Chest x-ray is normal. A peripheral blood smear is shown in the exhibit.
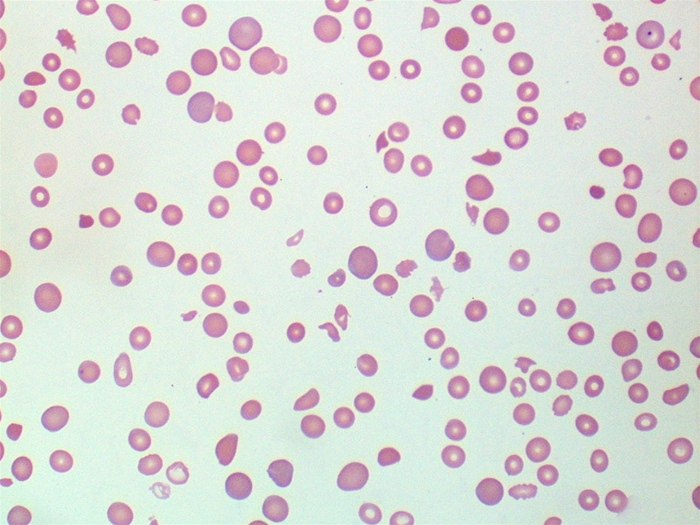 Which of the following is the goal of the first-line therapy for this patient's current condition?
Chest x-ray is normal. A peripheral blood smear is shown in the exhibit. Which of the following is the goal of the first-line therapy for this patient's current condition? (Multiple Choice)
4.9/5 (78)
(78) A 43-year-old man comes to the office due to a cough. The patient started with symptoms of nasal congestion, sore throat, and cough about 10 days ago, and most of the symptoms have since improved. However, the cough is persistent throughout the day and is productive of yellow sputum. He has no fever, chills, weight loss, or night sweats. The patient has had no prior respiratory problems, shortness of breath, sick contacts, or recent travel. He has taken lisinopril for hypertension and metformin for type 2 diabetes mellitus for the past 5 years. His last hemoglobin A1c was 6.6%. The patient has smoked half a pack of cigarettes daily for 5 years and is currently trying to quit. He drinks 1 or 2 cans of beer daily but does not use illicit drugs. Family history includes diabetes in multiple family members. Temperature is 36.1 C (97 F), blood pressure is 130/80 mm Hg, pulse is 65/min, and respirations are 14/min. The patient's pulse oximetry shows 99% on room air. On examination, the patient is in no apparent distress and appears his stated age. Mucous membranes are moist, and no lymphadenopathy or jugular venous distension is present. Heart rate is regular with normal S1 and S2. Bilateral scattered rhonchi are auscultated, which clear after expectoration. No crackles, wheezing, or rubs are heard. Percussion is resonant throughout, and normal tactile fremitus is observed. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (77)
(77) A 36-year-old woman comes to the physician due to low back pain. The pain began 5 months ago and is getting progressively worse. She describes it as aching, non-radiating, and without any aggravating or relieving factors. The patient underwent Roux-en-Y gastric bypass surgery for morbid obesity 2 years ago, after which she lost about 45.4 kg (100 lb). She takes a daily multivitamin containing calcium (1200 mg elemental calcium) and vitamin D (400 IU of cholecalciferol). She eats a normal diet. Spinal examination shows no focal tenderness. Laboratory results are as follows:  Bone mineral density, performed using dual-energy x-ray absorptiometry, reveals a T-score of -2.0 at the lumbar spine and -1.5 at the hip. Serum parathyroid hormone level is 955 pg/mL. Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.7/5 (66)
(66) A 4-year-old boy is brought to the emergency department by his mother due to refusing to walk since this morning. The patient started having right groin pain 2 days ago after T-ball practice, and his mother noticed him "walking funny" yesterday. She says, "I had to carry him here because he says it hurts too much to walk." The mother has witnessed no recent falls or injuries, and the symptoms have not improved with acetaminophen. The patient has had upper respiratory symptoms for the last 2 weeks and was diagnosed with viral pharyngitis a week ago. He has a history of atopic dermatitis that is controlled with low-dose topical corticosteroids. Immunizations are up to date. He takes no medications and has no known allergies. Temperature is 38.6 C (101.5 F). The patient appears tired but nontoxic. The posterior pharynx is clear and without exudates. The lungs are clear to auscultation. On examination of the right hip, the patient cries and resists passive movement. There is decreased range of motion of the right hip. Dry, erythematous patches are noted on the bilateral forearms. Laboratory findings show a white blood cell count of 14,000/mm3 and a C-reactive protein of 4.0 mg/L (normal: <3.0 mg/L). The patient undergoes aspiration of the right hip joint. Synovial fluid analysis shows a white blood cell count of 60,000/mm3 with a neutrophil predominance. Gram stain and culture are pending. Immediate initiation of which of the following therapies is most important to improve the long-term outcome of this patient's condition?
(Multiple Choice)
5.0/5 (83)
(83) A 27-year-old woman, gravida 1 para 0, at 28 weeks gestation comes to the office for a routine prenatal visit. Her initial prenatal laboratory results at 12 weeks gestation were as follows:  The patient reports no vaginal bleeding, leakage of fluid, or contractions. There is good fetal movement. She has increasing urinary frequency and nocturia but no dysuria or hematuria. The patient has a history of tension headaches, which have become more frequent but resolve with acetaminophen. She has no other chronic medical conditions or previous surgeries. The patient works in a retirement home and reports leg swelling at the end of her shift. She is a vegetarian and takes a daily prenatal vitamin. She does not use tobacco, alcohol, or illicit drugs. Temperature is 37 C (98.6 F), blood pressure is 128/76 mm Hg, and pulse is 86/min. BMI is 30 kg/m2; the patient has been gaining 0.5 kg (1.1 lb) a week during the pregnancy. The fetal heart rate is 152/min. Examination shows a uterus consistent with a 28-week gestation. There is trace lower extremity edema bilaterally. The patient has had no laboratory evaluations since her initial prenatal visit. Item 1 of 3
Which of the following is the most appropriate laboratory evaluation to perform at this visit?
The patient reports no vaginal bleeding, leakage of fluid, or contractions. There is good fetal movement. She has increasing urinary frequency and nocturia but no dysuria or hematuria. The patient has a history of tension headaches, which have become more frequent but resolve with acetaminophen. She has no other chronic medical conditions or previous surgeries. The patient works in a retirement home and reports leg swelling at the end of her shift. She is a vegetarian and takes a daily prenatal vitamin. She does not use tobacco, alcohol, or illicit drugs. Temperature is 37 C (98.6 F), blood pressure is 128/76 mm Hg, and pulse is 86/min. BMI is 30 kg/m2; the patient has been gaining 0.5 kg (1.1 lb) a week during the pregnancy. The fetal heart rate is 152/min. Examination shows a uterus consistent with a 28-week gestation. There is trace lower extremity edema bilaterally. The patient has had no laboratory evaluations since her initial prenatal visit. Item 1 of 3
Which of the following is the most appropriate laboratory evaluation to perform at this visit? (Multiple Choice)
4.9/5 (92)
(92) A 65-year-old woman comes to the physician with a 5-day history of rash and generalized itching. She initially developed a rash on her hand that spread to her feet, abdomen, and groin area. The patient also has intense pruritus that is worse at night. Her husband started having similar symptoms approximately 3 days ago. She works as a patient aide in a nursing home and has no other medical conditions. The patient had chickenpox when she was 7 years old. Her vital signs are within normal limits. Skin examination (image below) shows multiple small erythematous papules on her palms, sides of the fingers, wrists, lateral aspect of the feet, and periumbilical area. Her husband has similar lesions on the same body parts and also over the shaft of his penis. The remainder of her examination is within normal limits. 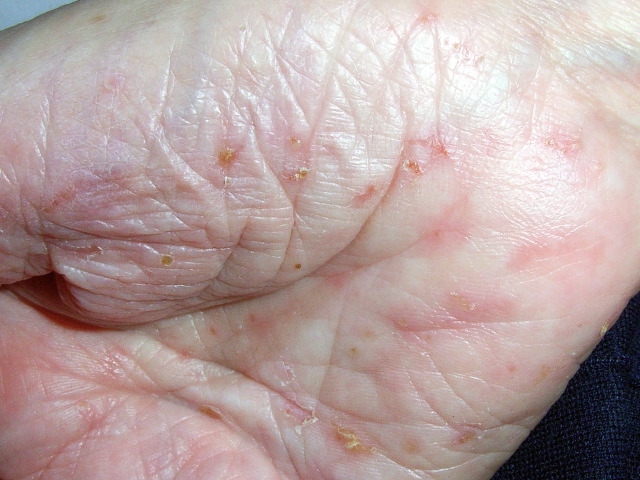 Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (74)
(74) A 22-year-old woman comes to the physician with her husband for intermittent dizziness, weakness, and unsteady gait for the last several weeks. She has also had visual loss and pain in the right eye that worsens with eye movement for the past 2 days. A year ago, the patient had tingling and numbness of her right hand accompanied by unsteadiness, which improved spontaneously after 3-4 days. She has no other medical problems and does not take any medications. The patient has no significant social or family history. Her temperature is 37.2 C (99 F), blood pressure is 122/80 mm Hg, pulse is 82/min, and respirations are 16/min. On neurologic examination, her right eye has diminished visual acuity and an afferent pupillary defect. She also has a right arm intention tremor. Both lower extremities have spastic paresis, hyperreflexia, and positive Babinski sign. Item 1 of 5
Which of the following is the most appropriate test to confirm the diagnosis in this patient?
(Multiple Choice)
4.8/5 (90)
(90) A 15-year-old girl is brought to the office after falling in the shower. Her mother was outside of the bathroom when she heard a thud, and went in and found her daughter trying to get back up. The patient insists, "I just slipped. It's no big deal. I am fine." She reports that she had no loss of consciousness, tongue biting, incontinence, or confusion. Her parents are concerned that she lost her balance because she is thin and eats poorly. They also note that she seems depressed and has not been interested in seeing any friends. The patient admits, "I have been a little down since my boyfriend broke up with me, but I don't blame him because I am so fat." She takes no medications, has no allergies, and does not use tobacco, alcohol, or illicit drugs. Temperature is 35.6 C (96 F), blood pressure is 100/60 mm Hg sitting and 80/48 mm Hg standing, pulse is 50/min, and respirations are 14/min. BMI is 16 kg/m2. Examination shows an alert and cooperative girl with dry mucous membranes and emaciation. Calluses are present over the knuckles. The abdomen is soft, nontender, and nondistended. Urine hCG is negative. Laboratory results are as follows:
 Item 1 of 2
Which of the following is the most appropriate next step in management of this patient?
Item 1 of 2
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.9/5 (69)
(69) A 43-year-old man comes to the office for follow up regarding back pain. He had acute onset of pain in the low back radiating to the buttocks 3 weeks ago after lifting heavy bags of fertilizer at his farm. The patient was treated with naproxen; with treatment, his pain has decreased from an 8/10 to 3/10 in severity, and he no longer has radiation of the pain. Medical history is notable only for 2 prior episodes of back pain in the last year. Vital signs are normal. BMI is 33 kg/m2. Physical examination shows no spinal tenderness, normal lower extremity strength and reflexes, and a negative straight-leg raising test bilaterally. The patient asks what is needed to prevent future episodes of back pain. Which of the following is the most appropriate response to this patient's question?
(Multiple Choice)
4.9/5 (85)
(85) Showing 201 - 220 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)