



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


A 28-year-old man comes to the office for a health maintenance visit. He has no history of serious illness but reports periodic headaches over the last several years that often respond to acetaminophen. Occasionally the headaches are severe enough to necessitate taking a sick day from work. He cannot recall specific triggers but notes that the headaches are usually unilateral. The patient does not use tobacco or illicit drugs. He drinks alcohol socially and 2-3 cups of coffee daily. He is a software engineer and often works at a computer 10-12 hours a day. His sister has a history of migraines. Vital signs are within normal limits. Physical examination, including neurological examination, is normal. Item 1 of 4
Which of the following is the best next step in management of this patient's headaches?
(Multiple Choice)
5.0/5  (88)
(88) A 68-year-old white male with a history of paroxysmal atrial fibrillation, hypertension, and hypercholesterolemia is brought to the physician's office by his daughter because of nausea, anorexia, and confusion. His daughter states that he was admitted at an outside hospital two weeks ago because of uncontrolled hypertension and palpitations. He was started on a new medication. Prior to the recent hospitalization, he was taking digoxin, warfarin, simvastatin, and hydrochlorothiazide. His physical examination shows an irregular heart rate, but is otherwise unremarkable. His blood pressure is 130/80 mmHg, pulse rate is 50/minute and irregular, temperature 37.2C (99F), and respirations are 14/minute. Which of the following is the most likely medication that is contributing to his symptoms?
(Multiple Choice)
4.9/5 (72)
(72) A 67-year-old man comes to the emergency department due to abdominal cramps, diarrhea, and fever that started 3 days ago. The patient initially had 3 or 4 stools per day for 2 days but, today, had 7 watery stools; the stools have not had gross blood or mucus or black discoloration. The patient has also had generalized weakness and malaise. Two weeks ago, he was treated with oral antibiotics for acute cellulitis. Since then, the patient's appetite has decreased, and he has had mild bloating. He has no history of recent travel, unusual foods, or sick contacts with similar symptoms. Other medical conditions include type 2 diabetes mellitus, hypertension, and hyperlipidemia. Temperature is 38.7 C (101.7 F), blood pressure is 110/70 mm Hg, and pulse is 95/min. Physical examination shows moderate abdominal tenderness. The cellulitis has resolved. Leukocytes are 26,000/mm3, serum creatinine is 1.9 mg/dL (increased from 1.2 mg/dL 2 months ago), and serum albumin is 2.9 g/dL. The patient does not want to be admitted to the hospital and would like to be treated as an outpatient.
Stool PCR testing for Clostridioides difficile PCR is positive. The patient is adamant about going home. He is given a prescription for oral fidaxomicin and discharged home against medical advice. The patient returns 2 days later feeling much worse. He says, "I just got the pills today and have taken only one dose." Temperature is 38.9 C (102 F), blood pressure is 90/60 mm Hg, pulse is 114/min, and respirations are 24/min. The patient appears uncomfortable. The abdomen is distended, and bowel sounds are decreased; there is tenderness and guarding to palpation. CT scan of the abdomen shows diffuse colonic wall thickening and dilation. In addition to the appropriate oral pharmacotherapy, what is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (69)
(69) A 29-year-old woman, gravida 1 para 0, at 18 weeks gestation comes to the emergency department due to severe right flank pain. The pain is sharp and paroxysmal and radiates to her labia. When the pain occurs, she has associated nausea and vomiting. The patient has no fever, hematuria, dysuria, or increased urinary frequency. She has no chronic medical conditions and has had no surgeries. Her pregnancy had been uncomplicated and initial prenatal laboratory testing was normal. The patient takes a daily prenatal vitamin and does not use tobacco, alcohol, or illicit drugs. Temperature is 36.7 C (98 F), blood pressure is 110/60 mm Hg, and pulse is 100/min. BMI is 32 kg/m2. The abdomen is tender to palpation along the right side, but there is no rebound or guarding. Pelvic examination reveals an 18-week-sized uterus. Laboratory results are as follows:  Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.8/5 (83)
(83) A 12-year-old boy is brought to the clinic by his mother for a preparticipation sports physical. The patient will be starting 6th grade in a few weeks and would like to join his school's cross-country team. He ran several short races last year and had no chest pain, shortness of breath, or dizziness. Last year, he did well in school and received mostly As and Bs. The patient has a good relationship with his parents and has many friends. He wears eyeglasses for myopia. He has no allergies or other medical conditions. His grandfather died of a "brain bleed" at age 75. The patient's height and weight are at the 98th and 50th percentiles, respectively. Temperature is 37 C (98.6 F), blood pressure is 110/72 mm Hg, pulse is 80/min, and respirations are 20/min. Cranial nerves II-XII are intact. Cardiac examination reveals a regular rate and rhythm. The lungs are clear to auscultation bilaterally. Achilles and patellar deep tendon reflexes are 2+ bilaterally. The patient's arm span to height ratio is increased. Physical examination is otherwise unremarkable. Which of the following is the best next step in management?
(Multiple Choice)
4.9/5 (72)
(72) A 33-year-old Caucasian female presents to your office with a six-month history of cold intolerance. When the weather is cold, her third and fourth fingers on both hands get numb and turn blue. She says, 'I wear gloves to keep my hands warm, but it does not always work'. Her past medical history is significant for non-ulcer dyspepsia treated with omeprazole. She does not smoke or consume alcohol, and denies any recreational drug use. She has no known drug allergies. She works as a nurse at a local hospital and considers her job moderately stressful. She is sexually active with her husband and uses condoms for contraception. Physical examination findings are within normal limits.
The patient returns in one month and complains that the treatment 'does not help much.' In addition, she has started to experience periodic joint and muscle pain. She says that she has been adherent to the medication and has tried to avoid going out in cold weather as much as possible. Her husband even gave up smoking because you had warned her that passive smoking may worsen her condition. Which of the following is the best next step in the management of this patient?
(Multiple Choice)
4.8/5 (91)
(91) A 21-year-old woman, gravida 1 para 1, comes to the emergency department for abdominal pain and a severe headache. The pain started 2 days ago in the epigastrium and now radiates to the right upper quadrant. The pain was initially responsive to acetaminophen but has become increasingly severe. The patient also reports an occipital headache accompanied by blurry vision. A week ago, she had an uncomplicated vaginal delivery at 39 weeks gestation and, after a normal postpartum course, was discharged on day 2. The patient has a history of migraines for which she typically takes daily prophylactic medication. She stopped the medication when she became pregnant. Temperature is 36.7 C (98 F), blood pressure is 150/90 mm Hg, and pulse is 94/min. The visual fields are normal and there is no nuchal rigidity. Abdominal examination reveals tenderness to palpation over the epigastrium and right upper quadrant, and there is hepatomegaly. Bilateral lower extremities have 2+ pitting edema to the knees. Laboratory results are as follows:  Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (71)
(71) A 36-year-old man comes to the office due to frequent "loose stools" for the past 10 months. The patient describes stools that are large in volume, liquid to semisolid, occurring up to 3-4 times a day, and often foul-smelling. He also reports excessive flatulence and occasional nausea and abdominal cramping. The patient says he may have lost some weight because his clothes are much looser than before. He has no prior medical problems and takes no medications. Family history is notable for hypertension and coronary artery disease in his father. The patient immigrated to the United States from Italy with his family when he was 2 years old and has not traveled out of the country since then. He does not use tobacco or illicit drugs and drinks alcohol occasionally. The patient works in a family-owned restaurant and has had no sick contacts. He consumes a balanced diet and notes no specific association of diarrhea to food. The patient has been in a monogamous relationship with his wife for the past 10 years. Temperature is 36.6 C (97.9 F), blood pressure is 130/86 mm Hg, and pulse is 72/min. Weight is 63.5 kg (140 lb). The sclerae are anicteric, and mucous membranes are moist without any lesions. Cardiopulmonary examination is unremarkable. The abdomen is soft, nondistended, and nontender, with no organomegaly. Bowel sounds are increased. Rectal examination shows no masses or tenderness and an empty rectal vault. Stool occult blood testing is negative. Samples for blood count, erythrocyte sedimentation rate, TSH, and serum electrolytes are obtained. The patient comes for a follow-up visit 2 weeks later. He continues to have large-volume, foul-smelling stools but has had no new symptoms. The patient recollects that his weight was about 75 kg (165 lb) prior to the onset of symptoms, and he has lost more than 5 kg (11 lb). Physical examination findings are unchanged. Laboratory testing performed during the previous visit is notable for the following:  Stool studies revealed a high osmotic gap. Further laboratory studies are ordered. Gastrointestinal endoscopy with biopsy is most likely to reveal which of the following?
 (Multiple Choice)
4.7/5 (72)
(72) A 17-year-old boy is evaluated for abnormal urinalysis findings. He came to the clinic 2 weeks ago with low back pain, and a urinalysis at that time showed 2+ protein. He currently feels fine and has no urinary complaints. The patient has not exercised vigorously or taken any medications. He has no other medical problems and received all appropriate childhood vaccinations. He does not use tobacco or illicit drugs. The patient is not sexually active. His father had early coronary disease and a stroke. His blood pressure is 112/70 mm Hg and pulse is 77/min. BMI is 24 kg/m2. Physical examination shows no abnormalities. Laboratory results from this visit are as follows:  Urine sediment microscopy is unremarkable for casts. A 24-hour urine collection shows 600 mg of protein (normal <150 mg).
Ultrasound of the kidneys shows no abnormalities. Split urine collection shows 40 mg of protein overnight (8 hours) and 500 mg of protein during the day (16 hours). Which of the following is the best next step in management of this patient?
Urine sediment microscopy is unremarkable for casts. A 24-hour urine collection shows 600 mg of protein (normal <150 mg).
Ultrasound of the kidneys shows no abnormalities. Split urine collection shows 40 mg of protein overnight (8 hours) and 500 mg of protein during the day (16 hours). Which of the following is the best next step in management of this patient? (Multiple Choice)
4.8/5 (88)
(88) A 72-year-old man is evaluated in his hospital room for hypoxemia and shortness of breath. He says, "I just can't seem to get enough air to breathe." He also has a cough that is intermittently productive of white sputum. The patient underwent emergency open colectomy 3 days ago for cecal volvulus. His course was complicated by postoperative respiratory failure, and he remained on a mechanical ventilator for 48 hours. He was extubated 12 hours ago and has since had significant pain around the incision site, receiving opioid medications as needed. Medical history includes hypertension, ischemic stroke with resulting left-sided weakness, and coronary artery disease. The patient has smoked a pack of cigarettes a day for the last 45 years. He has no history of alcohol or drug abuse. Temperature is 37 C (98.6 F), blood pressure is 145/90 mm Hg, pulse is 90/min, and respirations are 24/min. Oxygen saturation is 87% on room air. The patient appears chronically ill and drowsy. Examination shows moist mucous membranes and normal jugular venous pressure. Respirations are shallow and limited by pain around the incision. The patient has a weak cough with no stridor. Breath sounds are diminished at the bilateral lung bases, with scattered rhonchi. Heart sounds are normal. The abdomen is mildly distended and tender near the incision site. The surgical wound appears clean and is without discharge. There is 1+ bilateral edema of the lower extremities. A complete blood count and metabolic panel are normal. Arterial blood gas analysis on room air shows a pH of 7.47, PaO2 of 56 mm Hg, and PaCO2 of 33 mm Hg. Chest x-ray reveals small lung volumes and bilateral linear densities of the lower lobe. In addition to the supplemental oxygen to correct the hypoxemia, which of the following is most beneficial for treating this patient's respiratory symptoms?
(Multiple Choice)
4.8/5 (76)
(76) A 2-week-old girl is brought to the office because she looks "a bit yellow." She was born at 40 weeks gestation by normal spontaneous vaginal delivery to a mother whose blood type is AB+. Apgar scores were 9 (-1 color) and 9 (-1 color) at 1 and 5 minutes, respectively. Birth weight, length, and head circumference were at the 50th percentile. She was discharged home on the second day of life and has been breastfeeding every 2-3 hours for 15 minutes on each side. The infant has 6 wet diapers and 5-6 yellow seedy stools per day. She has regained her birth weight and has normal vital signs. Physical examination shows an active, crying infant with moist mucous membranes and jaundice of the face, neck, and chest. The remainder of the examination is normal. Total bilirubin is 10 mg/dL and direct bilirubin is 0.6 mg/dL. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
5.0/5 (83)
(83) A 46-year-old woman, gravida 2 para 2, comes to the office due to increasingly heavy menses. The patient's menstrual periods previously occurred every 30 days and consisted of 4-5 days of moderate bleeding with mild cramping. However, over the past 6 months, her menses have consisted of 5-6 days of heavy bleeding with the passage of clots and severe abdominal cramping. The cramping has been unresponsive to consistent ibuprofen administration. The patient reports increasing fatigue and often sleeps 9-10 hours a night. She had 2 vaginal deliveries and a tubal ligation after the birth of her second child. The patient has no known chronic medical conditions. In addition to ibuprofen, she takes a daily multivitamin. The patient is an accountant and is unable to work during her menstrual cycle due to the pain. She drinks a glass of wine with dinner most days of the week but does not use tobacco or illicit drugs. Temperature is 37 C (98.6 F), blood pressure is 120/70 mm Hg, and pulse is 105/min. BMI is 22 kg/m2. The thyroid is nontender with no obvious enlargement or masses. Pelvic examination reveals a uniformly enlarged, mobile uterus. No rectovaginal or adnexal tenderness is present. On speculum examination, the vagina appears well rugated and the cervix has no visible lesions. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (76)
(76) A 2-year-old boy is brought to the emergency department by his grandmother due to abdominal pain and lethargy. The grandmother reports that he was playing calmly last night when he suddenly began screaming and holding his abdomen. The pain resolved after several minutes, but the patient has had 5 additional episodes of sudden-onset, severe pain since then. Today, the grandmother notes that he has no interest in eating or drinking and has been "sleeping all day" but intermittently awakens in pain. The patient has also had several episodes of nonbloody, nonbilious emesis and "fewer wet diapers than usual." He has had no fever, diarrhea, or recent infections. He is an otherwise healthy child with no prior hospitalizations or chronic medical conditions. The patient takes no medications, and his immunizations are up to date. Temperature is 37 C (98.6 F), blood pressure is 90/56 mm Hg, pulse is 160/min, and respirations are 24/min. During the examination, the boy is sleeping and arouses briefly. The abdomen has hypoactive bowel sounds and diffuse mild tenderness to palpation. He is circumcised, with both testes descended and with intact cremasteric reflexes. Immediately after the examination, the child passes blood in his diaper, as shown in the image below. 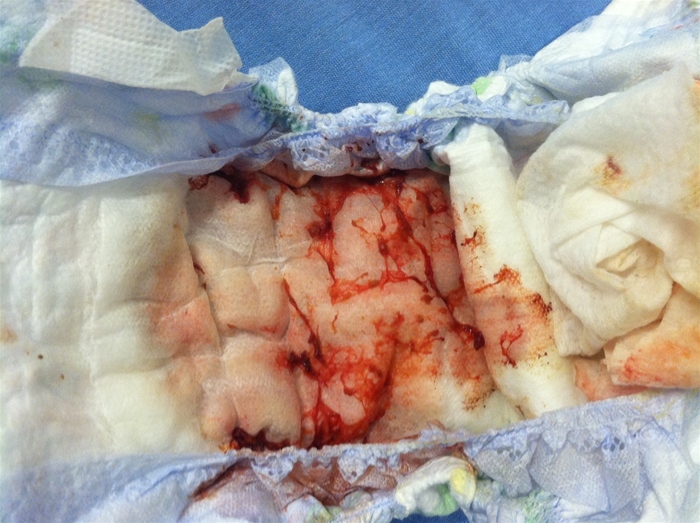 The medical team has determined the appropriate procedure. The patient lives with his parents and his grandmother about an hour away from the hospital. His grandmother drove him to the emergency department but is not his legal guardian. She states, "His mom should be on the way; she probably just left the house." However, despite multiple attempts, the medical team is unable to reach either of the patient's parents by telephone. Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.8/5 (76)
(76) A 57-year-old woman comes to the office due to discomfort in her right hand. She reports that periodically her fingers "feel numb, with some tingling, sort of like they fell asleep." When the patient shakes her hands, normal sensation is partially restored. The symptoms are more often present at night but are occasionally experienced during the daytime as well. She has not had abnormalities of sensation on the dorsal surfaces of her hands, and she reports no shoulder or neck pain. There is no history of injury to the upper extremities. Medical history is notable for irritable bowel syndrome, mitral valve prolapse, degenerative knee arthritis, and hypertension controlled with lisinopril. She also takes an over-the-counter fiber supplement. The patient works as a bookkeeper. She does not use tobacco, alcohol, or illicit drugs. Vital signs are normal. BMI is 32 kg/m2. Neurologic examination shows no sensory loss, muscle weakness, or muscle atrophy in the right upper extremity. The patient comes for follow-up 6 weeks after the initial visit. She has had no noticeable benefit from initial treatment measures and reports that she has had to reduce her work hours due to increasingly severe symptoms. Which of the following tests should be offered to this patient?
(Multiple Choice)
4.7/5 (76)
(76) A 39-year-old man comes to the outpatient clinic due to burning epigastric discomfort and nausea for the past 3 months. His symptoms are worse after meals. He has been taking over-the-counter ranitidine for the last 2 weeks with no relief of symptoms. The patient has no other medical issues, and family history is unremarkable. He does not use tobacco, alcohol, or illicit drugs. Physical examination shows no abnormalities. Hemoglobin is 15.4 g/dL and serum creatinine is 0.8 mg/dL. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (89)
(89) An 82-year-old woman comes to the office due to a day of low-grade fever and rash. Two days ago, the patient began having stabbing pain in her left flank. Over the following day, this area became itchy and red. The patient tried over-the-counter topical hydrocortisone and lidocaine but had no relief. She has a history of hypothyroidism, type 2 diabetes mellitus, rheumatoid arthritis, and osteoporosis. She was recently hospitalized for sepsis secondary to a urinary tract infection and discharged on oral ciprofloxacin that she completed yesterday. The patient has no history of drug allergy but noticed a "strange taste in my mouth" after taking ciprofloxacin. Her other medications include low-dose aspirin, alendronate, levothyroxine, glipizide, low-dose prednisone, calcium, and vitamin D supplementation. She does not smoke, consume alcohol, or use illicit drugs. Temperature is 37.8 C (100 F), blood pressure is 124/72 mm Hg, pulse is 92/min, and respirations are 14/min. Examination of her left flank shows bright patchy erythema, excoriations, and several fluid-filled blisters.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (83)
(83) A 12-year-old boy is brought to the emergency department by his parents due to left arm pain. He was competing in a basketball tournament and fell on his left arm while his left hand was outstretched and immediately experienced severe pain. The patient has seasonal allergies for which he takes loratadine daily. Immunizations are up to date. Physical examination reveals a tearful and anxious boy in moderate distress. There is significant swelling over the left elbow, and the patient has limited range of motion at the elbow secondary to pain. He can fully extend and flex all 5 digits. Radial pulse is palpable, and there is brisk capillary refill. There is no tenderness to palpation over the wrist or forearm. Radiograph of the elbow is shown below and reveals a displaced posterior fat pad in the olecranon fossa. In addition to administration of pain medication, which of the following is the most appropriate next step in management of this patient? 
(Multiple Choice)
4.9/5 (98)
(98) A 39-year-old woman, gravida 3 para 2, at 7 weeks gestation comes to the emergency department for vaginal bleeding that began 3 hours ago and has soaked through a pad. Since her arrival, the bleeding has subsided. She reports no abdominal pain or cramping. Her first prenatal visit is in 1 week. The patient has a history of HIV, contracted 3 years ago through unprotected sexual intercourse, but she has declined treatment as she has felt "healthy." She has no previous surgeries. The patient's 2 prior pregnancies ended in uncomplicated term vaginal deliveries; the last delivery was 4 years ago. Her last Pap test, 4 years ago, was normal. She has smoked half a pack of cigarettes a day for 13 years but does not drink alcohol or use illicit drugs. Blood pressure is 130/80 mm Hg and pulse is 82/min. BMI is 24 kg/m2. Abdominal examination shows no tenderness or masses. The external genitalia have no lesions. Speculum examination reveals minimal bright red blood in the vaginal vault. The cervix is closed and there is a 3-cm, firm, white, irregular mass on the anterior cervix that bleeds when touched with a cotton applicator. Laboratory results are as follows:  A bedside transvaginal ultrasound reveals an intrauterine gestation with normal fetal cardiac activity. Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.7/5 (84)
(84) A 65-year-old female is admitted to the intensive care unit for chest pain where she is diagnosed with a non-ST elevation myocardial infarction. She has a history of hypertension, type 2 diabetes mellitus, hyperlipidemia, and osteoporosis. Over the last two months, she has been getting occasional chest pain on exertion. She also complains of some recent fatigue and mild constipation. Cardiac catheterization is performed and shows severe triple-vessel coronary artery disease. A coronary artery bypass graft procedure (CABG) is planned. Her laboratory values include the following:
 Which of the following is the most appropriate next step in the management of this patient?
 (Multiple Choice)
4.9/5 (76)
(76) A 52-year-old woman undergoes laparoscopic cholecystectomy due to recurrent episodes of biliary colic. During the surgery, a blunt trocar is inserted near the umbilicus under direct vision (ie, open technique), and pneumoperitoneum is achieved via insufflation of the abdomen with carbon dioxide. Three additional trocars are inserted, and the cholecystectomy is completed uneventfully. After a period of observation in the postanesthesia care unit, the patient is discharged home. Three days later, the patient returns to the emergency department due to persistent abdominal pain and nausea. She takes acetaminophen and hydrocodone every 6 hours. Temperature is 38 C (100.4 F), blood pressure is 120/68 mm Hg, and pulse is 104/min. Physical examination shows intact port incisions with no erythema or discharge. There is mild generalized tenderness of the abdomen with some guarding. Bowel sounds are diminished. The remainder of the examination is normal. Laboratory testing shows leukocytes at 16,000/mm3; serum electrolytes and bilirubin are normal. Abdominal x-ray reveals generalized distension of the small and large bowel, stool in the distal colon, and intraperitoneal free air. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (79)
(79) Showing 541 - 560 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)