



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


A 30-year-old woman, gravida 1 para 0, at 34 weeks gestation comes to the office for a prenatal visit. The patient reports no abdominal pain, vaginal bleeding, or leakage of fluid. Fetal movement is normal. The patient has had urinary frequency throughout her pregnancy, but it has worsened over the last 4 days and is now associated with dysuria. She has no fevers, chills, nausea, vomiting, back pain, or hematuria. The pregnancy has been uncomplicated. The patient has no history of chronic medical conditions and has had no previous surgery. She takes a daily prenatal vitamin. The patient smokes half a pack of cigarettes a day but does not use alcohol or illicit drugs. Temperature is 36.7 C (98.0 F), blood pressure is 126/78 mm Hg, pulse is 76/min, and respirations are 18/min. BMI is 28 kg/m2. Fetal heart rate is 140/min. On physical examination, the uterus is nontender and fundal height is 34 cm. Suprapubic tenderness is elicited with deep palpation. There is no costovertebral angle tenderness. Laboratory results are as follows:  The patient is prescribed an appropriate antibiotic, and a clean-catch urine sample is obtained and sent for culture. The following day, the patient comes to the emergency department with fever, chills, nausea, and flank pain. Temperature is 38.3 C (101 F), blood pressure is 110/70 mm Hg, pulse is 96/min, and respirations are 16/min. The fetal heart rate tracing has a baseline of 170/min, moderate variability, multiple accelerations, and no decelerations. Tocometer shows no contractions. The left costovertebral angle is tender to palpation. Abdominal examination reveals a gravid, nontender uterus and no abdominal tenderness. A digital cervical examination reveals the cervix to be closed, long, and posterior. There is trace pedal edema over the bilateral lower extremities to the knees. Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5  (70)
(70) A 31-year-old man comes to the office with his wife, who is threatening to leave him if he does not get help. The patient was recently fired from his job as a computer programmer due to frequent lateness and absences caused by his elaborate morning showering ritual. He feels compelled to clean each part of his body in a specific order while counting to 27. If he misses a body part or makes a mistake in counting, he must start over. His wife adds that he often takes 3 showers in a row because "he won't accept that the towels I give him were just cleaned. It has become extremely difficult to live with him." Once dressed, the patient must go out of his way to take a certain route to work to avoid "dirty" street corners that may soil or contaminate his clothes. He says, "I know it makes no sense, but I can't get rid of the thought that my clothes are splattered with urine. Once this idea takes hold, I have to go home and change." The patient became concerned with cleanliness as a young teen and wonders whether this was inherited from his mother, whom he describes as "a control freak." He says, "I know I need help but prefer not to take medication if possible."
Which of the following nonpharmacologic approaches would be most effective for this patient?
(Multiple Choice)
4.8/5 (101)
(101) A 54-year-old woman is brought to the emergency department due to disorientation. She was recently on vacation and received treatment with high-dose oral prednisone for severe poison ivy dermatitis. In the emergency department, her temperature is 37 C (98.6 F), blood pressure is 138/80 mm Hg, pulse is 102/min, and respirations are 22/min. The mucous membranes are dry. Laboratory results show random blood glucose of 1020 mg/dL with a normal anion gap. Her hemoglobin A1c is 7.6%. The patient is started on intravenous fluids and an intravenous insulin infusion. After a day on intravenous insulin, her mental status is normal and she is transitioned to subcutaneous regular human insulin based on a sliding scale. Her finger stick blood glucose readings are 200-250 mg/dL. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (67)
(67) A 27-year-old woman, gravida 1 para 0, at 28 weeks gestation comes to the office for a routine prenatal visit. Her initial prenatal laboratory results at 12 weeks gestation were as follows:  The patient reports no vaginal bleeding, leakage of fluid, or contractions. There is good fetal movement. She has increasing urinary frequency and nocturia but no dysuria or hematuria. The patient has a history of tension headaches, which have become more frequent but resolve with acetaminophen. She has no other chronic medical conditions or previous surgeries. The patient works in a retirement home and reports leg swelling at the end of her shift. She is a vegetarian and takes a daily prenatal vitamin. She does not use tobacco, alcohol, or illicit drugs. Temperature is 37 C (98.6 F), blood pressure is 128/76 mm Hg, and pulse is 86/min. BMI is 30 kg/m2; the patient has been gaining 0.5 kg (1.1 lb) a week during the pregnancy. The fetal heart rate is 152/min. Examination shows a uterus consistent with a 28-week gestation. There is trace lower extremity edema bilaterally. The patient has had no laboratory evaluations since her initial prenatal visit. The patient comes to the hospital at 38 weeks gestation in active labor and with spontaneous rupture of membranes. Blood pressure is 130/84 mm Hg and heart rate is 96/min. Fetal heart rate tracing is reassuring. Uterine contractions are regular and occur every 4 minutes. Cervical examination reveals 5-cm dilation, 100% effacement, and a vertex presentation at −1 station. Complete blood count on admission is as follows:
 The patient requests neuraxial labor analgesia.
Which of the following is the most appropriate next step in management of this patient?
The patient reports no vaginal bleeding, leakage of fluid, or contractions. There is good fetal movement. She has increasing urinary frequency and nocturia but no dysuria or hematuria. The patient has a history of tension headaches, which have become more frequent but resolve with acetaminophen. She has no other chronic medical conditions or previous surgeries. The patient works in a retirement home and reports leg swelling at the end of her shift. She is a vegetarian and takes a daily prenatal vitamin. She does not use tobacco, alcohol, or illicit drugs. Temperature is 37 C (98.6 F), blood pressure is 128/76 mm Hg, and pulse is 86/min. BMI is 30 kg/m2; the patient has been gaining 0.5 kg (1.1 lb) a week during the pregnancy. The fetal heart rate is 152/min. Examination shows a uterus consistent with a 28-week gestation. There is trace lower extremity edema bilaterally. The patient has had no laboratory evaluations since her initial prenatal visit. The patient comes to the hospital at 38 weeks gestation in active labor and with spontaneous rupture of membranes. Blood pressure is 130/84 mm Hg and heart rate is 96/min. Fetal heart rate tracing is reassuring. Uterine contractions are regular and occur every 4 minutes. Cervical examination reveals 5-cm dilation, 100% effacement, and a vertex presentation at −1 station. Complete blood count on admission is as follows: The patient requests neuraxial labor analgesia.
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.8/5 (72)
(72) An 82-year-old woman is brought to the emergency department with high-grade fever. She resides at a local nursing home. The nursing home staff reports that in the past few days she has been quieter than usual but is otherwise at her baseline mental status. In the hospital, the patient is calm and cooperative and says that she feels "tired." Medical history includes diabetes mellitus, hypothyroidism, atrial fibrillation, chronic obstructive pulmonary disease, and severe, deforming rheumatoid arthritis. Her history is also significant for severe alcohol use disorder, which is in remission. The patient's medications include aspirin, insulin, albuterol inhaler, levothyroxine, warfarin, and low-dose prednisone. Temperature is 38.9 C (102 F), blood pressure is 126/84 mm Hg, pulse is 92/min, and respirations are 20/min. Oxygen saturation is 96% on 3 L of oxygen. The patient is awake and alert but subdued and minimally conversant. The mucous membranes are extremely dry. The rest of the physical examination is unremarkable. Initial laboratory results are as follows:  Other laboratory results are within normal limits. The patient is admitted to the hospital, and intravenous fluids and antibiotic therapy are administered. During the night, she becomes very restless, confused, and agitated. She pulls out her intravenous line, causing significant bleeding. When the staff arrives, she insists that one of the nurses is her mother, attempts to leave the bed, and pushes an aide aside. Which of the following is the most appropriate course of action?
 (Multiple Choice)
4.8/5 (85)
(85) A 33-year-old woman comes to the emergency department due to abdominal pain. The pain began 2 weeks ago and was initially mild, episodic, confined to the right lower quadrant, and resolved spontaneously without intervention. For the past 6 hours, the pain has been severe, constant, unrelieved by ibuprofen or acetaminophen, and radiating to the right flank. The pain is now accompanied by constant nausea and multiple episodes of emesis. The patient has had no diarrhea or recent travel. She has no chronic medical conditions but did have an appendectomy. The patient was treated for Chlamydia trachomatis cervicitis as a teenager. She is not currently sexually active. She does not use tobacco, alcohol, or illicit drugs. Temperature is 38 C (100.4 F), blood pressure is 130/80 mm Hg, pulse is 83/min, and respirations are 16/min. Abdominal examination shows tenderness and guarding in the right lower quadrant but no suprapubic or costovertebral angle tenderness. Pelvic examination shows a small, nontender, retroverted uterus and a tender right adnexal mass. Speculum examination is normal. Urine pregnancy test is negative. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (91)
(91) A 3-year-old boy is brought to the office for evaluation of chronic constipation. The patient first experienced difficulty stooling when he began toilet training several months ago, and the symptoms have persisted. He produces one small, hard stool every 3-4 days and often cries during defecation. The patient also has periodic abdominal pain that is relieved by defecation. He has no difficulty urinating and no history of encopresis. Initially, his diet consisted of cow's milk and assorted meats and starches. His parents have adjusted the diet to include more water and a variety of high-fiber fruits and vegetables, but there has been no improvement in his symptoms. The patient uses inhaled beta-agonists as needed for wheezing due to reactive airway disease that is triggered by upper respiratory infections. His mother has hypothyroidism and type 1 diabetes mellitus, and his maternal uncle has cystic fibrosis; otherwise, family history is insignificant. Review of growth chart shows weight tracking at the 25th percentile and height at the 40th percentile. Physical examination reveals an awake, alert child in no distress. He has no rhinorrhea and the pharynx and tympanic membranes appear normal. The neck is supple without adenopathy. S1 and S2 are normal without murmurs, and the lungs are clear to auscultation bilaterally. The abdomen is soft, nontender, and nondistended without organomegaly. Bowel sounds are normoactive. There is palpable stool in the left lower quadrant. Firm stool is also palpable in the rectal vault. There is a small anal fissure. Which of the following long-term daily therapies will most likely benefit this patient?
(Multiple Choice)
4.8/5 (78)
(78) A 36-year-old man comes to the office due to frequent "loose stools" for the past 10 months. The patient describes stools that are large in volume, liquid to semisolid, occurring up to 3-4 times a day, and often foul-smelling. He also reports excessive flatulence and occasional nausea and abdominal cramping. The patient says he may have lost some weight because his clothes are much looser than before. He has no prior medical problems and takes no medications. Family history is notable for hypertension and coronary artery disease in his father. The patient immigrated to the United States from Italy with his family when he was 2 years old and has not traveled out of the country since then. He does not use tobacco or illicit drugs and drinks alcohol occasionally. The patient works in a family-owned restaurant and has had no sick contacts. He consumes a balanced diet and notes no specific association of diarrhea to food. The patient has been in a monogamous relationship with his wife for the past 10 years. Temperature is 36.6 C (97.9 F), blood pressure is 130/86 mm Hg, and pulse is 72/min. Weight is 63.5 kg (140 lb). The sclerae are anicteric, and mucous membranes are moist without any lesions. Cardiopulmonary examination is unremarkable. The abdomen is soft, nondistended, and nontender, with no organomegaly. Bowel sounds are increased. Rectal examination shows no masses or tenderness and an empty rectal vault. Stool occult blood testing is negative. Samples for blood count, erythrocyte sedimentation rate, TSH, and serum electrolytes are obtained. This patient is most likely to respond to which of the following therapies?
(Multiple Choice)
4.9/5 (82)
(82) A 12-year-old girl is brought to the office for a preventive health maintenance examination. The patient's mother has noticed that over the last few months, her daughter "seems to sit sideways" and does not sit up straight when asked. The patient occasionally takes acetaminophen in the morning due to mild "aches and pains." She fractured her left femur in a horse-riding accident at age 8. Height and weight are at the 75th and 50th percentiles, respectively. Physical examination shows a well-appearing, nondysmorphic girl. Forward bend test demonstrates a right thoracic prominence that measures a 9-degree angle of trunk rotation and does not improve when a block is placed under the left foot. Flexion of the lumbar spine is normal and the patient is able to touch her toes. Lower extremity strength is normal. Patellar and Achilles deep tendon reflexes are 2+. Gait is normal.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (84)
(84) A 46-year-old woman comes to the office to follow up on back pain. The patient was involved in a motor vehicle collision 2 weeks ago and was transported to the emergency department due to back pain. Imaging revealed a bulging disc at L4-L5, with no nerve root impingement, and she was released with a prescription for naproxen. Since then, the patient has had only partial relief of pain; it is rated as 7 on a scale of 0-10 in severity and radiates to her right hip and thigh. Medical history is notable for hypothyroidism and irritable bowel syndrome. Vital signs are normal. BMI is 27 kg/m2. Examination shows tenderness in the right paraspinal region at the L4 level. Lower extremity motor strength and reflexes are normal, and straight-leg raising test is negative. The patient states, "My back is going to ruin my life. My mother lost her job due to back pain, and now I just know I'm going to lose my job, too." Which of the following is most predictive of poor long-term functional status in this patient?
(Multiple Choice)
4.7/5 (76)
(76) An 85-year-old man is evaluated at a nursing home due to intermittent agitation. The patient has dementia and has been residing in the facility for several years. He can communicate his needs but does not recognize his caregivers and requires assistance with all activities of daily living. According to the staff, the patient has had intermittent agitation and aggression; these have become somewhat more frequent over time. The patient is unable to provide meaningful history, but there is no report of fever, cough, abdominal pain, urinary symptoms, or change in appetite. Records indicate a history of hypertension but no cerebrovascular accidents or Parkinson disease. His only medications are olanzapine and haloperidol as needed for agitation. Temperature is 37 C (98.6 F), blood pressure is 130/70 mm Hg, and pulse is 78/min. The patient is comfortable but confused and oriented to self only. Lungs are clear to auscultation and heart sounds are normal. The abdomen is soft and nontender with normoactive bowel sounds. Neurological examination reveals mild resting hand tremors and rigidity of both arms. There is no extremity edema or rash. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.7/5 (85)
(85) A 62-year-old man is brought to the emergency department with pain and numbness in the right leg. He says "I was watching television 2 hours ago when the pain started, and then my leg became numb." Past medical history includes coronary artery disease with anterior wall myocardial infarction, ischemic cardiomyopathy, hypertension, and hyperlipidemia. He does not adhere regularly to prescribed medications. The patient does not smoke cigarettes but consumes alcohol occasionally. He appears to be in significant discomfort due to pain. His temperature is 36.7 C (98 F), blood pressure is 150/90 mm Hg, pulse is 102/min and regular, and respirations are 14/min. Physical examination shows a cool right lower extremity with delayed capillary refill. Even with Doppler examination, no pulses are detected at the right popliteal and dorsalis pedis arteries. Which of the following is the best next step in the management of this patient?
(Multiple Choice)
4.9/5 (102)
(102) A 30-year-old woman comes to the office due to tingling and numbness in both of her distal lower extremities for the last 3 months. Her symptoms are gradually worsening. She also has had intense fatigue. She has not had any weight change, constipation, skin dryness, headaches, or visual changes. The patient was diagnosed with primary hypothyroidism secondary to Hashimoto thyroiditis when she was 10 years old. She is currently on 100 mcg per day of levothyroxine orally. Her mother also has hypothyroidism. The patient does not use tobacco, alcohol, or recreational drugs. Her menstrual cycles have been irregular for the last 6 months. Her last menstrual period was 2 months ago. She is sexually active with one partner. Blood pressure is 114/78 mm Hg and pulse is 72/min. She weighs 69 kg (152 lbs) and is 163 cm (5'4") tall. Her thyroid is nonpalpable. Her mucous membranes are moist and pale. Her tongue appears to be bald. She does not have any scleral icterus. Vibration and proprioception are decreased in both of her lower extremities distally. Pain and temperature sensations appear normal. Her ankle jerks are absent, but other reflexes are brisk. Babinski is present, and Romberg signs is positive. The rest of the physical examination is unremarkable. Stool obtained from the rectal examination is negative for occult blood. Laboratory results reveal a hemoglobin of 8 g/dL and hematocrit of 24%. Her total leukocyte count is 3,200/mm3. Her platelet count is 300,000/mm3. Basic serum chemistries are within normal limits. Her total T4 level is 8.2 mcg/dL (normal 4-12 mcg/dL) and TSH level is 2.4 micro IU/mL. Which of the following is most crucial to monitor during the first few days of treatment in the above patient?
(Multiple Choice)
4.7/5 (71)
(71) A 65-year-old man comes to the emergency department 2 hours after the onset of weakness in his left arm and leg. Two months ago, he had a 15-minute episode of left arm weakness that resolved spontaneously. He has had no headache, nausea, vomiting, or difficulty swallowing. His medications include chlorthalidone, lisinopril, and metformin. The patient occasionally takes ibuprofen for muscle cramps and antacids for heartburn. His temperature is 36.7 C (98.0 F), blood pressure is 172/98 mm Hg, and pulse is 83/min with a regular rhythm. Physical examination shows a dense, left-sided hemiparesis. Fingerstick blood glucose is 108 mg/dL. CT scan of the head without contrast shows no signs of intracranial hemorrhage Item 1 of 2
Prior to any further emergency treatment, which of the following should be evaluated in this patient?
(Multiple Choice)
4.9/5 (84)
(84) A 7-year-old boy is brought to the emergency department by his parents due to left eye swelling and redness. The patient has had left eye pain for 2 days and the pain worsened today. He has no symptoms in his right eye. He has allergic rhinitis, for which he takes intranasal steroids. The patient developed sinusitis approximately 3 weeks ago and was treated with amoxicillin-clavulanate. He has no other medical conditions and has had no surgeries. The patient's mother was diagnosed with left leg deep vein thrombosis after a recent transatlantic flight. Temperature is 39.2 C (102.5 F), blood pressure is 102/70 mm Hg, pulse is 94/min, and respirations are 18/min. The left eyelid is erythematous, tender, and swollen. The conjunctiva is hyperemic. Movement of the left eye causes pain. Visual acuity and pupillary reaction are normal bilaterally. Purulent mucus is draining from the nose, and nasal turbinates are swollen and erythematous. Examination of the right eye is unremarkable, and facial sensation is intact. CT scan reveals inflammation of extraocular muscles, fat stranding, and mild anterior displacement of the globe. No fluid collections are identified. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (89)
(89) A 7-year-old boy is brought to the emergency department by his parents due to left eye swelling and redness. The patient has had left eye pain for 2 days and the pain worsened today. He has no symptoms in his right eye. He has allergic rhinitis, for which he takes intranasal steroids. The patient developed sinusitis approximately 3 weeks ago and was treated with amoxicillin-clavulanate. He has no other medical conditions and has had no surgeries. The patient's mother was diagnosed with left leg deep vein thrombosis after a recent transatlantic flight. Temperature is 39.2 C (102.5 F), blood pressure is 102/70 mm Hg, pulse is 94/min, and respirations are 18/min. The left eyelid is erythematous, tender, and swollen. The conjunctiva is hyperemic. Movement of the left eye causes pain. Visual acuity and pupillary reaction are normal bilaterally. Purulent mucus is draining from the nose, and nasal turbinates are swollen and erythematous. Examination of the right eye is unremarkable, and facial sensation is intact. Laboratory results are as follows:  Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (60)
(60) A 46-year-old woman, gravida 3 para 3, comes to the office due to left nipple discharge. She reports that the discharge began 1 month ago, is present almost daily, and stains her undergarments. It is typically yellow, thin, and sticky but occasionally stains her bra a rust color. The patient has no chronic medical conditions and takes no daily medications. Menses are regular and her last menstrual period was 3 weeks ago. The patient has 3 children; the youngest was born 6 years ago by cesarean delivery, and a bilateral tubal ligation was performed with the delivery. All 3 children were breastfed. There is no family history of breast cancer in her first-degree relatives. The patient drinks 8-10 alcoholic beverages a week but does not use tobacco or illicit drugs. She has no known drug allergies. Temperature is 37.2 C (99 F), blood pressure is 130/86 mm Hg, and pulse is 70/min. BMI is 33 kg/m2. Serous discharge is expressed from the left nipple. No palpable masses, skin discoloration or retraction, or axillary lymphadenopathy is present. The right breast has no expressed nipple discharge, masses, or lymphadenopathy. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (70)
(70) A 38-year-old woman comes to the office for follow-up after recent hospitalization. The patient went to the emergency department 2 weeks ago after several episodes of coffee-ground emesis. She had intermittent, burning, epigastric pain over the past several months prior to hospitalization. At that time, upper gastrointestinal endoscopy revealed a duodenal ulcer, and the patient was discharged on pantoprazole therapy. The patient reports improvement in abdominal pain and has had no further hematemesis, hematochezia, or melena. She has no other medical problems and in the past has taken only ibuprofen for occasional aches and pains. The patient does not use tobacco, alcohol, or illicit drugs and has no allergies. Family history is notable for gastric cancer in her father. Temperature is 36.5 C (97.7 F), blood pressure is 124/78 mm Hg, and pulse is 82/min. Cardiopulmonary examination is normal. The abdomen is nondistended, soft, and nontender. Gastric and duodenal biopsies performed during the endoscopy show chronic antral gastritis with presence of Helicobacter pylori but no evidence of malignancy.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (80)
(80) A 32-year-old Caucasian female presents to your office with a two month history of headaches. Initially, her headaches occurred only in the evening and while she tried to take a nap, but recently they seem to be persistent during the day. She describes them as diffuse throughout her entire head. She also complains of some nausea, occasional numbness of her fingertips, and blurry vision. Over-the-counter ibuprofen provides minimal relief. She denies any fevers, vomiting, imbalance, falls, or neck pain. She used to have migraines as a teenager, but they stopped years ago. Her family history is significant for migraines in her mother and older sister. Current medications include an oral contraceptive pill and a daily multivitamin. She smokes one pack of cigarettes per day and drinks alcohol occasionally. Her blood pressure is 152/90 mmHg and heart rate is 76/min. Her BMI is 35 kg/m2. Neurological examination is unremarkable. Which of the following is the best next step in managing this patient?
(Multiple Choice)
4.8/5 (84)
(84) A 72-year-old man comes to the office because of a skin lesion on his hand that first appeared 6 months ago. The lesion does not itch or cause pain. The patient has had similar lesions on his face; some spontaneously resolved, and some were successfully treated with topical liquid nitrogen therapy. Skin examination reveals a 1.3-cm lesion, as shown in the exhibit;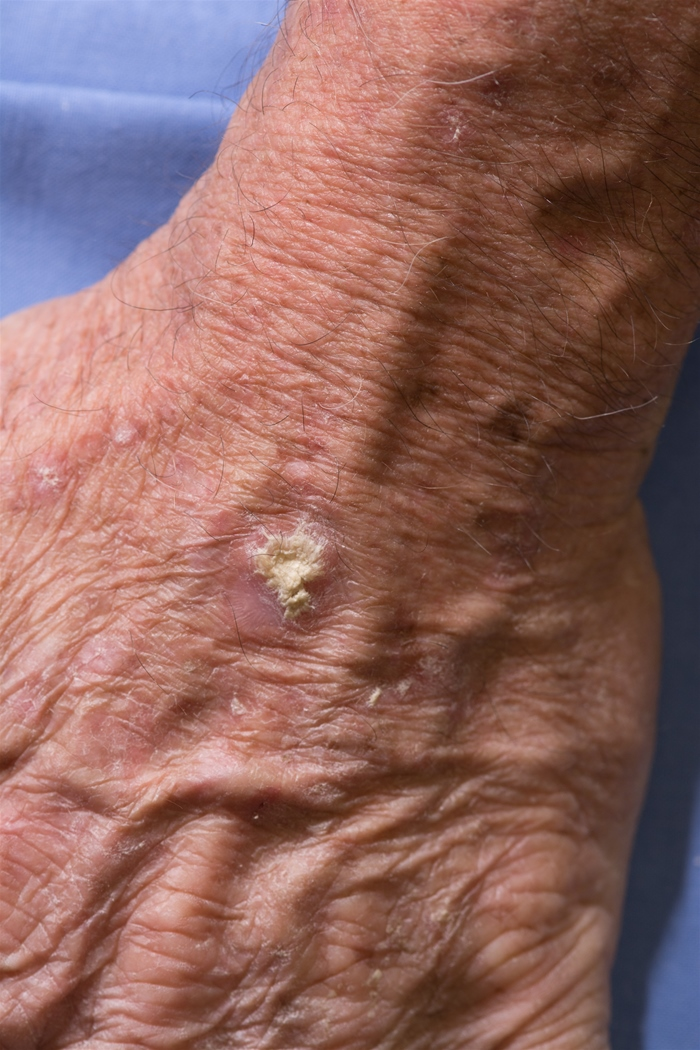 it is nontender. Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.9/5 (84)
(84) Showing 1001 - 1020 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)