



 Chat with AI
Exam 1: Advanced Clinical Medicine

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


A 38-year-old woman comes to the office due to worsening asthma symptoms for 2-3 days. She has shortness of breath, wheezing, and productive cough. The patient describes thick sputum that was blood-tinged yesterday. She was diagnosed with asthma 12 years ago but says that it had not been this bad until last year. For the past year the patient has had 2 hospitalizations for asthma exacerbations but has never been intubated. She completed a course of oral prednisone and azithromycin 2 months ago. Current medications include a daily fluticasone inhaler and as-needed albuterol inhaler. The patient reports no decrease in appetite or weight loss and has not travelled outside of her home state of New Jersey in the past 2 years. She works as a school teacher and does not use tobacco, alcohol, or illicit drugs. The patient has no second-hand tobacco exposure and no known allergies. Her grandmother also has asthma. Temperature is 37 C (98.6 F), blood pressure is 123/80 mm Hg, pulse is 94/min, and respirations are 16/min. Pulse oximetry shows 95% on room air. Pulmonary examination reveals scattered wheezes. Heart sounds are normal. There is no clubbing, peripheral edema, or skin rashes. Complete blood count shows the following:  Chest x-ray reveals patchy bilateral upper lobe infiltrates and prominent bronchial markings. Which of the following is the best next step in diagnosing the cause of this patient's worsening symptoms?
 (Multiple Choice)
4.9/5  (88)
(88) A 54-year-old man comes to the office for a routine follow-up visit. He feels well and has had no ongoing symptoms but has noticed a slow increase in his weight over the past year. He says, "When the nurse weighed me around this time last year I was 74.8 kg (165 lb) and now I am 82.5 kg (182 lb). I don't know what's causing that; my diet hasn't changed." The patient was diagnosed with HIV a year ago and initiated on antiretroviral therapy, which improved his CD4 count and viral load. He has no other chronic medical problems and has tested negative for hepatitis B and C viruses. His father had coronary artery disease and died of a myocardial infarction at age 55. The patient has a 28-pack-year smoking history and continues to smoke a pack of cigarettes daily. He used intravenous drugs in the past but is currently not using alcohol or illicit drugs. Temperature is 36.5 C (97.7 F), blood pressure is 112/72 mm Hg, pulse is 76/min, and respirations are 16/min. BMI is 26.9 kg/m2. There is adipose tissue deposition on the back of the neck. Abdominal examination reveals increased girth without a substantial increase in subcutaneous fat and palpable hepatomegaly with a soft, nontender liver edge. No striae, bruising, or skin atrophy are present. Laboratory studies reveal a normal complete blood count, basic chemistry, hepatic function panel, hemoglobin A1c, and TSH level. Lipid profile is as follows:  Liver ultrasound reveals increased parenchymal echogenicity, consistent with steatosis. Besides recommending lifestyle modifications, including regular exercise, tobacco cessation, and a heart-healthy diet, what is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (83)
(83) A 70-year-old man is brought to the emergency department by his wife after he passed out earlier this morning. The patient was sitting in a chair watching TV when he lost consciousness for approximately 3 minutes before spontaneously recovering. He did not fall off the chair, and his wife did not observe any convulsive limb movements. There was no soiling of his clothes by urine or stool. She says, "Doc, it has never happened to him before. He was completely unresponsive and looked pale. I got really scared." In the emergency department the patient has no headache, nausea, chest discomfort, or shortness of breath. He has no recollection of what happened and did not feel anything out of the ordinary beforehand. Medical history includes hypertension, hyperlipidemia, type 2 diabetes mellitus, and coronary artery disease. The patient had an anterolateral myocardial infarction 2 years ago and underwent coronary stent placement. Since then, he has had no episodes of angina. His lifestyle is sedentary and he spends little time outdoors. He becomes short of breath when climbing a flight of stairs. On initial evaluation the patient appears comfortable and asks if he can go home. Temperature is 36.7 C (98 F), blood pressure is 130/86 mm Hg sitting and 125/85 mm Hg standing, pulse is 78/min, and respirations are 16/min. Pulse oximetry shows 98% on room air. Neurologic examination is nonfocal. ECG shows normal sinus rhythm with anterolateral Q waves, unchanged from prior ECG. Blood cell counts, serum chemistry studies, and chest x-ray are within normal limits. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (79)
(79) A 35-year-old woman comes to the office with episodic abdominal pain. After dinner a day ago, she had intense epigastric pain that lasted 30-40 minutes, was dull with radiation to the back and right shoulder, and was accompanied by nausea and difficulty catching her breath. The pain resolved spontaneously after an hour and she did not seek medical care. The patient has had 2 similar episodes of lesser intensity in the past 6 months that resolved spontaneously. She has a history of migraine headaches treated with sumatriptan as needed. She does not use tobacco or illicit drugs. The patient has consumed 1 or 2 glasses of wine daily for the past 10 years. Her father died of pancreatic cancer at age 75, and her mother died of breast cancer at age 65. Vital signs are within normal limits. BMI is 35 kg/m2. Abdominal examination reveals normoactive bowel sounds without tenderness or guarding. The liver span is 8 cm and there is no palpable spleen. The remainder of the examination is within normal limits. Abdominal ultrasound is performed and shows a nondistended gallbladder with numerous gallstones. The size of the common bile duct is normal (0.5 cm), but the pancreas is not well visualized. Complete metabolic panel is normal. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (68)
(68) A 27-year-old HIV-positive man comes to the emergency department with shortness of breath, dry cough, and right-sided chest pain since yesterday. The chest pain is worse when he takes a deep breath or coughs. He has had chills and night sweats for the last week, which he has attributed to the flu. The patient has been hospitalized for opioid overdose several times in the past. Four months ago, he was admitted and treated for aspiration pneumonia. Last year he was hospitalized for cocaine overdose complicated by tonic-clonic seizures. His most recent CD4 lymphocyte count was 190/mm3 2 months ago. He has no drug allergies. In the emergency department he appears mildly uncomfortable and has shallow breathing. Temperature is 39.4 C (103 F), blood pressure is 100/70 mm Hg, pulse is 110/min and regular, and respirations are 22/min. BMI is 19 kg/m2. Pulse oximetry is 95% on room air. There are multiple needle tracks and a painful subcutaneous mass in the right antecubital area. The neck veins are flat with the patient in semi-recumbent position. There is a 2/6 systolic murmur heard at the left sternal border. The liver is palpated 1 cm below the costal margin and is nontender. Chest x-ray reveals nodular opacities in both lung fields, including subpleural opacities on the right. Serum potassium is 3.8 mg/dL and creatinine is 1.1 mg/dL. Blood cultures are obtained and intravenous fluids are initiated. Which of the following is most likely to establish the diagnosis in this patient?
(Multiple Choice)
4.9/5 (88)
(88) A 76-year-old female is seen in the clinic with numerous medical complaints. She is scheduled to undergo elective surgery for right hip replacement. She says she is tired, has a very poor appetite, and does not sleep well at night. She denies any fevers, chills, chest pain, or shortness of breath. Her ECG and chest x-ray are normal. She cannot remember which medications she takes. What is the most important factor in perioperative adverse drug reaction in the elderly population?
(Multiple Choice)
5.0/5 (86)
(86) A 36-year-old woman, gravida 6 para 5, at 41 weeks gestation comes to the emergency department for spontaneous rupture of membranes and contractions every 3 minutes; she has had no vaginal bleeding. Fetal movement is normal. The patient's current pregnancy has been uncomplicated. A 1-hour glucose challenge test was 155 mg/dL at 28 weeks gestation; however, a 3-hour glucose tolerance test was normal. She has no chronic medical conditions and has had no previous surgery. Vital signs are normal. The fetal heart rate tracing is category 1. The tocometer shows contractions every 3 minutes. Fundal height is 42 cm. Pelvic examination confirms rupture of membranes and the cervix is 5 cm dilated. The patient is admitted and epidural analgesia is administered. Her labor progresses normally. After 15 minutes of pushing, the fetal head delivers and, immediately after it delivers, retracts into the perineum. The patient is instructed to push, gentle downward traction is applied to the fetal head, and the anterior fetal shoulder does not deliver. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (69)
(69) A 44-year-old woman comes to the emergency department with sudden onset of weakness and dizziness. The patient does not have any chest pain but feels her heart pounding in her chest. She is otherwise healthy and does not have any other medical problems. Her maternal uncle died suddenly at age 42. Blood pressure is 110/60 mm Hg and pulse is 170/min. Lungs are clear to auscultation and cardiac examination is normal. Her electrocardiogram (ECG) is shown in this Exhibit. 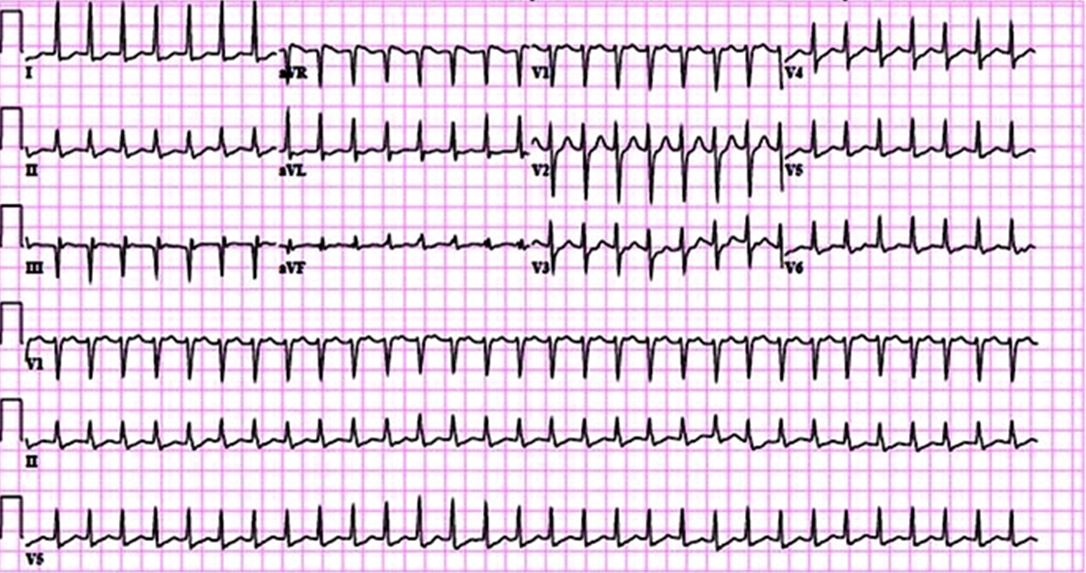 Which of the following is the best initial treatment for this patient's condition?
 (Multiple Choice)
4.8/5 (78)
(78) A 45-year-old Caucasian female presents to your office with abdominal discomfort and distention that is especially bothersome after meals. She has noticed recently that she gets tired more easily. She feels "down", but denies any sleep difficulty, crying spells and suicidal ideation. She visited a doctor approximately one year ago due to similar complaints, and was told that the problem was psychological. She underwent myomectomy for a large uterine fibroid 8 years ago. She is not sexually active. Her family history is significant for pancreatic cancer in her father and a thyroid disease in her mother. The physical examination is significant for mild pallor of the conjunctivae. The abdomen is somewhat distended with no palpable masses. The laboratory values are:  After taking the appropriate initial steps, you proceed with gastric endoscopy. Which of the following findings is more likely to be present in this patient?
 (Multiple Choice)
4.9/5 (88)
(88) A 5-year-old boy is brought to the emergency department with severe leg pain that started 6 hours earlier. His mother says that their heating system broke last night so she "tried to keep him warm with lots of blankets." The patient was given ibuprofen and oxycodone at home without relief of pain. He played outside with his brother yesterday but did not experience any trauma or injury. He has not had fever, cough, vomiting, or rash. Medical history includes mild persistent asthma and sickle cell disease, and he has been hospitalized once for a vaso-occlusive pain episode. Temperature is 37.2 C (99 F), blood pressure is 100/62 mm Hg, pulse is 150/min, and respirations are 20/min. Physical examination shows a young child lying in bed in significant discomfort, crying and holding his left leg. Mucous membranes are moist and capillary refill is <2 seconds. The lungs are clear to auscultation, and the abdomen is soft, nontender, and nondistended without organomegaly. The left anterior calf is markedly tender to palpation but does not have erythema, warmth, or swelling. A peripheral intravenous line is inserted, and a complete blood count is drawn. The child is admitted to the hospital and experiences improvement of his leg pain overnight. The next morning, however, he develops chest pain and difficulty breathing. Temperature is 38.9 C (102 F), blood pressure is 94/62 mm Hg, pulse is 124/min, and respirations are 28/min. The patient's pulse oximetry shows 95% on room air. Examination reveals diminished left-sided breath sounds with mild subcostal retractions. Hemoglobin is stable from admission at 9.5 g/dL, and a blood culture is sent. A chest x-ray is obtained. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.7/5 (75)
(75) A 78-year-old man comes to the office for the evaluation of persistent, severe, low back pain. The pain does not radiate down to his legs, and is not associated with bladder or bowel disturbances. He has metastatic prostate cancer, which has progressed despite hormonal therapy and chemotherapy. A bone scan done 6 weeks ago revealed the presence of 2 vertebral metastases in the L4 and L5 vertebral bodies. He was started on high-dose narcotic analgesics at that time. He says that the narcotics have "taken the edge" off the pain, but he continues to have severe debilitating pain. Neurological examination of the lower extremities is unremarkable. A repeat bone scan reveals results similar to the previous scan results. Which of the following is the next most appropriate step in controlling this patient's symptoms?
(Multiple Choice)
4.8/5 (74)
(74) A 27-year-old man comes to the office due to depressed mood and low energy for the past several months. He describes sad and irritable mood, sleeping 12-14 hours a day, decreased appetite, and poor concentration at work. The patient has stopped going to the gym and playing his guitar and has withdrawn from his friends and girlfriend. He has no medical problems and physical examination and routine laboratory tests are normal. Major depressive disorder is diagnosed and he is started on fluoxetine 20 mg. At his 2-month follow-up, the patient reports, "I'm feeling just a little better. I am still down on most days but at least I picked up my guitar once this week. The other thing is sex. In the beginning, I was so depressed that I didn't care whether I had sex. Now, I'm interested and get erections, but it's taking too long to ejaculate and it sometimes fails to happen altogether." The patient says that this is creating problems with his girlfriend and he is considering stopping the antidepressant. He drinks a beer a day and does not use illicit drugs. Which of the following is the best management strategy for this patient?
(Multiple Choice)
4.7/5 (79)
(79) A 70-year-old woman comes to the office due to back pain, fatigue, and inability to carry out her daily work. The pain began 6 months ago and has slowly intensified. The patient had a hip fracture 3 months ago but has no other medical conditions. She is a lifetime nonsmoker and drinks alcohol on social occasions. She currently takes no medications. The patient has no extremity weakness or paresthesia. She has mild constipation; urination is normal. Initial laboratory results are as follows:  Dipstick urinalysis is normal.
Which of the following is the best next step in management of this patient?
Dipstick urinalysis is normal.
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.7/5 (88)
(88) A 34-year-old, obese, Caucasian male presents to your office with an abnormal sensation over his right thigh. He says, "It gets numb, and sometimes I feel burning over my thigh." He denies any back pain, muscle weakness, or abnormal sensation below the knee. His past medical history is insignificant. He smokes two packs of cigarettes and consumes 1-2 bottles of beer daily. He is a construction worker. He frequently works in a squatting position. Physical examination reveals an area of decreased sensation over the right anterolateral thigh. There is no muscle weakness. Deep tendon reflexes are symmetrical.
Item 1 of 2
Which of the following is the most likely cause of this patient's condition?
(Multiple Choice)
4.8/5 (73)
(73) A 40-year-old man is evaluated for perioral paresthesias and cramping of both hands. The patient has a history of alcoholic cirrhosis and was admitted 24 hours ago due to recurrent episodes of hematemesis. Evaluation revealed acute variceal bleeding for which the patient received endoscopic therapy. He also received 6 units of packed red blood cells and 4 units of fresh frozen plasma since admission. The patient reports feelings of anxiety and worsening tingling and numbness around the mouth for the past 2 hours. He has also had severe muscle spasms of the hands and legs. Temperature is 37.1 C (98.8 F), blood pressure is 116/68 mm Hg, and pulse is 92/min. Jugular venous pressure is normal. The lungs are clear to auscultation and heart sounds are normal. Abdominal examination reveals moderate ascites with no tenderness. He has generalized mild muscle weakness and periodic spontaneous twitching in the major muscle groups. Laboratory studies at the time of admission are as follows: 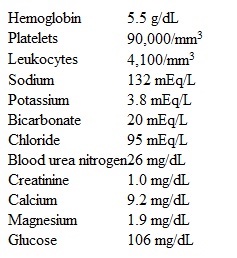 Hemoglobin level after the transfusions is 8.9 g/dL. Further diagnostic testing is pending. Intravenous administration of which of the following is most likely to improve this patient's current symptoms?
 (Multiple Choice)
4.9/5 (78)
(78) A 52-year-old woman comes to the emergency department with left leg pain and swelling. She is a commercial truck driver and first noticed the swelling 3 days ago. The patient initially attributed the swelling to a long haul truck ride as she often gets mild "puffiness" of her ankles by the end of the day. However, the swelling has persisted and now involves her entire left leg below the knee. She has discomfort with walking but no chest pain, palpitations, syncope, or difficulty breathing. The patient has a history of hypothyroidism and hypertension and takes levothyroxine and hydrochlorothiazide. She has also been on menopausal hormone therapy using estrogen-progestin for intractable hot flashes. She smokes a pack of cigarettes daily and drinks 2 beers each night. Temperature is 37.2 C (99 F), blood pressure is 134/89 mm Hg, and pulse is 78/min. BMI is 31 kg/m2. Extremity examination reveals a normal right leg and pitting edema and warmth over the left lower leg. ECG shows normal sinus rhythm, and chest x-ray is normal with no infiltrates. Serum creatinine level is 0.7 mg/dL. Duplex ultrasound of the lower extremities reveals noncompressibility of the left popliteal and femoral veins. The patient is started on rivaroxaban and scheduled to follow up with her primary care physician. She is counseled on smoking cessation and agrees to enroll in a smoking cessation clinic. The patient is also informed that her current menopausal hormone therapy (MHT) increases her risk of venous thromboembolism. She is concerned about experiencing hot flashes again. Which of the following is the most appropriate recommendation for treatment of this patient's menopausal symptoms?
(Multiple Choice)
4.8/5 (71)
(71) A 62-year-old hospitalized man is evaluated for new-onset, right lower extremity pain. The patient underwent bypass surgery for 3-vessel coronary artery disease 2 months ago. He arrived at the emergency department 2 nights ago due to recurrent chest pains. At that time, ECG showed sinus rhythm with no ST-segment changes, but cardiac troponin I levels were elevated. The patient was initiated on unfractionated heparin, antiplatelet agents, a beta blocker, and a nitrate. A coronary angiogram was performed via the radial artery; it revealed graft insertion site stenosis and was treated with stenting. Postintervention echocardiography revealed left ventricular ejection fraction of 50% with no regional wall motion abnormalities. This morning, the patient had new, sudden-onset, right lower extremity pain. He has never had pain in that extremity before. The patient has a history of hypertension, hyperlipidemia, and type 2 diabetes mellitus. Current medications include aspirin, clopidogrel, rosuvastatin, metoprolol, losartan, isosorbide mononitrate, basal-bolus insulins, and subcutaneous heparin at a prophylactic dose. The patient is a former smoker with a 30-pack-year history. Temperature is 37.6 C (99.7 F), blood pressure is 138/84 mm Hg, pulse is 96/min, and respirations are 18/min. Physical examination reveals normal jugular venous pressure, clear lungs, no heart murmurs, and a soft, nontender abdomen. The right leg is tender and cool to the touch when compared to the left leg. Right lower extremity distal pulses are diminished, but capillary refill is intact. Left leg examination is normal with the exception of healed scars from previous saphenous vein harvesting. Neurological examination is normal. Laboratory results are as follows:
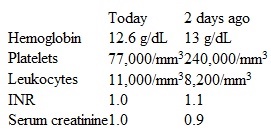 Immunoassay for heparin-induced thrombocytopenia antibody returns positive. His condition improves with treatment. Which of the following is the most accurate statement regarding heparin use and risk of recurrence of this patient's current condition?
 (Multiple Choice)
4.8/5 (68)
(68) A 31-year-old man comes to the office due to fullness in the epigastric area and occasional nausea over several months. He has had no heartburn, dysphagia, early satiety, or weight loss. The patient has no other medical conditions and takes no medications, including over-the-counter supplements. He does not use tobacco, alcohol, or illicit drugs. Family history is not significant, and the patient has no known drug allergies. Vital signs are within normal limits. Examination shows no abnormalities. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (73)
(73) A 1-hour-old boy is evaluated in the newborn nursery. The patient was born at 38 weeks gestation via spontaneous vaginal delivery to a 24-year-old woman, gravida 3 para 2. The mother had asymptomatic group B Streptococcus bacteriuria in the first trimester and was told that she would receive antibiotics prior to delivery. All other prenatal laboratory results were normal. The mother had spontaneous rupture of membranes at home, came immediately to the hospital, and received one dose of intravenous ampicillin. She delivered approximately 2 hours later. The patient's Apgar scores were 8 and 9 at 1 and 5 minutes, respectively. He received ophthalmic erythromycin and intramuscular vitamin K. Temperature is 37.1 C (98.8 F). All other vital signs are normal for age. Examination shows a quiet, awake neonate with normal tone and posture. What is the most appropriate next step in management of the patient?
(Multiple Choice)
4.9/5 (71)
(71) A 48-year-old man comes to the office due to progressive weakness for the past 2 months. The patient has experienced difficulty climbing stairs, especially when carrying heavy items such as groceries, and his symptoms have become progressively worse. He also reports occasional fevers, but no significant pain in the muscles or joints. The patient has had no diplopia, dyspnea, dysphagia, abdominal pain, or heat or cold intolerance. He has a history of hypertension and hyperlipidemia, for which he has taken losartan and atorvastatin, respectively, for the last 4 years. The patient does not use tobacco, alcohol, or illicit drugs. Temperature is 37.1 C (98.8 F), blood pressure is 132/84 mm Hg, pulse is 72/min, and respirations are 14/min. He has no scleral icterus. Cardiopulmonary examination is normal. The abdomen is soft and nontender with no hepatosplenomegaly. Muscle strength is 3/5 in the deltoids and hip flexors but is otherwise normal. Deep tendon reflexes are normal and symmetric, and sensations to pain and light touch are intact. There is mild muscle tenderness and some of the small joints of both hands are tender to palpation without any swelling or erythema. He has no skin rash. Laboratory results are as follows:
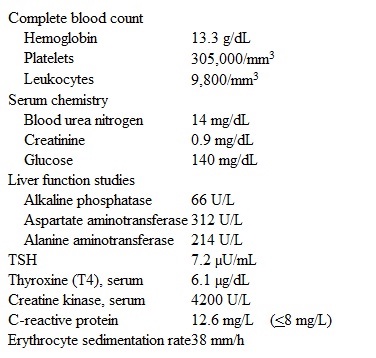 After confirmation of the diagnosis, the patient is started on appropriate therapy. During a follow-up visit 6 months later, he says the muscle weakness has improved but he becomes breathless on moderate exertion. The patient has to stop to catch his breath when walking 3 blocks to his office, which he had previously been able to do without stopping. He has also had a mild nonproductive cough. Temperature is 36.6 C (98 F), blood pressure is 130/80 mm Hg, pulse is 82/min, and respirations are 16/min. The neck veins are flat. Heart sounds are normal, but lung auscultation reveals bibasilar fine crackles. Muscle strength is normal. Blood cell counts and serum chemistry are within normal limits. Chest radiograph is normal. Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (85)
(85) Showing 941 - 960 of 1121

Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)