



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 53-year-old woman comes to the physician for evaluation of a pulmonary nodule detected on a chest x-ray performed for atypical central, burning chest pain. Her pain resolved with omeprazole. The patient has hypertension and chronic low back pain for which she takes hydrochlorothiazide and as-needed ibuprofen. She has a 30-pack-year smoking history and quit 3 years ago.
Blood pressure is 142/88 mm Hg and pulse is 78/min. The lungs are clear to auscultation, and the remainder of the examination shows no abnormalities.
CT scan of the chest reveals a 2.1-cm spiculated nodule with peripheral punctate calcifications in the periphery of the right upper lobe. There is no mediastinal lymphadenopathy. No previous radiographs are available for comparison.
Which of the following is the best next step in management of this patient's lung lesion?
(Multiple Choice)
4.9/5  (82)
(82) A 49-year-old alcoholic man is admitted for diarrhea and generalized abdominal pain. His blood pressure is 134/80 mm Hg, pulse is 90/min, respirations are 16/min, and oxygen saturation is 97% on room air. He is disheveled and looks chronically ill. He is oriented to person and place. His mucous membranes are dry. His abdomen is soft and mildly tender in the epigastric region. He has no focal neurologic findings.
An electrocardiogram and chest x-ray is unremarkable. Stool samples are sent for culture and microscopic examination.
Laboratory results are as follows:
 He is given thiamine and a multivitamin intravenously along with three liters of normal saline with 5% dextrose. He also receives intravenous potassium and magnesium supplementation. Thirty-six hours after admission, he complains of severe weakness. His oxygenation has decreased and he appears agitated.
Repeat laboratory results are as follows:
 Which of the following is the most likely cause of this patient's new-onset weakness?
He is given thiamine and a multivitamin intravenously along with three liters of normal saline with 5% dextrose. He also receives intravenous potassium and magnesium supplementation. Thirty-six hours after admission, he complains of severe weakness. His oxygenation has decreased and he appears agitated.
Repeat laboratory results are as follows:
Which of the following is the most likely cause of this patient's new-onset weakness? (Multiple Choice)
4.8/5 (90)
(90) A 30-year-old woman comes to the office due to a nodule in the right lobe of the thyroid gland. The nodule was discovered incidentally on a CT scan of the neck performed 2 weeks ago to evaluate neck pain following a motor vehicle collision. The patient feels well and has experienced no weight change, temperature intolerance, hair or skin changes, or menstrual irregularities. She has no chronic medical problems, takes no prescription medications, and has no history of radiation exposure. Family history is negative for thyroid cancer. The patient does not use tobacco, alcohol, or illicit drugs.
Blood pressure is 120/80 mm Hg and pulse is 72/min. Thyroid examination reveals a palpable, firm, 2-cm nodule on the right lobe. Neck lymph nodes are not enlarged. The remainder of the physical examination is normal.
Laboratory results are as follows:
 Ultrasonography of the thyroid gland shows a solid right lobe hyperechoic nodule measuring 2.3×1.6×1.2 cm with no evidence of microcalcification or internal vascularity. Which of the following is the best next step in evaluation of this patient?
 (Multiple Choice)
4.9/5 (85)
(85) You are following five patients who have had various aspects of their kidney function measured on one or more occasions over time. All patients are clinically stable without any ongoing acute events. Which of the following laboratory changes would represent the greatest loss in glomerular filtration rate?
(Multiple Choice)
4.9/5 (73)
(73) A 26-year-old man is brought to the physician by his former girlfriend, who became alarmed after receiving an email message in which he threatened suicide. The patient says he went into an overwhelming state of panic and depression when he heard that his former girlfriend was dating a new man and "wanted to get back at her." The patient has a history of "mood swings" since his teens and rage attacks when he feels that people are unsupportive. He has no delusions or hallucinations and no suicidal intent or plan. He describes his mood as "a deep pit of emptiness." Physical examination is normal except for cigarette burns on his thighs that he explains as self-harming behavior performed to relieve tension.
Which of the following is the best treatment for this patient?
(Multiple Choice)
4.8/5 (75)
(75) A 43-year-old white man comes to the office due to a 4-week history of malaise, profound fatigue, and cough. Over the last 3 days, he has noticed streaks of blood in his sputum. Since childhood, the patient has had mild, intermittent asthma that has been well controlled with as-needed albuterol and has not required hospitalization. Four months ago, the patient experienced pain and blurry vision in the right eye, which spontaneously improved over several days; he did not seek medical attention. The patient has no other medical issues, and family history is negative for cancer and rheumatic disease. He is a lifetime nonsmoker and has not traveled recently.
Temperature is 37.9 C (100.3 F), blood pressure is 135/70 mm Hg, and pulse is 92/min. BMI is 23 kg/m2. Visual acuity is normal and extraocular movements are not restricted. Several small oral ulcerations are present, but there are no skin rashes or lymphadenopathy. Bilateral scattered rhonchi are present on lung auscultation. Heart sounds are normal. Abdominal examination reveals no organomegaly. Laboratory results are as follows:
 Urinalysis shows 3+ protein, 30-50 erythrocytes/hpf, and 2-3 leukocytes/hpf. Chest x-ray reveals several ill-defined nodules with cavitation in both lungs.
Which of the following is the most likely diagnosis?
Urinalysis shows 3+ protein, 30-50 erythrocytes/hpf, and 2-3 leukocytes/hpf. Chest x-ray reveals several ill-defined nodules with cavitation in both lungs.
Which of the following is the most likely diagnosis? (Multiple Choice)
4.8/5 (71)
(71) A 29-year-old woman comes to the office due to amenorrhea. She has not had a menstrual period since an uncomplicated vaginal delivery 13 months ago. The patient stopped breastfeeding 7 months ago but still has some milky discharge from both breasts. She has no other symptoms. The patient has a 10-year history of hypothyroidism, for which she takes levothyroxine, the dose of which was increased during her pregnancy.
On breast examination, bilateral milky discharge is expressed. There are no palpable masses, skin changes, or axillary lymphadenopathy. The remainder of the physical examination is normal.
Laboratory results are as follows:
 Urine pregnancy test is negative.
Which of the following is the most appropriate next step in management of this patient?
Urine pregnancy test is negative.
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.8/5 (94)
(94) An 84-year-old nursing home resident with mild dementia is evaluated for acute onset of vomiting. She has had 6 episodes since this morning and "cannot keep anything down." She also reports an episode of watery diarrhea, muscle pains, and a mild headache. Six residents of her nursing home have had similar symptoms over the last week.
The patient's temperature is 38.1 C (100.6 F). Mucous membranes are dry. Abdominal examination shows no tenderness. The rest of the examination is unremarkable. Stool culture is negative.
Which of the following is the most likely cause of this patient's symptoms?
(Multiple Choice)
5.0/5 (73)
(73) A 67-year-old man comes to the office for a preventive examination. He feels well and has no concerns aside from occasional pain in his knees. Medical history is significant for hypertension and osteoarthritis, for which he takes chlorthalidone, lisinopril, and, occasionally, acetaminophen. The patient has a 20-pack-year smoking history but quit 25 years ago. His last colonoscopy 4 years ago was unremarkable. He does not drink alcohol. He is a retired plumber and lives with his wife in a retirement community.
Vital signs and physical examination show no abnormalities.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.7/5 (71)
(71) A 54-year-old woman comes to the office due to lower extremity swelling and discomfort over the past week. The patient says that she can no longer fit into her shoes. Otherwise, she feels fine and has no orthopnea, dyspnea on exertion, or chest pain. She was recently diagnosed with essential hypertension (systolic blood pressure 165-170 mm Hg and diastolic blood pressure 95-100 mm Hg) and was started on amlodipine. Complete blood count and chemistry panel were normal at that time.
The patient's current blood pressure is 156/95 mm Hg, pulse is 84/min, and respirations are 14/min. Pulse oximetry is 98% on room air. Her BMI is 28 kg/m2. Jugular venous pressure is estimated at 8 cm H2O. Lungs are clear to auscultation. There are no murmurs or additional heart sounds. The liver span is 10 cm and the spleen is not palpable. There is 2+ symmetric pitting edema involving her lower extremities.
Laboratory results are as follows:
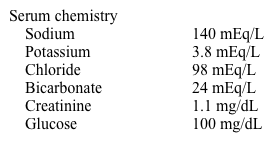 Which of the following therapies, if it had been initiated with amlodipine, could have most likely prevented this patient's current condition?
 (Multiple Choice)
4.8/5 (71)
(71) A 72 year-old man with a history of very severe chronic obstructive pulmonary disease (COPD) has increasing dyspnea that initially occurred only with exertion but has become present at rest over the last few years. He has a chronic cough with scant sputum production, which has not changed. The patient has not recently required hospitalization or other acute treatment for COPD exacerbations. He uses supplemental oxygen continuously. Medications include tiotropium, fluticasone/salmeterol, and theophylline. He also uses an albuterol rescue inhaler occasionally, but it provides very little relief. He quit smoking 4 years ago.
Respiratory rate is 20/min and pulse is 94/min. SaO2 is 92% on oxygen at 3 L/min. Physical examination shows cachexia and pursed lip breathing. There is decreased air entry bilaterally with no wheezes.
Chest x-ray reveals hyperinflation. Forced expiratory volume in 1 second (FEV1) is 19% predicted, forced vital capacity (FVC) is 56% predicted, and FEV1/FVC is 0.43.
Which of the following therapies should be considered in this patient?
(Multiple Choice)
4.7/5 (97)
(97) A 55-year-old man comes to the office due to the sudden onset 4 months ago of inability to maintain a firm erection. He is still interested in sex but feels guilty that he is disappointing his wife and ruining his marriage. The patient awakens with a normal erection but cannot maintain it to engage in intercourse. He has intermittent knee pain, decreased appetite, constipation, insomnia, and low energy. The patient has a history of hypercholesterolemia, hypertension, and type 2 diabetes mellitus. Medications include aspirin, metformin, atorvastatin, and lisinopril, which he has taken for the past 5 years. He denies any alcohol or substance abuse, except for smoking a pack of cigarettes daily for 20 years, which he stopped 5 years ago.
Temperature is 36.7 C (98.1 F), blood pressure is 130/80 mm Hg, pulse is 70/min, and respirations are 16/min. BMI is 28 kg/m2. Physical examination is normal. No hepatomegaly is present. The penis and testes appear normal, and there are no palpable masses. Neurologic examination is within normal limits.
Complete blood count and chemistries are normal. Hemoglobin A1c is 7.3%. TSH is 3 µU/mL, alanine aminotransferase is 24 U/L, and aspartate aminotransferase is 37 U/L.
Which of the following is the most likely cause of this patient's erectile dysfunction?
(Multiple Choice)
4.9/5 (81)
(81) A 24-year-old woman comes to the physician with joint pain and malaise for the past 2 weeks. She had pain in her right wrist and elbow initially, but now it involves primarily the right knee. Yesterday, she noted a red bump on her finger. She lives in Connecticut. The patient has no medical problems and takes no medications. She does not use tobacco, alcohol, or illicit drugs. She lives alone and has had a boyfriend for the past 2 years. Her last menstrual period was 2 weeks ago. Her mother suffers from hypertension and arthritis.
The patient's temperature is 38.1° C (100.6° F), blood pressure is 105/85 mm Hg, and pulse is 99/min. Physical examination shows no neck masses or lymphadenopathy. There are no cardiac murmurs. The spleen is not enlarged. The right knee is warm and slightly swollen without erythema. Range of motion is unrestricted. There is a pustule on the right index finger but otherwise there are no skin rashes.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (88)
(88) A 65-year-old man comes to the physician because of floaters in his right eye for the past 2 days. He also experienced some brief flashes of light as well as poor vision in the same eye 1 day ago. He has always been nearsighted and has worn glasses since he was a teenager. He has no eye pain or trauma. There is no history of diabetes mellitus.
No obvious abnormalities are detected on funduscopic examination, but an extensive right-sided visual field defect is confirmed by confrontation.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5 (94)
(94) A 26-year-old man comes to the office with a 4-week history of malaise, abdominal pain, and diarrhea. Two days ago, he noticed streaks of blood in his stool. The patient has not traveled recently and has not eaten anything out of the ordinary. He has no prior medical conditions. The patient occasionally drinks alcohol but does not use tobacco or illicit drugs. His father was diagnosed with colon cancer at age 55 and died of metastatic disease 5 years later.
Temperature is 38 C (100.4 F). Abdominal examination reveals tenderness in the periumbilical area and left lower quadrant with no guarding or rebound tenderness. Bowel sounds are increased. Rectal examination shows no hemorrhoids or fissures, but blood-streaked stool is present in the rectal vault.
Stool cultures and testing for infections, including Clostridioides difficile, are negative. Colonoscopy shows edematous, friable mucosa; multiple ulcerations; and exudates involving the entire colon. Biopsies reveal mononuclear cell infiltrates, cryptitis, and crypt abscesses.
Medical therapy is started. A follow-up colonoscopy 8 weeks later shows minimal mucosal edema but is otherwise unremarkable.
Which of the following is the best recommendation regarding colorectal cancer screening in this patient?
(Multiple Choice)
4.8/5 (89)
(89) A 67-year-old man comes to the physician because of vague abdominal discomfort over the last several months. He also complains of fatigue but denies constipation, diarrhea, and dysphagia. His other medical problems include hypercholesterolemia, hypertension, and vitamin D deficiency. The patient underwent cholecystectomy at the age of 42 for gallstones. His daily medications include aspirin, simvastatin, valsartan, and vitamin D. The patient is a plumber and specializes in replacing old pipes. He has a sister who was diagnosed with sarcoidosis. He does not use tobacco, alcohol, or drugs.
His temperature is 37.8 C (100 F), blood pressure is 150/80 mm Hg, pulse is 82/min, and respirations are 14/min. His BMI is 24 kg/m2. Cardiopulmonary examination is unremarkable. The liver span is 16 cm and the liver edge feels firm on palpation. The tip of the spleen is palpated on deep inspiration.
Laboratory studies reveal:
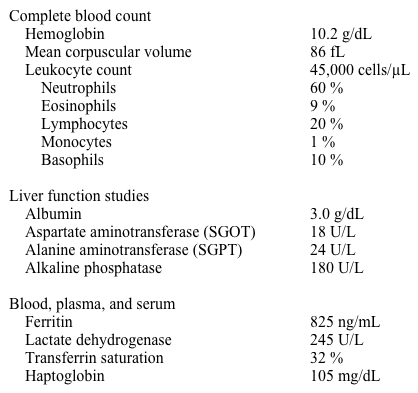 No inclusion bodies are seen in the red or white cells on the peripheral smear.
Which of the following is most likely to establish this patient's diagnosis?
No inclusion bodies are seen in the red or white cells on the peripheral smear.
Which of the following is most likely to establish this patient's diagnosis? (Multiple Choice)
4.7/5 (77)
(77) A 45-year-old man comes to the emergency department due to shortness of breath. His symptoms began when he woke up today and have not diminished since. The patient also reports mild chest pressure but has no cough, fever, wheezing, or chest pain. He was diagnosed with idiopathic membranous nephropathy 6 months ago during evaluation of anasarca, and cyclophosphamide and prednisone therapy were begun due to persistent heavy proteinuria. The patient is a lifelong nonsmoker and does not use alcohol or illicit drugs.
Temperature is 37.2 C (99.0 F), blood pressure is 144/84 mm Hg, pulse is 112/min and regular, and respirations are 18/min. Oxygen saturation is 91% while breathing ambient air. There is no jugular venous distension. The lungs are clear on auscultation, and cardiac examination shows no abnormalities with the exception of tachycardia. The patient has 2+ bilateral, lower extremity pitting edema. There is no calf tenderness.
Laboratory results are as follows:
 ECG shows sinus tachycardia with nonspecific ST-T changes.
Which of the following conditions is most likely associated with this patient's current symptoms?
ECG shows sinus tachycardia with nonspecific ST-T changes.
Which of the following conditions is most likely associated with this patient's current symptoms? (Multiple Choice)
4.9/5 (71)
(71) A 68-year-old man with a past medical history of hypertension and active smoking comes to the physician with complaints of daily sputum production, cough, and dyspnea. His dyspnea has progressed over the past 2 years so that he becomes dyspneic walking 2 blocks and up 1 flight of stairs. The patient uses albuterol/ipratropium 4 times daily. He has a 40-pack-year smoking history.
His blood pressure is 140/80 mm Hg, pulse is 100/min, and respirations are 18/min. Pulse oximetry shows 88% on room air. Estimated jugular venous pressure is 9 cm H2O. Examination shows a barrel-shaped chest. There is a split S2 with a holosystolic murmur heard at the left sternal border. Lung examination shows decreased air entry and slow expiratory phase in all lung fields. There is 1+ bilateral pitting edema in the lower extremities midway to the knees.
Pulmonary function testing shows the following:
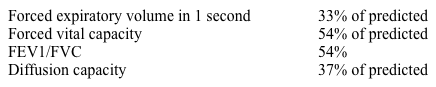 Chest x-ray shows hyperinflation of the lungs.
Pulmonary rehabilitation is most likely to result in which of the following in this patient?
Chest x-ray shows hyperinflation of the lungs.
Pulmonary rehabilitation is most likely to result in which of the following in this patient? (Multiple Choice)
4.9/5 (72)
(72) A 69-year-old man with a history of coronary artery disease comes to the office with chest pain on moderate exertion. Over the last year, he has experienced pressure-like chest pain when walking at a fast pace or climbing stairs. He thinks this affects his quality of life as he has to stop to rest and take sublingual nitroglycerin each time. The patient has no shortness of breath, lightheadedness, syncope, or lower extremity swelling. He underwent coronary artery bypass surgery 8 years ago and has had 2 percutaneous coronary interventions over the last 2 years. Current medications include metoprolol succinate, amlodipine, lisinopril, extended-release isosorbide mononitrate, aspirin, clopidogrel, high-intensity rosuvastatin, and sublingual nitroglycerin as needed. He stopped smoking 10 years ago and does not drink alcohol.
Blood pressure is 105/65 mm Hg and pulse is 55/min. The lungs are clear on auscultation. ECG shows normal sinus rhythm with T-wave inversion in leads III and aVF and a QTc interval of 410 msec. His last serum creatinine was 0.8 mg/dL and LDL cholesterol level was 68 mg/dL. Echocardiogram shows apical hypokinesis with left ventricular ejection fraction of 55%. Myocardial perfusion imaging reveals moderate ischemia of the inferior wall. Coronary angiography shows no intervenable lesions.
Which of the following is the best next step in management of this patient's symptoms?
(Multiple Choice)
4.8/5 (77)
(77) A 33-year-old man comes to the office for a routine follow-up visit. He was recently treated for esophageal achalasia with a pneumatic dilation. He reports a significant improvement in symptoms of dysphagia and nocturnal regurgitation. His past medical history is also significant for borderline hypertension and an anxiety disorder. He is an ex-smoker with a 5 pack-year smoking history. His mother suffered from Sjogren's disease and lymphoma. His medications include omeprazole and clonazepam.
His blood pressure is 135/85 mmHg and his pulse is 67/min. His BMI is 30 kg/m2. His physical examination is otherwise unremarkable.
Over the next 10 years, the patient is at the highest risk for which of the following?
(Multiple Choice)
4.7/5 (67)
(67) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)